
基本信息
- 标准SMILES
CC[C@H](C)C(=O)O[C@H]1C[C@@H](C)C=C2C=C[C@H](C)[C@H](CC[C@@H]3C[C@@H](O)CC(=O)O3)[C@H]21- InChIKey
PCZOHLXUXFIOCF-BXMDZJJMSA-N- 分子式
- C24H36O5
- 平均分子量
- 404.5 g/mol
- 单同位素质量
- 404.25627425
概述
Lovastatin can cause developmental toxicity according to state or federal government labeling requirements.
名称与标识
- 首选名称
- Lovastatin
- IUPAC
- [(1S,3R,7S,8S,8aR)-8-[2-[(2R,4R)-4-hydroxy-6-oxooxan-2-yl]ethyl]-3,7-dimethyl-1,2,3,7,8,8a-hexahydronaphthalen-1-yl] (2S)-2-methylbutanoate
- 中文名
- 洛伐他汀
- 英文名
- Lovastatin
- 分子式
- C24H36O5
- 分子量
- 404.54
名称与别名
lovastatin75330-75-5mevinolinMevacorMevinacorAltoprevMevlorSivlorAltocorMK-803Monacolin KLovastatine
展开更多名称
他汀美降脂脉温宁乐瓦停洛伐他丁洛伐它丁洛伐他汀洛伐司他汀汀洛伐他丁莫拉克林KLOVASTATIONLovastatin (Mevacor)Lovastatin,Monacolin Kmsd803LOVALIP
6alpha-MethylcompactinLovastatinaLovastatinum [Latin]6-alpha-MethylcompactinLovastatinumMK 803DTXSID50207849LHU78OQFD
数据库标识
- CAS
75330-75-5- PubChem CID
- 53232
- DTXSID
DTXSID5020784- ChEMBL
CHEMBL152032、CHEMBL503- ChEBI
CHEBI:40303- UNII
- 9LHU78OQFD
- EC Number
- 616-212-7、692-955-0、946-962-3
- Nikkaji
- J22.276C
性质
结构计算性质
- XLogP
- 4.3
- 极性表面积
- 72.8 Ų
- 氢键供体
- 1
- 氢键受体
- 5
- 可旋转键
- 7
- 重原子
- 29
- 形式电荷
- 0
- 复杂度
- 666
实验与物化性质
Drugs
Pharmaceuticals -> Antilipidemics
Pharmaceuticals -> Statins
Pharmaceutical
Pharmaceuticals -> Listed in ZINC15
LogP
log Kow = 4.26
4.5
4.04
Color/Form
White crystals
White crystals from acetone aqueous
A white, non-hygroscopic crystalline powder
Solubility
In water, 0.4X10⁻³ mg/mL at 25 °C
Insoluble in water
Solubility at 25 °C (mg/mL): acetone 47, acetonitrile 28, n-butanol 7, iso-butanol 14, chloroform 350, N,N-dimethylformamide 90, ethanol 16, methanol 28, n-octanol 2, n-propanol 11, iso-propanol 20
Practically insoluble in hexane
Very soluble in chloroform; soluble in dimethyl formamide; slightly soluble in acetone, ethanol
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anticholesteremic Agents; Hydroxymethylglutaryl-CoA Reductase Inhibitors; Hypolipidemic Agents
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Lipid-lowering agents
Endocrine DisruptorsPotential endocrine disrupting compound
Melting Point
179 °C
MP: 174.5 °C (under nitrogen)
174.5 °C
Optical RotationSpecific optical rotation at 25 °C for D (sodium) line: +323 deg (c = 0.5 g in 100 ml acetonitrile)
Physical DescriptionSolid
Stability/Shelf Life
Stable under recommended storage conditions.
Lovastatin tablets should be stored in well-closed, light-resistant containers at 5-30 °C. When stored under these conditions, the tablets are stable for 24 months after the date of manufacture. Lovastatin is sensitive to light. Following exposure to extreme light conditions, the drug is stable for 24 hours or 1 month when exposed to UV (approximately 3230 lux) or fluorescent (approximately 10,764 lux) light, respectively, at 28 °C in air.
Dissociation Constants13.49
物理化学性质
- 熔点
- 175 °C · 175°C
- 比旋光度
- 25 · D25 +323° (c = 0.5 g in 100 ml acetonitrile)
- 沸点
- 559.2 · 559.2±50.0 °C(Predicted)
- 密度
- 1.12 · 1.12±0.1 g/cm3(Predicted)
- 蒸气压
- 0 Pa · 0Pa at 25℃
- 折射率
- 320 ° · 320 ° (C=0.5, CH3CN)
- 储存条件
- -20 °C · -20°C
- 溶解度
- 9.8 · ethanol: soluble9.80-10.20mg/mL, clear, colorless to faintly yellow
- 形态
- White to off-white powder
- 酸度系数(pKa)
- 13.49 · 13.49±0.40(Predicted)
- 颜色
- White
- 水溶解性
- 0.0004 mg/mL · 0.0004 mg/mL at 25 ºC
- Merck
- 14 · 14,5586
- BCS Class
- 2 · 2
- 稳定性
- 2 years · Stable for 2 years from date of purchase as supplied. Solutions in DMSO or ethanol may be stored at -20°C for up to 2 months.
- InChIKey
- PCZOHLXUXFIOCF-BXMDZJJMSA-N
- SMILES
- [H][C@]12[C@H](C[C@@H](C)C=C1C=C[C@H](C)[C@@H]2CC[C@@H]3C[C@@H](O)CC(=O)O3)OC(=O)[C@@H](C)CC
- LogP
- 4.26 · 4.260
- CAS 数据库
- 75330 · 75330-75-5(CAS DataBase Reference)
- EPA化学物质信息
- Lovastatin (75330-75-5)
化学性质
白色结晶,熔点174.5℃(氮气中)。[α]D25+323°(C=0.5g溶于100ml乙腈)。UV最大吸收(甲醇):229,237,246nm(耳三550,6250,430)。室温溶解度(mg/m1):丙酮47,乙腈28,n-丁醇7,i-丁醇14,氯仿350,二甲基甲酰胺90,乙醇16,甲醇28,n-辛醇2,n-丙醇11,i-丙醇20,水0.4×10-3。急性毒性LD50小鼠(mg/kg):>1000口服。
安全与法规
GHS分类
GHS Classification
This chemical does not meet GHS hazard criteria for 0.4% (1 of 247) of reports.
Danger
H302 (19%): Harmful if swallowed [Warning Acute toxicity, oral]
P203, P260, P261, P264, P270, P272, P280, P301+P317, P302+P352, P318, P319, P321, P330, P333+P317, P362+P364, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 247 reports by companies from 18 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Warning
危害信息
Regulatory Information
Hazard Traits - Developmental Toxicity
Regulation (EC) No 178/2002 (amended)
Status: Active Update: 03-09-2012 https://echa.europa.eu/registration-dossier/-/registered-dossier/10864
Butanoic acid, 2-methyl-, (1S,3R,7S,8S,8aR)-1,2,3,7,8,8a-hexahydro-3,7-dimethyl-8-2-(2R,4R)-tetrahydro-4-hydroxy-6-oxo-2H-pyran-2-ylethyl-1-naphthalenyl ester, (2S)-: Does not have an individual approval but may be used as a component in a product covered by a group standard. It is not approved for use as a chemical in its own right.
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including lovastatin, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Toxic Combustion ProductsSpecial hazards arising from the substance or mixture: Carbon oxides.
Hazard Classes and Categories
Acute Tox. 4 (19%)
Acute Tox. 4 (100%)
Hazardous Reactivities and IncompatibilitiesIncompatible materials: Strong oxidizing agents.
安全与防护
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide.
Advice for firefighters: Wear self contained breathing apparatus for fire fighting if necessary.
Storage Conditions
Keep container tightly closed in a dry and well-ventilated place. Recommended storage temperature: 2 - 8 °C.
Store at 20 deg to 25 °C (68 deg to 77 °F). Lovastatin Tablets USP must be protected from light.
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Use personal protective equipment. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Avoid breathing dust. Environmental precautions: Do not let product enter drains. Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company; Contaminated packaging: Dispose of as unused product.
Preventive Measures
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Use personal protective equipment. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Avoid breathing dust. Environmental precautions: Do not let product enter drains.
Precautions for safe handling: Avoid contact with skin and eyes. Avoid formation of dust and aerosols. Provide appropriate exhaust ventilation at places where dust is formed.
Appropriate engineering controls: Handle in accordance with good industrial hygiene and safety practice. Wash hands before breaks and at the end of workday.
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands.
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Personal Protective Equipment (PPE)
Eye/face protection: Safety glasses with side-shields conforming to EN166. Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU).
Skin protection: Handle with gloves.
Body Protection: Complete suit protecting against chemicals. The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace.
Respiratory protection: For nuisance exposures use type P95 (US) or type P1 (EU EN 143) particle respirator. For higher level protection use type OV/AG/P99 (US) or type ABEK-P2 (EU EN 143) respirator cartridges. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU).
毒理信息
Interactions
... A 60-year-old black man developed rhabdomyolysis after receiving lovastatin for 14 months. Rhabdomyolysis developed in the absence of other medications previously reported to cause this adverse effect when administered concomitantly with lovastatin. Adverse drug reaction causality algorithms categorized this reaction as either possible or probable. Rhabdomyolysis is an uncommon adverse effect associated with lovastatin therapy. Although reported cases of lovastatin-induced rhabdomyolysis were associated with the coadministration of cyclosporine, erythromycin, gemfibrozil, or nicotinic acid, this adverse effect may occur in the absence of these agents.
Combined drug therapy should be approached with caution as information from controlled studies is limited. Based on post-marketing surveillance, gemfibrozil, other fibrates and lipid lowering doses of niacin (nicotinic acid) may increase the risk of myopathy when given concomitantly with HMG-CoA reductase inhibitors, probably because they can produce myopathy when given alone. Therefore, combined drug therapy should be approached with caution.
Grapefruit juice contains one or more components that inhibit CYP3A4 and can increase the plasma levels of drugs metabolized by CYP3A4. The effect of typical consumption (one 250-ml glass daily) is minimal (34% increase in active plasma HMG-CoA reductase inhibitory activity as measured by the area under the concentration-time curve) and of no clinical relevance. However, because larger quantities (over 1 liter daily) significantly increase the plasma levels of HMG-CoA reductase inhibitory activity, grapefruit juice should be avoided during lovastatin therapy.
Lovastatin, like several other inhibitors of HMG-CoA reductase, is a substrate of cytochrome P450 3A4 (CYP3A4). Certain drugs which inhibit this metabolic pathway can raise the plasma levels of lovastatin and may increase the risk of myopathy. These include itraconazole, ketoconazole, posaconazole, voriconazole, the macrolide antibiotics erythromycin and clarithromycin, the ketolide antibiotic telithromycin, HIV protease inhibitors, boceprevir, telaprevir, the antidepressant nefazodone, or cobicistat-containing products. Combination of these drugs with lovastatin is contraindicated. If short-term treatment with strong CYP3A4 inhibitors is unavoidable, therapy with lovastatin should be suspended during the course of treatment
For more Interactions (Complete) data for Lovastatin (20 total), please visit the HSDB record page.
Hepatotoxicity
Lovastatin therapy is associated with mild, asymptomatic and usually transient serum aminotransferase elevations. In summary analyses of large scale studies with prospective monitoring, ALT elevations above normal occurred in 3% to 5% of patients, but were above 3 times the upper limit of normal (ULN) in only 0.4% compared to 0.1% of placebo recipients. These elevations were more common with higher doses of lovastatin, being greater than 3 times ULN in 0.1% of patients receiving 20 mg daily, 0.9% with 40 mg and 1.5% with 80 mg daily. Most of these elevations were self-limited and did not require dose modification, although discontinuation is recommended for any elevation above 10 times and for persistent elevations above 5 times the ULN. Lovastatin is also associated with frank, clinically apparent hepatic injury, but cases are rare. The onset of clinical injury ranges from a few weeks to several years. The pattern of injury is typically cholestatic, but can be hepatocellular. Rash, fever and eosinophilia are uncommon as are autoimmune features. The injury usually resolves rapidly upon stopping lovastatin, but instances of fatal acute liver failure and of prolonged cholestasis have been reported (Case 1).
Ecotoxicity ValuesEC50; Species: Xenopus laevis (African Clawed Frog) blastula; Conditions: freshwater, renewal, 23 °C, pH 6.5-9, hardness 16-400 mg/L CaCO3; Concentration: 20500 ug/L for 96 hr; Effect: development, increased deformation /98% purity/
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 7400(SRC), determined from a structure estimation method(2), indicates that lovastatin is expected to be immobile in soil(SRC). Volatilization of lovastatin from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 2.1X10⁻¹⁰ atm-cu m/mole(SRC), using a fragment constant estimation method(3). Lovastatin is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 2.2X10⁻¹² mm Hg at 25 °C(SRC), determined from a fragment constant method(2). Biodegradation data in soil were not available(SRC, 2016).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 7400(SRC), determined from a structure estimation method(2), indicates that lovastatin is expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(3) based upon an estimated Henry's Law constant of 2.1X10⁻¹⁰ atm-cu m/mole(SRC), developed using a fragment constant estimation method(4). According to a classification scheme(5), an estimated BCF of 300(SRC), from its log Kow of 4.26(6) and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is high(SRC). Biodegradation data in water were not available(SRC, 2016).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), lovastatin, which has an estimated vapor pressure of 2.2X10⁻¹² mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase lovastatin may be removed from the air by wet and dry deposition(SRC). Lovastatin contains chromophores that absorb UV light at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Adverse EffectsLovastatin is generally well tolerated with mild and transient adverse reactions. There are few reported cases of severe adverse effects associated with lovastatin. Below are the reported side effects of the drug:
Exposure Routes
Studies suggest that <5% of the oral dose reaches the general circulation as active inhibitors. Time to peak serum concentration is 2-4 hours. Lovastatin undergoes extensive first-pass metabolism so the availability of the drug in the system is low and variable.
Toxicity Summary
IDENTIFICATION AND USE: Lovastatin is a white, non-hygroscopic crystalline powder. It is used for therapy as anticholesteremic agent, and Hydroxymethylglutaryl-CoA (HMG-CoA) reductase inhibitor. HUMAN EXPOSURE AND TOXICITY: Lovastatin, like other inhibitors of HMG-CoA reductase, occasionally causes myopathy manifested as muscle pain, tenderness or weakness with creatine kinase above ten times the upper limit of normal. Myopathy sometimes takes the form of rhabdomyolysis with or without acute renal failure secondary to myoglobinuria, and rare fatalities have occurred. The risk of myopathy is increased by high levels of HMG-CoA reductase inhibitory activity in plasma. There have been rare postmarketing reports of fatal and non-fatal hepatic failure in patients taking statins, including lovastatin. Treatment of HL-60 cells with lovastatin induced characteristic apoptosis in a dose-dependent manner. ANIMAL STUDIES: Lovastatin produced optic nerve degeneration (Wallerian degeneration of retinogeniculate fibers) in clinically normal dogs in a dose-dependent fashion starting at 60 mg/kg/day. Vestibulocochlear Wallerian-like degeneration and retinal ganglion cell chromatolysis were also seen in dogs treated for 14 weeks at 180 mg/kg/day. CNS vascular lesions, characterized by perivascular hemorrhage and edema, mononuclear cell infiltration of perivascular spaces, perivascular fibrin deposits and necrosis of small vessels, were seen in dogs treated with lovastatin at a dose of 180 mg/kg/day. In mice given oral lovastatin dosages of 100 or 500 mg/kg daily, an increase in the incidence of papilloma in the nonglandular mucosa of the stomach was observed. Since the glandular mucosa of the stomach in these rodents was not affected and the human stomach contains only glandular mucosa, the importance of this finding to humans is unclear. An increased incidence of hepatocellular carcinoma and adenoma was observed after 21 months in mice given oral lovastatin 500 mg/kg daily. Drug-related testicular atrophy, decreased spermatogenesis, spermatocytic degeneration and giant cell formation were seen in dogs starting at 20 mg/kg/day. Direct dosing of neonatal rats by subcutaneous injection with 10 mg/kg/day of the open hydroxyacid form of lovastatin resulted in delayed passive avoidance learning in female rats. Lovastatin has been shown to produce skeletal malformations in offspring of pregnant mice and rats dosed during gestation at 80 mg/kg/day. Lovastatin did not exhibit mutagenic potential in in vitro mammalian cell systems (rat or mouse hepatocytes, V-79 cell forward mutation study), in vitro (Chinese hamster ovary cell) or in vivo (mouse bone marrow) chromosomal aberration studies, or microbial (Ames test) systems with or without metabolic activation. There is some in vitro evidence, however, that inhibition of HMG-CoA reductase can inhibit DNA synthesis during the S phase of the cell life cycle; this inhibition appears to result from depletion of mevalonic acid and is independent of its conversion to cholesterol.
Researchers gave a single 200 mg dose of lovastatin to 5 healthy volunteers, and no clinically significant adverse effects were reported. Cases of lovastatin overdose are reported, but none of the patients reported any specific symptoms. All the patients recovered without complications. The patient should discontinue lovastatin use if severe muscle symptoms or fatigue develop. CPK, creatinine, and urinalysis should be done to assess for myoglobinuria. Mild to moderate muscle symptoms should also call for discontinuation of lovastatin, pending a thorough investigation of symptoms.
Lovastatin is structurally similar to the HMG, a substituent of the endogenous substrate of HMG-CoA reductase. Lovastatin is a prodrug that is activated <i>in vivo</i> via hydrolysis of the lactone ring to form the ‘_-hydroxyacid. The hydrolyzed lactone ring mimics the tetrahedral intermediate produced by the reductase allowing the agent to bind to HMG-CoA reductase with 20,000 times greater affinity than its natural substrate. The bicyclic portion of lovastatin binds to the coenzyme A portion of the active site.
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of December 8, 2016: http://actor.epa.gov/dashboard/]
Soil Adsorption/Mobility
Using a structure estimation method based on molecular connectivity indices(1), the Koc of lovastatin can be estimated to be 7400(SRC). According to a classification scheme(2), this estimated Koc value suggests that lovastatin is expected to be immobile in soil.
Natural Pollution Sources
Lovastatin has been isolated from Monascus ruber and Apergillus terreus(1), via fermentation(2,3). It can also obtained from the fungus Pleurotus ostreatus(4,5). Lovastatin is found in some red yeast rice products; red yeast rice is used as food in Chinese cuisine(6).
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ Five healthy human volunteers have received up to 200 mg of lovastatin as a single dose without clinically significant adverse experiences.
/SIGNS AND SYMPTOMS/ Lovastatin, like other inhibitors of HMG-CoA reductase, occasionally causes myopathy manifested as muscle pain, tenderness or weakness with creatine kinase (CK) above ten times the upper limit of normal (ULN). Myopathy sometimes takes the form of rhabdomyolysis with or without acute renal failure secondary to myoglobinuria, and rare fatalities have occurred. The risk of myopathy is increased by high levels of HMG-CoA reductase inhibitory activity in plasma.
/SIGNS AND SYMPTOMS/ There have been rare postmarketing reports of fatal and non-fatal hepatic failure in patients taking statins, including lovastatin. If serious liver injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs during treatment with lovastatin, promptly interrupt therapy. If an alternate etiology is not found, do not restart lovastatin.
/CASE REPORTS/ ... A 60-year-old black man developed rhabdomyolysis after receiving lovastatin for 14 months. Rhabdomyolysis developed in the absence of other medications previously reported to cause this adverse effect when administered concomitantly with lovastatin. Adverse drug reaction causality algorithms categorized this reaction as either possible or probable. Rhabdomyolysis is an uncommon adverse effect associated with lovastatin therapy. Although reported cases of lovastatin-induced rhabdomyolysis were associated with the coadministration of cyclosporine, erythromycin, gemfibrozil, or nicotinic acid, this adverse effect may occur in the absence of these agents.
For more Human Toxicity Excerpts (Complete) data for Lovastatin (20 total), please visit the HSDB record page.
Artificial Pollution SourcesLovastatin's production and administration as a hypercholesterolemic drug(1) may result in its release to the environment through various waste streams(SRC).
法规信息
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including lovastatin, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
安全数据
- wgk
- 3
- 毒性
- LD50 orally in mice: >1000 mg/kg (Endo)
- RTECS号
- EK7907000
- 包装类别
- III
- 危险等级
- 9
- 存储类别
- 11 - Combustible Solids
- 安全说明
- 22-24/25-36/37/39-26
- 海关编码
- 29322090
- 危险品标志
- Xi
- 危险性类别
- Carc. 2Repr. 2
- 危险类别码
- 36/37/38
- 毒害物质数据
- 75330-75-5(Hazardous Substances Data)
- 危险品运输编号
- 3077
化学与工业
药理信息
ATC Code
C - Cardiovascular system
QC - Cardiovascular system
Protein BindingBoth lovastatin and its β-hydroxy acid metabolite are highly bound (>95%) to human plasma proteins, largely due to its lipophilicity. Animal studies demonstrated that lovastatin crosses the blood-brain and placental barriers.
Pharmacodynamics
Lovastatin is an oral antilipemic agent which reversibly inhibits HMG-CoA reductase. It is used to lower total cholesterol, low density lipoprotein-cholesterol (LDL-C), apolipoprotein B (apoB), non-high density lipoprotein-cholesterol (non-HDL-C), and trigleride (TG) plasma concentrations while increasing HDL-C concentrations. High LDL-C, low HDL-C and high TG concentrations in the plasma are associated with increased risk of atherosclerosis and cardiovascular disease. The total cholesterol to HDL-C ratio is a strong predictor of coronary artery disease and high ratios are associated with higher risk of disease. Increased levels of HDL-C are associated with lower cardiovascular risk. By decreasing LDL-C and TG and increasing HDL-C, lovastatin reduces the risk of cardiovascular morbidity and mortality. Elevated cholesterol levels, and in particular, elevated low-density lipoprotein (LDL) levels, are an important risk factor for the development of CVD. Use of statins to target and reduce LDL levels has been shown in a number of landmark studies to significantly reduce the risk of development of CVD and all-cause mortality. Statins are considered a cost-effective treatment option for CVD due to their evidence of reducing all-cause mortality including fatal and non-fatal CVD as well as the need for surgical revascularization or angioplasty following a heart attack. Evidence has shown that even for low-risk individuals (with <10% risk of a major vascular event occurring within 5 years) statins cause a 20%-22% relative reduction in major cardiovascular events (heart attack, stroke, coronary revascularization, and coronary death) for every 1 mmol/L reduction in LDL without any significant side effects or risks. Clinical studies have shown that lovastatin reduces LDL-C and total cholesterol by 25-40%. The 50% inhibitory dose is known to be of 46 mcg/kg which is translated into a reduction of approximately 30% of plasma cholesterol. **Myopathy/Rhabdomyolysis** Lovastatin, like other inhibitors of HMG-CoA reductase, occasionally causes myopathy manifested as muscle pain, tenderness or weakness with creatine kinase (CK) above ten times the upper limit of normal (ULN). Myopathy sometimes takes the form of rhabdomyolysis with or without acute renal failure secondary to myoglobinuria, and rare fatalities have occurred. The risk of myopathy is dose-related and is increased by high levels of HMG-CoA reductase inhibitory activity in plasma. In a clinical study (EXCEL) in which patients were carefully monitored and some interacting drugs were excluded, there was one case of myopathy among 4933 patients randomized to lovastatin 20 to 40 mg daily for 48 weeks, and 4 among 1649 patients randomized to 80 mg daily. Predisposing factors for myopathy include advanced age (≥65 years), female gender, uncontrolled hypothyroidism, and renal impairment. Chinese patients may also be at increased risk for myopathy. In most cases, muscle symptoms and CK increases resolved when treatment was promptly discontinued. The risk of myopathy during treatment with lovastatin may be increased with concurrent administration of interacting drugs such as [fenofibrate], [niacin], [gemfibrozil], [cyclosporine], and strong inhibitors of the CYP3A4 enzyme. Cases of myopathy, including rhabdomyolysis, have been reported with HMG-CoA reductase inhibitors coadministered with [colchicine], and caution should therefore be exercised when prescribing these two medications together. Real-world data from observational studies has suggested that 10-15% of people taking statins may experience muscle aches at some point during treatment. **Liver Dysfunction** Persistent increases (to more than 3 times the upper limit of normal) in serum transaminases occurred in 1.9% of adult patients who received lovastatin for at least one year in early clinical trials. When the drug was interrupted or discontinued in these patients, the transaminase levels usually fell slowly to pretreatment levels. The increases usually appeared 3 to 12 months after the start of therapy with lovastatin, and were not associated with jaundice or other clinical signs or symptoms. In the EXCEL study, the incidence of persistent increases in serum transaminases over 48 weeks was 0.1% for placebo, 0.1% at 20 mg/day, 0.9% at 40 mg/day, and 1.5% at 80 mg/day in patients on lovastatin. However, in post-marketing experience with lovastatin, symptomatic liver disease has been reported rarely at all dosages.
Mechanism of Action
Lovastatin is a lactone which is readily hydrolyzed _in vivo_ to the corresponding β-hydroxyacid and strong inhibitor of HMG-CoA reductase, a hepatic microsomal enzyme which catalyzes the conversion of HMG-CoA (3-hydroxy-3-methylglutaryl-coenzyme A ) to mevalonate, an early rate-limiting step in cholesterol biosynthesis. At therapeutic lovastatin doses, HMG-CoA reductase is not completely blocked, thereby allowing biologically necessary amounts of mevalonate to be available. Because the conversion of HMG-CoA to mevalonate is an early step in the biosynthetic pathway for cholesterol, therapy with lovastatin would not be expected to cause an accumulation of potentially toxic sterols. Lovastatin acts primarily in the liver, where decreased hepatic cholesterol concentrations stimulate the upregulation of hepatic low density lipoprotein (LDL) receptors which increase hepatic uptake of LDL. Lovastatin also inhibits hepatic synthesis of very low density lipoprotein (VLDL). The overall effect is a decrease in plasma LDL and VLDL and a significant reduction in the risk of development of CVD and all-cause mortality. A significant effect on LDL-C reduction was seen within 2 weeks of initiation of lovastatin, and the maximum therapeutic response occurred within 4-6 weeks. The response was maintained during continuation of therapy. Single daily doses given in the evening were more effective than the same dose given in the morning, perhaps because cholesterol is synthesized mainly at night. When therapy with lovastatin is stopped, total cholesterol has been shown to return to pre-treatment levels. In vitro and in vivo animal studies also demonstrate that lovastatin exerts vasculoprotective effects independent of its lipid-lowering properties, also known as the pleiotropic effects of statins. This includes improvement in endothelial function, enhanced stability of atherosclerotic plaques, reduced oxidative stress and inflammation, and inhibition of the thrombogenic response. Statins have also been found to bind allosterically to β2 integrin function-associated antigen-1 (LFA-1), which plays an important role in leukocyte trafficking and in T cell activation. Lovastatin has been reported to have beneficial effects on certain cancers. This includes a multi-factorial stress-triggered cell death (apoptosis) and DNA degradation response in breast cancer cells. It has also been shown to inhibit histone deacetylase 2 (HDAC2) activity and increase the accumulation of acetylated histone-H3 and the expression of p21(WAF/CIP) in human cancer cells, suggesting that statins might serve as novel HDAC inhibitors for cancer therapy and chemoprevention.
The 3-hydroxy-3-methylglutaryl coenzyme A (HMG-CoA) reductase inhibitors (statins), atorvastatin, cerivastatin, fluvastatin, pravastatin, lovastatin and simvastatin, reduce atherogenesis and cardiovascular morbidity. Besides, there is growing evidence that statins have immunomodulatory activities. Statins downregulate the expression of adhesion molecules, intercellular adhesion molecule-1 (ICAM-1), monocyte chemotactic protein-1 (MAC-1) and lymphocyte function-associated antigen-1 (LFA-1), on leucocytes and endothelial cells and, through binding to LFA-1, interfere with ICAM-1-LFA-1 interaction, which is crucial for activation of lymphocytes by antigen-presenting cells, ingress of leucocytes into the inflammation sites and immunologic cytotoxicity. Statins inhibit the inducible expression of major histocompatibility complex class II in several cell types including macrophages and downregulate the expression of T-helper-1 (Th1) chemokine receptors on T cells, leading further to inhibition of activation of lymphocytes and their infiltration into the inflammation sites. Statins block the induction of inducible nitric oxide synthase and the expression of several proinflammatory cytokines such as tumor necrosis factor-alpha and interferon-gamma in macrophages and possess antioxidant effects. These agents inhibit the proliferation of immunocytes and the activation of natural killer cells.
Lovastatin, is a cholesterol-lowering agent isolated from a strain of Aspergillus terreus. After oral ingestion, lovastatin, which is an inactive lactone, is hydrolyzed to the corresponding beta-hydroxy acid form. This principal metabolite is a specific inhibitor of 3-hydroxy-3- methylglutaryl-coenzyme A (HMG-CoA) reductase. This enzyme catalyzes the conversion of HMG-CoA to mevalonate, which is an early and ratelimiting step in the biosynthesis of cholesterol.
Lovastatin is a member of Statins, which are beneficial in a lot of immunologic cardiovascular diseases and T cell-mediated autoimmune diseases. Kv1.3 channel plays important roles in the activation and proliferation of T cells, and have become attractive target for immune-related disorders. The present study was designed to examine the block effect of Lovastatin on Kv1.3 channel in human T cells, and to clarify its new immunomodulatory mechanism. We found that Lovastatin inhibited Kv1.3 currents in a concentration- and voltage-dependent manner, and the IC50 for peak, end of the pulse was 39.81 +/- 5.11, 6.92 +/- 0.95 uM, respectively. Lovastatin also accelerated the decay rate of current inactivation and negatively shifted the steady-state inactivation curves concentration-dependently, without affecting the activation curve. However, 30 uM Lovastatin had no apparent effect on KCa current in human T cells. Furthermore, Lovastatin inhibited Ca(2+) influx, T cell proliferation as well as IL-2 production. The activities of NFAT1 and NF-kB p65/50 were down-regulated by Lovastatin, too. At last, Mevalonate application only partially reversed the inhibition of Lovastatin on IL-2 secretion, and the siRNA against Kv1.3 also partially reduced this inhibitory effect of Lovastatin. In conclusion, Lovastatin can exert immunodulatory properties through the new mechanism of blocking Kv1.3 channel.
Biological Half-LifeLovastatin half-life is reported to be of 13.37 hours. The elimination half-life of the hydroxy acid form of lovastatin is reported to be of 0.7-3 hours.
Metabolism/Metabolites
Lovastatin is given as a lactone prodrug and thus, in order to produce its mechanism of action, it is required to be converted to the active beta-hydroxy form. This drug activation process does not seem to be related to CYP isoenzyme activity but rather to be controlled by the activity of serum paraoxonase. Lovastatin is metabolized by the microsomal hepatic enzyme system (Cytochrome P-450 isoform 3A4). The major active metabolites present in human plasma are the β-hydroxy acid of lovastatin, its 6'-hydroxy, 6'-hydroxymethyl, and 6'-exomethylene derivatives. The uptake of lovastatin by the liver is enhanced by the activity of OATP1B1.
Lovastatin is metabolized by the microsomal hepatic enzyme system (Cytochrome P-450 isoform 3A4). The major active metabolites present in human plasma are the beta-hydroxy acid of lovastatin, its 6'-hydroxy, 6'-hydroxymethyl, and 6'-exomethylene derivatives.
The major active metabolites present in human plasma are the beta-hydroxyacid of lovastatin, its 6'-hydroxy derivative, and two additional metabolites.
Lovastatin has known human metabolites that include 6'beta-Hydroxylovastatin and 3-Hydroxylovastatin.
Lovastatin is hepatically metabolized in which the major active metabolites are the beta-hydroxyacid of lovastatin, the 6'-hydroxy derivative, and two additional metabolites. Route of Elimination: Lovastatin undergoes extensive first-pass extraction in the liver, its primary site of action, with subsequent excretion of drug equivalents in the bile. 83% of the orally administered dose is excreted in bile and 10% is excreted in urine. Half Life: 5.3 hours
FDA Pharmacological Classification
9LHU78OQFD
LOVASTATIN
Established Pharmacologic Class [EPC] - HMG-CoA Reductase Inhibitor
Mechanisms of Action [MoA] - Hydroxymethylglutaryl-CoA Reductase Inhibitors
Lovastatin is a HMG-CoA Reductase Inhibitor. The mechanism of action of lovastatin is as a Hydroxymethylglutaryl-CoA Reductase Inhibitor.
LOVASTATIN
MeSH Pharmacological Classification
Substances used to lower plasma CHOLESTEROL levels.
Compounds that inhibit HYDROXYMETHYLGLUTARYL COA REDUCTASES. They have been shown to directly lower CHOLESTEROL synthesis.
Absorption, Distribution and Excretion
Lovastatin Cmax was found to be 3.013ng/mL with a Tmax of 3.36 hours. Plasma concentrations of total radioactivity (lovastatin plus 14C-metabolites) peaked at 2 hours and declined rapidly to about 10% of peak by 24 hours postdose. Absorption of lovastatin, estimated relative to an intravenous reference dose, in each of four animal species tested, averaged about 30% of an oral dose. In animal studies, after oral dosing, lovastatin had high selectivity for the liver, where it achieved substantially higher concentrations than in non-target tissues. Lovastatin undergoes extensive first-pass extraction in the liver, its primary site of action, with subsequent excretion of drug equivalents in the bile. As a consequence of extensive hepatic extraction of lovastatin, the availability of drug to the general circulation is low and variable. In a single dose study in four hypercholesterolemic patients, it was estimated that less than 5% of an oral dose of lovastatin reaches the general circulation as active inhibitors. Following administration of lovastatin tablets the coefficient of variation, based on between-subject variability, was approximately 40% for the area under the curve (AUC) of total inhibitory activity in the general circulation. The peak concentrations of lovastatin when a dose of 10-40 mg is administered are reported to range from 1.04-4.03 ng/ml and an AUC of 14-53 ng.h/ml. This indicates that lovastatin presents a dose-dependent pharmacokinetic profile. When lovastatin was given under fasting conditions, plasma concentrations of both active and total inhibitors were on average about two-thirds those found when lovastatin was administered immediately after a standard test meal. Genetic differences in the OATP1B1 (Organic-Anion-Transporting Polypeptide 1B1) hepatic transporter encoded by the SCLCO1B1 gene (Solute Carrier Organic Anion Transporter family member 1B1) have been shown to impact lovastatin pharmacokinetics. Evidence from pharmacogenetic studies of the c.521T>C single nucleotide polymorphism (SNP) showed that lovastatin Cmax and AUC were 340 and 286% higher, respectively, for individuals homozygous for 521CC compared to homozygous 521TT individuals. The 521CC genotype is also associated with a marked increase in the risk of developing myopathy, likely secondary to increased systemic exposure. Other statin drugs impacted by this polymorphism include [rosuvastatin], [pitavastatin], [atorvastatin], [simvastatin], and [pravastatin]. While specific dosage instructions are not included in the available product monographs for lovastatin, individuals with the above-mentioned c.521CC OATP1B1 genotype should be monitored for development of adverse effects from increased exposure to the drug, such as muscle pain and risk of rhabdomyolysis, particularly at higher doses.
Following an oral dose of 14C-labeled lovastatin to man, 10% of the dose was excreted in urine and 83% in feces. The latter represents absorbed drug excreted in bile, together with unabsorbed drug.
Lovastatin is able to cross the blood-brain barrier and placenta.
/MILK/ It is not known whether lovastatin is excreted in human milk.
Following an oral dose of (14)C-labeled lovastatin in man, 10% of the dose was excreted in urine and 83% in feces. The latter represents absorbed drug equivalents excreted in bile, as well as any unabsorbed drug. Plasma concentrations of total radioactivity (lovastatin plus (14)C-metabolites) peaked at 2 hours and declined rapidly to about 10% of peak by 24 hours postdose. Absorption of lovastatin, estimated relative to an intravenous reference dose, in each of four animal species tested, averaged about 30% of an oral dose. In animal studies, after oral dosing, lovastatin had high selectivity for the liver, where it achieved substantially higher concentrations than in non-target tissues. Lovastatin undergoes extensive first-pass extraction in the liver, its primary site of action, with subsequent excretion of drug equivalents in the bile. As a consequence of extensive hepatic extraction of lovastatin, the availability of drug to the general circulation is low and variable. In a single dose study in four hypercholesterolemic patients, it was estimated that less than 5% of an oral dose of lovastatin reaches the general circulation as active inhibitors. Following administration of lovastatin tablets the coefficient of variation, based on between-subject variability, was approximately 40% for the area under the curve (AUC) of total inhibitory activity in the general circulation.
Both lovastatin and its beta-hydroxyacid metabolite are highly bound (> 95%) to human plasma proteins. Animal studies demonstrated that lovastatin crosses the blood-brain and placental barriers.
Cellular LocationsCytoplasm
Metabolite PathwaysLovastatin Action Pathway
用途与制造
Uses
Anticholesteremic Agents; Hydroxymethylglutaryl-CoA Reductase Inhibitors
MEDICATION
Lovastatin is ... used as starting material for the synthesis of simvastatin.
Use (kg; approx.) in Germany (2009): >250
For management as an adjunct to diet to reduce elevated total-C, LDL-C, apo B, and TG levels in patients with primary hypercholesterolemia and mixed dyslipidemia. For primary prevention of coronary heart disease and to slow progression of coronary atherosclerosis in patients with coronary heart disease.
Methods of ManufacturingLovastatin is the delta-lactone of mevinolinic acid and is produced by fermentation of Aspergillus terreus. The drug has also been isolated as a fermentation metabolite of Monascus ruber.
Formulations/Preparations
Table: Lovastatin Preparations [Table#6040]
Table: Lovastatin Combinations Preparations [Table#6041]
应用领域
概述洛伐他汀是从土曲霉培养液中分离的六氢萘酯,为一无活性内酯,口服后被水解后才具活性,在肝脏对HMG-CoA还原酶具有强大的竞争性抑制作用。HMG-CoA还原酶是体内胆固醇从头合成的限速酶,该酶受抑,可阻断HMG-CoA向甲基戊酸转化,使胆固醇合成明显减少,引起肝脏 LDL受体表达增强,使血浆LDL-C的清除加强。胆固醇合成减少也可使肝脏合成ApoB100减少,从而使VLDL合成减少。临床观察表明,本品不论对杂合子家族性高胆固醇血症、多基因性高胆固醇血症、糖尿病或肾病综合征等各种原因引起的高胆固醇血症均有良好的降低血浆总胆固醇和LDLC作用。 他汀类是丝状真菌的次生代谢产物, 能选择性抑制羟甲基戊二酸辅酶A(HMG-CoA)还原酶活性,并阻断胆固醇生物合成,这与他汀类的酸式结构和HMG-CoA相似有关。 目前用于人类的这类药物(他汀类药物, statins)主要有天然他汀类和合成他汀类药物。天然他汀类药有洛伐他汀、美伐他汀(mevastatin)、普伐他汀(prav asta tin)和辛伐他汀(simvastatin), 洛伐他汀由土曲霉(Aspergil lus terreus)发酵生产, 美伐他汀由桔青霉(penicillium citrinum)发酵后经链球菌(stre ptomyces carbophilus)转化获得, 辛伐他汀由洛伐他汀经半合成(化学修饰侧链)生产。合成他汀类药物有氟伐他汀(fluv astatin)、西立伐他汀(cerivastatin)和阿托伐他汀(ato rvastatin)。
用途用于杂合子家族性、非家族性、继发性各型高脂血症,即糖尿病和肾病综合征继发性高胆固醇血症。可降低TC、LF、LDL-C,升高 HDL-C,减少心肌梗死、不稳定心绞痛的危险性及冠脉成形术的必要性。 有关洛伐他汀的概述、药用价值、生物合成、用途等是由Chemicalbook的侍艳编辑整理。(2015-12-28)
用途新型血脂调节药-HMG-CoA(β-羟基,β-甲基-戊二酸单酰辅酶A)还原酶抑制剂。能明显降低血清总胆固醇的浓度,口服后被水解成相应的β-羟基酸,3-羟基-3-甲基戊二酰辅酶A还原酶,而抑制胆固醇合成。临床用于杂合型家族性高胆固醇血症、严重及轻型原发性高胆固醇血症,还可作饮食疗法辅助药物,减少过高的胆固醇和低密度蛋白胆固醇水平。
用途心血管系统用药,能阻止动脉硬化的发展、减少心肌梗塞等的发病危险
用途降胆固醇药物和HMG-CoA还原酶的竞争性抑制剂,一种对胆固醇合成的速率限制酶。阻止胆固醇和异戊二烯生产的关键化合物甲羟戊酸(mevalonate)生产。该产品是Pgp 和 CYP3A的底物。它增加细胞对抗癌药物的耐药性,如阿霉素,诱导骨髓瘤细胞凋亡。该产品诱导众多癌细胞凋亡,部分通过抑制Rho家族GTP酶。它会导致细胞周期在G1和G2/ M期被捕获。
制备方法
生产方法洛伐他汀经发酵得到。可用的菌种有:①Monescus ruber;②Monescus purpureus;③Monescus pilosus;④Aspergillus terreus;⑤Penicillium Citrunum。用Monescus ruber作为菌种时,其培养液为:6%葡萄糖、2.5%胨、0.5%玉米浆、0.5%氯化铵。菌种和培养液一起,在28℃需氧条件下培养10d。过滤取5L滤液,用5L Ph值为3的乙酸乙酯提取。提取液真空浓缩至干,剩余物溶于100ml苯。过滤除去不溶物,滤液用100ml 5%碳酸钠水溶液洗2次,然后和100ml0.2mol/L氢氧化钠溶液一起在室温下搅拌2h。收集水层,用6mol/L盐酸调至Ph=3后,用100ml乙酸乙酯提取2次。提取液合并蒸发至干,得260mg油状物。将该油状物溶于小量苯,得到的结晶再用丙酮和水的混合液重结晶,得87mg无色的洛伐他汀结晶,熔点157~159℃(分解),[α]D23+307.6°(C=1,甲醇)。
上下游产品信息
上游原料
下游产品
试剂价格
- HY-N0504 · 10mg
- 洛伐他汀Lovastatin — 222元
- HY-N0504R · 5 mg
- 洛伐他汀Lovastatin (Standard) — 400元
供应商50 家
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
上海如吉生物科技发展有限公司+86-21-65211385-8001 36031160 · [email protected]
Jai Radhe Sales+(91)-(79)-26431096/65255722 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
上海迈瑞尔生化科技有限公司4006356688 18621169109 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
阿法埃莎(中国)化学有限公司400-6106006 · [email protected]
太原市瑞和丰科贸有限公司+86 351 7031519 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
上海柯维化学技术有限公司021-64609169 18901607656 · [email protected]
天津万象恒远科技有限公司15722085254 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
深圳虹彩祥根生物科技有限公司+86-0755-89668383 · [email protected]
上海隆盛化工有限公司58099637 13585536065 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
Abblis Chemicals LLC+1-832-373-8299 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
湖南汇百侍生物科技有限公司0731-85526065 13308475853 · [email protected]
斯百全化学(上海)有限公司021-021-021-67601398-809-809-809 15221380277 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
艾科试剂4008-755-333 18080918076 · [email protected]
深圳菲斯生物科技有限公司0755-83725681-603
上海思域化工科技有限公司86-21-34053660 · [email protected]
TCI AMERICA800-4238616 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
TCI Europe320-37350700 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
南京杜莱生物技术有限公司025-84699383-8003;025-846993838003-8003 18013301590 · [email protected]
Clearsynth Labs Limited+91-22-26355700 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
ApexBio Technology LLC+1-832-696-8203 · [email protected]
上海倍卓生物科技有限公司021-61119791,13386096464 · [email protected]
惠州拓康生物科技有限公司+86 (0752) 222-7171, +86 15815821171
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
上海将来实业股份有限公司021-61552785 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
成都零六生物科技有限公司400-1166-196 13458535857 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
上海卓因生物科技有限公司021-61317773 · [email protected]
湖南华腾制药有限公司400-8592883 · [email protected]
相关反应
23 条

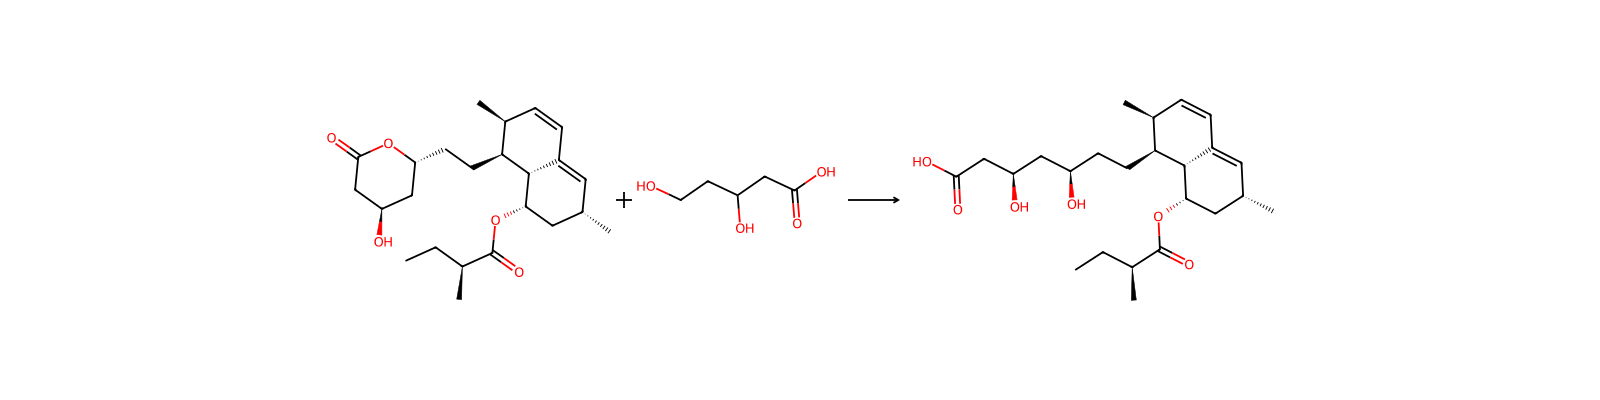
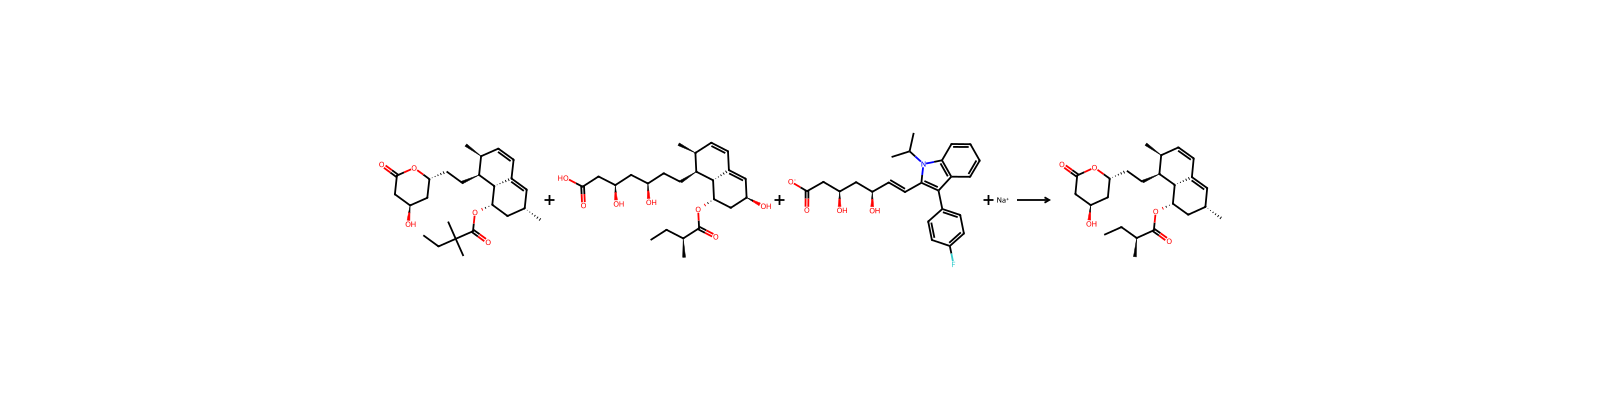

关联笔记
加载中…