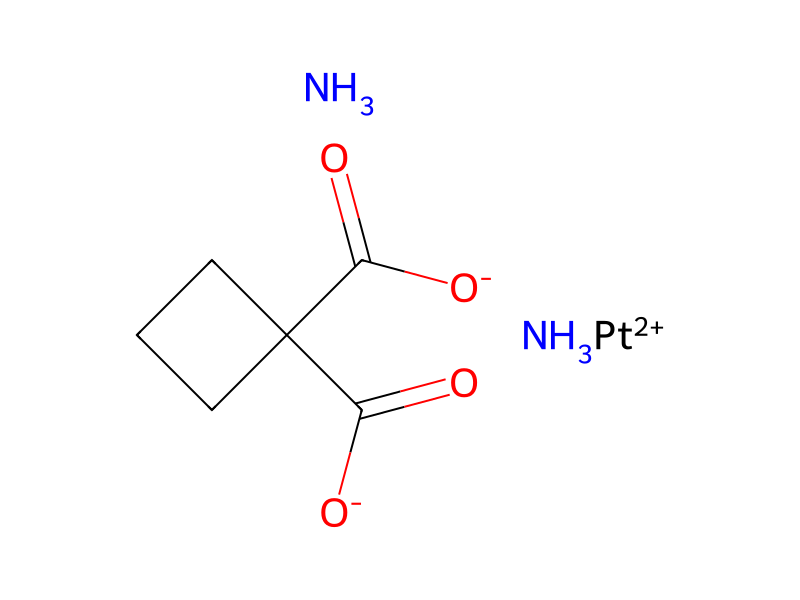
41575-94-4N.N.O=C([O-])C1(C(=O)[O-])CCC1.[Pt+2]OLESAACUTLOWQZ-UHFFFAOYSA-LCarboplatin is an organoplatinum antineoplastic alkylating agent used in the treatment of advanced ovarian carcinoma. Early clinical studies of carboplatin were performed in 1982. Carboplatin was developed as an analog of [cisplatin] with reduced nephrotoxicity and vomiting. Carboplatin was granted FDA approval on 3 March 1989.
41575-94-4DTXSID3046742CHEMBL1351、CHEMBL288376Sol in water
Water > 15 (mg/mL)
pH 4 Acetate Buffer 5 - 10 (mg/mL)
pH 9 Carbonate Buffer 5 - 10 (mg/mL)
10% Ethanol/H2O 5 - 10 (mg/mL)
Breast Feeding; Lactation; Milk, Human; Antineoplastic Agents; Platinum Compounds
FDA approved drugs -> Active ingredient
Cytotoxic medicines
The manufacturer states that constituted solns are stable for 8 hr at a room temp not exceeding 25 °C. However, other information indicates that the drug may be stable for a much longer time. At a concn of 15 mg/ml in sterile water for injection or at concns of 2 & 0.5 mg/ml in dextrose 5% in water, no decomp occurs in 24 hr at 22-25 °C. Aqueous solns of 10 mg/ml prefilled into plastic syringes exhibited no decomp in 5 days at 4 °C & only a 3% loss in 24 hr at 37 °C.
Bulk: No decomposition was detected after 30 days at 60 °C in the dark (HPLC). Solution: After 48 hours at room temperature an aqueous solution showed < 1% decomposition (HPLC).
Sicherheitsangaben dienen nur zur Orientierung und ersetzen weder das Sicherheitsdatenblatt (SDB) des Lieferanten noch geltende Vorschriften oder eine fachliche Bewertung.
Judson I, Kelland LR; Drugs 59 Suppl 4: 29-36 (2000). New developments and approaches in the platinum arena.
Giaccone G; Drugs 59 Suppl 4:9-17 (2000). Clinical perspectives on platinum resistance. The platinum compounds cisplatin and carboplatin are widely used in the treatment of a number of solid malignancies.
The dusts of soluble platinum salts cause a burning sensation in the eyes, lacrimation, and conjunctival hyperemia, sometimes associated with photophobia, which suggests that the corneal epithelium may be involved. /Soluble platinum salts/
Inhalation of the dust of sol platinum salts is irritating. /Platinum/
Persons not wearing protective equipment and clothing should be restricted from areas of spills until cleanup has been completed. If soluble platinum salts or liquids containing soluble salts are spilled, the following steps should be taken: 1. Ventilate area of spill; 2. Collect spilled material in the most convenient and safe manner for reclamation or for disposal in a secured sanitary landfill. Liquids containing soluble platinum salts should be absorbed in vermiculite, dry sand, earth, or a similar material, /Soluble platinum salts/
L - Antineoplastic and immunomodulating agents
QL - Antineoplastic and immunomodulating agents
L01XA02
Carboplatin is an organoplatinum antineoplastic alkylating agent used in the treatment of advanced ovarian carcinoma. Carboplatin has a long duration of action as it is given every 4 weeks, and a narrow therapeutic index. Patients should be counselled regarding bone marrow suppression and anemia.
Carboplatin predominantly acts by attaching alkyl groups to the nucleotides, leading to the formation of monoadducts, and DNA fragmenting when repair enzymes attempt to correct the error. 2% of carboplatin's activity comes from DNA cross-linking from a base on one strand to a base on another, preventing DNA strands from separating for synthesis or transcription. Finally, carboplatin can induce a number of different mutations.
The distribution half life of carboplatin is 1.1-2 hours, and the elimination half life was2.6-5.9 hours.
Ultrafilterable (non-protein bound) platinum in carboplatin has a much longer half-life (170 vs. 30 min) compared with cisplatin.
BG3F62OND5
CARBOPLATIN
Established Pharmacologic Class [EPC] - Platinum-based Drug
Platinum-containing Compounds [EXT]
Carboplatin is a Platinum-based Drug.
CARBOPLATIN
Wird geladen…
Incompatible with aluminum
Because of an interaction occurring between carboplatin & the metal aluminum, resulting in precipitate formation & loss of potency, only administration equipment such as needles, syringes, catheters, & sets that contain no aluminum should be used for this drug.
SRP: At the time of review, criteria for land treatment or burial (sanitary landfill) disposal practices are subject to significant revision. Prior to implementing land disposal of waste residue (including waste sludge), consult with environmental regulatory agencies for guidance on acceptable disposal practices.
Eating and smoking should not be permitted in areas where soluble platinum salts or liquids containing soluble platinum salts are handled, processed, or stored. Employees who handle soluble platinum salts or liquids containing soluble platinum salts should wash their hands thoroughly before eating, smoking, or using toilet facilities. /Soluble platinum salts/
Respirators may be used when engineering and work practice controls are not technically feasible, when such controls are in the process of being installed, or when they fail and need to be supplemented. ... If the use of respirators is necessary, the only respirators permitted are those that have been approved by the Mine Safety and Health Admin (formerly Mining Enforcement & Safety Admin) or by the National Institute for Occupational Safety & Health. In addition to respirator selection, a complete respiratory protection program should be instituted which includes regular training, maintenance, inspection, cleaning, and evaluation. /Soluble platinum salts/
Control can only be achieved by preventing the release of the soluble complex platinum salts to the atmosphere of the workshop. Good exhaust ventilation is necessary in platinum refineries. Chemical procedures which may generate these salts should be carried out in ventilated fume cupboards. Open centrifuges should not be used. Good personal hygiene is important. /Platinum compounds/
Workers whose clothing may have become contaminated should change into uncontaminated clothing before leaving the work premises. /Platinum sol salts, as Pt/
For more Preventive Measures (Complete) data for CARBOPLATIN (9 total), please visit the HSDB record page.
Employees should be provided with and required to use impervious clothing, face shields (eight-inch minimum), and other appropriate protective clothing necessary to prevent repeated or prolonged skin contact with soluble platinum salts or liquids containing soluble platinum salts, where skin contact may occur. ... Employees should be provided with and required to use dust- and splash-proof safety goggles where soluble platinum salts or liquids containing soluble platinum salts may contact the eyes. /Soluble platinum salts/
Recommendations for respirator selection. Max. concn for use: 4 mg/cu m. Any supplied-air respirator that has a full facepiece and is operated in a pressure-demand or other positive-pressure mode. /Platinum (soluble salts as Pt)/
Recommendations for respirator selection. Max. concn for use: 0.1 mg/cu m. Any air-purifying, full-facepiece respirator with a high-efficiency particulate filter.; Any self-contained breathing apparatus with a full facepiece.; Any supplied-air respirator with a full facepiece. /Platinum (soluble salts as Pt)/
Recommendations for respirator selection. Max. concn for use: 0.05 mg/cu m. Any supplied-air respirator operated in a continuous-flow mode. Substance causes eye irritation or damage; eye protection needed. /Platinum (soluble salts as Pt)/
For more Personal Protective Equipment (PPE) (Complete) data for CARBOPLATIN (6 total), please visit the HSDB record page.
High-dose cisplatin regimens have been shown to be highly active in advanced melanoma patients but are associated with unacceptable side effects. In order to increase the platinum dose but avoid severe side effects, we treated 15 dacarbazine (DTIC)-resistant metastatic melanoma patients with a combination regimen of cisplatin (100 mg/sq m) and carboplatin (200 mg/sq m), two platinum analogues with a similar mode of action but a different toxicity pattern. After a mean follow-up period of 10.7 months (range 4-18 months), two patients (13.3%) achieved complete remission and two patients (13.3%) showed partial remission, giving an overall response rate of 26.4% (95% confidence interval [CI] 4.2-49%). Furthermore, three patients (20%; 95% CI 0-40.2%) experienced stable disease. The median duration of response was 7.1 months (95% CI 4.2-10.0 months), and the median overall survival was 12.5 months (95% CI 5.8-19.2 months), with eight patients still alive. The main side effects were haematological (leukopenia/thrombocytopenia World Health Organization [WHO] grade I-IV; anaemia WHO grade I-III), gastrointestinal (WHO grade I-III), neurological (WHO grade I-II) and renal (WHO grade I) toxicity. Nevertheless, except in one patient, side effects did not result in discontinuation of therapy. Despite the small number of patients treated in this preliminary study, we believe that combining cisplatin and carboplatin represents a novel, active and well-tolerated therapeutic option as second-line chemotherapy in DTIC-resistant advanced melanoma patients.
The nephrotoxic effects of different platinum compounds based combination chemotherapies were compared. Chemotherapy consisted of either cisplatin fractionated over 5 days (5 x 20 mg/sq m) or given as a single-day infusion (1 x 50 mg/sq m) plus ifosfamide (4 g/cu m) or high-dose chemotherapy was applied including carboplatin (3 x 500 mg/sq m) and ifosfamide (3 x 4 g/sq m) fractionated over three consecutive days. Conventional parameters such as serum creatinine and glomerular filtration rate (GFR), as well as urinary protein excretion of N-acetyl-beta-D-glucosaminidase (NAG)) and alpha 1-micro-globulin were assessed in 52 patients. Fractionation over 5 days without adding other nephrotoxic agents, ie ifosfamide, prevented decreases in glomerular filtration rate following cisplatin, whereas the combination of conventional dose cisplatin and ifosfamide, given as a single-day infusion, and high-dose carboplatin/ifosfamide yielded a pronounced fall of glomerular filtration rate. All groups showed increases in the urinary excretion levels of serum derived proteins and N-acetyl-beta-D-glucosaminidase, but with significant differences; about 2 to 3-fold for 5-days cisplatin, 3 to 5-fold for single-day cisplatin/ifosfamide, and 20 to 35-fold for high-dose chemotherapy. Thus, conventional approaches can reduce but not prevent the nephrotoxicity of cisplatin-based chemotherapy. In particular, high-dose chemotherapy regimens including carboplatin and ifosfamide are associated with comparable or even higher nephrotoxicity to single-day cisplatin/ifosfamide.
Tumor necrosis factor related apoptosis inducing ligand (TRAIL) is one of the tumor necrosis factor ligand families and it selectively induces apoptosis against cancer cells. Several cytotoxic anticancer drugs also mediate apoptosis and may share the common intracellular pathways leading to apoptosis. We reasoned that combination treatment of cancer cells with TRAIL and drugs may overcome this resistance. ... Treatment of T24 cells with a combination of TRAIL and cisplatin resulted in a synergistic cytotoxic effect. Synergy was also achieved in the cisplatin resistant T24 line (T24/CDDP), 2 other bladder cancer lines and 3 freshly derived bladder cancer cells. The combination of TRAIL and carboplatin resulted in a synergistic cytotoxic effect on T24 cells. However, the combination of TRAIL and trans-diamminedichloroplatinum (II) resulted in an antagonistic cytotoxic effect. The synergy achieved in cytotoxicity with TRAIL and cisplatin was also achieved in apoptosis. Treating T24 cells with cisplatin enhanced the expression of bax but not bcl-2. Incubation of T24 cells with TRAIL increased the intracellular accumulation of cisplatin. CONCLUSIONS: This study demonstrates that combination treatment of bladder cancer cells with TRAIL and cisplatin overcomes their resistance. The sensitization obtained with established cisplatin resistant and freshly isolated bladder cancer cells required low subtoxic concentrations of cisplatin, supporting the in vivo potential application of a combination of TRAIL and cisplatin for treating TRAIL resistant and cisplatin resistant bladder cancer.
Mild and transient elevations in serum aminotransferase levels are found in up to one-third of patients taking carboplatin. However, clinically apparent acute liver injury from carboplatin is extremely rare and the characteristics of such injury have not been well defined. In addition, carboplatin has been used in combination with other alkylating agents in high doses in conditioning regimens in preparation of hematopoietic cell transplantation which may be associated with instances of sinusoidal obstruction syndrome, which can be severe and lead to acute liver failure. Onset of sinusoidal obstruction syndrome is generally within 10 to 20 days of transplantation and presents with right upper quadrant pain, hepatic tenderness, weight gain, edema and ascites, followed by jaundice. The role of carboplatin in causing these cases of sinusoidal obstruction syndrome has not been well defined.
Acute toxicity: nausea & vomiting. Delayed toxicity: Bone marrow depression; peripheral neuropathy (uncommon); hearing loss; transient cortical blindness; hemolytic anemia. /From table/
... Carboplatin, cis-diammine(cyclobutane-1, 1-dicarboxylato)platinum(II) has been shown to be an active agent for acute myeloid leukemia. This second-generation platinum drug has less nephrotoxicity and ototoxicity but more myelotoxicity than does the first-generation platinum drug cisplatin. The study was designed to elucidate whether their myelosuppressive activities equal their antileukemic effects. ... Cisplatin and carboplatin were used to treat four leukemic cell lines (CEM, HL60, K562 and U937), blast cells from 10 leukemic patients and hematopoietic progenitors from five umbilical cord blood samples. ... The mean IC50 of leukemic cell lines was 0.4 and 6.2 ug/ml, the mean IC50 of patients' leukemic blasts was 2.0 and 22.4 ug/ml and the mean IC50 of hematopoietic progenitors (BFU-E, CFU-E and CFU-GM) was 1.8 and 1.7 ug/ml for cisplatin and carboplatin, respectively. ... Carboplatin required a 10 times higher drug concentration than cisplatin to induce a similar degree of growth inhibition on leukemic cells. However, the hematopoietic progenitors responded equally to cisplatin and carboplatin at the same drug concentration. The results suggest that the myelosuppressive activity of carboplatin is greater than its antileukemic effect.
Telomerase is a ribonucleoprotein enzyme which is involved in the maintenance of chromosome ends. Telomerase activity is frequently associated with malignant phenotypes, and it can be considered a ubiquitous tumor marker. In this study we describe an approach for developing in vitro chemosensitivity assays based on the assessment of telomerase activity in squamous cell carcinoma to treatment with anticancer drugs. ... A431/CDDP1 and A431/CDDP2, two previously established cisplatin (CDDP)-resistant A431 sublines /were used/. These cell lines were not multidrug resistant but specifically resistant to the CDDP drug family. The telomeric repeat amplification protocol (TRAP assay) was used to measure telomerase activity in CDDP-resistant cell lines and to examine the effect of CDDP and other anticancer drugs on enzyme levels. We next analyzed the relations between telomerase activity and cytotoxic effects of CDDP in human squamous cell carcinoma (HSC2, HSC3, HSC4 and KB cell lines). RESULTS: The telomerase activity of A431/CDDP1 and A431/CDDP2 was significantly higher than that of the parent A431 cell (A431/P) treated with CDDP and carboplatin at IC(50). On the other hand, telomerase activity in these cell lines was not influenced by treatment with 5-fluorouracil, bleomycin, Adriamycin or taxol. The regression line derived from the quantitative analysis of the telomeric ladder versus IC(50) of CDDP concentrations was analyzed. Telomerase activity was found to be positively correlated with the IC(50) values for CDDP. ... The results of the present studies on in vitro squamous cell carcinoma cell lines indicate that telomerase activity inhibition can be used as a marker of tumor cell killing by CDDP. Therefore, the present investigation provides a rational basis for an in vitro chemosensitivity assay based on telomerase activity evaluation.
Drug Induced Liver Injury Rank (DILIrank 2.0)
Carboplatin
vLess-DILI-concern
3
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Basic treatment: Establish a patent airway. Suction if necessary. Watch for signs of respiratory insufficiency and assist ventilations if needed. Administer oxygen by nonrebreather mask at 10 to 15 L/min. Monitor for pulmonary edema and treat if necessary ... . Monitor for shock and treat if necessary ... . Anticipate seizures and treat if necessary ... . For eye contamination, flush eyes immediately with water. Irrigate each eye continuously with normal saline during transport ... . Do not use emetics. For ingestion, rinse mouth and administer 5 ml/kg up to 200 ml of water for dilution if the patient can swallow, has a strong gag reflex, and does not drool ... . Cover skin burns with dry sterile dressings after decontamination ... . /Poison A and B/
Advanced treatment: Consider orotracheal or nasotracheal intubation for airway control in the patient who is unconscious, has severe pulmonary edema, or is in respiratory arrest. Positive pressure ventilation techniques with a bag valve mask device may be beneficial. Monitor cardiac rhythm and treat arrhythmias as necessary ... . Start an IV with D5W /SRP: "To keep open", minimal flow rate/. Use lactated Ringer's if signs of hypovolemia are present. Watch for signs of fluid overload. Consider drug therapy for pulmonary edema ... . For hypotension with signs of hypovolemia, administer fluid cautiously. Watch for signs of fluid overload ... . Treat seizures with diazepam (Valium) ... . Use proparacaine hydrochloride to assist eye irrigation ... . /Poison A and B/
Rat(iv): LD50: 61 mg/kg
Mouse(ip): LD L0: 150 mg/kg
Mouse(iv): LD50: 143 mg/kg
LD50 Rat oral 343 mg/kg
LD50 Rat sc 72 mg/kg
LD50 Rat iv 61 mg/kg
LD50 Mouse ip 118 mg/kg
LD50 Mouse iv 89,360 ug/kg
Substances that inhibit or prevent the proliferation of NEOPLASMS.
Reagents with two reactive groups, usually at opposite ends of the molecule, that are capable of reacting with and thereby forming bridges between side chains of amino acids in proteins; the locations of naturally reactive areas within proteins can thereby be identified; may also be used for other macromolecules, like glycoproteins, nucleic acids, or other.
The Cmax and AUC of carboplatin increase proportionally with increasing doses. A 75 mg/m2 dose reaches a Cmax of 9.06 ± 0.74 µg/mL, with an AUC of 27.18 ± 11.28 h\*µg/mL. A 450 mg/m2 dose reaches a Cmax of 55.39 ± 18.30 µg/mL, with an AUC of 224.41 ± 69.07 h\*µg/mL.
Carboplatin is 65% eliminated in the urine within 12 hours, and 71% eliminated within 24 hours. An additional 3-5% is eliminated in urine from 24 hours to 96 hours. Biliary elimination has not been determined. Carboplatin is predominantly eliminated as the unchanged parent compound.
The apparent volume of distribution after a 30 minute intravenous infusion of 300-500 mg/m<sup>2</sup> was 16 L.
The total body clearance after a 30 minute intravenous infusion of 300-500 mg/m<sup>2</sup> was 4.4 L/h.
A higher percentage of a dose of carboplatin is excreted in the urine than cisplatin & most of the dose is excreted during the initial 24 hr after injection.
BeschreibungCarboplatin is a second generation, platinum-containing antineoplastic agent with significantly reduced nephro-, neuro-, and ototoxicity in comparison to cisplatin. It is effective in the treatment of advanced ovarian carcinoma of epithelial origin and small cell carcinoma of the lung.
VerwendenData on carboplatin production have not been found. Carboplatin is used in chemotherapy to treat cancer, and more particularly to treat cancer of ovary, embryonal carcinoma of the testis, microcellular carcinoma of the lung, neuroblastoma, and squamous cell carcinomas of the head and neck.
We have previously confirmed the in vitro activity of cisplatin and carboplatin against human melanoma cell lines. Both drugs are important components in the chemotherapy used in our service for advanced metastatic melanoma. In this communication we report the in vitro activity of oxaliplatin against human melanoma cell lines in comparison with cisplatin and carboplatin. Oxaliplatin was found to be active against C32 and G361 cell lines with IC50 values of 49.48 and 9.07 microM (1 hr exposure), 9.47 and 1.30 uM (4 h exposure), and 0.98 and 0.14 microM (24 hr exposure), respectively. The cytotoxic activity of oxaliplatin in this in vitro system appears to be significantly superior to that of carboplatin. Its activity becomes comparatively closer to that of cisplatin as exposure time increases. Indeed at a 24 h exposure oxaliplatin appears to be significantly more active than cisplatin against the G361 cell line (p=0.0343). Oxaliplatin merits evaluation in the clinic both as a single agent and in combination with other drugs active against melanoma.
For more Human Toxicity Excerpts (Complete) data for CARBOPLATIN (6 total), please visit the HSDB record page.