
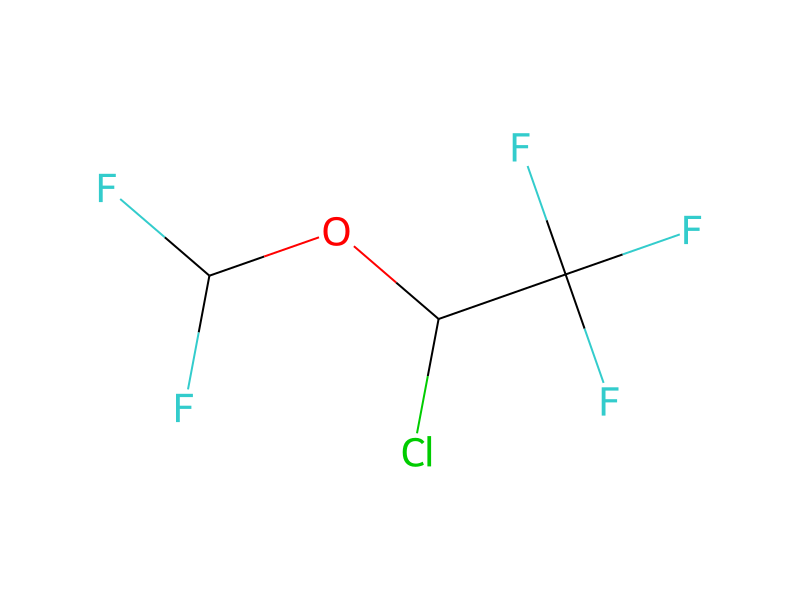
Grundinformationen
- Standard-SMILES
FC(F)OC(Cl)C(F)(F)F- InChIKey
PIWKPBJCKXDKJR-UHFFFAOYSA-N- Summenformel
- C3H2ClF5O
- Durchschnittliche Molmasse
- 184,49 g/mol
- Monoisotopische Masse
- 183,97143346
Überblick
Isoflurane is an organofluorine compound. It has a role as an inhalation anaesthetic. It is functionally related to a methoxyethane.
Namen und Bezeichner
- Bevorzugter Name
- Isoflurane
- IUPAC
- 2-chloro-2-(difluoromethoxy)-1,1,1-trifluoroethane
- Lokaler Name
- Isofluran
- Englischer Name
- Isoflurane
- Summenformel
- C3H2ClF5O
- Molmasse
- 184.49
Namen und Synonyme
isoflurane26675-46-71-Chloro-2,2,2-trifluoroethyl difluoromethyl etherForane2-Chloro-2-(difluoromethoxy)-1,1,1-trifluoroethaneForeneAerraneIsofluranoCompound 469IsoFloIsofluranumEthane, 2-chloro-2-(difluoromethoxy)-1,1,1-trifluoro-
Weitere Namen anzeigen
Isoflurane266(2R)-2-chloro-2-(difluoroMethoxy)-1,1,1-trifluoroethaneIsofLIsourane
TerrellDTXSID3020752CYS9AKD70PCOMPOUND-469Ether, 1-chloro-2,2,2-trifluoroethyl difluoromethyl2-chloro-2-difluoromethoxy-1,1,1-trifluoroethaneDTXCID30752CHEBI:6015
Datenbank-Bezeichner
- CAS
26675-46-7- PubChem CID
- 3763
- DTXSID
DTXSID3020752- ChEMBL
CHEMBL1256- ChEBI
CHEBI:6015- UNII
- CYS9AKD70P
- EC Number
- 247-897-7
- Nikkaji
- J2.770G
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 2,1
- Polarare Oberfläche (TPSA)
- 9,2 Ų
- H-Brücken-Donoren
- 0
- H-Brücken-Akzeptoren
- 6
- Frei drehbare Bindungen
- 2
- Schwere Atome
- 10
- Formalladung
- 0
- Komplexität
- 102
Experimentelle und physikochemische Eigenschaften
Chemical ClassesOther Uses -> Waste Anesthetic Gases
Drugs
Pharmaceuticals
Pharmaceuticals -> Anesthetics
Pharmaceuticals -> Nervous system -> Anesthetics
LogP
log Kow = 2.06
2.1
2.1
2.06
OdorSlight odor
Density
Specific gravity: 1.45
Relative density (water = 1): 1.5
1.45
Color/FormClear, colorless liquid
Solubility
In water, 4.47X10+3 mg/L at 37 °C
Easily miscible with organic liquids including fats and oils
3.56e+00 g/L
Solubility in water: poor
Human Drugs
Breast Feeding; Lactation; Anesthetics, Inhalation
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
General anaesthetics and oxygen > Inhalational medicines
Animal Drugs
Active Ingredients (Isoflurane) -> FDA Greenbook
Pharmaceuticals -> UK Veterinary Medicines Directorate List
Endocrine DisruptorsPotential endocrine disrupting compound
Boiling Point
48.5 °C
49 °C
48.5 °C
119.3 °F
DecompositionWhen heated to decomposition it emits toxic fumes of /fluorine and chlorine/.
Physikochemische Eigenschaften
- Schmelzpunkt
- 48.5 °C · 48.5°C
- Siedepunkt
- 48.5 °C · 48.5 °C
- Dichte
- 1.51 g/mL · 1.510 g/mL at 25 °C
- Dampfdruck
- 238 mmHg · 238 mmHg ( 20 °C)
- Brechungsindex
- 1.3002 · 1.3002
- Flammpunkt
- 48 · 48-49°C
- storage temp.
- 2 · 2-8°C
- Löslichkeit
- Practically insoluble in water, miscible with ethanol and trichloroethylene.
- Aggregatzustand
- liquid
- Farbe
- Colorless to Almost colorless
- Wichte
- 1.5 · approximate 1.50
- Wasserlöslichkeit
- Soluble in chloroform and ethyl acetate. Not miscible or difficult to mix in water.
- Merck
- 14 · 14,5175
- BRN
- 1852087 · 1852087
- Henry's Law Constant
- 2.4 · 2.4×10-4 mol/(m3Pa) at 25℃, Fogg and Sangster (2003)
- Stabilität
- Stable.
- InChI
- 1S/C3H2ClF5O/c4-1(3(7,8)9)10-2(5)6/h1-2H
- InChIKey
- PIWKPBJCKXDKJR-UHFFFAOYSA-N
- SMILES
- FC(F)OC(Cl)C(F)(F)F
- CAS Datenbank
- 26675 · 26675-46-7(CAS DataBase Reference)
- NIST chemische Informationen
- 1 · 1-Chloro-2,2,2-trifluoroethyl difluoromethyl ether(26675-46-7)
- EPA chemische Informationen
- Isoflurane (26675-46-7)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
This chemical does not meet GHS hazard criteria for 2.9% (3 of 103) of reports.
Warning
H336 (93.2%): May cause drowsiness or dizziness [Warning Specific target organ toxicity, single exposure; Narcotic effects]
P260, P261, P271, P304+P340, P319, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 103 reports by companies from 12 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Gefahrenhinweise
Regulatory InformationIsoflurane: Does not have an individual approval but may be used under an appropriate group standard
Fire HazardsNot combustible. Gives off irritating or toxic fumes (or gases) in a fire.
Hazards Summary
A skin, eye, and respiratory tract irritant; May cause CNS and cardiovascular system effects; [ICSC] Occupational asthma confirmed three workers exposed to Sevoflurane and Isoflurane; [Malo] 2021 TLV Basis: embryo damage, maternal body weight effects, CNS impairment; [ACGIH] Mice exposed to concentrations of 0.6% for 4hr/day during gestation produced smaller litters, delayed ossification, and increased frequency of cleft palate (maternal toxicity shown by weight reduction); Chronic exposure of mice to low anesthetic or sub-anesthetic doses demonstrated no evidence of effects male or female fertility, reproductive loss, or early postnatal fetal wastage; A more recent study associated chronic exposure with fetal growth retardation; Chronic exposure in rabbits produced significantly reduced sperm concentrations and motility; [REPROTOX] May cause drowsiness or dizziness; [Abbott Laboratories MSDS]
FDA Requirements
Isoflurane: ... For induction and maintenance of general anesthesia in horses and dogs.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including isoflurane, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Isoflurane is included on this list.
Chemical DangersDecomposes on contact with hot surfaces or flames. This produces toxic and corrosive fumes including phosgene, hydrogen chloride and hydrogen fluoride.
Physical DangersThe vapour is heavier than air and may accumulate in lowered spaces causing a deficiency of oxygen.
Hazard Classes and CategoriesSTOT SE 3 (93.2%)
Sicherheit und Schutzausrüstung
Fire FightingIn case of fire in the surroundings, use appropriate extinguishing media.
First Aid Measures
Fresh air, rest. Artificial respiration may be needed. Refer for medical attention.
Remove contaminated clothes. Rinse and then wash skin with water and soap.
First rinse with plenty of water for several minutes (remove contact lenses if easily possible), then refer for medical attention.
Rinse mouth. Refer for medical attention .
Safe StorageVentilation along the floor.
Exposure Control and Personal Protection2.0 [ppm]
Fire Fighting Procedures
As with all fires, evacuate personnel to a safe area. Firefighters should use self-contained breathing equipment and protective clothing.
The product is not flammable.Water fog, dry chemical, or carbon dioxide as appropriate for surrounding fire and materials.Do not use water jet as an extinguisher, as this will spread the fire.
Storage Conditions
Store at room temperature 15-30 degC (59-86 °F).
Store in tight container as defined in the USP-NF. This material should be handled and stored per label instructions to ensure product integrity.
Cleanup Methods
Stop the flow of material, if this is without risk. Dike the spilled material, where this is possible. Prevent entry into waterways, sewer, basements or confined areas. Wear approved respiratory protection, chemically compatible gloves, and protective clothing. Wipe up spillage or collect spillage using a high-efficiency vacuum cleaner. Avoid breathing vapor. Ventilate area and wash spill site. Place spillage in appropriately labeled container for disposal. Small quantities of liquid anesthetic agents may evaporate readily at room temperature.Large Spills: Stop the flow of material, if this is without risk. Dike the spilled material, where this is possible. Cover with plastic sheet to prevent spreading. Absorb in vermiculite, dry sand or earth and place into containers. Following product recovery, flush area with water. Never return spills in original containers for re-use.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
SRP: Wastewater from contaminant suppression, cleaning of protective clothing/equipment, or contaminated sites should be contained and evaluated for subject chemical or decomposition product concentrations. Concentrations shall be lower than applicable environmental discharge or disposal criteria. Alternatively, pretreatment and/or discharge to a permitted wastewater treatment facility is acceptable only after review by the governing authority and assurance that "pass through" violations will not occur. Due consideration shall be given to remediation worker exposure (inhalation, dermal and ingestion) as well as fate during treatment, transfer and disposal. If it is not practicable to manage the chemical in this fashion, it must be evaluated in accordance with EPA 40 CFR Part 261, specifically Subpart B, in order to determine the appropriate local, state and federal requirements for disposal.
Spillage DisposalPersonal protection: self-contained breathing apparatus. Ventilation. Collect leaking liquid in sealable containers. Absorb remaining liquid in sand or inert absorbent. Then store and dispose of according to local regulations.
Preventive Measures
Safety glasses with sideshields are recommended. Face shields or goggles may be required if splash potential exists or if corrosive materials are present. Approved eye protection (e.g., bearing the ANSI Z87 or CSA stamp) is preferred. Maintain eyewash facilities in the work area.
As a general rule, when handling USP Reference Standards, avoid all contact and inhalation of dust, mists, and/or vapors associated with the material. Clean equipment and work surfaces with suitable detergent or solvent after use. After removing gloves, wash hands and other exposed skin thoroughly.
Since exposure to WAGs is one possible factor in the findings for these studies, operating room personnel, and pregnant women in particular, should minimize exposure. Precautions include adequate general ventilation in the operating room, the use of a well-designed and well-maintained scavenging system, work practices to minimize leaks and spills while the anesthetic agent is in use, and routine equipment maintenance to minimize leaks.
Eye PreventionWear safety spectacles or eye protection in combination with breathing protection.
Inhalation RiskA harmful contamination of the air can be reached very quickly on evaporation of this substance at 20 °C.
Toxikologische Informationen
TreatmentStop drug administration, establish a clear airway, and initiate assisted or controlled ventilation with pure oxygen. (L1712)
Interactions
Isoflurane potentiates the muscle relaxant effect of all muscle relaxants, most notably nondepolarizing muscle relaxants, and MAC (minimum alveolar concentration) is reduced by concomitant administration of N2O.
Increasing numbers of people use cocaine recreationally and may require anesthesia care, having recently abused the drug. However, no data currently exist concerning potential interactions between toxic levels of cocaine and volatile anesthetic agents. This study investigated the effects of cocaine infusion on systemic hemodynamics, myocardial metabolism, and regional organ blood flow in relation to depth of isoflurane anesthesia. Prospective, randomized, controlled trial /was conducted in/ twelve miniature pigs. An open-chest swine model was used. Isoflurane (ISO) was the sole anesthetic, administered at 0.75 and 1.5 minimum alveolar concentration (MAC), and cocaine was infused (n = 6) at a rate of 0.5 mg/kg/min. Control animals (n = 6) received an equivalent amount of normal saline. Systemic and pulmonary arterial pressures and thermodilution cardiac output data were collected at 0.75 MAC and 1.5 MAC ISC. Regional myocardial and blood flows to other organs were measured using radiolabeled microspheres. Arrhythmias and altered ventricular conduction were noted only in the cocaine group, along with significant elevations in diastolic arterial pressure, coronary perfusion pressure, and systemic vascular resistance. Increased subendocardial blood flow occurred during cocaine infusion (p = 0.03); subepicardial perfusion was unchanged. Cerebral (p < 0.01) and spinal cord (p < 0.05) blood flows were reduced in animals receiving cocaine. Other organ blood flows were unchanged with depth of anesthesia or cocaine administration, with the exception of splenic blood flow (p < 0.04). Moderately toxic cocaine levels occurring during isoflurane at 0.75 MAC and 1.5 MAC are associated with hemodynamic abnormalities, a marked increase in systemic vascular resistance, and a tendency to produce cardiac arrhythmias. A reversal of endo/epicardial myocardial perfusion ratio occurs associated with cocaine infusion during ISO anesthesia. This is probably not related to a primary redistribution of subendocardial blood flow and may be related to a combination of increased myocardial oxygen demand and epicardial coronary vasoconstriction. The reductions in cerebral and spinal cord perfusion observed may explain, in part, the neurologic sequelae of cocaine toxicity.
Recent in vitro data indicate that isoflurane can reduce N-methyl-D-aspartate (NMDA) receptor-mediated responses and thereby might reduce excitotoxicity. However, the effect of isoflurane on NMDA receptor-mediated toxicity in vivo is not known. We conducted the present study to evaluate the effect of isoflurane on injury produced by cortical injection of NMDA in vivo and to compare it with dizocilpine, an antagonist of the NMDA receptor. Fasted Wistar-Kyoto rats were anesthetized with isoflurane. NMDA 50 nmoles (5-uL volume) were stereotactically injected into the cortex (2.8 mm lateral and 2.8 mm rostral to the bregma, depth 2 mm) of animals in one of four groups. In the isoflurane groups, the end-tidal concentration of isoflurane was maintained at either electroencephalogram (EEG)-burst suppression (BS) doses (2.2%-2.3%, n = 12) or a 1 minimum alveolar anesthetic concentration (MAC) dose (n = 10). In the dizocilpine group (n = 10), 10 mg/kg dizocilpine was injected IV 15 min before the NMDA injection. In the awake group and the dizocilpine group, anesthesia was discontinued on completion of the NMDA injection, and the animals were allowed to awaken. In the animals in the control group (n = 10), 20 uL of artificial cerebrospinal fluid was injected into the cortex. Injury to the cortex was evaluated 2 days after the NMDA injection. In 1 MAC doses and EEG-BS doses, isoflurane reduced the injury produced by a cortical NMDA injection compared with the awake state (1.74+/-0.49 and 0.96+/-0.46 vs 2.34+/-0.56 cu mm; P = 0.02). Dizocilpine reduced cortical injury (0.56+/-0.27; P = 0.01) compared with the awake state. Injury in the control group was limited to the trauma produced by cannula insertion. In the isoflurane EEG-BS and dizocilpine groups, the injury was not different from the control group. Isoflurane can reduce N-methyl-D-aspartate-mediated cortical injury in vivo in a dose-dependent manner. These data are consistent with the previously demonstrated ability of isoflurane to reduce N-methyl-D-aspartate receptor-mediated responses in vitro.
b-amyloid protein (Ab)-induced neurotoxicity is the main component of Alzheimer's disease (AD) neuropathogenesis. Inhalation anesthetics have long been considered to protect against neurotoxicity. However, recent research studies have suggested that the inhalation anesthetic isoflurane may promote neurotoxicity by inducing apoptosis and increasing Ab levels. We therefore set out to determine whether isoflurane can induce dose- and time-dependent dual effects on Ab-induced apoptosis: protection versus promotion. H4 human neuroglioma cells, primary neurons from naive mice, and naive mice were treated with Ab and/or isoflurane, and levels of caspase-3 cleavage (activation), apoptosis, Bcl-2, Bax, and cytosolic calcium were determined...the treatment with 2% isoflurane for six hours or 30 minutes potentiated, whereas the treatment with 0.5% isoflurane for six hours or 30 minutes attenuated, the Ab-induced caspase-3 activation and apoptosis in vitro. Moreover, anesthesia with 1.4% isoflurane for two hours potentiated, whereas the anesthesia with 0.7% isoflurane for 30 minutes attenuated, the Ab-induced caspase-3 activation in vivo. The high concentration isoflurane potentiated the Ab-induced reduction in Bcl-2/Bax ratio and caused a robust elevation of cytosolic calcium levels. The low concentration isoflurane attenuated the Ab-induced reduction in Bcl-2/Bax ratio and caused only a mild elevation of cytosolic calcium levels. These results suggest that isoflurane may have dual effects (protection or promotion) on Ab-induced toxicity, which potentially act through the Bcl-2 family proteins and cytosolic calcium. These findings would lead to more systematic studies to determine the potential dual effects of anesthetics on AD-associated neurotoxicity.
For more Interactions (Complete) data for Isoflurane (8 total), please visit the HSDB record page.
Health Effects
May lead to cardiac arrhythmias and death (Rarely). In susceptible individuals, Isoflurane anesthesia may trigger a skeletal muscle hypermetabolic state leading to high oxygen demand and the clinical syndrome known as malignant hyperthermia. The syndrome includes nonspecific features such as muscle rigidity, tachycardia, tachypnea, cyanosis, arrhythmias, and unstable blood pressure.(L1471)
Hepatotoxicity
Prospective, serial blood testing often demonstrates minor transient elevations in serum aminotransferase levels in the 1 to 2 weeks after major surgery and halogenated anesthetic agents. Appearance of ALT levels above 10 times the upper limit of normal, however, is distinctly unusual and points to significant hepatotoxicity. Clinically apparent, severe hepatic injury from isoflurane is very rare, only isolated case reports and small case series having been published. The injury is marked by acute elevations in serum aminotransferase levels (5- to 50-fold) and appearance of jaundice within 2 to 21 days of surgery. There are usually minimal increases in alkaline phosphatase and gammaglutamyl transpeptidase levels. Jaundice is usually preceded by a day or two of fever and may be accompanied by rash and eosinophilia. The acute liver injury may be self-limited and resolve within 4 to 8 weeks, but can be severe and associated with acute liver failure. A strong risk factor is previous exposure to any of the halogenated anesthetics and particularly a history of halothane hepatitis or unexplained fever and rash after anesthesia with one of these agents. The differential diagnosis of acute liver injury after surgery and anesthesia is sometimes difficult, and a clinical picture similar to isoflurane hepatitis can be caused by shock or ischemia, other idiosyncratic forms of drug induced liver injury and acute viral or herpes hepatitis.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 94(SRC), determined from a log Kow of 2.06(2) and a regression-derived equation(3), indicates that isoflurane is expected to have high mobility in soil(SRC). Volatilization of isoflurane from moist soil surfaces is expected to be an important fate process(SRC) given a Henry's Law constant of 2.87X10⁻² atm-cu m/mole(4). Isoflurane is expected to volatilize from dry soil surfaces(SRC) based upon a vapor pressure of 330 mm Hg at 25 °C(5). Biodegradation data in soil were not available(SRC, 2012).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 94(SRC), determined from a log Kow of 2.06(2) and a regression-derived equation(3), indicates that isoflurane is not expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is expected(4) based upon a Henry's Law constant of 2.87X10⁻² atm-cu m/mole(5). Using this Henry's Law constant and an estimation method(4), volatilization half-lives for a model river and model lake are approximately 4 hours and 5.4 days, respectively(SRC). According to a classification scheme(6), an estimated BCF of 11(SRC), from its log Kow(2) and a regression-derived equation(3), suggests the potential for bioconcentration in aquatic organisms is low(SRC). Biodegradation data in water were not available(SRC, 2012).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), isoflurane, which has a vapor pressure of 330 mm Hg at 25 °C(2), is expected to exist solely as a vapor in the ambient atmosphere. Vapor-phase isoflurane is degraded in the atmosphere by reaction with photochemically-produced hydroxyl radicals(SRC); the half-life for this reaction in air is estimated to be 460 days(SRC), calculated from its rate constant of 1.51X10⁻¹⁴ cu cm/molecule-sec at 25 °C(3). Isoflurane does absorbs light at wavelengths <200 nm(4) and, therefore, is not expected to be susceptible to direct photolysis by sunlight(SRC).
Adverse Effects
Neurotoxin - Acute solvent syndrome
Isoflurane should be carefully titrated to the patient’s hemodynamics as it can cause precipitous drops in blood pressure due to dose-dependent peripheral vasodilation. Hypovolemic patients may be susceptible to these effects. The most severe reported adverse reactions include agitation, breath-holding, arrhythmia, hepatotoxicity, and laryngospasm.
Exposure Routes
The substance can be absorbed into the body by inhalation of its vapour and by ingestion.
Inhalation
Toxicity Summary
Signs and Symptoms of Overdose
Isoflurane induces a reduction in junctional conductance by decreasing gap junction channel opening times and increasing gap junction channel closing times. Isoflurane also activates calcium dependent ATPase in the sarcoplasmic reticulum by increasing the fluidity of the lipid membrane. Also appears to bind the D subunit of ATP synthase and NADH dehydogenase. Isoflurane also binds to the GABA receptor, the large conductance Ca<sup>2+</sup> activated potassium channel, the glutamate receptor and the glycine receptor.
Signs and Symptoms
Cough. Sore throat. Dizziness. Drowsiness. Headache. Unconsciousness.
Redness. Dry skin.
Redness. Pain.
See Inhalation.
The predicted effects of acute overexposure by inhalation of Isoflurane, USP include headache, dizziness or (in extreme cases) unconsciousness. (L1471)
Soil Adsorption/Mobility
The Koc of isoflurane is estimated as 94(SRC), using a log Kow of 2.06(1) and a regression-derived equation(2). According to a classification scheme(3), this estimated Koc value suggests that isoflurane is expected to have high mobility in soil.
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ The maternal and neonatal effects of isoflurane and halothane combined with 50% N2O - 50% O2 were compared in 60 healthy parturients undergoing primary or repeat cesarean section. All patients had rapid sequence induction of anesthesia with sodium thiamylal 4 mg/kg followed by succinylcholine for tracheal intubation. Patients were randomly assigned to one of three groups of 20 each (inspired 0.5% isoflurane, 1% isoflurane or 0.5% halothane), combined with 50% N2O and O2. After delivery, 67% N2O in O2 was used, supplemented by butorphanol. Maternal blood loss did not differ significantly among the three groups and none of the patients developed intraoperative awareness. At the time of delivery, maternal plasma epinephrine levels were significantly above preinduction levels in the 0.5% isoflurane group but unchanged in the other two groups. Neonatal status as ascertained by Apgar scores, cord acid base status and the Neurologic and Adaptive Capacity Scores (NACS) was equally good in the three groups of patients. Serum inorganic fluoride concentrations in the mother after anesthesia were not significantly above preanesthetic levels in any of the groups and there was no biochemical evidence of renal toxicity. In all neonates fluoride ion concentrations in the first voided urine sample were less than 7 umol/L, a value well below that associated with nephrotoxicity. It is concluded that isoflurane is a safe supplement to N2O - O2 mixture for cesarean section and is a safer alternative to halothane in situations when patients receiving beta-adrenergic therapy require cesarean section since halothane might potentiate arrhythmias caused by beta adrenergic agonists.
/CASE REPORTS/ We describe a patient with tetanus, who received isoflurane for sedation to facilitate controlled mechanical ventilation. Isoflurane was administered for 34 days, resulting in a sustained serum inorganic fluoride ion concentration in excess of 50 umol /per/ L and a peak serum inorganic fluoride ion concentration of 87 umol /per/ L. Although these concentrations are potentially nephrotoxic, no toxicity was evident clinically.
/CASE REPORTS/ Isoflurane is considered a safe inhalational anesthetic. It has a low level of biotransformation, and low hepatic and renal toxicity. In clinical concentrations, it has minimal negative inotropic effect, causes a small reduction in systemic vascular resistance, and, rarely, can cause cardiac arrhythmias. The objective of this report was to present a case of severe hemodynamic instability in a patient with idiopathic scoliosis. Male patient, 13 years old, ASA physical status I, with no prior history of allergy to medications, scheduled for surgical repair of idiopathic scoliosis. After anesthetic induction with fentanyl, midazolam, propofol, and atracurium, 1% isoflurane with 100% oxygen was initiated for anesthesia maintenance. After five minutes, the patient presented severe hypotension (MAP = 26 mmHg) associated with sinus tachycardia (HR = 166 bpm) that did not respond to the administration of vasopressors and fluids. Lung and heart auscultation, pulse oxymetry, capnography, nasopharyngeal temperature, and arterial blood gases did not change. The patient was treated for anaphylaxis and the surgery was cancelled. The clear temporal relationship between the administration of isoflurane and the symptoms suggested the diagnosis of cardiovascular intolerance to inhalational isoflurane. Two weeks later, total intravenous anesthesia was administered without complications. There are no reports of severe hemodynamic instability caused by isoflurane in previously healthy individuals. Anaphylaxis, supraventricular tachycardia with hemodynamic consequences, and increased cardiac sensitivity to isoflurane are discussed as possible causes of the hemodynamic instability. Currently, there is evidence that isoflurane can interfere in the coupling-uncoupling system of myocardial contractility by reducing cytosolic Ca2+ and/or depressing the function of contractile proteins. The fundamental molecular mechanisms of this process remain to be elucidated. This report suggests that the administration of isoflurane was the cause of the hemodynamic changes; the patient probably developed an unusual cardiovascular sensitivity to the drug.
/GENOTOXICITY/ The alkaline single cell gel electrophoresis (comet) assay was applied to study genotoxic properties of two inhalation anesthetics-halothane and isoflurane-in human peripheral blood lymphocytes (PBL). The cells were exposed in vitro to either halothane (2-bromo-2-chloro-1,1,1-trifluoroethane) or isoflurane (1-chloro-2,2,2-trifluoroethyl difluoromethyl ether) at concentrations 0.1-10 mM in DMSO. The anesthetics-induced DNA strand breaks as well as alkali-labile sites were measured as total comet length (i.e., increase of a DNA migration). Both analysed drugs were capable of increasing DNA migration in a dose-dependent manner. In experiments conducted at two different electrophoretic conditions (0. 56 and 0.78 V/cm), halothane was able to increase DNA migration to a higher extent than isoflurane. The comet assay detects DNA strand breaks induced directly by genotoxic agents as well as DNA degradation due to cell death. For this reason a contribution of toxicity in the observed effects was examined. We tested whether the exposed PBL were able to repair halothane- and isoflurane-induced DNA damage. The treated cells were incubated in a drug-free medium at 37 degrees C for 120 min to allow processing of the induced DNA damage. PBL exposed to isoflurane at 1 mM were able to complete repair within 60 min whereas for halothane a similar result was obtained at a concentration lower by one order of magnitude: the cells exposed to halothane at 1 mM removed the damage within 120 min only partly. We conclude that the increase of DNA migration induced in PBL by isoflurane at 1 mM and by halothane at 0.1 mM was not a result of cell death-associated DNA degradation but was caused by genotoxic action of the drugs. The DNA damage detected after the exposure to halothane at 1 mM was in part a result of DNA fragmentation due to cell death.
For more Human Toxicity Excerpts (Complete) data for Isoflurane (10 total), please visit the HSDB record page.
Artificial Pollution SourcesIsoflurane's production and administration as an anaesthetic and solvent for fluorinated materials(1) may result in its release to the environment through various waste streams(SRC).
Regulatorische Informationen
FDA Requirements
Isoflurane: ... For induction and maintenance of general anesthesia in horses and dogs.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including isoflurane, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Isoflurane is included on this list.
Sicherheitsdaten
- wgk
- 3
- ridadr
- UN 3334
- hs_code
- 2909191800
- RTECS-Nr.
- KN6799000
- risk_code
- 36/37/38-67-48/20
- Toxizität
- An isomer of enflurane with similar anesthetic properties. Isoflurane has less effect on myocardial function, leaving the cardiovascular system normally responsive to epinephrine or hypercarbia, and it does not cause a marked increase in seizure susceptibility. It was not widely used because of reports that it caused increases in liver neoplasms in mice, but this observation has been challenged and the compound reintroduced.
- hazard_code
- F,T,Xn
- hazard_note
- Flammable/Toxic
- safety_code
- 26-36/37/39-24/25
- Speicherklasse
- 10 - Combustible liquids
- Giftige Stoffe Daten
- 26675-46-7(Hazardous Substances Data)
- Hazard Classifications
- STOT SE 3
Chemie und Industrie
Pharmakologische Informationen
ATC Code
N - Nervous system
QN - Nervous system
N01AB06
Pharmacodynamics
Isoflurane is a general inhalation anesthetic used for induction and maintenance of general anesthesia. It induces muscle relaxation and reduces pains sensitivity by altering tissue excitability. It does so by decreasing the extent of gap junction mediated cell-cell coupling and altering the activity of the channels that underlie the action potential.
Mechanism of Action
Isoflurane induces a reduction in junctional conductance by decreasing gap junction channel opening times and increasing gap junction channel closing times. Isoflurane also activates calcium dependent ATPase in the sarcoplasmic reticulum by increasing the fluidity of the lipid membrane. Also appears to bind the D subunit of ATP synthase and NADH dehydogenase. Isoflurane also binds to the GABA receptor, the large conductance Ca<sup>2+</sup> activated potassium channel, the glutamate receptor and the glycine receptor.
Metabolism/Metabolites
Minimal
Renal and hepatic toxicity of the fluorinated ether volatile anesthetics is caused by biotransformation to toxic metabolites. Metabolism also contributes significantly to the elimination pharmacokinetics of some volatile agents. Although innumerable studies have explored anesthetic metabolism in animals, there is little information on human volatile anesthetic metabolism with respect to comparative rates or the identity of the enzymes responsible for defluorination. The first purpose of this investigation was to compare the metabolism of the fluorinated ether anesthetics by human liver microsomes. The second purpose was to test the hypothesis that cytochrome P450 2E1 is the specific P450 isoform responsible for volatile anesthetic defluorination in humans. Microsomes were prepared from human livers. Anesthetic metabolism in microsomal incubations was measured by fluoride production. The strategy for evaluating the role of P450 2E1 in anesthetic defluorination involved three approaches: for a series of 12 human livers, correlation of microsomal defluorination rate with microsomal P450 2E1 content (measured by Western blot analysis), correlation of defluorination rate with microsomal P450 2E1 catalytic activity using marker substrates (para-nitrophenol hydroxylation and chlorzoxazone 6-hydroxylation), and chemical inhibition by P450 isoform-selective inhibitors. The rank order of anesthetic metabolism, assessed by fluoride production at saturating substrate concentrations, was methoxyflurane > sevoflurane > enflurane > isoflurane > desflurane > 0. There was a significant linear correlation of sevoflurane and methoxyflurane defluorination with antigenic P450 2E1 content (r = 0.98 and r = 0.72, respectively), but not with either P450 1A2 or P450 3A3/4. Comparison of anesthetic defluorination with either para-nitrophenol or chlorzoxazone hydroxylation showed a significant correlation for sevoflurane (r = 0.93, r = 0.95) and methoxyflurane (r = 0.78, r = 0.66). Sevoflurane defluorination was also highly correlated with that of enflurane (r = 0.93), which is known to be metabolized by human P450 2E1. Diethyldithiocarbamate, a selective inhibitor of P450 2E1, produced a concentration-dependent inhibition of sevoflurane, methoxyflurane, and isoflurane defluorination. No other isoform-selective inhibitor diminished the defluorination of sevoflurane, whereas methoxyflurane defluorination was inhibited by the selective P450 inhibitors furafylline (P450 1A2), sulfaphenazole (P450 2C9/10), and quinidine (P450 2D6) but to a much lesser extent than by diethyldithiocarbamate. These results demonstrate that cytochrome P450 2E1 is the principal, if not sole human liver microsomal enzyme catalyzing the defluorination of sevoflurane. P450 2E1 is the principal, but not exclusive enzyme responsible for the metabolism of methoxyflurane, which also appears to be catalyzed by P450s 1A2, 2C9/10, and 2D6. The data also suggest that P450 2E1 is responsible for a significant fraction of isoflurane metabolism. Identification of P450 2E1 as the major anesthetic metabolizing enzyme in humans provides a mechanistic understanding of clinical fluorinated ether anesthetic metabolism and toxicity.
Isoflurane undergoes minimal biotransformation in man.
Renal and hepatic toxicity of the fluorinated ether volatile anesthetics is caused by biotransformation to toxic metabolites. Metabolism also contributes significantly to the elimination pharmacokinetics of some volatile agents. Although innumerable studies have explored anesthetic metabolism in animals, there is little information on human volatile anesthetic metabolism with respect to comparative rates or the identity of the enzymes responsible for defluorination. The first purpose of this investigation was to compare the metabolism of the fluorinated ether anesthetics by human liver microsomes. The second purpose was to test the hypothesis that cytochrome P450 2E1 is the specific P450 isoform responsible for volatile anesthetic defluorination in humans. Microsomes were prepared from human livers. Anesthetic metabolism in microsomal incubations was measured by fluoride production. The strategy for evaluating the role of P450 2E1 in anesthetic defluorination involved three approaches: for a series of 12 human livers, correlation of microsomal defluorination rate with microsomal P450 2E1 content (measured by Western blot analysis), correlation of defluorination rate with microsomal P450 2E1 catalytic activity using marker substrates (para-nitrophenol hydroxylation and chlorzoxazone 6-hydroxylation), and chemical inhibition by P450 isoform-selective inhibitors. The rank order of anesthetic metabolism, assessed by fluoride production at saturating substrate concentrations, was methoxyflurane > sevoflurane > enflurane > isoflurane > desflurane > 0. There was a significant linear correlation of sevoflurane and methoxyflurane defluorination with antigenic P450 2E1 content (r = 0.98 and r = 0.72, respectively), but not with either P450 1A2 or P450 3A3/4. Comparison of anesthetic defluorination with either para-nitrophenol or chlorzoxazone hydroxylation showed a significant correlation for sevoflurane (r = 0.93, r = 0.95) and methoxyflurane (r = 0.78, r = 0.66). Sevoflurane defluorination was also highly correlated with that of enflurane (r = 0.93), which is known to be metabolized by human P450 2E1. Diethyldithiocarbamate, a selective inhibitor of P450 2E1, produced a concentration-dependent inhibition of sevoflurane, methoxyflurane, and isoflurane defluorination. No other isoform-selective inhibitor diminished the defluorination of sevoflurane, whereas methoxyflurane defluorination was inhibited by the selective P450 inhibitors furafylline (P450 1A2), sulfaphenazole (P450 2C9/10), and quinidine (P450 2D6) but to a much lesser extent than by diethyldithiocarbamate. These results demonstrate that cytochrome P450 2E1 is the principal, if not sole human liver microsomal enzyme catalyzing the defluorination of sevoflurane. P450 2E1 is the principal, but not exclusive enzyme responsible for the metabolism of methoxyflurane, which also appears to be catalyzed by P450s 1A2, 2C9/10, and 2D6. The data also suggest that P450 2E1 is responsible for a significant fraction of isoflurane metabolism. Identification of P450 2E1 as the major anesthetic metabolizing enzyme in humans provides a mechanistic understanding of clinical fluorinated ether anesthetic metabolism and toxicity.
Minimal
FDA Pharmacological Classification
CYS9AKD70P
ISOFLURANE
Physiologic Effects [PE] - General Anesthesia
Established Pharmacologic Class [EPC] - General Anesthetic
Isoflurane is a General Anesthetic. The physiologic effect of isoflurane is by means of General Anesthesia.
ISOFLURANE
MeSH Pharmacological Classification
Gases or volatile liquids that vary in the rate at which they induce anesthesia; potency; the degree of circulation, respiratory, or neuromuscular depression they produce; and analgesic effects. Inhalation anesthetics have advantages over intravenous agents in that the depth of anesthesia can be changed rapidly by altering the inhaled concentration. Because of their rapid elimination, any postoperative respiratory depression is of relatively short duration. (From AMA Drug Evaluations Annual, 1994, p173)
Absorption, Distribution and Excretion
In the postanesthesia period, only 0.17% of the isoflurane taken up can be recovered as urinary metabolites.
It is not known whether this drug is excreted in human milk.
Cellular LocationsCytoplasm
Verwendung und Herstellung
Uses
Used as a special solvent and as an inhalation anesthetic; [Merck Index] A stable, non-explosive inhalation anesthetic, relatively free from significant side effects. [ChemIDplus]
Solvent and dispersant for fluorinated materials
MEDICATION
MEDICATION (VET)
Use (kg) in Switzerland (2009): >750
For induction and maintenance of general anesthesia.
Methods of Manufacturing
Trifluoroethanol is methylated with dimethyl sulfate to form the methyl ether, which is then chlorinated to the dichloromethyl ether ... This latter compound, on treatment with HF/SbCl5 forms the product.
Isoflurane is prepared by chlorination of 2,2,2-trifluoroethoxydifluoromethane, itself obtained by alkylation of trifluoroethanol with difluorochloromethane.
Preparation: Croix, Terrell, DE 1814962 (1969); Terrell, US 3535425 (both to Air Reduction)
Formulations/Preparations
FORANE (isoflurane, USP) is also supplied in the /250 mL/ aluminum bottles.
FORANE (isoflurane, USP) is packaged in 100 mL and 250 mL amber-colored bottles.
Isoflurane USP is packaged in 250mL (NDC 66794-013-25) and 100mL (NDC 66794-013-10) amber-colored bottles./Vet/
Use ClassificationAnimal Drugs -> FDA Approved Animal Drug Products (Green Book) -> Active Ingredients
Anwendungen
VerwendenIsoflurane is a halogenated ether used for inhalational anesthesia. Recent studies suggest that there might be a relationship between administration of isoflurane and postoperative cognitive dysfunct ion (POCD).
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Nachgelagerte Produkte
Anbieter50 Anbieter
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
衢州润东化工有限公司0570-8789886 18892685668 · [email protected]
湖南韵邦生物科技股份有限公司85561037 15386497078 · [email protected]
艾吉析科技(上海)有限公司17717235263 · [email protected]
毕佳索(上海毕得医药科技股份有限公司)400-6005915 · [email protected]
上海毕合生物化学技术有限公司13816464724 · [email protected]
合肥翰刚医药科技有限公司+8618062405514 · [email protected]
杭州品高化工有限公司0571-87658025 · [email protected]
陕西缔都新材料有限公司029-63373950 17392216152 · [email protected]
江苏星科元信息科技有限公司400-605-7200 15335295587
武汉绿景丰华生物科技有限公司19972070065 · [email protected]
Syntechem Co.,Ltd[email protected]
上海迈瑞尔生化科技有限公司4006356688 18621169109 · [email protected]
上海颖心实验室设备有限公司021-59178156 17002132182 · [email protected]
阿法埃莎(中国)化学有限公司400-6106006 · [email protected]
太原市瑞和丰科贸有限公司+86 351 7031519 · [email protected]
上海德默医药科技有限公司400-021-7337 2355568890 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
武汉凯威斯科技有限公司86-027-67849912 · [email protected]
梯希爱(上海)化工贸易有限公司021-61109150 · [email protected]
广东方信生物科技有限公司0751-2838688 13376594225 · [email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
北京博奥森生物技术有限公司400-901-9800 18611424007 · [email protected]
嘉兴市艾森化工有限公司0573-85285100 18627885956 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
广东谦进化学试剂有限公司0751-2818792 13435114148 · [email protected]
山东艺鸿化工有限公司15253143303 15269100373
上海毕楷科技有限公司18516304666
合肥朝博科技有限公司19322001459
HONG KONG IPURE BIOLOGY CO.,LIMITED86 18062405514 18062405514 · [email protected]
Xiamen AmoyChem Co., Ltd+86-86-5926051114 · [email protected]
Wuhan Demeikai Biotechnology Co., Ltd+8618942921723 · [email protected]
北京伊诺凯科技有限公司15652467323 · [email protected]
苏州思变化学技术有限公司0512-65617459 18915409046 · [email protected]
TCI AMERICA800-4238616 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
TCI Europe320-37350700 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
武汉卡诺斯科技有限公司153-37111468 15337111468 · [email protected]
上氟科技021-65170832 15601903708
Clearsynth Labs Limited+91-22-26355700 · [email protected]
金瓯生物医药(南京)有限公司13000000000 · [email protected]
南京世洲生物科技有限公司13675144456 · [email protected]
石家庄鲲翔达科技有限公司0311-89683399 15373948595
杭州杰恒化工有限公司0571-87396432 · [email protected]
凯试(上海)科技有限公司021-50135380 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
Sigma-Aldrich西格玛奥德里奇(上海)贸易有限公司021-61415566 800-8193336 · [email protected]
江苏倍达医药科技有限公司0512-63009836 18994340901 · [email protected]
Zugehörige Reaktionen
26


Verknüpfte Notizen
Wird geladen…