
Grundinformationen
- Standard-SMILES
CC(C)c1nc(N(C)S(C)(=O)=O)nc(-c2ccc(F)cc2)c1/C=C/[C@@H](O)C[C@@H](O)CC(=O)O- InChIKey
BPRHUIZQVSMCRT-VEUZHWNKSA-N- Summenformel
- C22H28FN3O6S
- Durchschnittliche Molmasse
- 481,5 g/mol
- Monoisotopische Masse
- 481,16828484
Überblick
Rosuvastatin is a dihydroxy monocarboxylic acid that is (6E)-7-{4-(4-fluorophenyl)-2-[methyl(methylsulfonyl)amino]-6-(propan-2-yl)pyrimidin-5-yl} hept-6-enoic acid carrying two hydroxy substituents at positions 3 and 5 (the 3R,5S-diastereomer). It has a role as an antilipemic drug, a xenobiotic, a CETP inhibitor, an anti-inflammatory agent, a cardioprotective agent and an environmental contaminant. It is a sulfonamide, a dihydroxy monocarboxylic acid, a member of pyrimidines, a member of monofluorobenzenes and a statin (synthetic). It is functionally related to a hept-6-enoic acid. It is a conjugate acid of a rosuvastatin(1-).
Namen und Bezeichner
- Bevorzugter Name
- Rosuvastatin
- IUPAC
- (E,3R,5S)-7-[4-(4-fluorophenyl)-2-[methyl(methylsulfonyl)amino]-6-propan-2-ylpyrimidin-5-yl]-3,5-dihydroxyhept-6-enoic acid
- Englischer Name
- Rosuvastatin
- Summenformel
- C22H28FN3O6S
- Molmasse
- 481.54
Namen und Synonyme
Rosuvastatin287714-41-4CrestonX-PlendedZD-4522ZD4522Rosuvastatina413KH5ZJ73DTXSID8048492CHEBI:38545(3R,5S,6E)-7-(4-(4-fluorophenyl)-6-(1-methylethyl)-2-(ethyl(methylsulfonyl)amino)-5-pyrimidinyl)-3,5-dihydroxy-6-heptenoic acid(3R,5S,6E)-7-{4-(4-fluorophenyl)-6-isopropyl-2-[methyl(methylsulfonyl)amino]pyrimidin-5-yl}-3,5-dihydroxyhept-6-enoic acid
Weitere Namen anzeigen
CRESTORRosuvastatin AcidCRESTORCS-111Rosuvastatin- IP/EPROSUVASTATIN (ZD 4522)Rosuvastatin USP/EP/BP"(3R,5S)-Rosuvastatin"Rosuvastatin IP/EP/USP
6-Heptenoic acid, 7-(4-(4-fluorophenyl)-6-(1-methylethyl)-2-(ethyl(methylsulfonyl)amino)-5-pyrimidinyl)-3,5-dihydroxy-, (3R,5S,6E)(3R,5S,6E)-7-(4-(4-FLUOROPHENYL)-6-ISOPROPYL-2-(METHYL(METHYLSULFONYL)AMINO)PYRIMIDIN-5-YL)-3,5-DIHYDROXYHEPT-6-ENOIC ACIDrosuvastatinum(3R,5S)-7-(4-(4-fluorophenyl)-2-(methyl-methylsulfonylamino)-6-propan-2-ylpyrimidin-5-yl)-3,5-dihydroxyhept-6-enoic acid(3R,5S)-7-[4-(4-fluorophenyl)-2-(methyl-methylsulfonylamino)-6-propan-2-ylpyrimidin-5-yl]-3,5-dihydroxyhept-6-enoic acidRefChem:6205C10AA07DTXCID90820057
Datenbank-Bezeichner
- CAS
287714-41-4- PubChem CID
- 446157
- DTXSID
DTXSID8048492- ChEMBL
CHEMBL1496- ChEBI
CHEBI:38545- UNII
- 413KH5ZJ73
- EC Number
- 689-191-5
- Nikkaji
- J3.118.169K
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 1,6
- Polarare Oberfläche (TPSA)
- 149 Ų
- H-Brücken-Donoren
- 3
- H-Brücken-Akzeptoren
- 10
- Frei drehbare Bindungen
- 10
- Schwere Atome
- 33
- Formalladung
- 0
- Komplexität
- 767
Experimentelle und physikochemische Eigenschaften
Drugs
Pharmaceuticals -> Antilipidemics
Pharmaceuticals -> Statins
Pharmaceuticals -> Used in Switzerland
Pharmaceuticals -> Listed in ZINC15
LogP
Kow = 0.13 (pH 7.0) /log Kow = -0.88/
2.4
Solubility
Sparingly soluble in water
8.86e-02 g/L
Human DrugsBreast Feeding; Lactation; Milk, Human; Anticholesteremic Agents; Hypolipidemic Agents; Hydroxymethylglutaryl-CoA Reductase Inhibitors
Optical Rotation
White powder from water as the monohydrate; begins to melt at 155 °C with no definitive MP. Specific optical rotation: +14.8 deg at 24 °C/D (c = 1.012 in 50% methanol). Sparingly soluble in water, methanol; slightly soluble in ethanol /Rosuvastatin calcium salt/
Physical DescriptionSolid
Stability/Shelf LifeStable under recommended storage conditions. /Rosuvastatin calcium/
Ionization Efficiency
Positive
2.53
2.7
Agilent XCT
Electrospray ionization
formic acid (5.3nM)
Collision Cross Section213.85 Ų [M+K]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
Other Experimental PropertiespKa = 4.76; log Kow = 0.26-0.30 at pH 7.0. Solubility in water: 3820 mg/L (pH 5), 22,000 mg/L (pH 7), 4860 mg/l (pH 9). /Rosuvastatin calcium/
Physikochemische Eigenschaften
- Schmelzpunkt
- 161.9 °C · 161.9 °C
- Siedepunkt
- 745.6 · 745.6±70.0 °C(Predicted)
- Dichte
- 1.368 · 1.368±0.06 g/cm3(Predicted)
- storage temp.
- -20 °C · Sealed in dry,Store in freezer, under -20°C
- Löslichkeit
- DMSO (Slightly), Methanol (Slightly), Water (Slightly)
- Aggregatzustand
- Solid
- pka
- 4.25 · 4.25±0.10(Predicted)
- Farbe
- White to Pale Beige
- Henry's Law Constant
- 2.9 · 2.9×1014 mol/(m3Pa) at 25℃, HSDB (2015)
- BCS Class
- 3 · 3
- Major Application
- pharmaceutical
- InChIKey
- BPRHUIZQVSMCRT-VEUZHWNKSA-N
- SMILES
- C(O)(=O)C[C@H](O)C[C@H](O)/C=C/C1=C(C(C)C)N=C(N(C)S(C)(=O)=O)N=C1C1=CC=C(F)C=C1
- CAS Datenbank
- 287714 · 287714-41-4(CAS DataBase Reference)
- EPA chemische Informationen
- 6 · 6-Heptenoic acid, 7-[4-(4-fluorophenyl)-6-(1-methylethyl)-2-[methyl(methylsulfonyl)amino]-5-pyrimidinyl]-3,5-dihydroxy-, (3R,5S,6E)- (287714-41-4)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Danger
H351 (90%): Suspected of causing cancer [Warning Carcinogenicity]
P203, P273, P280, P318, P391, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 10 reports by companies from 2 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Gefahrenhinweise
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including rosuvastatin calcium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Rosuvastatin calcium/
Hazard Classes and CategoriesCarc. 2 (90%)
Hazardous Reactivities and IncompatibilitiesIncompatible materials: Strong oxidizing agents. /Rosuvastatin calcium/
Sicherheit und Schutzausrüstung
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide. /Rosuvastatin calcium/
Advice for firefighters: Wear self-contained breathing apparatus for firefighting if necessary. /Rosuvastatin calcium/
Storage Conditions
Store at controlled room temperature, 20-25 °C (68-77 °F). Protect from moisture.
Keep container tightly closed in a dry and well-ventilated place. Storage class (TRGS 510): Non Combustible Solids. /Rosuvastatin calcium/
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Avoid dust formation. Avoid breathing vapors, mist or gas. Environmental precautions: No special environmental precautions required. Methods and materials for containment and cleaning up: Sweep up and shovel. Keep in suitable, closed containers for disposal. /Rosuvastatin calcium/
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company; Contaminated packaging: Dispose of as unused product. /Rosuvastatin calcium/
Preventive Measures
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Avoid dust formation. Avoid breathing vapors, mist or gas. Environmental precautions: No special environmental precautions required. /Rosuvastatin calcium/
Precautions for safe handling: Further processing of solid materials may result in the formation of combustible dusts. The potential for combustible dust formation should be taken into consideration before additional processing occurs. Provide appropriate exhaust ventilation at places where dust is formed. /Rosuvastatin calcium/
Appropriate engineering controls: General industrial hygiene practice. /Rosuvastatin calcium/
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands. /Rosuvastatin calcium/
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Personal Protective Equipment (PPE)
Eye/face protection: Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU). /Rosuvastatin calcium/
Skin protection: Handle with gloves. /Rosuvastatin calcium/
Body Protection: Choose body protection in relation to its type, to the concentration and amount of dangerous substances, and to the specific work-place. /Rosuvastatin calcium/
Respiratory protection: Respiratory protection is not required. Where protection from nuisance levels of dusts are desired, use type N95 (US) or type P1 (EN 143) dust masks. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU). /Rosuvastatin calcium/
Toxikologische Informationen
Body BurdenDistributed into milk in animals; not known whether rosuvastatin is distributed into milk in humans.
TreatmentAfter ingestion exposure, administer charcoal as a slurry. In case of Rhabdomyolosis, administer sufficient 0.9% saline to maintain urine output of 2 to 3 mL/kg/hr. (L1160)
Interactions
Concomitant use of rosuvastatin and ritonavir-boosted tipranavir produces minimal to no change in exposure to rosuvastatin. Following concomitant use of rosuvastatin (10 mg as a single dose) and ritonavir-boosted tipranavir (tipranavir 500 mg with ritonavir 200 mg twice daily for 11 days), rosuvastatin peak plasma concentration and AUC were increased by twofold and 26%, respectively. Caution is advised if rosuvastatin is used concomitantly with ritonavir-boosted tipranavir.
Concomitant use of rosuvastatin and antilipemic dosages (1 g daily or higher) of niacin may increase the risk of myopathy. Data from several large randomized studies indicate that concomitant use of niacin (1.5-2 g daily) with another statin (i.e., simvastatin 40-80 mg once daily, with or without ezetimibe) resulted in an increased risk of severe adverse effects, including disturbances in glycemic control requiring hospitalization, development of diabetes mellitus, adverse GI effects, myopathy, gout, rash, skin ulceration, infection, and bleeding. Caution is advised if rosuvastatin is used concomitantly with antilipemic dosages of niacin.
Following concomitant use of rosuvastatin (single 20-mg dose) with lomitapide (10 mg once daily for 7 days), peak plasma concentration and AUC of rosuvastatin were increased by 6 and 2%, respectively. Following concomitant use of rosuvastatin (single 20-mg dose) with lomitapide (60 mg once daily for 7 days), peak plasma concentration and AUC of rosuvastatin were increased by 4 and 32%, respectively. Dosage adjustment of rosuvastatin is not required during concomitant use with lomitapide.
Concomitant use of rosuvastatin (80 mg as a single dose) and ketoconazole (200 mg twice daily for 7 days) decreased rosuvastatin peak plasma concentration by 5% and increased rosuvastatin AUC by 2%.
For more Interactions (Complete) data for Rosuvastatin (25 total), please visit the HSDB record page.
Health Effects
Health effects include abdominal pain, dizziness, hypersensitivity (including rash, pruritus, urticaria, and angioedema) and pancreatitis. The following laboratory abnormalities have also been reported: dipstick-positive proteinuria and microscopic hematuria; elevated creatine phosphokinase, transaminases, glucose, glutamyl transpeptidase, alkaline phosphatase, and bilirubin; and thyroid function abnormalities (A308).
Hepatotoxicity
Rosuvastatin therapy is associated with mild, asymptomatic and usually transient serum aminotransferase elevations in 1% to 3% of patients. ALT levels above 3 times the upper limit of normal (ULN) occur slightly more frequently among rosuvastatin treated [1.1%] than placebo [0.5%] recipients. Serum enzyme elevations are more common with higher doses of rosuvastatin, being 2.2% with 40 mg daily. Most of these elevations are self-limited and do not require dose modification. Rosuvastatin is also associated with frank, clinically apparent hepatic injury but this is rare, estimated to occur in only 1:16,000 patients, a rate that is lower than atorvastatin (1:10,000) but higher than simvastatin (1:52,000). The onset is typically after 2 to 4 months and the pattern of serum enzyme elevations is usually hepatocellular, although cholestatic cases have also been reported. Rash, fever and eosinophilia are uncommon. Several statins including rosuvastatin have been linked to hepatitis with autoimmune features marked by ANA positivity, elevations in serum immunoglobulin levels, and a clinical response to corticosteroids. Such features are not, however, invariable (Case 1). The injury is usually self-limited and resolves rapidly once rosuvastatin is stopped, but it can be severe and fatal instances have been reported.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 48(SRC), determined from a structure estimation method(2), indicates that rosuvastatin is expected to have very high mobility in soil(SRC). The estimated pKa of rosuvastatin is 4.0(3), indicating that this compound will exist almost entirely in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization from moist soil is not expected because the compound exists as an anion and anions do not volatilize(SRC). Rosuvastatin is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 5.3X10⁻¹⁹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2). Biodegradation half-lives of 3.1 and 5.2 days were reported for rosuvastatin calcium in the Modified OECD 302B test(5) suggesting that biodegradation of rosuvastatin may be an important environmental fate process in soil(SRC). However, <1% of rosuvastatin calcium was mineralized(5).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 48(SRC), determined from a structure estimation method(2), indicates that rosuvastatin is not expected to adsorb to suspended solids and sediment(SRC). The estimated pKa of 4.0(3) indicates rosuvastatin will exist almost entirely in the anion form at pH values of 5 to 9 and, therefore, volatilization from water surfaces is not expected to be an important fate process(SRC). According to a classification scheme(4), an estimated BCF of 3(SRC), from its log Kow of -0.88(5) and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is low(SRC). Biodegradation half-lives of 3.1 and 5.2 days were reported for rosuvastatin calcium in the Modified OECD 302B test(6) suggesting that biodegradation of rosuvastatin may be an important environmental fate process in water(SRC). However, <1% of rosuvastatin calcium was mineralized(6).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), rosuvastatin, which has an estimated vapor pressure of 5.3X10⁻¹⁹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase rosuvastatin may be removed from the air by wet and dry deposition(SRC). Rosuvastatin contains chromophores that absorb at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Adverse EffectsClinically Relevant Adverse Effects
Exposure Routes
Inhalation. Bioavailability is approximately 20%. Peak plasma concentrations were reached 3 to 5 hours following oral dosing. Both Cmax and AUC increased in approximate proportion to CRESTOR dose. Food has no effect on the AUC of rosuvastatin.
Milk Concentrations
EXPERIMENTAL: It is not known whether rosuvastatin is excreted in human milk. Studies in lactating rats have demonstrated that rosuvastatin is secreted into breast milk at levels 3 times higher than that obtained in the plasma following oral gavage dosing.
Toxicity Summary
IDENTIFICATION AND USE: Rosuvastatin is hydroxymethylglutaryl-CoA reductase inhibitor. It is is indicated to reduce the risk of stroke, myocardial infarction, and arterial revascularization procedures. HUMAN EXPOSURE AND TOXICITY: Rosuvastatin is the most potent 3-hydroxy-3-methyl-glutaryl-coenzyme A reductase inhibitor commercially available to lower low-density lipoprotein cholesterol. Rosuvastatin has been associated with several adverse effects, including rhabdomyolysis and arthralgias. Myopathy and rhabdomyolysis with acute renal failure secondary to myoglobinuria have been reported in patients receiving statins, including rosuvastatin. These adverse effects can occur at any dosage, but the risk is increased with the highest dosage of rosuvastatin (40 mg daily). There is a report of Takotsubo cardiomyopathy, triggered by delayed-onset rhabdomyolysis following the administration of long-term rosuvastatin treatment, without any preceding stressors or changes in the patient's medical condition, in association with complaints of non-specific muscle-related symptoms. Literature reported the case of a marathon runner who presented with acute rhabdomyolysis during competition while being under rosuvastatin treatment. A 77-year-old patient developed acute pancreatitis after treatment with rosuvastatin, which resolved on withdrawal of the medication. There have been rare postmarketing reports of fatal and non-fatal hepatic failure in patients taking statins, including rosuvastatin. The genotoxic potential of rosuvastatin was assessed by chromosomal aberrations (CAs), micronucleus (MN) and DNA damage by comet assay in human peripheral blood lymphocytes. According to these results, rosuvastatin is cytotoxic and clastogenic/aneugenic in human peripheral lymphocytes. ANIMAL STUDIES: Rosuvastatin was shown to be of low acute toxicity following administration of single doses to rats and dogs by oral and intravenous routes. There were no mortalities in rats given an oral dose of 1000 mg/kg or 2000 mg/kg, and other than depression of bodyweight at 2000 mg/kg, there were no treatment-related effects at either dose level. Dogs received oral doses of 1000 mg/kg or 2000 mg/kg with vomiting on the day of dosing observed as the major clinical finding in both sexes. In a 104-week carcinogenicity study in rats at dose levels of 2, 20, 60 or 80 mg/kg/day, the incidence of uterine polyps was statistically significantly increased only in females at the dose of 80 mg/kg/day. In a 107-week carcinogenicity study in mice given 10, 60, 200 or 400 mg/kg/day, the 400 mg/kg/day dose was poorly tolerated, resulting in early termination of this dose group. An increased incidence of hepatocellular carcinomas was observed at 200 mg/kg/day and an increase in hepatocellular adenomas was seen at 60 and 200 mg/kg/day. Rosuvastatin administration did not indicate a teratogenic effect in rats at </= 25 mg/kg/day or in rabbits </= 3 mg/kg/day. In vitro, rosuvastatin was not mutagenic or clastogenic with or without metabolic activation in the Ames test with Salmonella typhimurium and Escherichia coli, L-5178 y +/- mouse lymphomas, and the chromosomal aberration assay in Chinese hamster lung cells. Rosuvastatin was negative in the in vivo mouse micronucleus test.
Signs and Symptoms of Overdose
Rosuvastatin is a competitive inhibitor of HMG-CoA reductase. HMG-CoA reductase catalyzes the conversion of HMG-CoA to mevalonate, an early rate-limiting step in cholesterol biosynthesis. Rosuvastatin acts primarily in the liver. Decreased hepatic cholesterol concentrations stimulate the upregulation of hepatic low density lipoprotein (LDL) receptors which increases hepatic uptake of LDL. Rosuvastatin also inhibits hepatic synthesis of very low density lipoprotein (VLDL). The overall effect is a decrease in plasma LDL and VLDL. In vitro and in vivo animal studies also demonstrate that rosuvastatin exerts vasculoprotective effects independent of its lipid-lowering properties. Rosuvastatin exerts an anti-inflammatory effect on rat mesenteric microvascular endothelium by attenuating leukocyte rolling, adherence and transmigration (A2814). The drug also modulates nitric oxide synthase (NOS) expression and reduces ischemic-reperfusion injuries in rat hearts (A2818). Rosuvastatin increases the bioavailability of nitric oxide (A2814, 12031849, 15914111) by upregulating NOS (A2816) and by increasing the stability of NOS through post-transcriptional polyadenylation (A7824). It is unclear as to how rosuvastatin brings about these effects though they may be due to decreased concentrations of mevalonic acid.
Signs and Symptoms
Generally well-tolerated. Side effects may include myalgia, constipation, asthenia, abdominal pain, and nausea. Other possible side effects include myotoxicity (myopathy, myositis, rhabdomyolysis) and hepatotoxicity. To avoid toxicity in Asian patients, lower doses should be considered. Pharmacokinetic studies show an approximately two-fold increase in peak plasma concentration and AUC in Asian patients (Philippino, Chinese, Japanese, Korean, Vietnamese, or Asian-Indian descent) compared to Caucasians patients.
Effluent ConcentrationsRosuvastatin was detected in 36% of samples at an average concentration of 31.0 ng/L (max 979 ng/L) following EU monitoring of 90 wastewater treatment plant effluents conducted in 2010; detection limit = 10 ng/L(1).
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including rosuvastatin calcium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Rosuvastatin calcium/
Sicherheitsdaten
- wgk
- WGK 3
- Speicherklasse
- 11 - Combustible Solids
- Giftige Stoffe Daten
- 287714-41-4(Hazardous Substances Data)
- Hazard Classifications
- Aquatic Chronic 2
Chemie und Industrie
Pharmakologische Informationen
ATC Code
C10AA07
C - Cardiovascular system
QC - Cardiovascular system
Protein BindingRosuvastatin is 88% bound to plasma proteins, mostly albumin. This binding is reversible and independent of plasma concentrations.
Pharmacodynamics
Rosuvastatin is a synthetic, enantiomerically pure antilipemic agent. It is used to lower total cholesterol, low density lipoprotein-cholesterol (LDL-C), apolipoprotein B (apoB), non-high density lipoprotein-cholesterol (non-HDL-C), and trigleride (TG) plasma concentrations while increasing HDL-C concentrations. High LDL-C, low HDL-C and high TG concentrations in the plasma are associated with increased risk of atherosclerosis and cardiovascular disease. The total cholesterol to HDL-C ratio is a strong predictor of coronary artery disease and high ratios are associated with higher risk of disease. Increased levels of HDL-C are associated with lower cardiovascular risk. By decreasing LDL-C and TG and increasing HDL-C, rosuvastatin reduces the risk of cardiovascular morbidity and mortality. Elevated cholesterol levels, and in particular, elevated low-density lipoprotein (LDL) levels, are an important risk factor for the development of CVD. Use of statins to target and reduce LDL levels has been shown in a number of landmark studies to significantly reduce the risk of development of CVD and all-cause mortality. Statins are considered a cost-effective treatment option for CVD due to their evidence of reducing all-cause mortality including fatal and non-fatal CVD as well as the need for surgical revascularization or angioplasty following a heart attack. Evidence has shown that even for low-risk individuals (with <10% risk of a major vascular event occurring within 5 years) statins cause a 20%-22% relative reduction in major cardiovascular events (heart attack, stroke, coronary revascularization, and coronary death) for every 1 mmol/L reduction in LDL without any significant side effects or risks. **Skeletal Muscle Effects** Cases of myopathy and rhabdomyolysis with acute renal failure secondary to myoglobinuria have been reported with HMG-CoA reductase inhibitors, including rosuvastatin. These risks can occur at any dose level, but are increased at the highest dose (40 mg). Rosuvastatin should be prescribed with caution in patients with predisposing factors for myopathy (e.g., age ≥ 65 years, inadequately treated hypothyroidism, renal impairment). The risk of myopathy during treatment with rosuvastatin may be increased with concurrent administration of some other lipid-lowering therapies (such as [fenofibrate] or [niacin]), [gemfibrozil], [cyclosporine], [atazanavir]/[ritonavir], [lopinavir]/ritonavir, or [simeprevir]. Cases of myopathy, including rhabdomyolysis, have been reported with HMG-CoA reductase inhibitors, including rosuvastatin, coadministered with [colchicine], and caution should therefore be exercised when prescribing these two medications together. Real-world data from observational studies has suggested that 10-15% of people taking statins may experience muscle aches at some point during treatment. **Liver Enzyme Abnormalities** Increases in serum transaminases have been reported with HMG-CoA reductase inhibitors, including rosuvastatin. In most cases, the elevations were transient and resolved or improved on continued therapy or after a brief interruption in therapy. There were two cases of jaundice, for which a relationship to rosuvastatin therapy could not be determined, which resolved after discontinuation of therapy. There were no cases of liver failure or irreversible liver disease in these trials. **Endocrine Effects** Increases in HbA1c and fasting serum glucose levels have been reported with HMG-CoA reductase inhibitors, including rosuvastatin calcium tablets. Based on clinical trial data with rosuvastatin, in some instances these increases may exceed the threshold for the diagnosis of diabetes mellitus. An in vitro study found that [atorvastatin], [pravastatin], [rosuvastatin], and [pitavastatin] exhibited a dose-dependent cytotoxic effect on human pancreas islet β cells, with reductions in cell viability of 32, 41, 34 and 29%, respectively, versus control]. Moreover, insulin secretion rates were decreased by 34, 30, 27 and 19%, respectively, relative to control. HMG-CoA reductase inhibitors interfere with cholesterol synthesis and lower cholesterol levels and, as such, might theoretically blunt adrenal or gonadal steroid hormone production. Rosuvastatin demonstrated no effect upon nonstimulated cortisol levels and no effect on thyroid metabolism as assessed by TSH plasma concentration. In rosuvastatin treated patients, there was no impairment of adrenocortical reserve and no reduction in plasma cortisol concentrations. Clinical studies with other HMG-CoA reductase inhibitors have suggested that these agents do not reduce plasma testosterone concentration. The effects of HMG-CoA reductase inhibitors on male fertility have not been studied. The effects, if any, on the pituitarygonadal axis in premenopausal women are unknown. **Cardiovascular** Ubiquinone levels were not measured in rosuvastatin clinical trials, however significant decreases in circulating ubiquinone levels in patients treated with other statins have been observed. The clinical significance of a potential long-term statin-induced deficiency of ubiquinone has not been established. It has been reported that a decrease in myocardial ubiquinone levels could lead to impaired cardiac function in patients with borderline congestive heart failure. **Lipoprotein A** In some patients, the beneficial effect of lowered total cholesterol and LDL-C levels may be partly blunted by a concomitant increase in the Lipoprotein(a) [Lp(a)] concentrations. Present knowledge suggests the importance of high Lp(a) levels as an emerging risk factor for coronary heart disease. It is thus desirable to maintain and reinforce lifestyle changes in high-risk patients placed on rosuvastatin therapy. Further studies have demonstrated statins affect Lp(a) levels differently in patients with dyslipidemia depending on their apo(a) phenotype; statins increase Lp(a) levels exclusively in patients with the low molecular weight apo(a) phenotype.
Mechanism of Action
Rosuvastatin is a statin medication and a competitive inhibitor of the enzyme HMG-CoA (3-hydroxy-3-methylglutaryl coenzyme A) reductase, which catalyzes the conversion of HMG-CoA to mevalonate, an early rate-limiting step in cholesterol biosynthesis. Rosuvastatin acts primarily in the liver, where decreased hepatic cholesterol concentrations stimulate the upregulation of hepatic low density lipoprotein (LDL) receptors which increases hepatic uptake of LDL. Rosuvastatin also inhibits hepatic synthesis of very low density lipoprotein (VLDL). The overall effect is a decrease in plasma LDL and VLDL. In vitro and in vivo animal studies also demonstrate that rosuvastatin exerts vasculoprotective effects independent of its lipid-lowering properties, also known as the pleiotropic effects of statins. This includes improvement in endothelial function, enhanced stability of atherosclerotic plaques, reduced oxidative stress and inflammation, and inhibition of the thrombogenic response. Statins have also been found to bind allosterically to β2 integrin function-associated antigen-1 (LFA-1), which plays an important role in leukocyte trafficking and in T cell activation. Rosuvastatin exerts an anti-inflammatory effect on rat mesenteric microvascular endothelium by attenuating leukocyte rolling, adherence and transmigration. The drug also modulates nitric oxide synthase (NOS) expression and reduces ischemic-reperfusion injuries in rat hearts. Rosuvastatin increases the bioavailability of nitric oxide by upregulating NOS and by increasing the stability of NOS through post-transcriptional polyadenylation. It is unclear as to how rosuvastatin brings about these effects though they may be due to decreased concentrations of mevalonic acid.
Crestor is a selective and competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl coenzyme A to mevalonate, a precursor of cholesterol. In vivo studies in animals, and in vitro studies in cultured animal and human cells have shown rosuvastatin to have a high uptake into, and selectivity for, action in the liver, the target organ for cholesterol lowering. In in vivo and in vitro studies, rosuvastatin produces its lipid-modifying effects in two ways. First, it increases the number of hepatic LDL receptors on the cell-surface to enhance uptake and catabolism of LDL. Second, rosuvastatin inhibits hepatic synthesis of VLDL, which reduces the total number of VLDL and LDL particles.
Biological Half-Life
The elimination half-life (t½) of rosuvastatin is approximately 19 hours and does not increase with increasing doses.
The elimination half-life of rosuvastatin is approximately 19 hours.
Metabolism/Metabolites
Rosuvastatin is not extensively metabolized, as demonstrated by the small amount of radiolabeled dose that is recovered as a metabolite (~10%). Cytochrome P450 (CYP) 2C9 is primarily responsible for the formation of rosuvastatin's major metabolite, N-desmethylrosuvastatin, which has approximately 20-50% of the pharmacological activity of its parent compound in vitro. However, this metabolic pathway isn't deemed to be clinically significant as there were no observable effects found on rosuvastatin pharmacokinetics when rosuvastatin was coadministered with fluconazole, a potent CYP2C9 inhibitor. In vitro and in vivo data indicate that rosuvastatin has no clinically significant cytochrome P450 interactions (as substrate, inhibitor or inducer). Consequently, there is little potential for drug-drug interactions upon coadministration with agents that are metabolized by cytochrome P450.
Rosuvastatin is not extensively metabolized; approximately 10% of a radiolabeled dose is recovered as metabolite. The major metabolite is N-desmethyl rosuvastatin, which is formed principally by cytochrome P450 \ 2C9, and in vitro studies have demonstrated that N-desmethyl rosuvastatin has approximately one-sixth to one-half the HMG-CoA reductase inhibitory activity of the parent compound. Overall, greater than 90% of active plasma HMG-CoA reductase inhibitory activity is accounted for by the parent compound.
Not extensively metabolized. Only ~10% is excreted as metabolite. Cytochrome P450 (CYP) 2C9 is primarily responsible for the formation of rosuvastatin's major metabolite, N-desmethylrosuvastatin. N-desmethylrosuvastatin has approximately 50% of the pharmacological activity of its parent compound in vitro. Rosuvastatin clearance is not dependent on metabolism by cytochrome P450 3A4 to a clinically significant extent. Rosuvastatin accounts for greater than 90% of the pharmacologic action. Inhibitors of CYP2C9 increase the AUC by less than 2-fold. This interaction does not appear to be clinically significant. Route of Elimination: Rosuvastatin is not extensively metabolized; approximately 10% of a radiolabeled dose is recovered as metabolite. Following oral administration, rosuvastatin and its metabolites are primarily excreted in the feces (90%). After an intravenous dose, approximately 28% of total body clearance was via the renal route, and 72% by the hepatic route. Half Life: 19 hours
FDA Pharmacological Classification
413KH5ZJ73
ROSUVASTATIN
Established Pharmacologic Class [EPC] - HMG-CoA Reductase Inhibitor
Mechanisms of Action [MoA] - Hydroxymethylglutaryl-CoA Reductase Inhibitors
Rosuvastatin is a HMG-CoA Reductase Inhibitor. The mechanism of action of rosuvastatin is as a Hydroxymethylglutaryl-CoA Reductase Inhibitor.
ROSUVASTATIN
MeSH Pharmacological Classification
Substances used to lower plasma CHOLESTEROL levels.
Compounds that inhibit HYDROXYMETHYLGLUTARYL COA REDUCTASES. They have been shown to directly lower CHOLESTEROL synthesis.
Absorption, Distribution and Excretion
In a study of healthy white male volunteers, the absolute oral bioavailability of rosuvastatin was found to be approximately 20% while absorption was estimated to be 50%, which is consistent with a substantial first-pass effect after oral dosing. Another study in healthy volunteers found that the peak plasma concentration (Cmax) of rosuvastatin was 6.06ng/mL and was reached at a median of 5 hours following oral dosing. Both Cmax and AUC increased in approximate proportion to dose. Neither food nor evening versus morning administration was shown to have an effect on the AUC of rosuvastatin. Many statins are known to interact with hepatic uptake transporters and thus reach high concentrations at their site of action in the liver. Breast Cancer Resistance Protein (BCRP) is a membrane-bound protein that plays an important role in the absorption of rosuvastatin, particularly as CYP3A4 has minimal involvement in its metabolism. Evidence from pharmacogenetic studies of c.421C>A single nucleotide polymorphisms (SNPs) in the gene for BCRP has demonstrated that individuals with the 421AA genotype have reduced functional activity and 2.4-fold higher AUC and Cmax values for rosuvastatin compared to study individuals with the control 421CC genotype. This has important implications for the variation in response to the drug in terms of efficacy and toxicity, particularly as the BCRP c.421C>A polymorphism occurs more frequently in Asian populations than in Caucasians. Other statin drugs impacted by this polymorphism include [fluvastatin] and [atorvastatin]. Genetic differences in the OATP1B1 (organic-anion-transporting polypeptide 1B1) hepatic transporter have also been shown to impact rosuvastatin pharmacokinetics. Evidence from pharmacogenetic studies of the c.521T>C SNP showed that rosuvastatin AUC was increased 1.62-fold for individuals homozygous for 521CC compared to homozygous 521TT individuals. Other statin drugs impacted by this polymorphism include [simvastatin], [pitavastatin], [atorvastatin], and [pravastatin]. For patients known to have the above-mentioned c.421AA BCRP or c.521CC OATP1B1 genotypes, a maximum daily dose of 20mg of rosuvastatin is recommended to avoid adverse effects from the increased exposure to the drug, such as muscle pain and risk of rhabdomyolysis.
Rosuvastatin is not extensively metabolized; approximately 10% of a radiolabeled dose is recovered as metabolite. Following oral administration, rosuvastatin and its metabolites are primarily excreted in the feces (90%). After an intravenous dose, approximately 28% of total body clearance was via the renal route, and 72% by the hepatic route. A study in healthy adult male volunteers found that approximately 90% of the rosuvastatin dose was recovered in feces within 72 hours after dose, while the remaining 10% was recovered in urine. The drug was completely excreted from the body after 10 days of dosing. They also found that approximately 76.8% of the excreted dose was unchanged from the parent compound, with the remaining dose recovered as the metabolites n-desmethyl rosuvastatin and rosuvastatin-5S-lactone. Renal tubular secretion is responsible for >90% of total renal clearance, and is believed to be mediated primarily by the uptake transporter OAT3 (Organic anion transporter 1), while OAT1 had minimal involvement.
Rosuvastatin undergoes first-pass extraction in the liver, which is the primary site of cholesterol synthesis and LDL-C clearance. The mean volume of distribution at steady-state of rosuvastatin is approximately 134 litres.
In clinical pharmacology studies in man, peak plasma concentrations of rosuvastatin were reached 3 to 5 hours following oral dosing. Both Cmax and AUC increased in approximate proportion to Crestor dose. The absolute bioavailability of rosuvastatin is approximately 20%. Administration of Crestor with food did not affect the AUC of rosuvastatin. The AUC of rosuvastatin does not differ following evening or morning drug administration.
Mean volume of distribution at steady-state of rosuvastatin is approximately 134 liters. Rosuvastatin is 88% bound to plasma proteins, mostly albumin. This binding is reversible and independent of plasma concentrations.
Following oral administration, rosuvastatin and its metabolites are primarily excreted in the feces (90%). ... After an intravenous dose, approximately 28% of total body clearance was via the renal route, and 72% by the hepatic route.
Cellular LocationsExtracellular
Metabolite PathwaysRosuvastatin Action Pathway
Verwendung und Herstellung
Uses
Hydroxymethylglutaryl-CoA Reductase Inhibitors
MEDICATION
Use (kg; approx.) in Germany (2009): >100
Used as an adjunct to dietary therapy to treat primary hyperlipidemia (heterozygous familial and nonfamilial), mixed dyslipidemia and hypertriglyceridemia. Also indicated for homozygous familial hypercholesterolemia as an adjunct to other lipid-lowering therapies or when other such therapies are not available. Furthermore, it is used to slow the progression of atherosclerosis and for primary prevention of cardiovascular disease.
Methods of Manufacturing
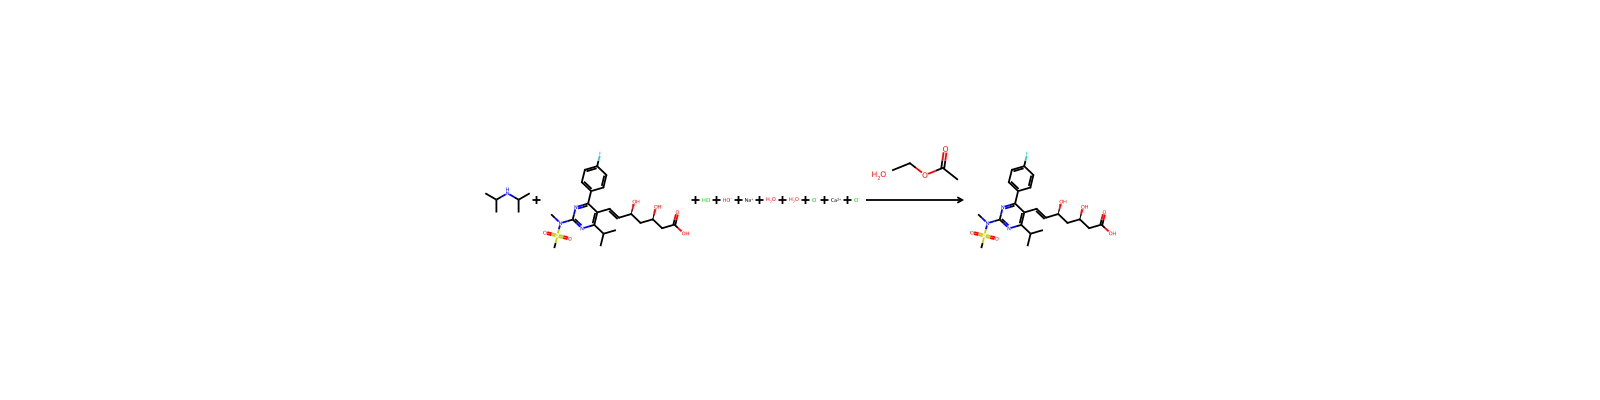
The preparation of the intermediate ethyl 4-(4-fluorophenyl)-6-isopropyl-2-(N-methyl-N-methylsulfonylamino)pyrimidine-5-carboxylate occur according to standard chemical procedures. Reduction to the 5-hydroxymethyl derivative proceeds smoothly with diisobutylaluminum hydride (DIBALH) in toluene at -10 °C. The hydroxymethyl group is then converted to the bromo derivative, which upon reaction with triphenylphosphine affords the Wittig reagent. The latter is treated with tert-butyl 2-[(4R,6S)-6-formyl-2,2-dimethyl-1,3-dioxan-4-yl]acetate and provides the protected rosuvastatin ester. Removal of the dioxane protecting group by HCl, ester hydrolysis with NaOH and precipitation with CaCl2 gives /rosuvastatin/. The 6-formyl side chain intermediate is prepared by oxidation of the corresponding 6-hydroxymethyl compound, e.g., with DMSO-oxalyl chloride.
Preparation: K. Hirai et al., European Patent Office patent 521471; eidem, United States of America patent 5260440 (both 1993 to Shionogi).
Formulations/PreparationsTable: Rosuvastatin Preparations [Table#6909]
Anwendungen
BeschreibungRosuvastatin is the most recent FDA-approved statin (doses 5–40 mg) for the treatment of dyslipidemia. Rosuvastatin, which has a structure similar to other synthetic statins, has a long halflife (20–24 hours) similar to atorvastatin and hydrophilicity comparable to pravastatin. Consequently, rosuvastatin is minimally metabolized and has no significant cytochrome P450 drug interactions. The efficacy of rosuvastatin is superior to that of other statins. Compared to atorvastatin, rosuvastatin provides approximately an 8% additional lowering of LDL-C on an equivalent dose level. This provides modestly more efficacy than a doubling of the dose of atorvastatin. Rosuvastatin also increases HDL-C slightly more than atorvastatin, especially at the highest doses.
HistoryRosuvastatin, marketed as Crestor, is an HMG-CoA reductase inhibitor and a synthetic statin, a class of lipid-lowering drugs. Its development began with a research team at Shionogi & Co., Ltd. in Japan, aiming to develop a compound that was more effective and better tolerable than existing statins. The discovery and patent application of this compound are primarily attributed to Shionogi's team of chemists, with key inventors including Kentaro Hirai, Teruyuki Ishiba, Haruo Koike, and Masamichi Watanabe. The discovery of this compound dates back to the early 1990s. In 1991, Shionogi successfully synthesized rosuvastatin and filed a patent application on July 1st of the same year. Rosuvastatin's unique molecular structure includes a sulfonamide group, giving it hydrophilicity, which is believed to contribute to its potential for liver selectivity and reduced muscle toxicity. In the subsequent development and commercialization process, AstraZeneca granted AstraZeneca an exclusive global license for rosuvastatin. In 2003, rosuvastatin (Crestor) received approval from the U.S. Food and Drug Administration (FDA) for the treatment of hypercholesterolemia.
VerwendenRosuvastatin Calcium is a competitive inhibitor of HMG-CoA reductase with IC50 of 11 nM.
Darstellung
synthetischeRosuvastatin synthesis: Reduction to the 5-hydroxymethyl derivative proceeds smoothly with diisobutylaluminum hydride (DIBALH) in toluene at -10 °C. The hydroxymethyl group is then converted to the bromo derivative, which upon reaction with triphenylphosphine affords the Wittig reagent. The latter is treated with tert-butyl 2-[(4R,6S)-6-formyl-2,2-dimethyl-1,3-dioxan-4-yl]acetate and provides the protected rosuvastatin ester. Removal of the dioxane protecting group by HCl, ester hydrolysis with NaOH and precipitation with CaCl2 gives rosuvastatin.Kleemann A; Cardiovascular Drugs. Ullmann's Encyclopedia of Industrial Chemistry 7th ed. (1999-2017). NY, NY: John Wiley & Sons. Online Posting Date: January 15, 2008
Anbieter50 Anbieter
北京华美互利生物化工010-56205725 · [email protected]
南通飞宇生物科技有限公司0513-68819626 15152877458 · [email protected]
合肥翰刚医药科技有限公司+8618062405514 · [email protected]
Hong Kong Tiansheng New Material Trading Co., Ltd+8617320695765 · [email protected]
咸宁深蓝生物医药研发有限公司18171815831 · [email protected]
上海优宁维生物科技股份有限公司15921930842 15921930842 · [email protected]
普善实业(陕西)有限公司029-81310890 18165209495 · [email protected]
河北展药生物科技有限公司15369953316 +8615369953316 · [email protected]
南京世洲生物科技有限公司025-025-85560043 17301488900 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
上海晶抗生物工程有限公司021-54721350 13524668266 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
梯希爱(上海)化工贸易有限公司021-61109150 · [email protected]
InvivoChem中国13549236410 · [email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
上海隆盛化工有限公司58099637 13585536065 · [email protected]
上海尺水药物研究有限公司[email protected] 13564957716 · [email protected]
武汉丰泰威远科技有限公司+86-27-8746-5837 +86-18627785180 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
佛山宝诺生物科技有限公司0757-85921206 18520245316 · [email protected]
HONG KONG IPURE BIOLOGY CO.,LIMITED86 18062405514 18062405514 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
Wuhan NCE Biomedical Co.,Ltd.4000-027-021 |24 +86-13986109188 | +86-15623472865 | +81-08033611988
上海健超生物科技有限公司150-2103-5486 18017383231 · [email protected]
成都思天德生物科技有限公司028-83243028 19136088901 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
武汉鹏胤药业有限公司13163333255 · [email protected]
惠州拓康生物科技有限公司+86 (0752) 222-7171, +86 15815821171
上海喀露蓝科技有限公司18149758185 18149758185 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
湖南华腾制药有限公司400-8592883 · [email protected]
天津普西唐生物医药科技有限公司010-60605840 · [email protected]
上海御略医药科技有限公司021-60345187 13671753212 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
上海嵩爰化工科技有限公司010-1234567 18521000990 · [email protected]
南京百鑫德诺生物科技有限公司025-58849295 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
TargetMol中国(陶术生物)021-021-33632979 15002134094 · [email protected]
上海昕凯医药科技有限公司21-619849051-1 18521059765 · [email protected]
上海陶术生物科技股份有限公司+1-781-999-5354; +1-00000000000 · [email protected]
斯派螺(武汉)药物研发有限公司[email protected]
西安美川生物科技有限公司029-89275612 +8618991951683 · [email protected]
Hangzhou Proserre Chemical Co.,Ltd.+86-571-86088112 · [email protected]
苏州美石生物科技有限公司1173954148q · [email protected]
sgtlifesciences pvt ltd+91-8790379245 · [email protected]
上海珞珐生化科技有限公司021-51111890 15317326293 · [email protected]
Ergänzende Hinweise
DefinitionChEBI: Rosuvastatin is a dihydroxy monocarboxylic acid that is (6E)-7-{4-(4-fluorophenyl)-2-[methyl(methylsulfonyl)amino]-6-(propan-2-yl)pyrimidin-5-yl} hept-6-enoic acid carrying two hydroxy substituents at positions 3 and 5 (the 3R,5S-diastereomer). It has a role as an antilipemic drug, an anti-inflammatory agent, a CETP inhibitor, a cardioprotective agent, a xenobiotic and an environmental contaminant. It is a member of pyrimidines, a sulfonamide, a dihydroxy monocarboxylic acid, a statin (synthetic) and a member of monofluorobenzenes. It derives from a hept-6-enoic acid. It is a conjugate acid of a rosuvastatin(1-).
Zugehörige Reaktionen
16




Verknüpfte Notizen
Wird geladen…