

Grundinformationen
- Standard-SMILES
Cc1nccn1CC1CCc2c(c3ccccc3n2C)C1=O- InChIKey
FELGMEQIXOGIFQ-UHFFFAOYSA-N- Summenformel
- C18H19N3O
- Durchschnittliche Molmasse
- 293,4 g/mol
- Monoisotopische Masse
- 293,15281223
Überblick
Ondansetron is a member of carbazoles.
Namen und Bezeichner
- Bevorzugter Name
- Ondansetron
- IUPAC
- 9-methyl-3-[(2-methylimidazol-1-yl)methyl]-2,3-dihydro-1H-carbazol-4-one
- Englischer Name
- Ondansetron
- Summenformel
- C18H19N3O
- Molmasse
- 293.36
Namen und Synonyme
ondansetron99614-02-5ZudanZofran ODTZuplenz9-methyl-3-[(2-methylimidazol-1-yl)methyl]-2,3-dihydro-1H-carbazol-4-oneDTXSID80233934AF302ESOSA04AA01EUR-1025NSC-7578701,2,3,9-Tetrahydro-9-methyl-3-((2-methyl-1H-imidazol-1-yl)methyl)-4H-carbazol-4-one
Weitere Namen anzeigen
ONDANSETRON HCLONDANSETRON HYDROCHLORIDE DIHYDRATEONDANSETRON HCL DIHYDRATEOndansetroOndanestronONDANCETRON1,2,3,4-Tetrahydro-9-methyl-3-(2-methyl-1H-imidazol-1-ylmethyl)carbazol-4-oneYatroxgr38032gr38032x
9-methyl-3-[(2-methyl-1H-imidazol-1-yl)methyl]-2,3,4,9-tetrahydro-1H-carbazol-4-oneDTXCID8033931,2,3,9-tetrahydro-9-methyl-3-[(2-methyl-1H-imidazol-1-yl)methyl]-4H-carbazol-4-one4H-Carbazol-4-one, 1,2,3,9-tetrahydro-9-methyl-3-((2-methyl-1H-imidazol-1-yl)methyl)-Odansetron (common misspelling of ondansetron)Odansetron [common misspelling of ondansetron]Monohydrochloride, OndansetronMonohydrochloride Dihydrate, Ondansetron
Datenbank-Bezeichner
- CAS
99614-02-5- PubChem CID
- 4595
- DTXSID
DTXSID8023393- ChEMBL
CHEMBL46- ChEBI
CHEBI:7773- UNII
- 4AF302ESOS
- EC Number
- 619-449-4
- Nikkaji
- J245.610I
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 2,3
- Polarare Oberfläche (TPSA)
- 39,8 Ų
- H-Brücken-Donoren
- 0
- H-Brücken-Akzeptoren
- 2
- Frei drehbare Bindungen
- 2
- Schwere Atome
- 22
- Formalladung
- 0
- Komplexität
- 440
Experimentelle und physikochemische Eigenschaften
DrugsPharmaceuticals
LogP1.92
Color/FormCrystals from methanol
Solubility
Sparingly soluble in water
Very soluble in acid solutions
Human Drugs
Breast Feeding; Lactation; Milk, Human; Antiemetics; Gastrointestinal Agents; Serotonin Antagonists; Serotonin 5-HT3 Receptor Antagonists
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Antiemetic medicines
Melting Point
231-232 °C
231 - 232 °C
Physical DescriptionSolid
Stability/Shelf LifeStable under recommended storage conditions. /Ondansetron hydrochloride dihydrate/
Collision Cross Section171.7 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
Other Experimental PropertiesWhite crystalline solid from water/isopropanol. MP: 178.5-179.5 °C. pKa 7.4 /Ondanestron hydrochloride dihydrate/
Physikochemische Eigenschaften
- Schmelzpunkt
- 231 · 231-232°
- Siedepunkt
- 435.21 °C · 435.21°C (rough estimate)
- Dichte
- 1.1385 · 1.1385 (rough estimate)
- Brechungsindex
- 1.5855 · 1.5855 (estimate)
- storage temp.
- 20 °C · −20°C
- Löslichkeit
- 2 O: · H2O: >5 mg/mL
- Aggregatzustand
- solid
- pka
- 7.4 · pKa 7.4 (Uncertain)
- Farbe
- white
- InChI
- 1S/C18H19N3O/c1-12-19-9-10-21(12)11-13-7-8-16-17(18(13)22)14-5-3-4-6-15(14)20(16)2/h3-6,9-10,13H,7-8,11H2,1-2H3
- InChIKey
- FELGMEQIXOGIFQ-UHFFFAOYSA-N
- SMILES
- [n]4(c(ncc4)C)CC1CCc2[n](c3c(c2C1=O)cccc3)C
- CAS Datenbank
- 99614 · 99614-02-5(CAS DataBase Reference)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Danger
H301 (88.2%): Toxic if swallowed [Danger Acute toxicity, oral]
P203, P260, P261, P263, P264, P264+P265, P270, P271, P273, P280, P301+P316, P302+P352, P304+P340, P305+P351+P338, P305+P354+P338, P317, P318, P319, P321, P330, P332+P317, P337+P317, P362+P364, P391, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 17 reports by companies from 9 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Danger
H301: Toxic if swallowed [Danger Acute toxicity, oral]
Gefahrenhinweise
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including ondansetron, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including ondansetron hydrochloride, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Ondansetron hydrochloride/
Toxic Combustion ProductsSpecial hazards arising from the substance or mixture: Carbon oxides, nitrogen oxides (NOx), Hydrogen chloride gas /Ondansetron hydrochloride dihydrate/
Hazard Classes and CategoriesAcute Tox. 3 (88.2%)
Hazardous Reactivities and IncompatibilitiesIncompatible materials: Strong oxidizing agents /Ondansetron hydrochloride dihydrate/
Sicherheit und Schutzausrüstung
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide. /Ondansetron hydrochloride dihydrate/
Advice for firefighters: Wear self contained breathing apparatus for fire fighting if necessary. /Ondansetron hydrochloride dihydrate/
Storage Conditions
Store upright between 15 deg and 30 °C (59 deg and 86 °F). Protect from light. Store bottles upright in cartons.
Keep container tightly closed in a dry and well-ventilated place. Recommended storage temperature: -20 °C. /Ondansetron hydrochloride dihydrate/
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Wear respiratory protection. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Evacuate personnel to safe areas. Avoid breathing dust; Environmental precautions: Prevent further leakage or spillage if safe to do so. Do not let product enter drains; Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal. /Ondansetron hydrochloride dihydrate/
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company. Contact a licensed professional waste disposal service to dispose of this material. Dissolve or mix the material with a combustible solvent and burn in a chemical incinerator equipped with an afterburner and scrubber; Contaminated packaging: Dispose of as unused product. /Ondansetron hydrochloride dihydrate/
Preventive Measures
Precautions for safe handling: Avoid contact with skin and eyes. Avoid formation of dust and aerosols. Provide appropriate exhaust ventilation at places where dust is formed. Normal measures for preventive fire protection. /Ondansetron hydrochloride dihydrate/
Appropriate engineering controls: Avoid contact with skin, eyes and clothing. Wash hands before breaks and immediately after handling the product. /Ondansetron hydrochloride dihydrate/
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands. /Ondansetron hydrochloride dihydrate/
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Personal Protective Equipment (PPE)
Eye/face protection: Face shield and safety glasses. Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU). /Ondansetron hydrochloride dihydrate/
Skin protection: Handle with gloves. /Ondansetron hydrochloride dihydrate/
Body Protection: Complete suit protecting against chemicals. The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace. /Ondansetron hydrochloride dihydrate/
Respiratory protection: Where risk assessment shows air-purifying respirators are appropriate use a full-face particle respirator type N99 (US) or type P2 (EN 143) respirator cartridges as a backup to engineering controls. If the respirator is the sole means of protection, use a full-face supplied air respirator. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU). /Ondansetron hydrochloride dihydrate/
Toxikologische Informationen
TreatmentThere is no specific antidote for ondansetron overdose. Patients should be managed with appropriate supportive therapy. (L1712)
Interactions
The nephrotoxicity limits the clinical application of cisplatin. Human organic cation transporter 2 (OCT2) and multidrug and toxin extrusion proteins (MATEs) work in concert in the elimination of cationic drugs such as cisplatin from the kidney. We hypothesized that co-administration of ondansetron would have an effect on cisplatin nephrotoxicity by altering the function of cisplatin transporters. The inhibitory potencies of ondansetron on metformin accumulation mediated by OCT2 and MATEs were determined in the stable HEK-293 cells expressing these transporters. The effects of ondansetron on drug disposition in vivo were examined by conducting the pharmacokinetics of metformin, a classical substrate for OCTs and MATEs, in wild-type and Mate1-/- mice. The nephrotoxicity was assessed in the wild-type and Mate1-/- mice received cisplatin with and without ondansetron. Both MATEs, including human MATE1, human MATE2-K, and mouse Mate1, and OCT2 (human and mouse) were subject to ondansetron inhibition, with much greater potencies by ondansetron on MATEs. Ondansetron significantly increased tissue accumulation and pharmacokinetic exposure of metformin in wild-type but not in Mate1-/- mice. Moreover, ondansetron treatment significantly enhanced renal accumulation of cisplatin and cisplatin-induced nephrotoxicity which were indicated by increased levels of biochemical and molecular biomarkers and more severe pathohistological changes in mice. Similar increases in nephrotoxicity were caused by genetic deficiency of MATE function in mice. Therefore, the potent inhibition of MATEs by ondansetron enhances the nephrotoxicity associated with cisplatin treatment in mice. Potential nephrotoxic effects of combining the chemotherapeutic cisplatin and the antiemetic 5-hydroxytryptamine-3 (5-HT3) receptor antagonists, such as ondansetron, should be investigated in patients.
Although no pharmacokinetic drug interaction between ondansetron and tramadol has been observed, data from 2 small trials indicate that ondansetron may be associated with an increase in patient controlled administration of tramadol.
Serotonin syndrome (including altered mental status, autonomic instability, and neuromuscular abnormalities) has been described following the concomitant use of 5-HT3 receptor antagonists and other serotonergic drugs, including selective serotonin reuptake inhibitors (SSRIs) and serotonin and noradrenaline reuptake inhibitors.
In patients treated with potent inducers of CYP3A4 (i.e., phenytoin, carbamazepine, and rifampicin), the clearance of ondansetron was significantly increased and ondansetron blood concentrations were decreased. However, on the basis of available data, no dosage adjustment for ondansetron is recommended for patients on these drugs.
For more Interactions (Complete) data for Ondansetron (8 total), please visit the HSDB record page.
Adverse Effects
The most commonly reported side effects (occurring in more than 10% of adults) include headaches, fatigue, dry mouth, malaise, and constipation. Some less common effects range from central nervous system (CNS) manifestations, such as drowsiness and sedation, to local injection site reactions and pruritus. A transient increase in liver function tests has also been reported. The pattern of liver enzyme elevation is normally hepatocellular, with rare cases of clinically apparent acute liver injury or jaundice.
Exposure RoutesOndansetron is well absorbed after oral administration and undergoes limited first-pass metabolism.
Toxicity Summary
IDENTIFICATION AND USE: Ondansetron forms as crystals from methanol. It is a drug used for the prevention of nausea and vomiting associated with highly emetogenic cancer chemotherapy in both human and veterinary cases. Prolongation of the QT interval and cases of torsades de pointes have been reported in patients receiving ondansetron. Liver failure and death have been reported rarely in patients with cancer receiving ondansetron concomitantly with other drugs, including potentially hepatotoxic cytotoxic chemotherapy and antibiotics. Ondansetron hydrochloride may cause a serious anaphylactic reaction. In a study of children whose mothers received promethazine or ondansetron during pregnancy, no clinically significant adverse neurobehavioral effects or obstetric outcomes were identified. According to a different study, the teratogenic risk with ondansetron is low but an increased risk for a cardiac septum defect is likely. There was also no evidence of damage to genetic material noted in in vitro chromosome aberration tests using human peripheral lymphocytes. ANIMAL STUDIES: Ondansetron was administered orally to rats at doses of 1, 4, and 15 mg/kg during gametogenesis, mating, pregnancy, and lactation periods. It is proposed that the maximum noneffective dose of ondansetron was 4 and 15 mg/kg with respect to general toxicity and reproductive capacity in F0 animals respectively. The maximum noneffective dose with respect to development in F1 and F2 animals was suggested to be 15 mg/kg. After IV administration of 0.5, 1.5, and 4 mg/kg of ondansetron daily during gestation and lactation period, the results suggest that the maximum noneffective dose of ondansetron for general toxicity in dams was 1.5 mg/kg and that for reproduction toxicity in dams and developmental toxicity in fetuses and offspring was 4 mg/kg. A slight maternal toxicity was observed at the highest dose level in intravenous organogenesis (4.0 mg/kg/day) studies in the rabbit. Effects included maternal body weight loss and increased incidence of early fetal death. There was no evidence of damage to genetic material noted in in vitro V-79 mammalian cell mutation studies or in vivo chromosome aberration assays in mouse bone marrow. No evidence of mutagenicity was observed in microbial mutagen tests using mutant strains of Salmonella typhimurium, Escherichia coli or Saccharomyces cerevisiae, with or without a rat liver post-mitochondrial metabolizing system. Carcinogenic effects were not seen in 2-year studies in rats and mice with oral ondansetron doses up to 10 and 30 mg/kg/day, respectively.
There is no known antidote to ondansetron, and supportive measures are used for overdose. A case report describes an ondansetron overdose in an infant presenting with seizures, QTc prolongation, hepatotoxicity, and serotonin syndrome. The patient required endotracheal intubation, supportive care, and lorazepam for seizures.
Ondansetron is a selective serotonin 5-HT<sub>3</sub> receptor antagonist. The antiemetic activity of the drug is brought about through the inhibition of 5-HT<sub>3</sub> receptors present both centrally (medullary chemoreceptor zone) and peripherally (GI tract). This inhibition of 5-HT<sub>3</sub> receptors in turn inhibits the visceral afferent stimulation of the vomiting center, likely indirectly at the level of the area postrema, as well as through direct inhibition of serotonin activity within the area postrema and the chemoreceptor trigger zone.
Signs and SymptomsLow blood pressure and fainting, sudden blindness, severe constipation
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of December 17, 2015: http://actor.epa.gov/dashboard/]
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ Prolongation of the QT interval has been observed with ondansetron and other members of the 5-HT3 antagonist class. This /was a/ QTc study of ondansetron conducted in accordance with ICH E14 guidelines, designed to investigate the effect of single intravenous (IV) doses of ondansetron on cardiac conduction compared to placebo and a positive control, moxifloxacin, in healthy subjects. Statistical analysis of dose-response showed the maximum mean difference in QTcF, compared to placebo and corrected for baseline (ddQTcF), was less than 10 milliseconds (ms) after an 8 mg IV dose and approximately 20 ms after the 32 mg dose, each infused over 15 minutes. The concentration-response (Cp-ddQTcF) model resulted in similar predictions for the 8 and 32 mg and was used to predict the maximum mean ddQTcF (upper 90% CI bound) of 9.2 (11.2) ms for 16 mg IV. As a result, single IV doses of ondansetron greater than 16 mg should no longer be used. Adult cancer patients, under 75 years, may receive up to a maximum initial 15-minute IV dose of 16 mg, prior to chemotherapy, followed by 2 additional IV or IM doses of 8 mg for the management of chemotherapy-induced nausea and vomiting (CINV).
/SIGNS AND SYMPTOMS/ Prolongation of the QT interval and cases of torsades de pointes have been reported in patients receiving ondansetron.
/SIGNS AND SYMPTOMS/ Individual doses of 84 mg and 145 mg and total daily doses as large as 252 mg have been administered with only mild side effects.
/SIGNS AND SYMPTOMS/ Liver failure and death have been reported rarely in patients with cancer receiving ondansetron concomitantly with other drugs, including potentially hepatotoxic cytotoxic chemotherapy and antibiotics; the etiology of the liver failure is unclear.
For more Human Toxicity Excerpts (Complete) data for Ondansetron (14 total), please visit the HSDB record page.
Carcinogen ClassificationNo indication of carcinogenicity to humans (not listed by IARC).
Drug Induced Liver Injury
Drug-Induced Liver Injury Severity and Toxicity (DILIst)
ondansetron
DILI Positive
Oral
DOI:10.1016/j.drudis.2019.09.022
Non-Human Toxicity Excerpts
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ Carcinogenic effects were not seen in 2-year studies in rats and mice with oral ondansetron doses up to 10 and 30 mg/kg/day, respectively.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ Ondansetron, a serotoninergic 5-HT3 receptor antagonist which can inhibit radiation- and cytotoxic substances-induced vomiting, was administered orally to rats at doses of 1, 4, and 15 mg/kg during gametogenesis, mating, pregnancy, and lactation periods. The body weight gain of F0 male and female during the premating period, pregnancy, and lactation, mating capacity of F0 animals, and development of F1 and F2 animals were observed. It is proposed that the maximum noneffective dose of ondansetron was 4 and 15 mg/kg with respect to general toxicity and reproductive capacity in F0 animals respectively. The maximum noneffective dose with respect to development in F1 and F2 animals was suggested to be 15 mg/kg.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ The reproduction and developmental toxicity of ondansetron, a serotoninergic 5-HT3 receptor antagonist were studied in rats by oral administration of 1, 4, and 15 mg/kg of ondansetron daily during the gestation and lactation periods. The results suggest that the maximum noneffective dose of ondansetron for general and reproduction toxicity in dams was 15 mg/kg and that for developmental toxicity in fetuses and offspring was 4 mg/kg.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ The reproduction and developmental toxicity of ondansetron, a serotoninergic 5-HT3 receptor antagonist, were studied in rats by IV administration of 0.5, 1.5, and 4 mg/kg of ondansetron daily during gestation and lactation period. The results suggest that the maximum noneffective dose of ondansetron for general toxicity in dams was 1.5 mg/kg and that for reproduction toxicity in dams and developmental toxicity in fetuses and offspring was 4 mg/kg.
For more Non-Human Toxicity Excerpts (Complete) data for Ondansetron (10 total), please visit the HSDB record page.
Populations at Special Risk
Because clearance of ondansetron is decreased and apparent volume of distribution and plasma half-life are increased in patients with severe hepatic impairment, the drug should be used with caution and at reduced dosage in such patients.
Because of the risk of QT-interval prolongation, ondansetron should be avoided in patients with congenital long QT syndrome.
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including ondansetron, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including ondansetron hydrochloride, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Ondansetron hydrochloride/
Sicherheitsdaten
- wgk
- 3
- ridadr
- UN 2811 6.1/PG 3
- hs_code
- 29339900
- RTECS-Nr.
- FE6375500
- risk_code
- 25-36/37/38
- Toxizität
- TDLo vn-man: 229 mg/kg/I LANCAO 344,190,94
- hazard_code
- T,Xi
- safety_code
- 45-37/39-26
- Speicherklasse
- 6.1C - Combustible acute toxic Cat.3toxic compounds or compounds which causing chronic effects
- Giftige Stoffe Daten
- 99614-02-5(Hazardous Substances Data)
- Hazard Classifications
- Acute Tox. 3 OralAquatic Acute 1Aquatic Chronic 1Eye Dam. 1
Chemie und Industrie
Pharmakologische Informationen
ATC Code
A04AA01
A - Alimentary tract and metabolism
QA - Alimentary tract and metabolism
A04AA01
Protein BindingThe plasma protein binding associated with ondansetron was documented as approximately 73%.
Pharmacodynamics
Ondansetron is a highly specific and selective serotonin 5-HT<sub>3</sub> receptor antagonist, not shown to have activity at other known serotonin receptors and with low affinity for dopamine receptors,. The serotonin 5-HT<sub>3</sub> receptors are located on the nerve terminals of the vagus in the periphery, and centrally in the chemoreceptor trigger zone of the area postrema,. The temporal relationship between the emetogenic action of emetogenic drugs and the release of serotonin, as well as the efficacy of antiemetic agents, suggest that chemotherapeutic agents release serotonin from the enterochromaffin cells of the small intestine by causing degenerative changes in the GI tract,. The serotonin then stimulates the vagal and splanchnic nerve receptors that project to the medullary vomiting center, as well as the 5-HT<sub>3</sub> receptors in the area postrema, thus initiating the vomiting reflex, causing nausea and vomiting,. Moreover, the effect of ondansetron on the QTc interval was evaluated in a double-blind, randomized, placebo and positive (moxifloxacin) controlled, crossover study in 58 healthy adult men and women. Ondansetron was tested at single doses of 8 mg and 32 mg infused intravenously over 15 minutes. At the highest tested dose of 32 mg, prolongation of the Fridericia-corrected QTc interval (QT/RR0.33=QTcF) was observed from 15 min to 4 h after the start of the 15 min infusion, with a maximum mean (upper limit of 90% CI) difference in QTcF from placebo after baseline-correction of 19.6 (21.5) msec at 20 min. At the lower tested dose of 8 mg, QTc prolongation was observed from 15 min to 1 h after the start of the 15-minute infusion, with a maximum mean (upper limit of 90% CI) difference in QTcF from placebo after baseline-correction of 5.8 (7.8) msec at 15 min. The magnitude of QTc prolongation with ondansetron is expected to be greater if the infusion rate is faster than 15 minutes. The 32 mg intravenous dose of ondansetron must not be administered. No treatment-related effects on the QRS duration or the PR interval were observed at either the 8 or 32 mg dose. An ECG assessment study has not been performed for orally administered ondansetron. On the basis of pharmacokinetic-pharmacodynamic modelling, an 8 mg oral dose of ondansetron is predicted to cause a mean QTcF increase of 0.7 ms (90% CI -2.1, 3.3) at steady-state, assuming a mean maximal plasma concentration of 24.7 ng/mL (95% CI 21.1, 29.0). The magnitude of QTc prolongation at the recommended 5 mg/m2 dose in pediatrics has not been studied, but pharmacokinetic-pharmacodynamic modeling predicts a mean increase of 6.6 ms (90% CI 2.8, 10.7) at maximal plasma concentrations. In healthy subjects, single intravenous doses of 0.15 mg/kg of ondansetron had no effect on esophageal motility, gastric motility, lower esophageal sphincter pressure, or small intestinal transit time. Multiday administration of ondansetron has been shown to slow colonic transit in healthy subjects. Ondansetron has no effect on plasma prolactin concentrations.
Mechanism of Action
Ondansetron is a selective antagonist of the serotonin receptor subtype, 5-HT3. Cytotoxic chemotherapy and radiotherapy are associated with the release of serotonin (5-HT) from enterochromaffin cells of the small intestine, presumably initiating a vomiting reflex through stimulation of 5-HT3 receptors located on vagal afferents. Ondansetron may block the initiation of this reflex. Activation of vagal afferents may also cause a central release of serotonin from the chemoreceptor trigger zone of the area postrema, located on the floor of the fourth ventricle. Thus, the antiemetic effect of ondansetron is probably due to the selective antagonism of 5-HT3 receptors on neurons located in either the peripheral or central nervous systems, or both. Although the mechanisms of action of ondansetron in treating postoperative nausea and vomiting and cytotoxic induced nausea and vomiting may share similar pathways, the role of ondansetron in opiate-induced emesis has not yet been formally established.
Biological Half-Life
The half-life of ondansetron after either an 8 mg oral dose or intravenous dose was approximately 3-4 hours and could be extended to 6-8 hours in the elderly.
In humans ... elimination half lives are approximately 3-4 hours, but are prolonged in elderly patients.
... Six cats with normal complete blood count, serum biochemistry, and urinalysis received 2 mg oral (mean 0.43 mg/kg), subcutaneous (mean 0.4 mg/kg), and intravenous (mean 0.4 mg/kg) ondansetron in a cross-over manner with a 5-day wash out. Serum was collected prior to, and at 0.25, 0.5, 1, 2, 4, 8, 12, 18, and 24 hr after administration of ondansetron. ... Calculated elimination half-life of ondansetron was 1.84 + or - 0.58 hr (intravenous), 1.18 + or - 0.27 hr (oral) and 3.17 + or - 0.53 hr (subcutaneous). The calculated elimination half-life of subcutaneous ondansetron was significantly longer (P < 0.05) than oral or intravenous administration. ...
... A single 8-mg oral dose of ondansetron was administered to beagles (n = 18), ... and the half-life calculated from the terminal phase was 1.3 +/- 0.7 hr. ...
Metabolism/Metabolites
In vitro metabolism studies have shown that ondansetron is a substrate for human hepatic cytochrome P450 enzymes, including CYP1A2, CYP2D6 and CYP3A4. In terms of overall ondansetron turnover, CYP3A4 played the predominant role. Because of the multiplicity of metabolic enzymes capable of metabolizing ondansetron, it is likely that inhibition or loss of one enzyme (e.g. CYP2D6 enzyme deficiency) will be compensated by others and may result in little change in overall rates of ondansetron clearance. Following oral or IV administration, ondansetron is extensively metabolised and excreted in the urine and faeces. In humans, less than 10% of the dose is excreted unchanged in the urine. The major urinary metabolites are glucuronide conjugates (45%), sulphate conjugates (20%) and hydroxylation products (10%). The primary metabolic pathway is subsequently hydroxylation on the indole ring followed by subsequent glucuronide or sulfate conjugation. Although some nonconjugated metabolites have pharmacologic activity, these are not found in plasma at concentrations likely to significantly contribute to the biological activity of ondansetron.
Ondansetron is extensively metabolized in humans, with approximately 5% of a radiolabeled dose recovered as the parent compound from the urine. The primary metabolic pathway is hydroxylation on the indole ring followed by subsequent glucuronide or sulfate conjugation. Although some nonconjugated metabolites have pharmacologic activity, these are not found in plasma at concentrations likely to significantly contribute to the biological activity of ondansetron.
Ondansetron has known human metabolites that include 6-hydroxy-ondansetron, 7-hydroxy-ondansetron, and 8-hydroxy-ondansetron.
Hepatic Half Life: 5.7 hours
FDA Pharmacological Classification
4AF302ESOS
ONDANSETRON
Mechanisms of Action [MoA] - Serotonin 3 Receptor Antagonists
Established Pharmacologic Class [EPC] - Serotonin-3 Receptor Antagonist
Ondansetron is a Serotonin-3 Receptor Antagonist. The mechanism of action of ondansetron is as a Serotonin 3 Receptor Antagonist.
ONDANSETRON
MeSH Pharmacological Classification
Drugs used to prevent NAUSEA or VOMITING.
Agents, usually topical, that relieve itching (pruritus).
Drugs that bind to but do not activate SEROTONIN 5-HT3 RECEPTORS, thereby blocking the actions of SEROTONIN or SEROTONIN 5-HT3 RECEPTOR AGONISTS.
Absorption, Distribution and Excretion
Ondansetron is absorbed from the gastrointestinal tract and undergoes some limited first-pass metabolism. Mean bioavailability in healthy subjects, following administration of a single 8-mg tablet, was recorded as being approximately 56% to 60%. Bioavailability is also slightly enhanced by the presence of food. Ondansetron systemic exposure does not increase proportionately to dose. The AUC from a 16-mg tablet was 24% greater than predicted from an 8-mg tablet dose. This may reflect some reduction of first-pass metabolism at higher oral doses.
Following oral or IV administration, ondansetron is extensively metabolised and excreted in the urine and faeces.
The volume of distribution of ondansetron has been recorded as being approximately 160L.
The clearance values determined for ondansetron in various patient age groups were recorded as approximately 0.38 L/h/kg in normal adult volunteers aged 19-40 yrs, 0.32 L/h/kg in normal adult volunteers aged 61-74 yrs, 0.26 L/h/kg in normal adult volunteers aged >=75 yrs.
Ondansetron is a 5-HT3 receptor antagonist that is an effective anti-emetic in cats. The purpose of this study was to evaluate the pharmacokinetics of ondansetron in healthy cats. Six cats with normal complete blood count, serum biochemistry, and urinalysis received 2 mg oral (mean 0.43 mg/kg), subcutaneous (mean 0.4 mg/kg), and intravenous (mean 0.4 mg/kg) ondansetron in a cross-over manner with a 5-day wash out. Serum was collected prior to, and at 0.25, 0.5, 1, 2, 4, 8, 12, 18, and 24 hr after administration of ondansetron. Ondansetron concentrations were measured using liquid chromatography coupled to tandem mass spectrometry. Noncompartmental pharmacokinetic modeling and dose interval modeling were performed. Repeated measures anova was used to compare parameters between administration routes. Bioavailability of ondansetron was 32% (oral) and 75% (subcutaneous). Calculated elimination half-life of ondansetron was 1.84 + or - 0.58 hr (intravenous), 1.18 + or - 0.27 hr (oral) and 3.17 + or - 0.53 hr (subcutaneous). The calculated elimination half-life of subcutaneous ondansetron was significantly longer (P < 0.05) than oral or intravenous administration. Subcutaneous administration of ondansetron to healthy cats is more bioavailable and results in a more prolonged exposure than oral administration. This information will aid management of emesis in feline patients.
Nausea and vomiting are some of the major side effects caused by certain drug therapies, e.g. chemotherapy, radiotherapy and general anesthesia. Because of the nature of the symptoms, oral delivery is inappropriate, while intravenous administration may be unpractical. The aim of the present study was to develop a transdermal gel (2% Klucel) for ondansetron, a first line 5-HT3-receptor-antagonist antiemetic. The effects of the penetration enhancer camphor and isopropyl-myristate (IPM) were first investigated in-vitro using modified Franz diffusion-cells and then tested in-vivo in a rabbit model by measuring skin and plasma concentrations. Since a disadvantage of transdermal delivery is a prolonged lag-time, the effect of skin treatment with a micro-needle roller was tested. The in-vitro permeation studies through excised porcine ear skin showed that the presence of 2.5% camphor or IPM increased steady state flux by 1.2- and 2.5-fold, respectively, compared to the control gel. Ondansetron was not detectable in either skin or plasma following in-vivo application of the base-gel, whereas the camphor gel and IPM gel delivered 20 and 81 ug/sq cm of ondansetron, respectively. Microporation led to an increase in plasma Cmax and AUC by 10.47 + or - 1.68-fold and 9.31 + or - 4.91-fold, respectively, for the camphor gel, and by 2.31 + or -0.53-fold and 1.59 + or - 0.38-fold, respectively for the IPM gel. In conclusion, the 2.5% IPM gel demonstrated optimal in-vivo transdermal flux. Skin pretreatment with a micro-needle roller slightly improved the delivery of the IPM gel, whereas dramatically increased the transdermal delivery of the camphor gel.
Tissue LocationsLiver
Cellular LocationsMembrane
Verwendung und Herstellung
Uses
MEDICATION
Use (kg; approx.) in Germany (2009): >25
For the prevention of nausea and vomiting associated with emetogenic cancer chemotherapy, postoperation, and radiation. Also used for the treatment of postoperative nausea and vomiting.
Methods of ManufacturingPreparation: I. H. Coates et al., European Patent Office patent 191562; eidem, United States of America patent 4695578 (1986, 1987 both to Glaxo).
Formulations/Preparations
Table: Ondansetron Preparations [Table#8315]
Table: Ondansetron Hydrochloride Preparations [Table#8316]
Anwendungen
BeschreibungOndansetron (hydrochloride) (CRM) (Item No. 21710) is a certified reference material categorized as an antiemetic. Formulations containing ondansetron have been used to reduce alcohol consumption and mood disturbances in early-onset alcoholics. This product is intended for research and forensic applications.
Verwendenantibacterial
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Anbieter50 Anbieter
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
湖北永阔科技有限公司027-59223108 15972152991 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
成都超九八生物科技有限公司13348960310 13348960310 · [email protected]
HubeiwidelychemicaltechnologyCo.,Ltd18627774460 · [email protected]
Dayang Chem (Hangzhou) Co.,Ltd.+86-0571-88938639 17705817739 · [email protected]
南京世洲生物科技有限公司025-025-85560043 17301488900 · [email protected]
北京安司莫森技术有限公司010-82954736 13391601435 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
安耐吉化学&3A(安徽泽升科技有限公司)021-58432009 400-005-6266 · [email protected]
常州科化生物科技有限公司0519-68985668 13685222090 · [email protected]
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
上海相辉医药科技有限公司13761987713 · [email protected]
Ascent Scientific4401179829988 · [email protected]
武汉丰泰威远科技有限公司+86-27-8746-5837 +86-18627785180 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
天津希恩思生化科技有限公司400 638 7771 · [email protected]
上海特伯化学科技有限公司+86-21-60341587 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
上海遐瑞医药科技有限公司+86 21 61551611
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
Clearsynth Labs Limited+91-22-26355700 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
苏州亚科科技股份有限公司0512-87182055 13451648594 · [email protected]
上海陶素生化科技有限公司021-33632979 · [email protected]
南京世洲生物科技有限公司13675144456 · [email protected]
Cato Research Chemicals Inc.020-81960175 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
济南鲁欣化工科技有限公司0531-0531-82929600 18615510361 · [email protected]
上海洽凡生化科技有限公司+86-021-61654350 · [email protected]
陕西缔都医药化工有限公司+86-29-87569262 +86-15003564040 · [email protected]
上海孚一生物科技有限公司+86 (21) 61124340
凯试(上海)科技有限公司021-50135380 · [email protected]
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
TargetMol中国(陶术生物)021-021-33632979 15002134094 · [email protected]
上海陶术生物科技股份有限公司+1-781-999-5354; +1-00000000000 · [email protected]
厦门志信化学有限公司+86-5922680277 +86-13806087780 · [email protected]
广东翁江化学试剂有限公司0751-2886766 13927870850 · [email protected]
Alfa Chemistry+1-5166625404 · [email protected]
sgtlifesciences pvt ltd+91-8790379245 · [email protected]
EMMX Biotechnology LLC888-539-0666 · [email protected]
南京熙朗化工产品有限公司18936048580 · [email protected]
广州市齐云生物技术有限公司020-61288194 61288195 · [email protected]
上海前衍生物科技有限公司02781293128 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
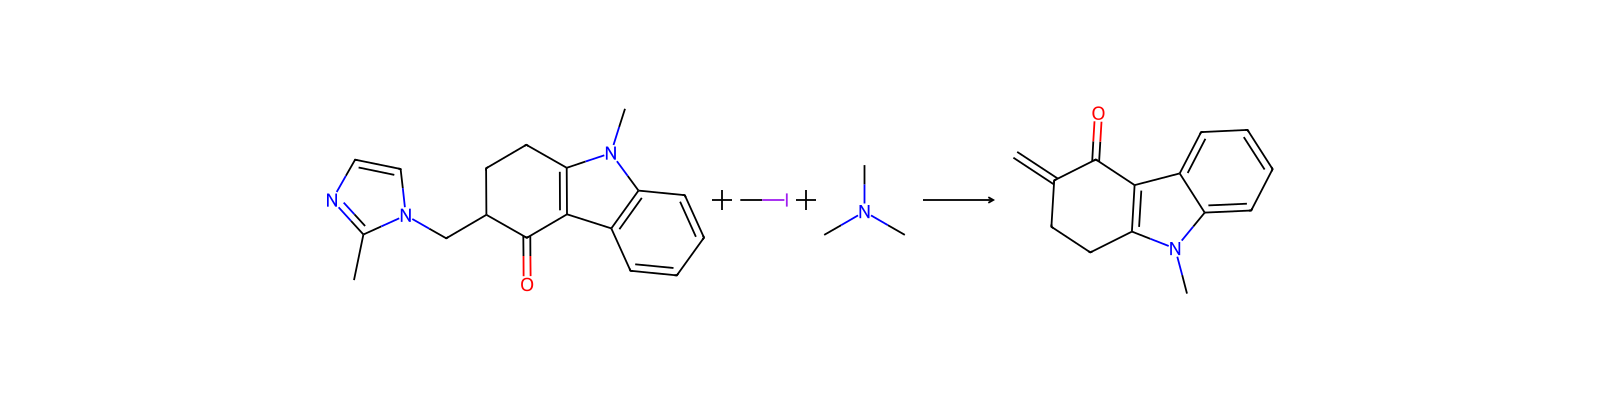
Zugehörige Reaktionen
46



Verknüpfte Notizen
Wird geladen…