

Grundinformationen
- Standard-SMILES
CCc1nc(N)nc(N)c1-c1ccc(Cl)cc1- InChIKey
WKSAUQYGYAYLPV-UHFFFAOYSA-N- Summenformel
- C12H13ClN4
- Durchschnittliche Molmasse
- 248,71 g/mol
- Monoisotopische Masse
- 248,0828741
Überblick
Pyrimethamine can cause developmental toxicity according to state or federal government labeling requirements.
Namen und Bezeichner
- Bevorzugter Name
- Pyrimethamine
- IUPAC
- 5-(4-chlorophenyl)-6-ethylpyrimidine-2,4-diamine
- Lokaler Name
- Pyrimethamin
- Englischer Name
- Pyrimethamine
- Summenformel
- C12H13ClN4
- Molmasse
- 248.71
Namen und Synonyme
pyrimethamine58-14-0DaraprimChloridine5-(4-chlorophenyl)-6-ethylpyrimidine-2,4-diamineChloridinDiaminopyritaminEthylpyrimidinePirimecidanPirimetaminPirimetaminaChloridyn
Weitere Namen anzeigen
PyremethamineFansidarwr2978bw50-63Malacid
DarachlorErbaprelinaKhloridinTindurinMalocidPrimethaminePyrimethamin5-(4-CHLOROPHENYL)-6-ETHYL-2,4-PYRIMIDINEDIAMINE
Datenbank-Bezeichner
- CAS
58-14-0- PubChem CID
- 4993
- DTXSID
DTXSID9021217- ChEMBL
CHEMBL36- ChEBI
CHEBI:8673- UNII
- Z3614QOX8W
- EC Number
- 200-364-2
- Nikkaji
- J4.589F
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 2,7
- Polarare Oberfläche (TPSA)
- 77,8 Ų
- H-Brücken-Donoren
- 2
- H-Brücken-Akzeptoren
- 4
- Frei drehbare Bindungen
- 2
- Schwere Atome
- 17
- Formalladung
- 0
- Komplexität
- 243
Experimentelle und physikochemische Eigenschaften
DrugsPharmaceuticals -> Listed in ZINC15
SpringerMaterials Properties15N nuclear magnetic resonance spectrum
LogP
log Kow = 2.69
2.7
2.69
Color/Form
Crystals
White scored tablets contains 25 mg pyrimethamine /Daraprim/
Solubility
less than 0.1 mg/mL at 70 °F (NTP, 1992)
In water, 10 mg/L (temperature not specified)
Practically insoluble in water; slightly soluble in ethanol (about 9 g/L), in dilute HCl (about 5 g/L); soluble in boiling ethanol (about 25 g/L); Very sparingly soluble in propylene glycol and dimethylacetamide at 70 °C
1.79e-01 g/L
>37.3 [ug/mL] (The mean of the results at pH 7.4)
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anti-infective Agents; Antiparasitic Agents; Antimalarials; Antiprotozoal Agents
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Antipneumocystosis and antitoxoplasmosis medicines
Animal Drugs
Active Ingredients (Pyrimethamine) -> FDA Greenbook
Pharmaceuticals -> Animal Drugs -> Approved in Taiwan
DecompositionWhen heated to decomposition it emits very toxic fumes of /HCl and oxides of nitrogen/.
Melting Point
451 to 453 °F (capillary) (NTP, 1992)
233-234 °C (capillary); 240-242 °C (copper block)
233.5 °C
Physical Description
Pyrimethamine is an odorless white crystalline powder. Tasteless. An antimalarial drug.
Solid
Dissociation Constants
7.34 (at 20 °C)
pKa = 7.34 at 20 °C (conjugate acid)
Collision Cross Section
158.8 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: APCI+; Dataset: TOXCAST; Source Identifier: DTXSID9021217]
155.8 Ų [M+H]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
153.6 Ų [M+Na]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
Physikochemische Eigenschaften
- Schmelzpunkt
- 233 · 233-234°C
- Siedepunkt
- 393.35 °C · 393.35°C (rough estimate)
- Dichte
- 1.2171 · 1.2171 (rough estimate)
- Brechungsindex
- 1.611 · 1.6110 (estimate)
- storage temp.
- Keep in dark place,Inert atmosphere,Room temperature
- Löslichkeit
- 0.25 g · Prepare the solution immediately before use. Dissolve 0.25 g in a mixture of 1 volume of methanol R and 3 volumes of methylene chloride R and dilute to 10 mL with the same mixture of solvents. The solution is clear (2.2.1) and not more intensely coloured than reference solution BY6 (2.2.2, Method II).
- Aggregatzustand
- Solid
- pka
- 7 · pKa 7(t=20.0) (Uncertain)
- Farbe
- White to Off-White
- Wasserlöslichkeit
- 0.01 g/100 · <0.01 g/100 mL at 21 ºC
- Merck
- 14 · 14,7985
- BRN
- 219864 · 219864
- Henry's Law Constant
- 9.1 · 9.1×104 mol/(m3Pa) at 25℃, HSDB (2015)
- BCS Class
- 2 · 2 (CLogP), 4 (LogP),3
- Stabilität
- Stable, but light sensitive. Combustible. Incompatible with strong oxidizing agents.
- Major Application
- clinical testing
- InChI
- 1S/C12H13ClN4/c1-2-9-10(11(14)17-12(15)16-9)7-3-5-8(13)6-4-7/h3-6H,2H2,1H3,(H4,14,15,16,17)
- InChIKey
- WKSAUQYGYAYLPV-UHFFFAOYSA-N
- SMILES
- CCC1=NC(N)=NC(N)=C1C2=CC=C(Cl)C=C2
- CAS Datenbank
- 58 · 58-14-0(CAS DataBase Reference)
- NIST chemische Informationen
- Pyrimethamine(58-14-0)
- EPA chemische Informationen
- Pyrimethamine (58-14-0)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Warning
H302 (99.2%): Harmful if swallowed [Warning Acute toxicity, oral]
P264, P270, P301+P317, P330, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 133 reports by companies from 7 notifications to the ECHA C&L Inventory.
Gefahrenhinweise
Regulatory InformationHazard Traits - Developmental Toxicity
Other Safety InformationIMAP assessments - 2,4-Pyrimidinediamine, 5-(4-chlorophenyl)-6-ethyl-: Environment tier I assessment
DOT LabelPoison
Fire HazardsFlash point data for this chemical are not available; however, it is probably combustible. (NTP, 1992)
Health Hazards
SYMPTOMS: Symptoms of exposure to this compound include megaloblastic anemia, leukopenia, thrombocytopenia, pancytopenia, atrophic glossitis, vomiting, convulsions, respiratory failure and death. Chronic exposure may cause depression of hemopoiesis due to interference in the metabolism of folic acid. Skin rashes may also occur.
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including pyrimethamine, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Oral dosage form new animal drug. Sulfadiazine/pyrimethamine suspension. ... For the treatment of equine protozoal myeloencephalitis (EPM) caused by Sarcocystis neurona. Limitations: Do not use in horses intended for human consumption. Federal law restricts this drug to use by or on the order of a licensed veterinarian.
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Pyrimethamine is included on this list.
Reactive GroupAmines, Phosphines, and Pyridines
Reactivity Profile
PYRIMETHAMINE is sensitive to exposure to light (NTP, 1992). Neutralizes acids to form salts plus water in exothermic reactions. May be incompatible with isocyanates, halogenated organics, peroxides, phenols (acidic), epoxides, anhydrides, and acid halides. Flammable gaseous hydrogen may be generated in combination with strong reducing agents, such as hydrides.
Air and Water ReactionsInsoluble in water.
Hazard Classes and CategoriesAcute Tox. 4 (99.2%)
Sicherheit und Schutzausrüstung
Fire FightingFires involving this material can be controlled with a dry chemical, carbon dioxide or Halon extinguisher. (NTP, 1992)
First Aid
EYES: First check the victim for contact lenses and remove if present. Flush victim's eyes with water or normal saline solution for 20 to 30 minutes while simultaneously calling a hospital or poison control center. Do not put any ointments, oils, or medication in the victim's eyes without specific instructions from a physician. IMMEDIATELY transport the victim after flushing eyes to a hospital even if no symptoms (such as redness or irritation) develop.
Storage ConditionsStore at 15 deg to 25 °C (59 deg to 77 °F) in a dry place and protect from light.
Nonfire Spill Response
SMALL SPILLS AND LEAKAGE: If a spill of this chemical occurs, FIRST REMOVE ALL SOURCES OF IGNITION, then you should dampen the solid spill material with acetone and transfer the dampened material to a suitable container. Use absorbent paper dampened with acetone to pick up any remaining material. Seal your contaminated clothing and the absorbent paper in a vapor-tight plastic bag for eventual disposal. Solvent wash all contaminated surfaces with acetone followed by washing with a soap and water solution. Do not reenter the contaminated area until the Safety Officer (or other responsible person) has verified that the area has been properly cleaned.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
SRP: At the time of review, regulatory criteria for small quantity disposal are subject to significant revision, however, household quantities of waste pharmaceuticals may be managed as follows: Mix with wet cat litter or coffee grounds, double bag in plastic, discard in trash.
Isolation and EvacuationExcerpt from ERG Guide 154 [Substances - Toxic and/or Corrosive (Non-Combustible)]:
Personal Protective Equipment (PPE)
RECOMMENDED RESPIRATOR: Where the neat test chemical is weighed and diluted, wear a NIOSH-approved half face respirator equipped with a combination filter cartridge, i.e. organic vapor/acid gas/HEPA (specific for organic vapors, HCl, acid gas, SO2 and a high efficiency particulate filter). (NTP, 1992)
Toxikologische Informationen
Interactions
Although the clinical importance is unclear, mild hepatotoxicity has been reported in some patients receiving pyrimethamine and lorazepam concomitantly.
Although the clinical importance is unclear, p-aminobenzoic acid (PABA) reportedly interferes with the action of pyrimethamine and probably should not be used in patients receiving pyrimethamine.
An increased incidence and severity of adverse effects has been reported when chloroquine was used concomitantly with the fixed combination of sulfadoxine and pyrimethamine compared with use of the fixed combination alone. Sulfadoxine and pyrimethamine is compatible with quinine and with other anti-infectives.
Concomitant use of pyrimethamine or sulfadoxine and pyrimethamine with other antifolate agents (e.g., sulfonamides, co-trimoxazole, trimethoprim) is not recommended since such use may increase the risk of bone marrow suppression. If signs of folate deficiency develop, pyrimethamine or sulfadoxine and pyrimethamine should be discontinued and leucovorin administered (if necessary) until normal hematopoiesis is restored.
For more Interactions (Complete) data for Pyrimethamine (6 total), please visit the HSDB record page.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), estimated Koc values of 1540 and 590(SRC), determined from a structure estimation method(2) and from a log Kow of 2.69(3) and a regression-derived equation(2) respectively, indicate that pyrimethamine is expected to have low mobility in soil(SRC). The pKa of pyrimethamine is 7.34(4), indicating that this compound will exist in cation form; in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(5). Also, aromatic amines are expected to bind strongly to humus or organic matter in soils due to the high reactivity of the aromatic amino group(6,7), suggesting that pyrimethamine may be immobile in some soils(SRC). Volatilization of pyrimethamine from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 1.08X10⁻¹⁰ atm-cu m/mole(SRC), using a fragment constant estimation method(2). Pyrimethamine is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 1.32X10⁻⁸ mm Hg at 25 °C(SRC), determined from a fragment constant method(2).
AQUATIC FATE: Based on a classification scheme(1), estimated Koc values of 1540 and 590(SRC), determined from a structure estimation method(2) and from a log Kow of 2.69(3) and a regression-derived equation(2) respectively, indicate that pyrimethamine is expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(4) based upon an estimated Henry's Law constant of 1.08X10⁻¹⁰ atm-cu m/mole(SRC), developed using a fragment constant estimation method(2). According to a classification scheme(5), an estimated BCF of 28(SRC), from its log Kow and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is low(SRC). Pyrimethamine is not expected to undergo hydrolysis in the environment due to the lack of functional groups that hydrolyze under environmental conditions(4).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), pyrimethamine, which has an estimated vapor pressure of 1.32X10⁻⁸ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), will exist in both the vapor and particulate phases in the ambient atmosphere. Vapor-phase pyrimethamine is degraded in the atmosphere by reaction with photochemically-produced hydroxyl radicals(SRC); the half-life for this reaction in air is estimated to be 2 hours(SRC), calculated from its rate constant of 2.0X10⁻¹⁰ cu cm/molecule-sec at 25 °C(SRC) that was derived using a structure estimation method(2). Particulate-phase pyrimethamine may be removed from the air by wet or dry deposition(SRC).
Exposure RoutesWell absorbed with peak levels occurring between 2 to 6 hours following administration
Milk Concentrations
The concentration of chloroquine, dapsone and pyrimethamine in plasma and milk were measured following the coadministration of a single dose of chloroquine and Maloprim to lactating women. The milk to plasma area under the concentration-time curve (AUC) ratio ranged from 1.96 to 4.26 for chloroquine, 0.22 to 0.45 for dapsone and 0.46 to 0.66 for pyrimethamine. Assuming a daily milk ingestion of 1 l by the infant, the maximum percentage of the maternal dose for chloroquine, dapsone and pyrimethamine in milk was 4.2%, 14.3% and 45.6%, respectively, over a 9 day period.
Pyrimethamine was detected in raw bovine milk samples collected in Spain at a concentration of 0.15 ug/kg(1) and in whole milk samples at a concentration of 0.21 ug/kg; concentrations in skim milk samples ranged from 0.07-0.17 ug/kg(1).
Pyrimethamine is excreted into milk. It is estimated that approximately 3-4 mg of the drug would be ingested by a nursing infant over the first 48-hour period following administration of a single 75-mg oral dose to the mother.
Toxicity Summary
Pyrimethamine inhibits the dihydrofolate reductase of plasmodia and thereby blocks the biosynthesis of purines and pyrimidines, which are essential for DNA synthesis and cell multiplication. This leads to failure of nuclear division at the time of schizont formation in erythrocytes and liver.
Ongoing Test Status
The following link will take the user to the National Toxicology Program (NTP) Test Agent Search Results page, which tabulates all of the "Standard Toxicology & Carcinogenesis Studies", "Developmental Studies", and "Genetic Toxicity Studies" performed with this chemical. Clicking on the "Testing Status" link will take the user to the status (i.e., in review, in progress, in preparation, on test, completed, etc.) and results of all the studies that the NTP has done on this chemical.[Available from, as of June 21, 2012: http://ntp-apps.niehs.nih.gov/ntp_tox/index.cfm?fuseaction=ntpsearch.searchresults&searchterm=58-14-0]
Soil Adsorption/Mobility
The pKa of pyrimethamine is 7.34(1), indicating that this compound will exist partially in cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(2). Because pyrimethamine ionizes in the environment, two estimated Koc values have been calculated(SRC). Using a structure estimation method based on molecular connectivity indices(3), the Koc of pyrimethamine can be estimated to be 1540(SRC). The Koc of pyrimethamine is estimated as 590(SRC), using a log Kow of 2.69(4) and a regression-derived equation(3). According to a classification scheme(5), these estimated Koc values suggest that pyrimethamine is expected to have low mobility in soil. Also, aromatic amines are expected to bind strongly to humus or organic matter in soils due to the high reactivity of the aromatic amino group(6,7), suggesting that pyrimethamine may be immobile in some soils(SRC).
Human Toxicity Excerpts
/SIGNS AND SYMPTOMS/ Following the ingestion of 300 mg or more of pyrimethamine, gastrointestinal and/or central nervous system signs may be present, including convulsions. The initial symptoms are usually gastrointestinal and may include abdominal pain, nausea, severe and repeated vomiting, possibly including hematemesis. Central nervous system toxicity may be manifest by initial excitability, generalized and prolonged convulsions which may be followed by respiratory depression, circulatory collapse, and death within a few hours. Neurological symptoms appear rapidly (30 minutes to 2 hours after drug ingestion), suggesting that in gross overdosage pyrimethamine has a direct toxic effect on the central nervous system.
/CASE REPORTS/ There have been at least 2 reports of cancer associated with long-term use of pyrimethamine for the treatment of toxoplasmosis; one 51-year-old woman developed chronic granulocytic leukemia after receiving the drug for 2 years and one 56-year-old patient developed reticulum cell sarcoma after receiving the drug for 14 months.
/CASE REPORTS/ Toxoplasmosis is one of the life-threatening infections that can occur after hematopoietic stem cell transplantation (HSCT) and also solid organ transplantation. The standard treatment for toxoplasmosis is combination therapy with pyrimethamine and sulfadiazine, both of which inhibit folate metabolism. Therefore, therapy with these agents could result in marrow toxicity including megaloblastic anemia or pancytopenia, which is reversible or preventable with folate supplementation. Transplant-associated microangiopathy (TAM) is another situation where folate is required to compensate for increased erythropoiesis due to hemolysis after allogeneic HSCT. Here, we report a case of severe marrow toxicity manifesting as pancytopenia due to low-dose pyrimethamine, which was triggered by TAM after HSCT.
/CASE REPORTS/ Curative treatment of congenital toxoplasmosis is based on the association of pyrimethamine and sulfonamide. There is currently no pediatric galenic formulation. /The investigators/ report the case of a newborn child affected by asymptomatic congenital toxoplasmosis who received an overdose of pyrimethamine. The patient received a dose of pyrimethamine 4 times, equal to 100 times the recommended dose, due to an error in the prescription. He had partial seizures 48 h after the last medicinal absorption. /The investigators/ noted a lack of appetite and vomiting, with a favorable progression in 5 days. Blood analysis showed isolated, spontaneously regressive moderate cholestasis.
For more Human Toxicity Excerpts (Complete) data for Pyrimethamine (11 total), please visit the HSDB record page.
Artificial Pollution SourcesPyrimethamine's production and use as an antimalarial and antiprotozoal drug(1) may result in its release to the environment through various waste streams(SRC).
Carcinogen Classification
Pyrimethamine
Group 3: Not classifiable as to its carcinogenicity to humans
Volume 13: (1977) Some Miscellaneous Pharmaceutical Substances
1987
1987
Pyrimethamine
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Pyrimethamine
vLess-DILI-concern
3
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Environmental Bioconcentration
An estimated BCF of 28 was calculated in fish for pyrimethamine(SRC), using a log Kow of 2.69(1) and a regression-derived equation(2). According to a classification scheme(3), this BCF suggests the potential for bioconcentration in aquatic organisms is low(SRC).
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including pyrimethamine, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Oral dosage form new animal drug. Sulfadiazine/pyrimethamine suspension. ... For the treatment of equine protozoal myeloencephalitis (EPM) caused by Sarcocystis neurona. Limitations: Do not use in horses intended for human consumption. Federal law restricts this drug to use by or on the order of a licensed veterinarian.
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Pyrimethamine is included on this list.
Sicherheitsdaten
- wgk
- 3
- ridadr
- 3249
- hs_code
- 29335990
- RTECS-Nr.
- UV8140000
- risk_code
- 22-36
- Toxizität
- LD50 oral in rat: 440mg/kg
- hazard_code
- Xn
- safety_code
- 26
- hazard_class
- 6.1(b)
- packing_group
- III
- Speicherklasse
- 11 - Combustible Solids
- Giftige Stoffe Daten
- 58-14-0(Hazardous Substances Data)
- Hazard Classifications
- Acute Tox. 4 Oral
Chemie und Industrie
Pharmakologische Informationen
ATC Code
P01BD01
P - Antiparasitic products, insecticides and repellents
P01BD01
Protein Binding87%
Pharmacodynamics
Pyrimethamine is an antiparasitic compound commonly used as an adjunct in the treatment of uncomplicated, chloroquine resistant, P. falciparum malaria. Pyrimethamine is a folic acid antagonist and the rationale for its therapeutic action is based on the differential requirement between host and parasite for nucleic acid precursors involved in growth. This activity is highly selective against plasmodia and Toxoplasma gondii. Pyrimethamine possesses blood schizonticidal and some tissue schizonticidal activity against malaria parasites of humans. However, the 4-amino-quinoline compounds are more effective against the erythrocytic schizonts. It does not destroy gametocytes, but arrests sporogony in the mosquito. The action of pyrimethamine against Toxoplasma gondii is greatly enhanced when used in conjunction with sulfonamides.
Mechanism of Action
Pyrimethamine inhibits the dihydrofolate reductase of plasmodia and thereby blocks the biosynthesis of purines and pyrimidines, which are essential for DNA synthesis and cell multiplication. This leads to failure of nuclear division at the time of schizont formation in erythrocytes and liver.
Pyrimethamine is an antimalarial drug that has also been used successfully to treat autoimmune diseases such as lymphoproliferative syndrome. In this work, the effect of pyrimethamine (PYR) on the production of free radicals in malaria-infected mice was studied to better understand the drug's immunomodulatory properties. BALB/c and CBA/Ca mice were infected with Plasmodium yoelii 17XL. Seven days after infection, mice were treated with PYR or vehicle and sacrificed 24h later. Treatment with PYR increased superoxide dismutase and glutathione peroxidase activities in erythrocytes and the liver, augmented the levels of nitric oxide in the serum, and upregulated mRNA levels of superoxide dismutase, glutathione peroxidase, catalase, and iNOS in the spleen. In addition, PYR increased lipoperoxidation and protein carbonylation in infected mice. Our results indicate that P. yoelii 17XL reduces oxidative stress in infected cells, while PYR induces it, which is associated with increased parasite elimination. Thus, it is possible that oxidative stress generated by pyrimethamine is also involved in its immunomodulatory mechanism of action.
Co-infection of human immunodeficiency virus (HIV) with malaria is one of the pandemic problems in Africa and parts of Asia. Here we investigated the impact of pyrimethamine (PYR) and two other clinical anti-malarial drugs (chloroquine [CQ] or artemisinin [ART]) on HIV-1 replication. Peripheral blood mononuclear cells (PBMCs) or MT-2 cells were infected with HIV(NL4.3) strain and treated with different concentrations of the anti-malarial drugs. HIV-1 replication was measured using p24 ELISA. We show that 10 uM CQ and ART inhibited HIV-1 replication by 76% and 60% in PBMCs, respectively, but not in MT-2 cells. In contrast, 10 uM PYR enhanced HIV-1 replication in MT-2 cells by >10-fold. A series of molecular mechanism studies revealed that PYR increased intracellular HIV gag proteins without affecting the promoter or the reverse transcriptase activity. The effect of PYR was independent of HTLV-1 produced by MT-2 cells. Of interest, PYR treatment led to S-phase accumulation and increased AZT and d4T antiviral activity by ~ 4-fold. Taken together, we show that PYR significantly enhances HIV-1 replication by affecting the cellular machinery. Our results could be relevant for the management of malaria and HIV particularly in regions where HIV-1 and malaria epidemics overlap.
Autosomal dominant polycystic kidney disease (ADPKD) is a commonly inherited disorder mostly caused by mutations in PKD1, encoding polycystin-1 (PC1). The disease is characterized by development and growth of epithelium-lined cyst in both kidneys, often leading to renal failure. There is no specific treatment for this disease. Here, we report a sustained activation of the transcription factor signal transducer and activator of transcription 3 (STAT3) in ischemic injured and uninjured Pkd1 knockout polycystic kidneys and in human ADPKD kidneys. Through a chemical library screen, we identified the anti-parasitic compound pyrimethamine as an inhibitor of STAT3 function. Treatment with pyrimethamine decreases cell proliferation in human ADPKD cells and blocks renal cyst formation in an adult and a neonatal PKD mouse model. Moreover, we demonstrated that a specific STAT3 inhibitor, S3I-201, reduces cyst formation and growth in a neonatal PKD mouse model. Our results suggest that PC1 acts as a negative regulator of STAT3 and that blocking STAT3 signaling with pyrimethamine or similar drugs may be an attractive therapy for human ADPKD.
The unresponsiveness of metastatic melanoma to conventional chemotherapeutic and biological agents is largely due to the development of resistance to apoptosis. Pyrimethamine belongs to the group of antifolate drugs, and in addition to antiprotozoan effects, it exerts a strong proapoptotic activity, which we recently characterized in human T lymphocytes. However, no data regarding pyrimethamine anticancer activity are available thus far. To this end, we examined the in vitro effects of pyrimethamine on apoptosis, cell cycle distribution, and cell proliferation of human metastatic melanoma cell lines. The in vivo antitumor potential of pyrimethamine was evaluated in a severe combined immunodeficiency (SCID) mouse xenotransplantation model. Our data indicate that pyrimethamine, when used at a clinically relevant concentration, induced apoptosis in metastatic melanoma cells via the activation of the cathepsin B and the caspase cascade (i.e., caspase-8 and caspase-9) and subsequent mitochondrial depolarization. This occurred independently from CD95/Fas engagement. Moreover, pyrimethamine induced a marked inhibition of cell growth and an S-phase cell cycle arrest. Results obtained in SCID mice, injected s.c. with metastatic melanoma cells and treated with pyrimethamine, indicated a significant inhibitory effect on tumor growth. In conclusion, our results suggest that pyrimethamine-induced apoptosis may be considered as a multifaceted process, in which different inducers or regulators of apoptosis are simultaneously implicated, thus permitting death defects of melanoma cells to be bypassed or overcome. On these bases, we hypothesize that pyrimethamine could represent an interesting candidate for the treatment of metastatic melanoma.
Pyrimethamine is a folic acid antagonist and has a mechanism of action similar to that of trimethoprim. By binding to and reversibly inhibiting dihydrofolate reductase, pyrimethamine inhibits the reduction of dihydrofolic acid to tetrahydrofolic acid (folinic acid). Pyrimethamine interferes with the synthesis of tetrahydrofolic acid in malarial parasites at a point immediately succeeding that where sulfonamides act. Sulfadoxine, like other sulfonamides, is a structural analog of p-aminobenzoic acid (PABA) and competitively inhibits dihydrofolic acid synthesis which is necessary for the conversion of PABA to folic acid. The combination of sulfadoxine and pyrimethamine results in a synergistic action against susceptible plasmodia.
Biological Half-Life
96 hours
Pyrimethamine reportedly has an average plasma half-life of 111 hours (range: 54-148 hours). The plasma half-life of sulfadoxine reportedly averages 169 hours (range: 100-231 hours).
To determine pyrimethamine levels in sera, cerebrospinal fluid, and ventricular fluid in infants, specimens were examined from 37 infants, ages 10 days to 1.5 yr, receiving pyrimethamine 1 mg/kg of body weight daily for 2 months followed by the same dosage each Monday, Wednesday, and Friday for treatment of suspect or proven congenital toxoplasmosis. The pyrimethamine half-life obtained from serum of 9 babies was 64 hr, which was significantly different than for 2 infants taking phenobarbital (33 hr).
A pharmacokinetic study of pyrimethamine was carried out in 4- (103-115 g) and 12-week-old (260-280 g) white male Wistar rats fed a standard diet containing 24% protein, and a low-protein diet containing 8% protein. After intragastric administration of the drug in a single dose of 40 mg/kg body weight, the concentrations of pyrimethamine in the blood were determined at different time points from 15 min to 20 hours post-dose...The elimination half-life (t1/2) was higher in the 4-week-old rats (i.e. 57.1 hr; 8% protein, and 51.2 hr; 24% protein) than in the 12-week-old animals (i.e. 42.4 hr; 8% protein, and 36.0 hr; 24% protein).
Metabolism/Metabolites
Hepatic
Pyrimethamine is metabolized to several unidentified metabolites. About 5% of a dose of sulfadoxine is present in plasma as an acetylated metabolite and about 2-3% is present as the glucuronide.
Hepatic Half Life: 96 hours
FDA Pharmacological Classification
Z3614QOX8W
PYRIMETHAMINE
Established Pharmacologic Class [EPC] - Dihydrofolate Reductase Inhibitor Antimalarial
Mechanisms of Action [MoA] - Dihydrofolate Reductase Inhibitors
Pyrimethamine is a Dihydrofolate Reductase Inhibitor Antimalarial. The mechanism of action of pyrimethamine is as a Dihydrofolate Reductase Inhibitor.
PYRIMETHAMINE
MeSH Pharmacological Classification
Agents used in the treatment of malaria. They are usually classified on the basis of their action against plasmodia at different stages in their life cycle in the human. (From AMA, Drug Evaluations Annual, 1992, p1585)
Substances that are destructive to protozoans.
Inhibitors of the enzyme, dihydrofolate reductase (TETRAHYDROFOLATE DEHYDROGENASE), which converts dihydrofolate (FH2) to tetrahydrofolate (FH4). They are frequently used in cancer chemotherapy. (From AMA, Drug Evaluations Annual, 1994, p2033)
Absorption, Distribution and Excretion
Well absorbed with peak levels occurring between 2 to 6 hours following administration
The concentration of chloroquine, dapsone and pyrimethamine in plasma and milk were measured following the coadministration of a single dose of chloroquine and Maloprim to lactating women. The milk to plasma area under the concentration-time curve (AUC) ratio ranged from 1.96 to 4.26 for chloroquine, 0.22 to 0.45 for dapsone and 0.46 to 0.66 for pyrimethamine. Assuming a daily milk ingestion of 1 l by the infant, the maximum percentage of the maternal dose for chloroquine, dapsone and pyrimethamine in milk was 4.2%, 14.3% and 45.6%, respectively, over a 9 day period.
Pyrimethamine is excreted into milk. It is estimated that approximately 3-4 mg of the drug would be ingested by a nursing infant over the first 48-hour period following administration of a single 75-mg oral dose to the mother.
In this study, the kinetics of pyrimethamine elimination via the urine was investigated. The experiments were carried out on six healthy male volunteers aged 23-32 years. The drug was administered orally (p.o.) in a single dose at three different concentrations i.e.: 50, 75 and 100 mg. The concentration of the drug in the urine was determined via the modified method of Bonini et al. and Garber et al. It was found that 13.4 +/- 1.3% of the dose eliminated via the urine was in unchanged form. The process of pyrimethamine elimination may be described according to an open kinetic two-compartmental model: the formula showing the course of pyrimethamine elimination over time has been given. Several examples of the quantitative exposure test have been proposed, which allow the calculation of the drug dose absorbed and thus the degree of toxicity to be determined. This test can also be useful in a controlled clinical setting.
A pharmacokinetic study of pyrimethamine was carried out in 4- (103-115 g) and 12-week-old (260-280 g) white male Wistar rats fed a standard diet containing 24% protein, and a low-protein diet containing 8% protein. After intragastric administration of the drug in a single dose of 40 mg/kg body weight, the concentrations of pyrimethamine in the blood were determined at different time points from 15 min to 20 hours post-dose. On the basis of the results obtained, a number of parameters characterizing the course of absorption and elimination of the drug from the blood were calculated. The majority of parameters were dependent on both age and type of diet. The greatest bioavailability was observed in the 4-week-old rats: for the animals fed the low-protein diet, the area under the concentration-time curve (AUC) amounted to 593.0 and for those on the standard diet the AUC was 503.1. In the older rats, this parameter was 339.3 and 228.1 respectively. The k(e) values were lower in the younger rats (i.e. 0.0121 hr(-1) and 0.0135 h(-1)) than in the older animals (i.e. 0.0164 h(-1) and 0.0193 hr(-1) respectively). The elimination half-life (t1/2) was higher in the 4-week-old rats (i.e. 57.1 hr; 8% protein, and 51.2 hr; 24% protein) than in the 12-week-old animals (i.e. 42.4 hr; 8% protein, and 36.0 hr; 24% protein).
For more Absorption, Distribution and Excretion (Complete) data for Pyrimethamine (10 total), please visit the HSDB record page.
Cellular LocationsMembrane
Verwendung und Herstellung
Uses
MEDICATION
MEDICATION (VET)
For the treatment of toxoplasmosis and acute malaria; For the prevention of malaria in areas non-resistant to pyrimethamine
Methods of Manufacturing
Ethyl propionate is condensed with p-chlorophenylacetonitrile in the presence of sodium methylate. The resulting alpha-propionyl-p-chlorophenylacetonitrile is reacted with isoamyl alcohol to form the hemiacetal which undergoes dehydration to alpha-(p-chlorophenyl)-beta-ethyl-beta-isoamyloxylacrylonitrile. /alpha-(p-Chlorophenyl)-beta-ethyl-beta-isoamyloxylacrylonitrile/ is reacted with guanidine where upon cyclization occurs because of (a) the liberation of isoamyl alcohol by condensation involving the imino hydrogen of guanidine and the isoamyloxy group of alpha-(p-chlorophenyl)-beta-ethyl-beta-isoamyloxylacrylonitrile, and (b) an addition reaction involving an amino group of guanidine and nitrile group of alpha-(p-chlorophenyl)-beta-ethyl-beta-isoamyloxylacrylonitrile.
Formulations/PreparationsDaraprim Oral Tablets 25 mg, manufactured by GlaxoSmithKline
Use Classification
Animal Drugs -> FDA Approved Animal Drug Products (Green Book) -> Active Ingredients
Pharmaceuticals -> Animal Drugs -> Approved in Taiwan
Anwendungen
VerwendenFor the treatment of toxoplasmosis and acute malaria; For the prevention of malaria in areas non-resistant to pyrimethamine. Pyrimethamine is a dihydrofolate reductase inhibitor, like the biguanides, and is structurally related to trimethoprim. It is seldom used alone. Pyrimethamine in fixed combinations with dapsone or sulfadoxine is used for treatment and prophylaxis of chloroquine-resistant falciparum malaria. The synergistic activities of pyrimethamine and sulfonamides are similar to those of trimethoprim/sulfonamide combinations. Resistant strains of Plasmodium falciparum have appeared world wide. Prophylaxis against falciparum malaria with pyrimethamine alone is therefore not recommended. Most strains of Plasmodium vivax have remained sensitive. Pyrimethamine is also used in combination with a sulfonamide for the treatment of Toxoplasmosis. It is slowly absorbed from the gastrointestinal tract with peak plasma levels 4–6 hours after dosing. Pyrimethamine is bound to plasma proteins and is extensively metabolized before excretion. Its elimination half-life is 3–5 days.
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Anbieter50 Anbieter
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
衢州润东化工有限公司0570-8789886 18892685668 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
湖北威德利化学试剂有限公司181-6332-1995 18062128043 · [email protected]
Jai Radhe Sales+(91)-(79)-26431096/65255722 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
太原市瑞和丰科贸有限公司+86 351 7031519 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
上海泰坦科技股份有限公司400-6009262 15618770481 · [email protected]
上海隆盛化工有限公司58099637 13585536065 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
山东西亚化学有限公司13355009207 13355009207 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
斯百全化学(上海)有限公司021-021-021-67601398-809-809-809 15221380277 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
上海思域化工科技有限公司86-21-34053660 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
深圳康特腾科技有限公司86-0755-86635001 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
ApexBio Technology LLC+1-832-696-8203 · [email protected]
湖北威德利化学试剂有限公司186-02735115 18602735115 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
上海将来实业股份有限公司021-61552785 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
上海乾劲化工科技有限公司021-20900665 17321230821 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
凯试(上海)科技有限公司021-50135380 · [email protected]
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
天津阿尔塔科技有限公司022-6537-8550 15522853686 · [email protected]
TargetMol中国(陶术生物)021-021-33632979 15002134094 · [email protected]
上海陶术生物科技股份有限公司+1-781-999-5354; +1-00000000000 · [email protected]
成都瑞欧克科技有限公司028-64353063 · [email protected]
九鼎化学(上海)科技有限公司4009209199 · [email protected]
BOC Sciences16314854226; +8616314854226 · [email protected]
成都润泽本土化工有限公司028-88469284 18000562381 · [email protected]
南京艾比克斯生化科技有限公司025-87193546 18652950785 · [email protected]
上海思言生物科技有限公司021-50908862,442785678,326799392 18721037013 · [email protected]
南京熙朗化工产品有限公司18936048580 · [email protected]
Ergänzende Hinweise
DefinitionChEBI: An aminopyrimidine that is pyrimidine-2,4-diamine which is substituted at position 5 by a p-chlorophenyl group and at position 6 by an ethyl group. It is a folic acid antagonist used as an antimalarial or with a sulfonamide to treat toxoplasmo is.
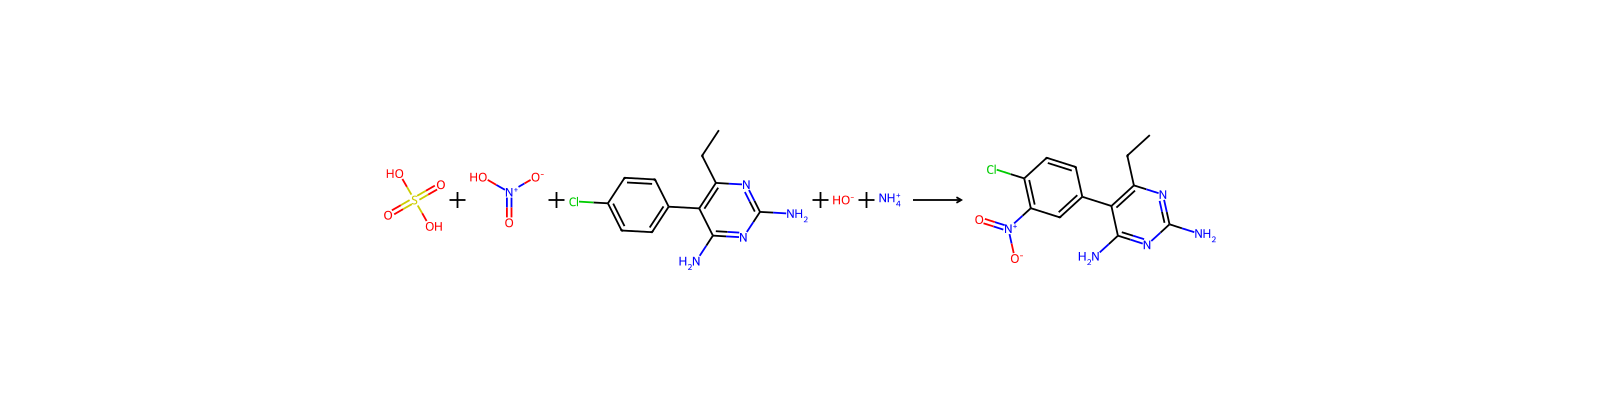
Zugehörige Reaktionen
19




Verknüpfte Notizen
Wird geladen…