

Grundinformationen
- Standard-SMILES
CC(C)(O)c1ccccc1CC[C@@H](SCC1(CC(=O)O)CC1)c1cccc(/C=C/c2ccc3ccc(Cl)cc3n2)c1- InChIKey
UCHDWCPVSPXUMX-TZIWLTJVSA-N- Summenformel
- C35H36ClNO3S
- Durchschnittliche Molmasse
- 586,2 g/mol
- Monoisotopische Masse
- 585,21044269
Überblick
Montelukast is an aliphatic sulfide, a monocarboxylic acid and a member of quinolines. It has a role as an anti-arrhythmia drug, a leukotriene antagonist and an anti-asthmatic drug. It is a conjugate acid of a montelukast(1-).
Namen und Bezeichner
- Bevorzugter Name
- Montelukast
- IUPAC
- 2-[1-[[(1R)-1-[3-[(E)-2-(7-chloroquinolin-2-yl)ethenyl]phenyl]-3-[2-(2-hydroxypropan-2-yl)phenyl]propyl]sulfanylmethyl]cyclopropyl]acetic acid
- Englischer Name
- Montelukast
- Summenformel
- C35H36ClNO3S
- Molmasse
- 586.18
Namen und Synonyme
montelukast158966-92-8Brondilat(R-(E))-1-(((1-(3-(2-(7-Chloro-2-quinolinyl)ethenyl)phenyl)-3-(2-(1-hydroxy-1-methylethyl)phenyl)propyl)thio)methyl)cyclopropaneacetic acidMHM278SD3E1-((((1R)-1-(3-((1E)-2-(7-Chloro-2-quinolinyl)ethenyl)phenyl)-3-(2-(1-hydroxy-1-methylethyl)phenyl)propyl)thio)methyl)cyclopropaneacetic acidDTXSID9023334CHEBI:50730Cyclopropaneacetic acid, 1-(((1-(3-(2-(7-chloro-2-quinolinyl)ethenyl)phenyl)-3-(2-(1-hydroxy-1-methylethyl)phenyl)propyl)thio)methyl)-, (R-(E))-1-[[[(1 R)-1-[3-[(1E)-2-(7-chloro-2-quinolinyl)ethenyl] phenyl]-3-[2-(1-hydroxy-1-methylethyl)phenyl]propyl]sulfanyl]methyl]cyclopropaneacetic acidMontelukastum1-((((1 R)-1-(3-((1E)-2-(7-chloro-2-quinolinyl)ethenyl) phenyl)-3-(2-(1-hydroxy-1-methylethyl)phenyl)propyl)sulfanyl)methyl)cyclopropaneacetic acid
Weitere Namen anzeigen
Montelukast AcidMontelukMontelukasMontelukast USP/EP/BP(R,E)-2-(1-(((1-(3-(2-(7-Chloroquinolin-2-yl)vinyl)phenyl)-3-(2-(2-hydroxypropan-2-yl)phenyl)propyl)thio)methyl)cyclopropyl)acetic acidSingularMontelukastlMontelukast(Form A)
RefChem:6040DTXCID403334R03DC031-((((1R)-1-(3-((E)-2-(7-chloro-2-quinolinyl)ethenyl)phenyl)-3-(2-(1-hydroxy-1-methylethyl)phenyl)propyl)thio)methyl)-cyclopropaneacetic acidMK-0476Singulair142522-28-92-[1-[[(1R)-1-[3-[(E)-2-(7-chloroquinolin-2-yl)ethenyl]phenyl]-3-[2-(2-hydroxypropan-2-yl)phenyl]propyl]sulfanylmethyl]cyclopropyl]acetic acid
Datenbank-Bezeichner
- CAS
158966-92-8- PubChem CID
- 5281040
- DTXSID
DTXSID9023334- ChEMBL
CHEMBL787- ChEBI
CHEBI:50730- UNII
- MHM278SD3E
- EC Number
- 605-168-4
- Nikkaji
- J2.625.694A、J870.100H
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 7,7
- Polarare Oberfläche (TPSA)
- 95,7 Ų
- H-Brücken-Donoren
- 2
- H-Brücken-Akzeptoren
- 5
- Frei drehbare Bindungen
- 12
- Schwere Atome
- 41
- Formalladung
- 0
- Komplexität
- 891
Experimentelle und physikochemische Eigenschaften
DrugsPharmaceuticals -> Listed in ZINC15
LogP7.9
Solubility
mixes with water (>100 mg/ml, 25 C)
MW 608.17, Hygroscopic, white to off-white powder. Freely sol in ethanol, methanol, water. Practically insol in acetonitrile /Monosodium salt/
8.20e-06 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anti-Asthmatic Agents; Leukotriene Antagonists
Pharmaceuticals
Physical DescriptionSolid
Collision Cross Section243 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
Physikochemische Eigenschaften
- Schmelzpunkt
- 145 · 145-148 °C(Solv: toluene (108-88-3); methanol (67-56-1))
- Siedepunkt
- 750.5 · 750.5±60.0 °C(Predicted)
- Dichte
- 1.272 · 1.272±0.06 g/cm3(Predicted)
- storage temp.
- 2 · Store at 2-8°C
- Löslichkeit
- 2 mg/ml,DMSO: · DMF: 2 mg/ml,DMSO: 2 mg/ml,Ethanol: insol,PBS (pH 7.2): insol
- Aggregatzustand
- A solid
- pka
- 4.76 · 4.76±0.10(Predicted)
- Farbe
- Light yellow to yellow
- InChIKey
- UCHDWCPVSPXUMX-TZIWLTJVSA-N
- SMILES
- C1(CS[C@@H](C2=CC=CC(/C=C/C3C=CC4C(N=3)=CC(Cl)=CC=4)=C2)CCC2=CC=CC=C2C(O)(C)C)(CC(O)=O)CC1
- CAS Datenbank
- 158966 · 158966-92-8(CAS DataBase Reference)
- EPA chemische Informationen
- 1 · Cyclopropaneacetic acid, 1-[[[(1R)-1-[3-[(1E)-2-(7-chloro-2-quinolinyl)ethenyl]phenyl]-3-[2-(1-hydroxy-1-methylethyl)phenyl]propyl]thio]methyl]- (158966-92-8)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
This chemical does not meet GHS hazard criteria for 50% (1 of 2) of reports.
Warning
H302 (50%): Harmful if swallowed [Warning Acute toxicity, oral]
P261, P264, P270, P271, P280, P301+P317, P302+P352, P304+P340, P317, P321, P330, P362+P364, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 2 reports by companies from 2 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Gefahrenhinweise
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl Montelukast sodium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Montelukast sodium/
Sicherheit und Schutzausrüstung
Storage Conditions
Commercially available montelukast sodium film-coated and chewable tablets and oral granules should be stored at 25 °C and protected from light and moisture with exposure for short periods to temperatures of 15-30 °C permitted. When stored as directed, montelukast sodium film-coated and chewable tablets have an expiration date of 2 years after the date of manufacture.
Disposal Methods
SRP: At the time of review, criteria for land treatment or burial (sanitary landfill) disposal practices are subject to significant revision. Prior to implementing land disposal of waste residue (including waste sludge), consult with environmental regulatory agencies for guidance on acceptable disposal practices.
Toxikologische Informationen
Interactions
Concurrent use /of phenobarbital/ results in significant decreases (approximately 40%) in the area under the curve [AUC] for montelukast, of induction of hepatic metabolism...
... This study was designed to evaluate whether montelukast at clinically used dosage levels would interfere with the anticoagulant effect of warfarin. In a two-period, double-blind, randomized crossover study, 12 healthy male subjects received a single oral dose of 30 mg warfarin on the 7th day of a 12-day treatment with montelukast, 10 mg daily by mouth, or a placebo. Montelukast had no significant effect on the area under the plasma concentration-time curves and peak plasma concentrations of either R- or S-warfarin. However, slight but statistically significant decreases in time to peak concentration of both warfarin enantiomers and in elimination half-life of the less potent R-warfarin were observed in the presence of montelukast. These changes were not considered as clinically relevant. Montelukast had no significant effect on the anticoagulant effect of warfarin, as assessed by the international normalized ratio (INR) for prothrombin time (AUC0-144 and INR maximum). The results of this study suggest that a clinically important interaction between these drugs is unlikely to occur in patients requiring concomitant administration of both drugs.
The effect of montelukast (MK-0476), a cysteinyl leukotriene receptor antagonist, ... on single-dose theophylline plasma concentrations was studied in three separate clinical trials. Montelukast was evaluated at 10 mg once daily (the clinical dosage), 200 mg once daily, and 600 mg (200 mg three times daily). At the clinical dosage, montelukast did not change single-dose theophylline plasma concentration in a clinically important manner. The geometric mean ratios for theophylline area under the plasma concentration versus time curve (AUC0-->infinity ) (0.92) and maximal plasma concentration (Cmax ) (1.04) were well within the predefined and generally accepted bioequivalence range of 0.80 and 1.25. Montelukast decreased theophylline Cmax by 12% and 10%, AUC0-->infinity by 43% and 44%, and elimination half-time by 44% and 39% at 200 mg/d (oral and intravenous, respectively), and at 600 mg/d, montelukast decreased theophylline Cmax by 25%, AUC0-->infinity by 66%, and elimination half-time by 63%. These results show that montelukast at the clinical dosage did not change theophylline pharmacokinetics in a clinically important manner, but at 20- to 60-fold higher dosages, montelukast significantly reduced the theophylline pharmacokinetics parameters; an apparent dosage dependence is suggested.
High aminotransferases and prolonged prothrombin time on entering our liver unit were revealing parenchymal collapse for this 45-year-old obese woman; treatment failure led her to death. Autoimmunity, paracetamol use, alcoholism, and Wilson's disease were all excluded as causes. Because of chronic asthma, she had been receiving a leukotriene receptor antagonist (montelukast) for 5 years before the current presentation; 1 week before onset she had had 1 week of treatment with two dietary supplements for weight control; one of these included Garcinia Cambogia, a possible cause of two recent cases of hepatitis in the USA; in addition, both formulas contained a citrus derivative that interferes cytochrome functions. /The authors/ speculate on a causal relationship between the assumption of the additives and the fatal hepatitis and envisage a synergy between the additives and montelukast, which per se has well been studied as a hepatotoxic drug. Despite the speculative nature of this presentation, /investigators/ believe the warning may serve to focus attention on the uncontrolled escalation of food additives going on /at present/.
... The present case describes an asthmatic patient, who developed severe obstructive symptoms and progressive heart failure after two sequential exposures to montelukast. As the patient exhibited a markedly raised blood eosinophil count with diffuse infiltrates on chest x-ray and signs of myocarditis, Churg-Strauss syndrome (CSS) was suspected. The disease was confirmed by open lung biopsy. The symptoms improved rapidly after administration of high dose immunosuppression with methylprednisolone and cyclophosphamide. This case is noteworthy because the time course of events strongly suggests a direct aetiological role for montelukast in the development of CSS. The pathophysiological mechanism of the association remains unknown.
Hepatotoxicity
In clinical trials, mild elevations in serum aminotransferase levels were found in 1% to 2% of patients taking montelukast chronically, but similar rates are reported in matched placebo recipients. The ALT abnormalities were usually mild, asymptomatic and self limited. Clinically apparent liver injury from montelukast is rare; but more than a dozen cases reported in the literature. In these cases, the latency to onset of injury was highly variable, ranging from a few days to several years. Patients presented with anorexia, nausea, right upper quadrant pain, dark urine, and jaundice. The pattern of enzyme elevation was usually mixed, but both hepatocellular or cholestatic patterns have been reported. Allergic features and autoantibody formation were rare. Eosinophilia was often reported, but this may have been due to the underlying allergic condition rather than the liver injury. The injury usually resolved within 1 to 4 months of stopping the drug.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 6.0X10+7(SRC), determined from a structure estimation method(2), indicates that montelukast is expected to be immobile in soil(SRC). The estimated pKa of montelukast is 4.3(3), indicating that this compound will primarily exist in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization of montelukast from moist soil surfaces is not expected to be an important fate process(SRC) based upon the estimated pKa(3). Montelukast is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 4.1X10⁻²¹ mm Hg(SRC), determined from a fragment constant method(5). Biodegradation data for montelukast were not available(SRC, 2008).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 6.0X10+7(SRC), determined from a structure estimation method(2), indicates that montelukast is expected to adsorb to suspended solids and sediment(SRC). An estimated pKa of 4.3(3) indicates montelukast will exist almost entirely in the anion form at pH values of 5 to 9 and therefore volatilization from water surfaces is not expected to be an important fate process(4). According to a classification scheme(5), an estimated BCF of 3.2(SRC), from an estimated log Kow of 9.5(6) and a regression-derived equation(7), suggests the potential for bioconcentration in aquatic organisms is low(SRC). Biodegradation data for montelukast were not available(SRC, 2008).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), montelukast, which has an estimated vapor pressure of 4.1X10⁻²¹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase montelukast may be removed from the air by wet or dry deposition(SRC). Montelukast contains chromophores that absorb at wavelengths >290 nm(3) and therefore may be susceptible to direct photolysis by sunlight(SRC).
Adverse Effects
Neuropsychiatric events have been reported in patients receiving montelukast. These events have been noted in adults, teenagers, and younger patients. They include, but are not limited to: anxiety, depression, aggressiveness, agitation, attention and memory impairment, sleeping disorders (insomnia, somnambulism, dream anomalies), seizures, paresthesia, hypoesthesia, as well as suicidal thoughts and behavior.
Toxicity Summary
In clinical studies, montelukast has been used at high doses in adult patients (up to 200 mg daily for 22 weeks and up to 900 mg daily for about a week) without significant adverse effects. Cases of acute overdosage with montelukast have been reported in adults and children with doses as high as 1000 mg. However, clinical and biological signs in such cases were relatively benign, including headaches, thirst, somnolence or hyperactivity, vomiting, and abdominal pain.
Soil Adsorption/Mobility
Using a structure estimation method based on molecular connectivity indices(1), the Koc of montelukast can be estimated to be 6.0X10+7(SRC). According to a classification scheme(2), this estimated Koc value suggests that montelukast is expected to be immobile in soil. The estimated pKa of montelukast is 4.3(3), indicating that this compound will primarily exist in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4).
Human Toxicity Excerpts
/SIGNS AND SYMPTOMS/ There have been reports of acute overdosage with Montelukast doses of up to 1 g in adults and children. While adverse effects were not reported in most incidents of overdosage, the most frequently reported adverse experiences that were reported included abdominal pain, somnolence, thirst, headache, vomiting, and psychomotor hyperactivity. Clinical and laboratory findings associated with these reports were consistent with the safety profile of the drug in adults and pediatric patients.
/CASE REPORTS/ The case history is presented of a man with allergic rhinitis and asthma who had received intermittent pulse therapy with oral corticosteroids. Pulmonary eosinophilia developed while he was receiving treatment with montelukast, a chemically distinct cysteinyl leukotriene type 1 receptor antagonist. After discontinuation of montelukast therapy and administration of systemic corticosteroids the patient's symptoms reversed rapidly and there was prompt resolution of the pulmonary infiltrates. /Investigators/ believe that cysteinyl leukotriene type 1 receptor antagonists are safe and effective drugs for most patients with asthma but caution is needed for those with more severe disease who require systemic corticosteroids, especially if they show characteristics of the atypical allergic diathesis seen in the prodromal phase of Churg-Strauss syndrome.
/CASE REPORTS/ A 68-year-old asthmatic presented markedly unwell with arthralgia, mononeuritis multiplex, peripheral neuropathy, and eosinophilia. His past medical history included perennial rhinitis, and nasal polyps. Three months prior to admission his prednisolone was stopped and Montelukast was started. The diagnosis of Montelukast-associated Churg-Strauss syndrome was made. The drug was stopped and steroids started with general improvement and reduction of eosinophilia; however, the neurological deficit persisted.
/CASE REPORTS/ ... A 28-year-old man with allergic rhinitis and moderate persistent asthma developed generalized urticaria 5 days after the initiation of montelukast and inhaled fluticasone. Symptoms disappeared within one day after suspension of both drugs. Two months later, after the resumption of montelukast and fluticasone, the patient developed generalized urticaria and eyelid angioedema, which were successfully treated with intravenous betamethasone, achieving complete remission within hours. After 2 days, the patient resumed inhaled fluticasone only and continued this therapy for several months without any adverse reaction. /Investigators/ attributed the adverse reaction to montelukast because of the temporal relationship between use of montelukast and urticaria, the absence of other identified causative factors and other explanations for allergic reactions, and the positive dechallenge and rechallenge. The Naranjo probability scale showed a probable relationship between skin manifestations and montelukast treatment. ...
For more Human Toxicity Excerpts (Complete) data for MONTELUKAST (9 total), please visit the HSDB record page.
Artificial Pollution SourcesMontelukast's production and use as an antiasthmatic(1) may result in its release to the environment through various waste streams(SRC).
Drug Induced Liver Injury
Benchmark Dataset for the Liver Toxicity Knowledge Base (LTKB)
montelukast
Singulair®
Antiasthamatics
3
less-DILI-concern drugs
Environmental Bioconcentration
An estimated BCF of 3.2 was calculated for montelukast(SRC), using an estimated log Kow of 9.5(1) and a regression-derived equation(2). According to a classification scheme(3), this BCF suggests the potential for bioconcentration in aquatic organisms is low(SRC).
Volatilization from Water/Soil
An estimated pKa of 4.3(1) indicates montelukast will exist almost entirely in the anion form at pH values of 5 to 9 and therefore volatilization from water surfaces or moist soil is not expected to be an important fate process(2). Montelukast is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 4.1X10⁻²¹ mm Hg(SRC), determined from a fragment constant method(3).
Non-Human Toxicity Excerpts
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ A 2-year study in Sprague-Dawley rats at oral (gavage) doses of up to 200 mg per kg of body weight per day (mg/kg/day) (approximately 160 and 190 times the maximum recommended daily oral dose in adults and children, respectively, on a mg per square meter of body surface area basis) found no evidence of carcinogenicity or tumorigenicity.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ A 92-week study in mice at oral doses of up to 100 mg/kg/day (approximately 40 and 50 times the maximum recommended daily oral dose in adults and children, respectively, on a mg per square meter of body surface area basis) found no evidence of carcinogenicity or tumorigenicity.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ Studies in rats at oral doses of up to 400 mg/kg/day (approximately 320 times the maximum recommended daily oral dose in adults on a mg per square meter of body surface area basis) and in rabbits at oral doses of up to 300 mg/kg/day (approximately 490 times the maximum recommended daily oral dose in adults on a mg per square meter of body surface area basis) found no evidence of teratogenicity.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ No reduction in fertility was seen in male rats at oral doses of up to 800 mg/kg (approximately 650 times the maximum recommended daily oral dose in adults, on a mg per square meter of body surface area basis).
For more Non-Human Toxicity Excerpts (Complete) data for MONTELUKAST (6 total), please visit the HSDB record page.
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl Montelukast sodium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Montelukast sodium/
Sicherheitsdaten
- Giftige Stoffe Daten
- 158966-92-8(Hazardous Substances Data)
Chemie und Industrie
Pharmakologische Informationen
ATC Code
R03DC03
R - Respiratory system
QR - Respiratory system
Protein BindingIt has been determined that the protein binding of montelukast to plasma proteins exceeds 99%.
Pharmacodynamics
Montelukast is a leukotriene receptor antagonist that demonstrates a marked affinity and selectivity to the cysteinyl leukotriene receptor type-1 in preference to many other crucial airway receptors like the prostanoid, cholinergic, or beta-adrenergic receptors. As a consequence, the agent can elicit substantial blockage of LTD4 leukotriene-mediated bronchoconstriction with doses as low as 5 mg. Moreover, a placebo-controlled, crossover study (n=12) demonstrated that montelukast is capable of inhibiting early and late phase bronchoconstriction caused by antigen challenge by 75% and 57% respectively. In particular, it has been documented that montelukast can cause bronchodilation as soon as within 2 hours of oral administration. This action can also be additive to the bronchodilation caused by the concomitant use of a beta agonist. Nevertheless, clinical investigations performed with adults 15 years of age and older revealed that no additional clinical benefit is obtained when doses of montelukast greater than 10 mg a day are used. Additionally, in clinical trials with adults and pediatric asthmatic patients aged 6 to 14 years, it was also determined that montelukast can reduce mean peripheral blood eosinophils by about 13% to 15% from baseline in comparison to placebo during double-blind treatment periods. At the same time, in patients aged 15 years and older who were experiencing seasonal allergic rhinitis, the use of montelukast caused a median reduction of 13% in peripheral blood eosinophil counts when compared to placebo as well.
Mechanism of Action
Cysteinyl leukotrienes (CysLT) like LTC4, LTD4, and LTE4, among others, are eicosanoids released by a variety of cells like mast cells and eosinophils. When such CysLT bind to corresponding CysLT receptors like CysLT type-1 receptors located on respiratory airway smooth muscle cells, airway macrophages, and on various pro-inflammatory cells like eosinophils and some specific myeloid stem cells activities that facilitate the pathophysiology of asthma and allergic rhinitis are stimulated. In particular, CysLT-mediated airway bronchoconstriction, occluding mucous secretion, vascular permeability, and eosinophil recruitment are all types of effects that facilitate asthma. Alternatively, in allergic rhinitis, CysLTs are released by the nasal mucosa when exposed to allergens during both early and late phase reactions and participate in eliciting symptoms of allergic rhinitis like a congested nose and airway. Subsequently, montelukast is a leukotriene receptor antagonist that binds with high affinity and selectivity to the CysLT type 1 receptor, which consequently assists in inhibiting any physiological actions of CysLTs like LTC4, LTD4, and LTE4 at the receptor that may facilitate asthma or allergic rhinitis.
Montelukast inhibits bronchoconstriction due to antigen challenge. Montelukast is a selective leukotriene receptor antagonist of the cysteinyl leukotriene CysLT1 receptor. The cysteinyl leukotrienes (LTC4 , LTD4, LTE4) are products of arachidonic acid metabolism that are released from various cells, including mast cells and eosinophils. They bind to cysteinyl leukotriene receptors (CysLT) found in the human airway. Binding of cysteinyl leukotrienes to leukotriene receptors has been correlated with the pathophysiology of asthma, including airway edema, smooth muscle contraction, and altered cellular activity associated with the inflammatory process, factors that contribute to the signs and symptoms of asthma. Montelukast binding to the CysLT1, receptor is high-affinity and selective, preferring the CysLT1 receptor to other pharmacologically important airway receptors, such as the prostanoid, cholinergic, or beta-adrenergic receptor. Montelukcast inhibits physiologic actions of LTD4 at the CysLT1 receptors, without any agonist activity.
Because of the role of leukotrienes in the pathogenesis of asthma, modification of leukotriene activity may be used to reduce airway symptoms, decrease bronchial smooth muscle tone, and improve asthma control. Inhibition of leukotriene-mediated effects may be achieved by drugs that interrupt 5-lipoxygenase activity and prevent formation of leukotrienes (e.g., zileuton) or by antagonism of leukotriene activity at specific receptor sites in the airway (e.g., montelukast, zafirlukast). The antagonist activity of montelukast is selective, competitive, and reversible. Montelukast competitively inhibits the action of LTD4 at a subgroup of CysLT receptors (CysLT1) in airway smooth muscle. In vitro, montelukast possesses affinity for the CysLT1 receptor that is similar to that of LTD4. In in vitro studies, montelukast antagonized contraction of isolated animal smooth muscle produced by LTD4, but did not antagonize contraction produced by LTC4. In animal studies, montelukast antagonized contraction of airway smooth muscle produced by LTD4 or antigen.
Biological Half-Life
Studies have demonstrated that the mean plasma half-life of montelukast varies from 2.7 to 5.5 hours when observed in healthy young adults.
The mean plasma elimination half-life of montelukast in adults 19-48 years of age is 2.7-5.5 hours, and plasma clearance averages 45 mL/minute. A plasma elimination half-life of 3.4-4.2 hours has been reported in children 6-14 years of age. Limited data indicate that the plasma elimination half-life of montelukast is prolonged slightly in geriatric adults and in patients with mild to moderate hepatic impairment, although dosage adjustment is not required. A plasma elimination half-life of 6.6 or 7.4 hours has been reported in geriatric adults 65-73 years of age or patients with mild to moderate hepatic impairment, respectively.
Metabolism/Metabolites
It has been determined that montelukast is highly metabolized and typically so by the cytochrome P450 3A4, 2C8, and 2C9 isoenzymes. In particular, it seems that the CYP2C8 enzymes play a significant role in the metabolism of the drug. Nevertheless, at therapeutic doses, the plasma concentrations of montelukast metabolites are undetectable at steady state in adults and pediatric patients.
Biotransformation /is/ hepatic and extensive involving cytochrome P450 3A4 and 2C9
The metabolic fate of montelukast has not been fully determined, but the drug is extensively metabolized in the GI tract and/or liver and excreted in bile. Several metabolic pathways have been identified including acyl glucuronidation, and oxidation catalyzed by several cytochrome P-450 (CYP) isoenzymes. In vitro studies indicate that the microsomal P-450 isoenzyme CYP3A4 is the major enzyme involved in formation of the 21-hydroxy metabolite (M5) and a sulfoxide metabolite (M2), and CYP2C9 is the major isoenzyme involved in the formation of the 36-hydroxy metabolite (M6). Other identified metabolites include an acyl glucuronide (M1) and a 25-hydroxy (a phenol, M3) analog.
Following oral administration of 54.8 mg of radiolabeled montelukast, metabolites of the drug represented less than 2% of circulating radioactivity. Montelukast metabolites that have been identified in plasma in radiolabeled studies include the 21-hydroxy (diastereomers of a benzylic acid, M5a and M5b) and the 36-hydroxy (diastereomers of a methyl alcohol, M6a and M6b) metabolites. Following oral administration of therapeutic doses of montelukast, plasma concentrations of metabolites at steady-state in adults and children were below the level of detection.
Montelukast has known human metabolites that include Montelukast 1, 2-Diol, 21(S)-Hydroxy Montelukast, 21-Hydroxymontelukast, and montelukast sulfoxide.
FDA Pharmacological Classification
MHM278SD3E
MONTELUKAST
Established Pharmacologic Class [EPC] - Leukotriene Receptor Antagonist
Mechanisms of Action [MoA] - Leukotriene Receptor Antagonists
Montelukast is a Leukotriene Receptor Antagonist. The mechanism of action of montelukast is as a Leukotriene Receptor Antagonist.
MONTELUKAST
MeSH Pharmacological Classification
Drugs that are used to treat asthma.
A class of drugs designed to prevent leukotriene synthesis or activity by blocking binding at the receptor level.
Drugs and compounds that induce the synthesis of CYTOCHROME P-450 CYP1A2.
Absorption, Distribution and Excretion
It has been observed that montelukast is quickly absorbed following administration by the oral route. The oral bioavailability documented for the drug is 64%. Furthermore, it seems that having a regular meal in the morning or even a high fat snack in the evening does not affect the absorption of montelukast.
It has been reported that montelukast and its metabolites are almost exclusively excreted in the bile and into the feces.
The steady-state volume of distribution recorded for montelukast is an average between 8 to 11 litres.
The plasma clearance documented for montelukast is an average of 45 mL/min when observed in healthy adults.
Montelukast is rapidly absorbed from the GI tract, and peak plasma concentrations are attained within 3-4, 2-2.5, or 2 hours following oral administration in the fasted state of a single 10-mg film-coated (in adults), 5-mg chewable (in adults), or 4-mg chewable (in children 2-5 years of age) tablet, respectively. ... Ingestion of a high-fat meal in the morning with the 4-mg oral granules formulation had no effect on the AUC of montelukast; however, the time to peak plasma concentrations was prolonged from 2.3 hours to 6.4 hours and peak plasma concentrations were reduced by 35%.
Absorption /of montelukast is/ rapid. For the 10-mg tablets: mean oral bioavailability is 64%. Bioavailability is not affected by a standard meal in the morning. For the 5-mg chewable tablet: mean oral bioavailability is 73% in the fasted state versus 63% when administered with a standard meal in the morning.
Cellular LocationsCytoplasm
Verwendung und Herstellung
Uses
MEDICATION
Therapeutic Category: Antiasthmatic
Use (kg; approx.) in Germany (2009): >250
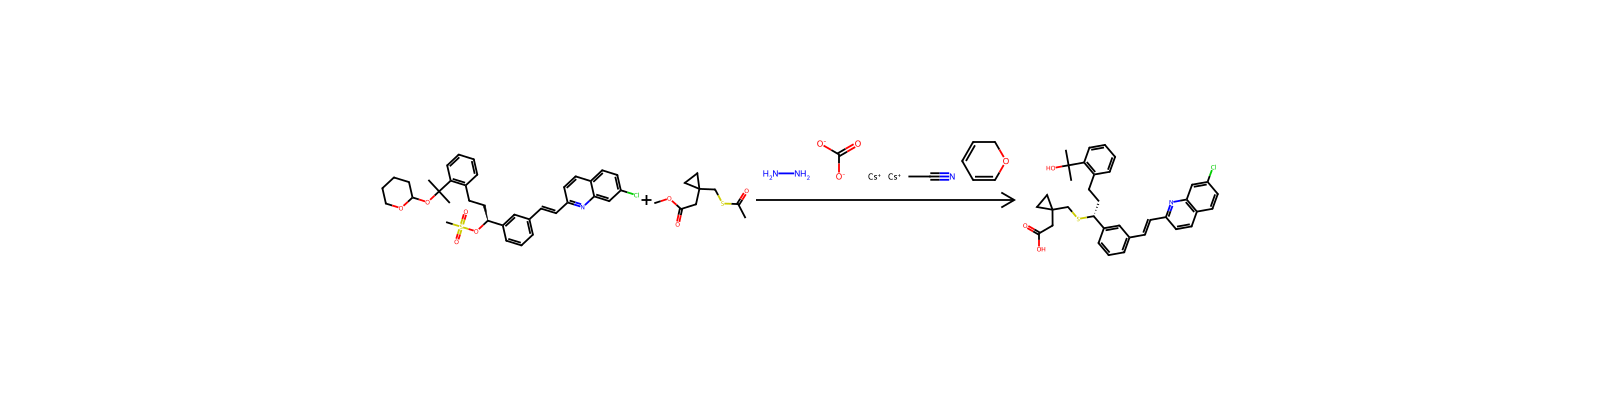
Methods of ManufacturingPreparation: ML Belley et al, EP 480717; eidem, US 5565473 (1992, 1996 both to Merck Frosst)
Formulations/PreparationsMontelukast oral formulations: Granules 4 mg (of Montelukast) Singulair, Merck; Tablets, chewable 4 and 5 mg (of Montelukast) Singulair, Merck; Tablets, film-coated 10 mg (of Montelukast) Singulair, Merck
Use ClassificationPharmaceuticals
General Manufacturing InformationMontelukast sodium, the active ingredient in Singulair, is a selective and orally active leukotriene receptor antagonist that inhibits the cysteinyl leukotrience CysLT, receptor. /Montelukast sodium/
Anwendungen
BeschreibungMontelukast is a leukotriene receptor antagonist prescribed as add-on therapy for asthma[1]. The drug is evaluated for preventing and treating capsular contracture in breast implant surgery, where it reduces incidence rates in specific patient groups[2]. Pharmacovigilance reports indicate that users exhibit higher levels of anxiety and depression[1].
Verwendencardiostimulant,
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Anbieter50 Anbieter
北京华美互利生物化工010-56205725 · [email protected]
武汉英诺医药科技有限公司+86-027-59232304 15387063101 · [email protected]
成都超九八生物科技有限公司13348960310 13348960310 · [email protected]
上海麦克林生化科技股份有限公司021-50706066 15221275939 · [email protected]
咸宁深蓝生物医药研发有限公司18171815831 · [email protected]
杭州品高化工有限公司0571-87658025 · [email protected]
普善实业(陕西)有限公司029-81310890 18165209495 · [email protected]
湖北科乐精细化工有限公司027-59101668 19945030958 · [email protected]
Dayang Chem (Hangzhou) Co.,Ltd.+86-0571-88938639 17705817739 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
深圳市简一生物科技有限公司0755-84826604 · [email protected]
湖北威德利化学试剂有限公司17771473825 13385289472 · [email protected]
山东八方化工科技有限公司0535-15589503653 15589503653
安耐吉化学&3A(安徽泽升科技有限公司)021-58432009 400-005-6266 · [email protected]
北京亿思研科技开发中心010-56645598 13366904824 · [email protected]
梯希爱(上海)化工贸易有限公司021-61109150 · [email protected]
China Kouting Group Limited+86 (21) 5811-6473 5811-6475 · [email protected]
深圳市恩赞生物医药有限公司0755-25325458 13602565027 · [email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
学研惠(武汉)科技有限公司15727060112 · [email protected]
上海尺水药物研究有限公司[email protected] 13564957716 · [email protected]
武汉丰泰威远科技有限公司+86-27-8746-5837 +86-18627785180 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
河北茹麒科技有限公司176-03256889 17603256889 · [email protected]
BOC Sciences1-631-485-4226; 16314854226 · [email protected]
上海健超生物科技有限公司15021035486 18081542813 · [email protected]
湖北斯麦尔医药科技有限公司15527913960 · [email protected]
上海明褀化学有限公司86-21-60936353
深圳菲斯生物科技有限公司0755-83725681-603
Shenzhen Excellent Biotech Co., Ltd.13480692018 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
天津普西唐生物医药科技有限公司010-60605840 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
上海孚一生物科技有限公司+86 (21) 61124340
池州凯隆进出口贸易有限公司[email protected]
Sigma-Aldrich西格玛奥德里奇(上海)贸易有限公司021-61415566 800-8193336 · [email protected]
AN PharmaTech Co Ltd86(21)68097365 · [email protected]
江苏倍达医药科技有限公司0512-63009836 18994340901 · [email protected]
TargetMol中国(陶术生物)021-021-33632979 15002134094 · [email protected]
南京红胜火生物科技有限公司025-58311670 18020159086 · [email protected]
上海陶术生物科技股份有限公司+1-781-999-5354; +1-00000000000 · [email protected]
湖北威德利化学科技有限公司027-83989310 18627915365
武汉峰耀同辉化学制品有限公司027-87466205 15377579727 · [email protected]
西安美川生物科技有限公司029-89275612 +8618991951683 · [email protected]
武汉鑫儒化工有限公司15927387915 15337108568
广东翁江化学试剂有限公司0751-2886766 13927870850 · [email protected]
Zugehörige Reaktionen
11




Verknüpfte Notizen
Wird geladen…