

Grundinformationen
- Standard-SMILES
Nc1ccn([C@@H]2O[C@H](CO)[C@@H](O)C2(F)F)c(=O)n1- InChIKey
SDUQYLNIPVEERB-QPPQHZFASA-N- Summenformel
- C9H11F2N3O4
- Durchschnittliche Molmasse
- 263,2 g/mol
- Monoisotopische Masse
- 263,07176216
Namen und Bezeichner
- Bevorzugter Name
- Gemcitabine
- IUPAC
- 4-amino-1-[(2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]pyrimidin-2-one
- Englischer Name
- Gemcitabine
- Summenformel
- C9H11F2N3O4
- Molmasse
- 263.2
Namen und Synonyme
gemcitabine95058-81-42'-Deoxy-2',2'-difluorocytidine2',2'-DifluorodeoxycytidinedFdCGemcitabinaGemcitabinumDFdCydLY-188011LY1880114-amino-1-[(2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]-1,2-dihydropyrimidin-2-oneB76N6SBZ8R
Weitere Namen anzeigen
GeMcitabinGEMCITABINE HCL USP4-amino-1-[(2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]pyrimidin-2(1H)-one4-Amino-1-((2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)tetrahydrofuran-2-yl)pyrimidin-2(1H)-oneZefeiGemcelGemLipT11BaseLY-18011
2',2'-difluoro-2'-deoxycytidine4-Amino-1-[(2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)oxolan-2-yl]pyrimidin-2-oneNSC-613327DTXSID30404872'deoxy-2',2'-difluorocytidineCHEBI:1759014-amino-1-((2R,4R,5R)-3,3-difluoro-4-hydroxy-5-(hydroxymethyl)-tetrahydrofuran-2-yl)pyrimidin-2(1H)-onegemicitabine
Datenbank-Bezeichner
- CAS
95058-81-4- PubChem CID
- 60750
- DTXSID
DTXSID3040487- ChEMBL
CHEMBL888- ChEBI
CHEBI:175901- UNII
- B76N6SBZ8R
- EC Number
- 619-100-6
- Nikkaji
- J357.909C
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- -1,5
- Polarare Oberfläche (TPSA)
- 108 Ų
- H-Brücken-Donoren
- 3
- H-Brücken-Akzeptoren
- 6
- Frei drehbare Bindungen
- 2
- Schwere Atome
- 18
- Formalladung
- 0
- Komplexität
- 426
Experimentelle und physikochemische Eigenschaften
LogP
-1.4
-1.4
Color/FormCrystals from water, pH = 8.5
Solubility
15.3
2.23e+01 g/L
Melting Point168.64 °C
Optical Rotation
Crystals from water-acetone, mp 287-292 °C (dec). Specific optical rotation = +48 deg at 25 °C/D; +257.9 deg at 365 °C (c = 1.0 in deuterated water). UV max (water): 232, 268 nm (epsilon 7960, 9360). /Hydrochloride/
Specific optical rotation: +425.36 deg at 365 °C; + 71.51 deg at 25 °C/D (c = 0.96 in methanol)
Physical DescriptionSolid
Dissociation Constants3.6
Other Experimental PropertiesWhite to off-white solid. MW: 299.66. Soluble in water, slightly soluble in methanol, and practically insoluble in ethanol and polar solvents. /Hydrochloride/
Physikochemische Eigenschaften
- Schmelzpunkt
- 168 · 168,64 C
- Siedepunkt
- 482.7 · 482.7±55.0 °C(Predicted)
- Dichte
- 1.84 · 1.84±0.1 g/cm3(Predicted)
- storage temp.
- -20 °C · Keep in dark place,Sealed in dry,Store in freezer, under -20°C
- Löslichkeit
- Methanol (Slightly), Water (Slightly, Heated)
- pka
- 11.65 · 11.65±0.70(Predicted)
- Aggregatzustand
- Solid
- Farbe
- White to Off-White
- InChI
- InChI=1S/C9H11F2N3O4/c10-9(11)6(16)4(3-15)18-7(9)14-2-1-5(12)13-8(14)17/h1-2,4,6-7,15-16H,3H2,(H2,12,13,17)/t4-,6-,7-/m1/s1
- InChIKey
- SDUQYLNIPVEERB-QPPQHZFASA-N
- SMILES
- OC[C@H]1O[C@@H](N2C=CC(N)=NC2=O)[C@](F)(F)[C@@H]1O
- CAS Datenbank
- 95058 · 95058-81-4(CAS DataBase Reference)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Danger
H302 (20%): Harmful if swallowed [Warning Acute toxicity, oral];H312 (40%): Harmful in contact with skin [Warning Acute toxicity, dermal];H315 (80%): Causes skin irritation [Warning Skin corrosion/irritation];H319 (80%): Causes serious eye irritation [Warning Serious eye damage/eye irritation];H335 (20%): May cause respiratory irritation [Warning Specific target organ toxicity, single exposure; Respiratory tract irritation];H340 (40%): May cause genetic defects [Danger Germ cell mutagenicity];H351 (20%): Suspected of causing cancer [Warning Carcinogenicity];H360 (20%): May damage fertility or the unborn child [Danger Reproductive toxicity];H360FD (20%): May damage fertility; May damage the unborn child [Danger Reproductive toxicity];H361 (40%): Suspected of damaging fertility or the unborn child [Warning Reproductive toxicity];H361fd (20%): Suspected of damaging fertility; Suspected of damaging the unborn child [Warning Reproductive toxicity];H372 (20%): Causes damage to organs through prolonged or repeated exposure [Danger Specific target organ toxicity, repeated exposure];H373 (20%): May causes damage to organs through prolonged or repeated exposure [Warning Specific target organ toxicity, repeated exposure];H411 (20%): Toxic to aquatic life with long lasting effects [Hazardous to the aquatic environment, long-term hazard]
P203, P260, P261, P264, P264+P265, P270, P271, P273, P280, P301+P317, P302+P352, P304+P340, P305+P351+P338, P317, P318, P319, P321, P330, P332+P317, P337+P317, P362+P364, P391, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 5 reports by companies from 5 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.;Information may vary between notifications depending on impurities, additives, and other factors. The percentage value in parenthesis indicates the notified classification ratio from companies that provide hazard codes. Only hazard codes with percentage values above 10% are shown. For more detailed information, please visit ECHA C&L website.
Gefahrenhinweise
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl gemcitabine hydrochloride approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Gemcitabine hydrochloride/
Hazard Classes and CategoriesAcute Tox. 4 (20%);Acute Tox. 4 (40%);Skin Irrit. 2 (80%);Eye Irrit. 2 (80%);STOT SE 3 (20%);Muta. 1B (40%);Carc. 2 (20%);Repr. 1B (20%);Repr. 2 (40%);Repr. 2 (20%);STOT RE 1 (20%);STOT RE 2 (20%);Aquatic Chronic 2 (20%)
Shipment Methods and Regulations
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Methods for transporting hazardous drugs to the health-care setting should be consistent with environmental protection and national or local regulations for transporting hazardous substances. When hazardous drugs are being transported to the home-care setting, appropriate containers (eg, lined cardboard boxes) and procedures should be used to prevent breakage and contain leakage. ... The drugs must be securely capped or sealed and properly packaged and protected during transport to reduce further the chance of breakage and spillage in a public area such as a corridor or elevator. /Antineoplastic agents/
Sicherheit und Schutzausrüstung
Disposal Methods
SRP: At the time of review, criteria for land treatment or burial (sanitary landfill) disposal practices are subject to significant revision. Prior to implementing land disposal of waste residue (including waste sludge), consult with environmental regulatory agencies for guidance on acceptable disposal practices.
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ All contaminated disposables should be contained in sealable bags for transfer to larger waste containers. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ All bottles must be discarded as contaminated waste after decontamination of the biohazard cabinet. All protective apparel (gown, gloves, goggles, and respirator) should be discarded as contaminated waste. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ The contaminated filters must be removed, bagged in thick plastic and prepared for disposal in a hazardous waste dump site or incinerator licensed by the Environmental Protection Agency (EPA). /Antineoplastic agents/
For more Disposal Methods (Complete) data for GEMCITABINE (8 total), please visit the HSDB record page.
Preventive Measures
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Accidental contamination of the health-care environment, resulting in exposure of personnel, patients, visitors, and family members to hazardous substances, is prevented by maintaining the physical integrity and security of packages of hazardous drugs. 1. Access to all areas where hazardous drugs are stored is limited to specified authorized staff. 2. A method should be present for identifying to personnel those drugs that require special precautions (eg, cytotoxics). One way to accomplish this is to apply appropriate warning labels to all hazardous drug containers, shelves, and bins where the drug products are stored. ... 3. A method of identifying, for patients and family members, those drugs that require special precautions in the home should be in place. This may be accomplished in the health-care setting, by providing specific labeling for discharge medications, along with written instructions. 4. Methods for identifying shipping cartons of hazardous drugs should be required from manufacturers and distributors of these drugs. 5. Written procedures for handling damaged packages of hazardous drugs should be maintained. Personnel involved in shipping and receiving hazardous drugs should be trained in these procedures, including the proper use of protective garments and equipment. Damaged shipping cartons of hazardous drugs should be received and opened in an isolated area (eg, in a laboratory fume hood, if available, not in a vertical laminar airflow biological safety cabinet used for preparing sterile products). /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Facilities (eg, shelves, carts, counters, and trays) for storing hazardous drugs are designed to prevent breakage and to limit contamination in the event of leakage. Bins, shelves with barriers at the front, or other design features that reduce the chance of drug containers falling to the floor should be used. Hazardous drugs requiring refrigeration should be stored separately from nonhazardous drugs in individual bins designed to prevent breakage and to contain leakage. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Until the reproductive risks (or lack thereof) associated with handling hazardous drugs within a safety program have been substantiated, staff who are pregnant or breast-feeding should be allowed to avoid contact with these drugs. Policies should be in effect that provide these individuals with alternative tasks or responsibilities if they so desire. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ The pharmacy should provide access to information on toxicity, treatment of acute exposure (if available), chemical inactivators, solubility and stability of hazardous drugs (including investigational agents) used in the workplace. /Antineoplastic agents/
For more Preventive Measures (Complete) data for GEMCITABINE (20 total), please visit the HSDB record page.
Personal Protective Equipment (PPE)
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Protective apparel: Disposable closed-front gown or coveralls, disposable utility gloves over disposable latex gloves, NIOSH-approved air-purifying half-mask respirator equipped with a high efficiency filter, and eye protection should be worn. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Class 100 clean-air work stations, both horizontal and vertical airflow (with no containment characteristics), are inappropriate engineering controls for handling hazardous drugs because they provide no personnel protection and permit environmental contamination. Although there are no engineering controls designed specifically for the safe handling of hazardous chemicals as sterile products, Class II contained vertical-flow biological safety cabinets (biohazard cabinets) have been adopted for this use. Biohazard cabinetry is, however, designed for the handling of infectious agents, not hazardous chemicals. ... Based on design, ease of use, and cost considerations, Class II contained-vertical-flow biohazard cabinetry is currently recommended for use in preparing sterile doses of hazardous drugs. Class II cabinetry design and performance specifications are defined in NSF Standard 49. Biological safety cabinets selected for use with hazardous drugs should meet NSF Standard 49 specifications to ensure the maximum protection from these engineering controls. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Workers should wear powder free, disposable surgical latex gloves of good quality when preparing hazardous drugs. Selection criteria for gloves should include thickness (especially at the fingertips where stress is the greatest), fit, length, and tactile sensation. ... The practice of double gloving is supported by research that indicates that many glove materials vary in drug permeability even within lots; therefore, double gloving is recommended. ... In general, surgical latex gloves fit better, have appropriate elasticity for double gloving and maintaining the integrity of the glove-gown interface, and have sufficient tactile sensation (even during double gloving) for stringent aseptic procedures. ... Powdered gloves should be avoided. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ Workers who are not protected by the containment environment of a biohazard cabinet should use respiratory protection when handling hazardous drugs. Respiratory protection should be an adjunct to and not a substitute for engineering controls. Surgical masks of all types provide no respiratory protection against powdered or liquid aerosols of hazardous drugs. In situations where workers may be exposed to potential eye contact with hazardous drugs, an appropriate plastic face shield or splash goggles should be worn. /Antineoplastic agents/
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ During compounding of hazardous drugs (eg, crushing, dissolving, and preparing an ointment), workers should wear low permeability gowns and double gloves. Compounding should take place in a protective area such as a disposable glove box. If compounding must be done in the open, an area away from drafts and traffic must be selected, and the worker should use appropriate respiratory protection. /Antineoplastic agents/
Toxikologische Informationen
Interactions
... /The authors/ present the first case of a nonlung cancer patient experiencing not only acne-like skin toxicity, but subsequently also severe interstitial lung disease during therapy with gemcitabine and erlotinib. Both therapeutic agents were suspected as a possible cause of this adverse event. An interaction between gemcitabine and erlotinib might have also contributed to the pathogenesis of this pulmonary toxicity. Treatment with high-dose steroids was, however, very effective in our patient and a complete recovery appeared within a few days. Thus, pulmonary side effects should be regarded carefully in pancreatic cancer patients receiving palliative therapy with gemcitabine and erlotinib.
/The authors/ investigated the possible pharmacokinetic interactions of gemcitabine and oxaliplatin in patients with advanced solid tumors. Ten patients with advanced stage solid tumors were treated with gemcitabine (1500 mg/sq m) as a 30-min intravenous infusion on days 1 and 8, followed by oxaliplatin (130 mg/sq m) as a 4-hr intravenous infusion, on day 8 every 21 days. Pharmacokinetic data for 24 hr after dosing were obtained for both day 1 (gemcitabine without oxaliplatin coadministration) and day 8 (gemcitabine with oxaliplatin) during the first cycle of treatment. Gemcitabine levels in plasma were quantified using a reverse-phase high-performance liquid chromatography assay with ultraviolet detection, and total and ultrafiltrated platinum levels by flameless atomic absorption spectrophotometry with deuterium correction. All pharmacokinetic parameters of gemcitabine seemed to be unchanged when coadministered with oxaliplatin (day 8) compared with pharmacokinetic data of gemcitabine given as a single agent (day 1). The mean (maximum) concentration of gemcitabine on days 1 and 8 was 13.57 (+/-7.42) and 10.23 (+/-5.21) mg/L, respectively (P=0.28), and the mean half-life was 0.32 and 0.44 hr, respectively (P=0.40). Similarly, the P-values for AUC0-24 and the observed clearance were 0.61 and 0.30, respectively. Plasma total and free platinum levels were in agreement with other published data. Gemcitabine disposition appeared to be unaffected by oxaliplatin coadministration because no significant changes in pharmacokinetics between day 1 (gemcitabine without oxaliplatin coadministration) and day 8 (gemcitabine with oxaliplatin) were observed.
Hepatotoxicity
Elevations in serum aminotransferase levels occur in 30% to 90% of patients receiving cyclic therapy with gemcitabine. The elevations are generally mild-to-moderate, asymptomatic and self-limited, frequently resolving without discontinuation or even interruption of therapy. ALT or AST elevations above 5 times the upper limit of the normal range occur in 1-4% of patients yet rarely lead to symptoms or clinically apparent liver injury. Serum bilirubin and alkaline phosphatase elevations are less common, but also typically transient and mild. Despite wide use, gemcitabine has only rarely been implicated in rare cases of acute liver injury with jaundice, and most published cases have been reported in patients with underlying chronic liver disease or extensive hepatic metastases. The clinical features of hepatotoxicity from gemcitabine have not been well described. Most cases were marked by a progressive cholestasis and hepatic failure developing after several cycles of therapy in patients with preexisting chronic liver disease (hepatitis C, alcoholic liver disease) or significant hepatic metastases or local invasion.;As with many antineoplastic agents and regimens, therapy with gemcitabine has also been associated rare cases of with reactivation of hepatitis B in persons with preexisting HBsAg in serum. At least one case of sinusoidal obstruction syndrome (veno-occlusive disease) has been reported with use of gemcitabine in a patient with underlying chronic hepatitis C who received no other antineoplastic agent.;Likelihood score: C (probable rare cause of clinically apparent liver injury).
Milk ConcentrationsIt is not known wether gemcitabine or its metabolites are distributed into breast milk.
Medical Surveillance
/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ There is no method available for routine monitoring of personnel for evidence of hazardous drug exposure. Tests for the presence of mutagens or chromosomal damage are not drug specific and are of value only in controlled studies. Chemical analysis of urine for the presence of hazardous drugs at the sensitivity level needed to detect occupational exposure is limited to a few drugs and is not yet commercially available. /Antineoplastic agents/
Human Toxicity Excerpts
/CASE REPORTS/ ... Three patients presented to two major teaching hospitals with significant pulmonary dysfunction while receiving gemcitabine. Case data were obtained from patient records. A review of the literature was done to seek reports of pulmonary toxicity with gemcitabine and cytosine arabinoside (ara-C). The common features of the respiratory illnesses of the three patients in this study were tachypnea, marked hypoxemia, and an interstitial infiltrate on chest radiograph consistent with pulmonary edema. There was no evidence of underlying heart disease in any patient. In addition, there was no evidence of infection, metabolic causes, or lymphangitic carcinomatosis to explain the clinical findings. Two patients died, and postmortem examination confirmed acute RDS (respiratory distress syndrome), whereas in the third patient a transbronchial biopsy showed interstitial pneumonitis. These findings were consistent with drug-induced pulmonary toxicity. Diuretics and corticosteroids were useful measures for treating the patients' symptoms, and one patient survived after gemcitabine was withdrawn. These three cases of acute RDS may be the result of a capillary leak phenomenon due to treatment with gemcitabine, as observed in patients given intermediate dose and high dose ara-C, a drug similar in structure and metabolism to gemcitabine.
/CASE REPORTS/ /Investigators/ report the case of a 75-year-old man with stage IV non-small-cell lung carcinoma treated with combination of gemcitabine 1000 mg/sq m and cisplatin 75 mg/sq m repeated every 28 days, who developed bilateral cutaneous bullous lesions of lower limbs following gemcitabine administration. Histopathologic examination did not show any toxidermy aspect and there was not any sign of immunoglobulin deposit in direct immunofluorescence test. Chemotherapy was stopped and lesions disappeared without any treatment. Even delayed with regard to gemcitabine administration, the causal relationship of gemcitabine treatment with skin reaction is possible according to the Naranjo probability scale.
/CASE REPORTS/ A 43-year-old woman with postpartum cardiomyopathy and ischemic heart disease was treated with gemcitabine for metastatic nonsmall cell lung cancer. Three days after her 5th treatment with gemcitabine, she developed chest pain and was diagnosed as having acute, non-q-wave myocardial infarction. She made an uneventful recovery. An objective causality assessment revealed that the adverse event was possible. Gemcitabine has been previously reported to be causative of acute myocardial infarction. Ischemic complications of chemotherapeutic agents are discussed.
/CASE REPORTS/ /Investigators/ hereby report a case of radiation recall dermatitis and myositis occurring on gemcitabine monotherapy, five months after completing chemoradiation for locally advanced pancreatic cancer. Radiation recall resolved spontaneously with withdrawal of gemcitabine. This ... case report ... describes gemcitabine-induced radiation recall in rectus abdominus muscles after gemcitabine-based radiation therapy.
For more Human Toxicity Excerpts (Complete) data for GEMCITABINE (13 total), please visit the HSDB record page.
Drug Induced Liver Injury
Drug-Induced Liver Injury Severity and Toxicity (DILIst)
gemcitabine
DILI Positive
Intravenous
DOI:10.1016/j.drudis.2019.09.022
Non-Human Toxicity Excerpts
/GENOTOXICITY/ Gemcitabine was mutagenic in in vitro (mouse lymphoma assay) and in vivo (mouse micronucleus assay) mammalian test systems. However, it was not mutagenic in the Ames test, in vivo sister chromatid exchange, or in in vitro (chromosomal aberration assay and unscheduled DNA synthesis) test systems.
Populations at Special Risk
... Gemcitabine is characterized by a narrow therapeutic index, and its liver elimination depends upon a key enzymatic step, driven by cytidine deaminase (CDA). CDA is prone to gene polymorphism, including the 208A>G mutation, which can result in marked enzymatic deficiency with subsequent impact on drug exposure levels and related toxicities. We have developed a simple and inexpensive method to determine phenotypically CDA status in cancer patients, as an attempt to detect those at risk upon gemcitabine intake. Conjointly to genotypic investigations, this method was used to phenotype, in a retrospective setting, a female patient displaying extremely severe, and eventually lethal, toxicities after administration of a standard gemcitabine/carboplatin protocol. Phenotypic investigation showed a marked CDA deficiency (-75%) in this patient when compared with a reference, nontoxic population. Genetic studies undertaken next to screen mutations, possibly at the origin of this deficiency, showed heterozygosity for the 79A>C single-point mutation, whereas surprisingly the canonical CDA 208A>G polymorphism was not found. Taken together, this case report demonstrates, for the first time, that CDA downregulation can lead to toxic-death in patients exposed to gemcitabine. ...
Probable Routes of Human Exposure/PRECAUTIONS FOR ANTINEOPLASTIC AGENTS:/ ... exposure may be through inadvertent ingestion of the drug on foodstuffs (eg, workers' lunches), inhalation of drug dusts or droplets or direct skin contact. /Antineoplastic agents/
Environmental Water Concentrations
While data specific to gemcitabine were not located(SRC, 2007), the literature suggests that some pharmaceutically active compounds originating from human and veterinary therapy are not eliminated completely in municipal sewage treatment plants and are therefore discharged into receiving waters(1). Wastewater treatment processes often were not designed to remove them from the effluent(2). Selected organic waste compounds may be degrading to new and more persistent compounds that may be released instead of or in addition to the parent compound(2). Studies have indicated that several polar pharmaceutically active compounds can leach through soil(1).
Antidote and Emergency Treatment
Emergency and supportive measures. Maintain an open airway and assist ventilation if necessary. Treat coma, seizures, hypotensin, and arrhythmias if they occur. Treat nausea and vomiting with metoclopramide and fluid loss caused by gastroenteritis with intravenous crystalloid fluids. /Antineoplastic agents/
Bone marrow depression should be treated with the assistance of an experienced hematologist or oncologist. /Antineoplastic agents/
Decontamination. Administer activated charcoal orally if conditions are appropriate. Gastric lavage is not necessary after small to moderate ingestions if activated charcoal can be given promptly. /Antineoplastic agents/
Enhanced elimination. Because of the rapid intracellular incorporation of most of these agents, dialysis and other extracorporeal removal procedures are generally not effective. /Antineoplastic agents/
Effects During Pregnancy and Lactation
◉ Summary of Use during Lactation;Most sources consider breastfeeding to be contraindicated during maternal antineoplastic drug therapy. It might be possible to breastfeed safely during intermittent gemcitabine therapy with an appropriate period of breastfeeding abstinence; the manufacturer recommends an abstinence period of at least 1 week after the last dose. Chemotherapy may adversely affect the normal microbiome and chemical makeup of breastmilk. Women who receive chemotherapy during pregnancy are more likely to have difficulty nursing their infant.;◉ Effects in Breastfed Infants;Relevant published information was not found as of the revision date.;◉ Effects on Lactation and Breastmilk;A telephone follow-up study was conducted on 74 women who received cancer chemotherapy at one center during the second or third trimester of pregnancy to determine if they were successful at breastfeeding postpartum. Only 34% of the women were able to exclusively breastfeed their infants, and 66% of the women reported experiencing breastfeeding difficulties. This was in comparison to a 91% breastfeeding success rate in 22 other mothers diagnosed during pregnancy, but not treated with chemotherapy. Other statistically significant correlations included: 1. mothers with breastfeeding difficulties had an average of 5.5 cycles of chemotherapy compared with 3.8 cycles among mothers who had no difficulties; and 2. mothers with breastfeeding difficulties received their first cycle of chemotherapy on average 3.4 weeks earlier in pregnancy. Of the 9 women who received a fluorouracil-containing regimen, 8 had breastfeeding difficulties.
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl gemcitabine hydrochloride approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Gemcitabine hydrochloride/
Sicherheitsdaten
- hs_code
- 29349990
- risk_code
- 21-36/38-46-62-63
- Toxizität
- LD10 i.v. in rats: 200 mg/m2 (Abbruzzese)
- hazard_code
- Xn,Xi
- safety_code
- 25-26-36/37-53
- Giftige Stoffe Daten
- 95058-81-4(Hazardous Substances Data)
Chemie und Industrie
Pharmakologische Informationen
ATC Code
L01BC05
L01BC05
L - Antineoplastic and immunomodulating agents;L01 - Antineoplastic agents;L01B - Antimetabolites;L01BC - Pyrimidine analogues;L01BC05 - Gemcitabine
QL - Antineoplastic and immunomodulating agents;QL01 - Antineoplastic agents;QL01B - Antimetabolites;QL01BC - Pyrimidine analogues;QL01BC05 - Gemcitabine
L01BC05
Protein BindingGemcitabine plasma protein binding is less than 10%.
Pharmacodynamics
Gemcitabine is a nucleoside analog that mediates its antitumour effects by promoting apoptosis of malignant cells undergoing DNA synthesis. More specifically, it blocks the progression of cells through the G1/S-phase boundary. Gemcitabine demonstrated cytotoxic effects against a broad range of cancer cell lines _in vitro_. It displayed schedule-dependent antitumour activity in various animal models and xenografts from human non-small cell lung cancer (NSCLC) and pancreatic cancer. Therefore, the antineoplastic effects of gemcitabine are enhanced through prolonged infusion time rather than higher dosage. Gemcitabine inhibited the growth of human xenografts from carcinoma of the lung, pancreas, ovaries, head and neck, and breast. In mice, gemcitabine inhibited the growth of human tumour xenografts from the breast, colon, lung or pancreas by 69 to 99%. In clinical trials of advanced NSCLC, gemcitabine monotherapy produced objective response rates ranging from 18 to 26%, with a median duration of response ranging from 3.3 to 12.7 months. Overall median survival time was 6.2 to 12.3 months. The combined use of cisplatin and gemcitabine produced better objective response rates compared to monotherapy. In patients with advanced pancreatic cancer, objective response rates in patients ranged from 5.to 12%, with a median survival duration of 3.9 to 6.3 months. In Phase II trials involving patients with metastatic breast cancer, treatment with gemcitabine alone or with adjuvant chemotherapies resulted in response rate ranging from 13 to 42% and median survival duration ranging from 11.5 to 17.8 months. In metastatic bladder cancer, gemcitabine has a response rate 20 to 28%. In Phase II trials of advanced ovarian cancer, patients treated with gemcitabine had response rate of 57.1%, with progression free survival of 13.4 months and median survival of 24 months. Gemcitabine causes dose-limiting myelosuppression, such as anemia, leukopenia, neutropenia, and thrombocytopenia; howe
Mechanism of Action
Gemcitabine is a potent and specific deoxycytidine analog. After uptake into malignant cells, gemcitabine is phosphorylated by deoxycytidine kinase to form gemcitabine monophosphate, which is then converted to the active compounds, gemcitabine diphosphate (dFdCDP) and gemcitabine triphosphate (dFdCTP). These active metabolites are nucleosides that mediate antitumour effects. dFdCTP competes with deoxycytidine triphosphate (dCTP) for incorporation into DNA, thereby competitively inhibiting DNA chain elongation. The non-terminal position of dFdCTP in the DNA chain prevents detection of dFdCTP in the chain and repair by proof-reading 3′5′-exonuclease: this process is referred to as "masked DNA chain termination." Incorporation of dFdCTP into the DNA chain ultimately leads to chain termination, DNA fragmentation, and apoptotic cell death of malignant cells. Gemcitabine has self-potentiating pharmacological actions that can increase the probability of successful incorporation of gemcitabine triphosphate into the DNA chain: dFdCDP inhibits ribonucleotide reductase, an enzyme responsible for catalyzing the reactions that generate dCTP for DNA synthesis. Since dFdCDP reduces the levels of dCTP, there is less competition for gemcitabine triphosphate for incorporation into DNA. Gemcitabine can also reduce metabolism and elimination of active metabolites from the target ce1l, prolonging high intracellular concentrations of the active metabolites. Such self-potentiating effects are not present with [cytarabine].
Gemcitabine hydrochloride, a synthetic pyrimidine nucleoside, is an antineoplastic agent. The nucleoside analog consists of the pyrimidine base difluorocytidine, and the sugar moiety deoxyribose. Like most antimetabolite antineoplastic agents, gemcitabine is cell-cycle specific, acting principally in the S phase of the cell cycle; the drug also may cause cellular arrest at the G1-S border. The cytotoxic activity of gemcitabine (2'-deoxy-2',2'-difluorocytidine) depends on intracellular conversion to its 5'-diphosphate and -triphosphate metabolites; thus, deoxydifluorocytidine-5?-diphosphate (dFdCDP, gemcitabine diphosphate) and -triphosphate (dFdCTP, gemcitabine triphosphate) and not unchanged gemcitabine are the pharmacologically active forms of the drug. Gemcitabine is phosphorylated by deoxycytidine kinase to gemcitabine monophosphate, which subsequently is phosphorylated to the corresponding diphosphate and triphosphate nucleosides, presumably by deoxycytidylate kinase and nucleoside diphosphate kinase, respectively. The cytotoxic effect of gemcitabine is attributed to the combined actions of its diphosphate and triphosphate nucleosides, which lead to inhibition of DNA synthesis.
Gemcitabine diphosphate inhibits ribonucleotide reductase, which is responsible for catalyzing the formation of deoxynucleoside triphosphates needed in DNA synthesis. By inhibiting this reductase, gemcitabine diphosphate interferes with subsequent de novo nucleotide production. Gemcitabine triphosphate inhibits DNA synthesis by competing with the physiologic substrate, deoxycytidine triphosphate, for DNA polymerase and incorporation into DNA. The reduction in intracellular concentrations of deoxycytidine triphosphate induced by gemcitabine diphosphate actually enhances the incorporation of gemcitabine triphosphate into DNA, a mechanism referred to as ''self-potentiation.'' Following incorporation of gemcitabine triphosphate into the DNA chain, a single additional nucleotide, a normal base pair, is added and DNA synthesis is terminated, resulting in apoptosis (programmed cell death). DNA polymerase ? is unable to recognize the abnormal (gemcitabine) nucleotide and repair the DNA strand as a result of masking by the terminal normal base pair nucleotide (masked chain termination). This inability to recognize and excise the abnormal nucleotide results in a prolonged intracellular half-life of gemcitabine compared with other nucleoside analogs such as cytarabine and is thought to contribute to gemcitabine's expanded spectrum of antineoplastic activity relative to such agents. In CEM T lymphoblastoid cells, gemcitabine induces internucleosomal DNA fragmentation, which is characteristic of programmed cell death.
Biological Half-Life
Following intravenous infusions lasting less than 70 minutes, the terminal half-life ranged from 0.7 to 1.6 hours. Following infusions ranging from 70 to 285 minutes, the terminal half-life ranged from 4.1 to 10.6 hours. Females tend to have longer half-lives than male patients. Gemcitabine triphosphate, the active metabolite of gemcitabine, can accumulate in circulating peripheral blood mononuclear cells. The terminal half-life of gemcitabine triphosphate, the active metabolite, from mononuclear cells ranges from 1.7 to 19.4 hours.
The current study was performed in nonhuman primates to determine the plasma and CSF pharmacokinetics of gemcitabine and its inactive metabolite, difluorodeoxyuridine (dFdU) following iv administration. Gemcitabine, 200 mg/kg, was administered iv over 45 min to four nonhuman primates. Serial plasma and CSF samples were obtained prior to, during, and after completion of the infusion for determination of gemcitabine and dFdU concentrations. ... Plasma elimination was rapid with a mean t1/2 of 8 +/- 4 min (mean +/- SD) for gemcitabine and 83 +/- 8 min for dFdU. Gemcitabine total body clearance (ClTB) was 177 +/- 40 mL/min per kg and the Vdss was 5.5 +/- 1.0 L/kg. The maximum concentrations (Cmax) and areas under the time concentration curves (AUC) for gemcitabine and dFdU in plasma were 194 +/- 64 uM and 63.8 +/- 14.6 uM.hr, and 783 +/- 99 uM and 1725 +/- 186 uM.hr, respectively. The peak CSF concentrations of gemcitabine and dFdU were 2.5 +/- 1.4 uM and 32 +/- 41 uM, respectively. The mean CSF:plasma ratio was 6.7% for gemcitabine and 23.8% for dFdU. There is only modest penetration of gemcitabine into the CSF after iv administration.
In this study, the plasma pharmacokinetics (PKs) of gemcitabine and dFdU are further explored after gemcitabine doses of 10, 30, and 60 mg/kg administered by intravenous infusion with a loading dose /to dogs/. Gemcitabine displayed linear PKs, while the kinetics of 2',2'-difluorodeoxyuridine (dFdU) were not dose proportional. The overall clearance, volume of distribution at steady-state, and terminal elimination half-life (t(1/2)) for gemcitabine were 0.421 L/hr.kg, 0.822 L/kg, and 1.49 hr, respectively. Plasma concentrations of dFdU peaked at approximately 2 hr postdosing and had a t(1/2) of 14.9 hr.
Metabolism/Metabolites
Following administration and uptake into cancer cells, gemcitabine is initially phosphorylated by deoxycytidine kinase (dCK), and to a lower extent, the extra-mitochondrial thymidine kinase 2 to form gemcitabine monophosphate (dFdCMP). dFdCMP is subsequently phosphorylated by nucleoside kinases to form active metabolites, gemcitabine diphosphate (dFdCDP) and gemcitabine triphosphate (dFdCTP). Gemcitabine is also deaminated intracellularly and extracellularly by cytidine deaminase to its inactive metabolite 2′,2′-difluorodeoxyuridine or 2´-deoxy-2´,2´-difluorouridine (dFdU). Deamination occurs in the blood, liver, kidneys, and other tissues, and this metabolic pathway accounts for most of drug clearance.
Gemcitabine undergoes intracellular metabolism, via nucleoside kinases, to produce two active metabolites (gemcitabine diphosphate and gemcitabine triphosphate) and also undergoes deamination to an active uracil metabolite.
... After intravenous injection, gemcitabine is rapidly converted to the inactive metabolite 2'-deoxy-2',2'-difluorouridine by cytidine deaminase. ...
FDA Pharmacological Classification
B76N6SBZ8R
GEMCITABINE
Mechanisms of Action [MoA] - Nucleic Acid Synthesis Inhibitors
Established Pharmacologic Class [EPC] - Nucleoside Metabolic Inhibitor
Gemcitabine is a Nucleoside Metabolic Inhibitor. The mechanism of action of gemcitabine is as a Nucleic Acid Synthesis Inhibitor.
GEMCITABINE
MeSH Pharmacological ClassificationAntimetabolites that are useful in cancer chemotherapy.
Absorption, Distribution and Excretion
Peak plasma concentrations of gemcitabine range from 10 to 40 mg/L following a 30-minute intravenous infusion, and are reached at 15 to 30 minutes. One study showed that steady-state concentrations of gemcitabine showed a linear relationship to dose over the dose range 53 to 1000 mg/m2. Gemcitabine triphosphate, the active metabolite of gemcitabine, can accumulate in circulating peripheral blood mononuclear cells. In one study, the Cmax of gemcitabine triphosphate in peripheral blood mononuclear cells occurred within 30 minutes of the end of the infusion period and increased increased proportionally with gemcitabine doses of up to 350 mg/m2.
Gemcitabine mainly undergoes renal excretion. Within a week following administration of a single dose of 1000 mg/m<sup>2</sup> infused over 30 minutes, about 92-98% of the dose was recovered in urine where 89% of the recovered dose was excreted as difluorodeoxyuridine (dFdU) and less than 10% as gemcitabine. Monophosphate, diphosphate, or triphosphate metabolites of gemcitabine are not detectable in urine. In a single-dose study, about 1% of the administered dose was recovered in the feces.
In patients with various solid tumours, the volume of distribution increased with infusion length. The volume of distribution of gemcitabine was 50 L/m<sup>2</sup> following infusions lasting less than 70 minutes. For long infusions, the volume of distribution rose to 370 L/m<sup>2</sup>. Gemcitabine triphosphate, the active metabolite of gemcitabine, accumulates and retains in solid tumour cells _in vitro_ and _in vivo_. It is not extensively distributed to tissues after short infusions that last less than 70 minutes. It is not known whether gemcitabine crosses the blood-brain barrier, but gemcitabine is widely distributed into tissues, including ascitic fluid. In rats, placental and lacteal transfer occurred rapidly at five to 15 minutes following drug administration.
Following intravenous infusions lasting less than 70 minutes, clearance ranged from 41 to 92 L/h/m<sup>2</sup> in males and ranged from 31 to 69 L/h/m<sup>2</sup> in females. Clearance decreases with age. Females have about 30% lower clearance than male patients.
Gemcitabine pharmacokinetics are linear and are described by a 2-compartment model. Population pharmacokinetic analyses of combined single and multiple dose studies showed that the volume of distribution of gemcitabine was significantly influenced by duration of infusion and gender. Clearance was affected by age and gender. Differences in either clearance or volume of distribution based on patient characteristics or the duration of infusion result in changes in half-life and plasma concentrations.
Protein binding /of gemcitabine/ is very low, less than 10%.
Cellular LocationsCytoplasm;Membrane
Metabolite PathwaysGemcitabine Action Pathway;Gemcitabine Metabolism Pathway
Verwendung und Herstellung
Uses
For use in combination with cisplatin for the first-line treatment of patients with inoperable, locally advanced (Stage IIIA or IIIB) or metastatic (Stage IV) non-small cell lung cancer.
... In the treatment of ovarian cancer /Hydrochloride/
THERAP CAT: Antineoplastic.
Use (kg) in Switzerland (2009): >25;Use (kg; approx.) in Germany (2009): >250;Use (kg; exact) in Germany (2009): 360;Use (kg) in USA (2002): 273;Consumption (g per capita) in Switzerland (2009): 0.0032;Consumption (g per capita; approx.) in Germany (2009): 0.0031;Consumption (g per capita; exact) in Germany (2009): 0.0044;Consumption (g per capita) in the USA (2002): 0.00097;Excretion rate: 0.05;Calculated removal (%): 22
Impurities4-aminopyrimidin-2(1H)-one; 4-amino-1-(2-deoxy-2,2-difluoro-alpha-D-erythro-pentofuranosyl)pyrimidin-2(1h)-one
Methods of Manufacturing
Preparation: L.W. Hertel, GB 2136425; idem, US 4808614 (1984, 1989 both to Lilly)
The acetonide of 2,3-dihydroxypropanal (chiron- from mannitol) undergoes a Reformatsky reaction with ethyl 2,2-dibromo-2-fluoroacetate to yield the classic alcohol product, which is then benzylated to protect the generated OH group. Treatment with acid removes the acetonide group and the resulting diol forms a lactone with the gamma-OH function. The free OH is benzylated (protection) and the lactone carbonyl reduced to form a mixture of isomers of 3,3-difluoro-4,5-di(benzyloxy)-2-furanol and the free OH is converted to a mesyl ester (I) with methanesulfonyl chloride and base. Cysteine is reacted with trimethylsilyl chloride to silylate the hydroxyl and amino groups (II). Compound I reacts with II, accompanied by loss of the mesyl group and, after removal of the benzyloxy groups with ammonia, yields the title compound.
Formulations/PreparationsParenteral gemcitabine for injection, for IV infusion: 200 mg (of gemcitabine) Gemzar (with mannitol), Lilly. One g (of gemcitabine) Gemzar (with mannitol), Lilly.
Use ClassificationPharmaceuticals -> Antineoplastic and immunomodulating agents -> Antineoplastic agents -> Antimetabolites -> Pyrimidine analogues -> Cytostatics
Anwendungen
BeschreibungGemcitabine is an anticancer nucleoside analog that inhibits the growth of HL-60 promyelocytic leukemia cells with an LC50 value of 40 nM. It inhibits the growth of MX-1 mammary, CX-1, HC-1, GC3, and VRC5 colon, LX-1, Calu-6, and NCI-H460 lung, and HS766T, PaCa-2, PANC-1, and BxPC-3 pancreatic cancer tumors in mouse xenograft models (45-93% inhibition). Gemcitabine is a prodrug that is metabolized to a diphosphate and triphosphate form in cells. The triphosphate form is incorporated into DNA which induces masked chain termination and cell death. By specifically inhibiting growth arrest and DNA damage inducible protein 45 a (Gadd45a), a key mediator of active DNA demethylation, gemcitabine, at concentrations ranging from 34 to 134 nM, inhibits repair-mediated DNA demethylation in a methylation-sensitive reporter assay. Gemcitabine also has broad antiretroviral activity, decreasing MuLV cell infectivity, a murine AIDS model, in cell culture (EC50 = ~1.5 nM) and inhibits the progression of murine AIDS in vivo at a dose of 1-2 mg/kg per day.
VerwendenGemcitabine(Gemzar) belongs to the group of medicines called antimetabolites. It is used alone or in combination with other medicines to treat cancer of the breast, ovary, pancreas, and lung. Gemcitabine interferes with the growth of cancer cells, which a
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Nachgelagerte Produkte
Anbieter50 Anbieter
北京华美互利生物化工010-56205725 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
INTATRADE GmbH+49 3493/605464 · [email protected]
上海如吉生物科技发展有限公司+86-21-65211385-8001 36031160 · [email protected]
韶远科技(上海)有限公司021-50795510 4000665055 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
上海波以尔化工有限公司[email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
南京仕浪药业有限公司86-25-87797880,81,82 -809 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
上海相辉医药科技有限公司13761987713 · [email protected]
常州希辰曦生物科技有限公司13000000000 · [email protected]
上海景颜化工科技有限公司13817811078 · [email protected]
嘉兴市艾森化工有限公司0573-85285100 18627885956 · [email protected]
上海泰坦科技股份有限公司400-6009262 15618770481 · [email protected]
武汉威顺达科技发展有限公司86-027-88774375 · [email protected]
上海隆盛化工有限公司58099637 13585536065 · [email protected]
凯试(上海)科技有限公司021-50135380 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
上海攀鸿化工科技有限公司021-56491756 13512199871 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
湖南汇百侍生物科技有限公司0731-85526065 13308475853 · [email protected]
同创医药(苏州)有限公司0512-63263366 18912765016 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
Wuhan NCE Biomedical Co.,Ltd.4000-027-021 |24 +86-13986109188 | +86-15623472865 | +81-08033611988
上海遐瑞医药科技有限公司+86 21 61551611
上海健超生物科技有限公司150-2103-5486 18017383231 · [email protected]
上海赢瑞生物医药科技有限公司21-33585366 13311639313 · [email protected]
TCI AMERICA800-4238616 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
TCI Europe320-37350700 · [email protected]
越林试剂021-62960152 · [email protected]
上海睿升化工科技有限公司+86-021-50935922
南京杜莱生物技术有限公司025-84699383-8003;025-846993838003-8003 18013301590 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
上海汇凯化学科技有限公司021-61995394 18916691159 · [email protected]
上海倍卓生物科技有限公司021-61119791,13386096464 · [email protected]
北京环宇世纪化学科技有限公司hysj_bj.com
上海喀露蓝科技有限公司18149758185 18149758185 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
上海笛柏生物科技有限公司400-008-9730,021-54359730 400-008-9730 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
成都零六生物科技有限公司400-1166-196 13458535857 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
Zugehörige Reaktionen
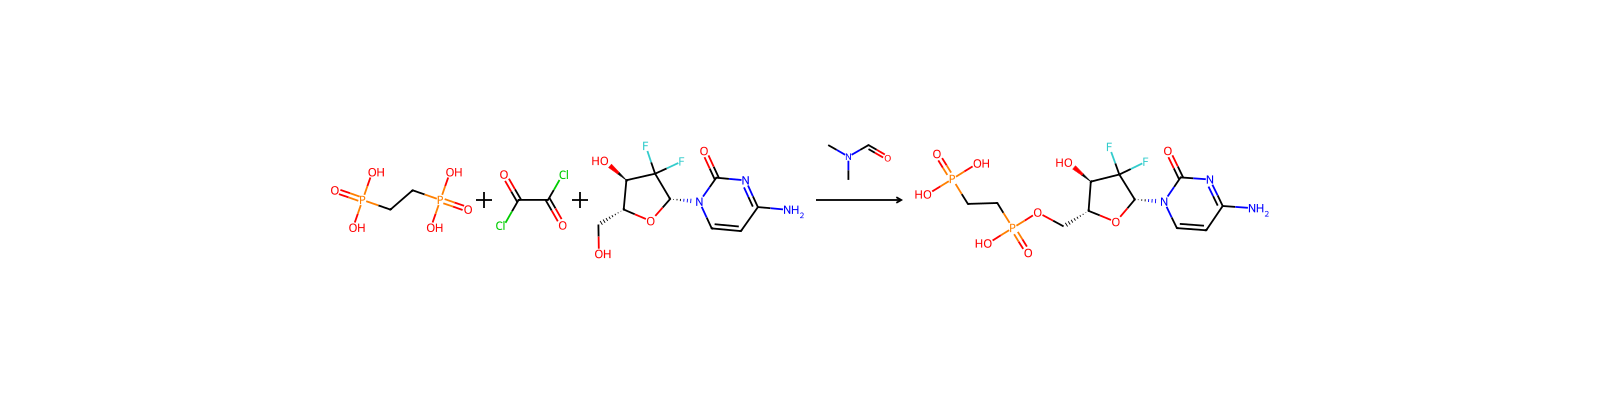
10



Verknüpfte Notizen
Wird geladen…