Daten werden ergänzt – lade die Seite später neu, um den aktuellen Stand zu sehen
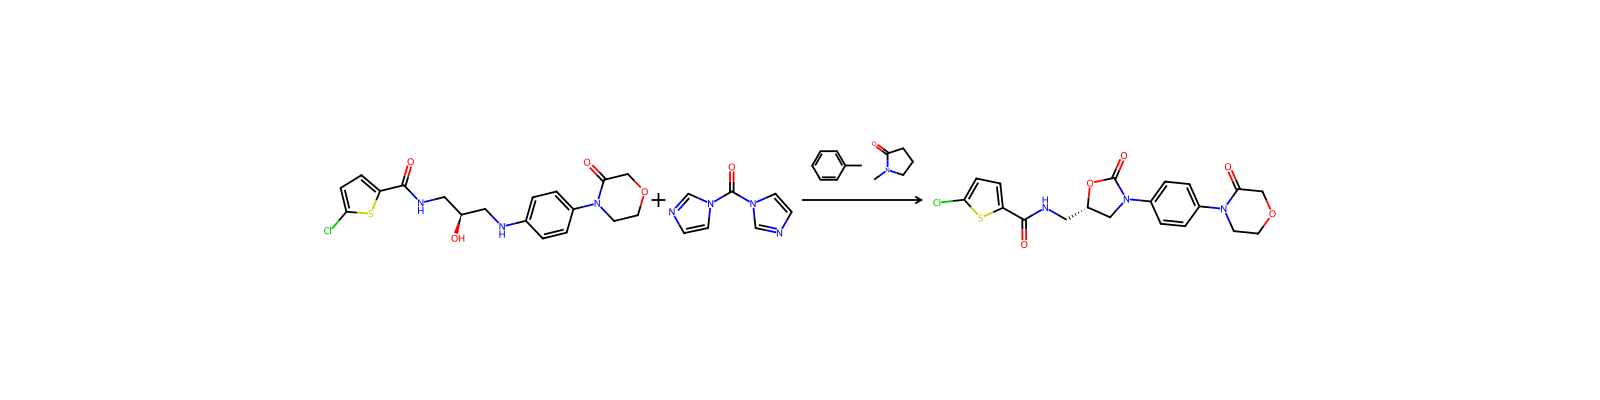
366789-02-8O=C(NC[C@H]1CN(c2ccc(N3CCOCC3=O)cc2)C(=O)O1)c1ccc(Cl)s1KGFYHTZWPPHNLQ-AWEZNQCLSA-NRivaroxaban is a monocarboxylic acid amide obtained by formal condensation of the carboxy group of 5-chlorothiophene-2-carboxylic acid with the amino group of 4-{4-[(5S)-5-(aminomethyl)-2-oxo-1,3-oxazolidin-3-yl]phenyl}morpholin-3-one. An anticoagulant used for prophylaxis of venous thromboembolism in patients with knee or hip replacement surgery. It has a role as an anticoagulant and an EC 3.4.21.6 (coagulation factor Xa) inhibitor. It is a lactam, a member of thiophenes, a monocarboxylic acid amide, an organochlorine compound, a member of morpholines, an oxazolidinone and an aromatic amide.
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Used in Switzerland
Breast Feeding; Lactation; Milk, Human; Anticoagulants; Antithrombins
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
Sicherheitsangaben dienen nur zur Orientierung und ersetzen weder das Sicherheitsdatenblatt (SDB) des Lieferanten noch geltende Vorschriften oder eine fachliche Bewertung.
This chemical does not meet GHS hazard criteria for 1.2% (1 of 85) of reports.
H411 (89.4%): Toxic to aquatic life with long lasting effects [Hazardous to the aquatic environment, long-term hazard]
P273, P391, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 85 reports by companies from 17 notifications to the ECHA C&L Inventory.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including rivaroxaban, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
B - Blood and blood forming organs
QB - Blood and blood forming organs
Rivaroxaban is an anticoagulant which binds directly to factor Xa. Thereafter, it effectively blocks the amplification of the coagulation cascade, preventing the formation of thrombus. Rivaroxaban is a unqiue anticoagulant for two reasons. First of all, it is does not involve antithrombin III (ATIII) to exert its anticoagulant effects. Secondly, it is an oral agent whereas the widely used unfractionated heparin and low molecular weight heparins are for parenteral use only. Although the activated partial thromboplastin time (aPTT) and HepTest (a test developed to assay low molecular weight heparins) are prolonged in a dose-dependant manner, neither test is recommended for the assessment of the pharmacodynamic effects of rivaroxaban. Anti-Xa activity and inhibition of anti-Xa activity monitoring is also not recommended despite being influenced by rivaroxaban.
Rivaroxaban competitively inhibits free and clot bound factor Xa. Factor Xa is needed to activate prothrombin (factor II) to thrombin (factor IIa). Thrombin is a serine protease that is required to activate fibrinogen to fibrin, which is the loose meshwork that completes the clotting process. Since one molecule of factor Xa can generate more than 1000 molecules of thrombin, selective inhibitors of factor Xa are profoundly useful in terminating the amplification of thrombin generation. The action of rivaroxaban is irreversible.
Rivaroxaban, an oral, direct activated factor X (Xa) inhibitor, is an anticoagulant. Factor Xa plays a central role in the blood coagulation cascade by serving as the convergence point for the intrinsic and extrinsic pathways; inhibition of coagulation factor Xa by rivaroxaban prevents conversion of prothrombin to thrombin and subsequent thrombus formation. Rivaroxaban inhibits both free and prothrombinase-bound factor Xa. Unlike fondaparinux, heparin, and the low molecular weight heparins, rivaroxaban binds directly to the active site of factor Xa without the need for a cofactor (e.g., antithrombin III). Rivaroxaban inhibits factor Xa with more than 100,000-fold greater selectivity than other biologically important serine proteases (e.g., thrombin, trypsin, plasmin, factor VIIa, factor IXa, urokinase, activated protein C).
Wird geladen…
366789-02-8DTXSID3057723CHEMBL198362CHEBI:68579Accidental release measures. After Inhalation: cordon off area of spill; wear self-contained breathing apparatus, protective clothing and heavy rubber gloves. Measures for cleaning/collecting: absorb solutions with finely- powdered liquid-binding material (diatomite, universal binders); decontaminate surfaces and equipment by scrubbing with alcohol; dispose of contaminated material.
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
SRP: At the time of review, regulatory criteria for small quantity disposal are subject to significant revision, however, household quantities of waste pharmaceuticals may be managed as follows: Mix with wet cat litter or coffee grounds, double bag in plastic, discard in trash.
Patients with renal impairment receiving full dose Xarelto in combination with drugs classified as combined P-gp and weak or moderate CYP3A4 inhibitors (e.g., amiodarone, diltiazem, verapamil, quinidine, ranolazine, dronedarone, felodipine, erythromycin, and azithromycin) may have increases in exposure compared with patients with normal renal function and no inhibitor use, since both pathways of rivaroxaban elimination are affected. Xarelto should be used in patients with CrCl 15 to 50 mL/min who are receiving concomitant combined P-gp and weak or moderate CYP3A4 inhibitors only if the potential benefit justifies the potential risk.
Single doses of enoxaparin and Xarelto given concomitantly resulted in an additive effect on anti-factor Xa activity. Single doses of warfarin and Xarelto resulted in an additive effect on factor Xa inhibition and PT. Concomitant aspirin use has been identified as an independent risk factor for major bleeding in efficacy trials. NSAIDs are known to increase bleeding, and bleeding risk may be increased when NSAIDs are used concomitantly with Xarelto. Coadministration of the platelet aggregation inhibitor clopidogrel and Xarelto resulted in an increase in bleeding time for some subjects. Avoid concurrent use of Xarelto with other anticoagulants due to increased bleeding risk unless benefit outweighs risk. Promptly evaluate any signs or symptoms of blood loss if patients are treated concomitantly with aspirin, other platelet aggregation inhibitors, or NSAIDs.
Results from drug interaction studies and population PK analyses from clinical studies indicate coadministration of Xarelto with a combined P-gp and strong CYP3A4 inducer (e.g., rifampicin, phenytoin) decreased rivaroxaban exposure by up to 50%. Similar decreases in pharmacodynamic effects were also observed. These decreases in exposure to rivaroxaban may decrease efficacy. Avoid concomitant use of Xarelto with drugs that are combined P-gp and strong CYP3A4 inducers (e.g., carbamazepine, phenytoin, rifampin, St. John's wort).
When data suggest a change in exposure is unlikely to affect bleeding risk (e.g., clarithromycin, erythromycin), no precautions are necessary during coadministration with drugs that are combined P-gp and CYP3A4 inhibitors. Avoid concomitant administration of Xarelto with combined P-gp and strong CYP3A4 inhibitors.
For more Interactions (Complete) data for Rivaroxaban (10 total), please visit the HSDB record page.
Chronic therapy with rivaroxaban is associated with moderate ALT elevations (greater than 3 times the upper limit of normal) in 1.5% to 3% of patients, an overall rate which is slightly lower than with low molecular weight heparins and similar to the rates with warfarin. During the large, prelicensure clinical trials of rivaroxaban, several instances of ALT elevations with jaundice occurred, but few details were provided and it was not clear whether the liver injury was clinically apparent. The cases were evidently mild and self-limited, resolving completely once therapy was stopped. Since its licensure and more wide scale use, rivaroxaban has been linked to many instances of acute liver injury with jaundice. The clinical features of these cases varied widely. Most cases had an onset within 1 to 8 weeks of starting rivaroxaban and presented with jaundice, fatigue and a hepatocellular pattern of serum enzyme elevations. In some individuals, a cholestatic or mixed pattern was found. Immunoallergic features and autoimmune markers were atypical but at least one case occurred with skin rash and fever suggestive of DRESS syndrome. One case of acute hepatic necrosis and death attributed to rivaroxaban has been reported, but ischemic hepatitis due to severe heart failure was a more likely cause of the acute liver failure. All other reported cases of rivaroxaban induced liver injury recovered upon stopping rivaroxaban, usually quite promptly, within 2 to 4 weeks. In large health care databases, hospitalization for acute liver injury arises in approximately 1 in 2,200 cases, but whether all cases in these databases represent liver injury from rivaroxaban is uncertain.
Patients with minor bleeding are managed conservatively, and a single dose of anticoagulation is skipped or delayed. Patients with major bleeding receive initial management with antifibrinolytic agents such as tranexamic acid or epsilon-aminocaproic acid, which are used off-label as hemostatic agents in major NOAC-associated bleeds; however, there is currently insufficient data on their efficacy. For patients with life-threatening bleeding associated with direct factor Xa inhibitor anticoagulation, unactivated 4-factor PCC can be used.
/CASE REPORTS/ A 61-year-old female patient who developed a spontaneous spinal epidural hematoma (SSEH) after being treated by rivaroxaban, a new agent for the prevention of venous thromboembolic events in orthopedic surgery /is reported/. Although the pathogenesis of SSEH is unclear, anticoagulant therapy is a known risk factor. The patient sustained a sudden onset of severe back pain in the thoracic spine, followed by paraplegia below T8, 2 days after proximal tibial osteotomy and rivaroxaban therapy. Magnetic resonance imaging (MRI) of the whole spine demonstrated a ventral SSEH from C2 to T8. Whilst preparing for the emergency evacuation of the SSEH, the neurological symptoms recovered spontaneously 4 hr after onset without surgery. After monitored bed rest for 48 hr the MRI was repeated and the SSEH was no longer present. This rare condition of spinal cord compression and unusually rapid spontaneous recovery has not previously been reported following rivaroxaban therapy.
/CASE REPORTS/ Managing patients with new oral anticoagulants in perioperative period is not yet well protocolized. ... A clinical case of a critical hematuria after prostate biopsies to a patient treated with RIivaroxaban /is reported/. Monitoring and treatment of the hematuria have been difficult due to the lack of biological control and antidote for this treatment.
/ALTERNATIVE and IN VITRO TESTS/ Blood from patients with known coronary artery disease who were treated with aspirin but no other antithrombotic agent was spiked in vitro with rivaroxaban alone or in combination with a direct acting P2Y12 antagonist (cangrelor). To limit cofounding effects of anticoagulants and to enable interaction between coagulation factors, blood was anticoagulated only with a specific inhibitor of Factor XIIa, corn trypsin inhibitor. Polymerization of fibrin was prevented with the peptide GPRP. Activation of platelets was determined with the use of flow cytometry in response to lipidated tissue factor, thrombin, the collagen mimetic convulxin, and adenosine diphosphate (ADP). Rivaroxaban inhibited the activation of platelets induced by tissue factor and to a lesser extent activation induced by thrombin, effects that were accentuated when combined with cangrelor. Rivaroxaban did not attenuate convulxin-induced activation of platelets; however, a limited but consistent attenuation of ADP-induced platelet activation was seen with blood anticoagulated with rivaroxaban. Effects of rivaroxaban on ADP-induced platelet activation were not mediated by thrombin, tissue factor, or platelet-leukocyte aggregation. In conclusion, rivaroxaban attenuated in vitro the activation of platelets mediated by thrombin. In light of the pivotal role of thrombin in platelet activation after rupture of an atherosclerotic plaque, rivaroxaban should attenuate platelet activation in vivo, an effect that is accentuated by combination with a P2Y12 antagonist.
/ALTERNATIVE and IN VITRO TESTS/ ... This study investigated the direct effects of rivaroxaban on bone biology using an in vitro cell culture model from the human female osteoblastic cell line SaOS2. Cells at subconfluence were treated for 24 hr with different concentrations of rivaroxaban and analyzed for DNA synthesis and creatine kinase- and alkaline phosphatase-specific activities, and were treated 21 days for analyzing mineralization. Rivaroxaban (0.01-50 ug/mL) dose-dependently inhibited up to 60% DNA synthesis of the cells. Creatine kinase-specific activity was also inhibited dose-dependently to a similar extent by the same concentrations. Alkaline phosphatase-specific activity was dose-dependently inhibited but only up to 30%. Cell mineralization was unaffected by 10 ug/mL rivaroxaban. This model demonstrated a significant rivaroxaban-induced reduction in osteoblastic cell growth and energy metabolism, and slight inhibition of the osteoblastic marker, alkaline phosphatase, while osteoblastic mineralization was unaffected. These findings might indicate that rivaroxaban inhibits the first stage of bone formation but does not affect later stages (i.e., bone mineralization).
Drug Induced Liver Injury Rank (DILIrank 2.0)
Rivaroxaban
vLess-DILI-concern
5
Adverse reactions
DOI:10.1016/j.drudis.2016.02.015
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ Rivaroxaban was not carcinogenic when administered by oral gavage to mice or rats for up to 2 years. The systemic exposures (AUCs) of unbound rivaroxaban in male and female mice at the highest dose tested (60 mg/kg/day) were 1- and 2-times, respectively, the human exposure of unbound drug at the human dose of 20 mg/day. Systemic exposures of unbound drug in male and female rats at the highest dose tested (60 mg/kg/day) were 2- and 4-times, respectively, the human exposure.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ Animal reproduction studies have shown pronounced maternal hemorrhagic complications in rats and an increased incidence of post-implantation pregnancy loss in rabbits. Rivaroxaban increased fetal toxicity (increased resorptions, decreased number of live fetuses, and decreased fetal body weight) when pregnant rabbits were given oral doses of > or = 10 mg/kg rivaroxaban during the period of organogenesis. This dose corresponds to about 4 times the human exposure of unbound drug, based on AUC comparisons at the highest recommended human dose of 20 mg/day. Fetal body weights decreased when pregnant rats were given oral doses of 120 mg/kg. This dose corresponds to about 14 times the human exposure of unbound drug.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ No impairment of fertility was observed in male or female rats when given up to 200 mg/kg/day of rivaroxaban orally. This dose resulted in exposure levels, based on the unbound AUC, at least 13 times the exposure in humans given 20 mg rivaroxaban daily.
/GENOTOXICITY/ Rivaroxaban was not mutagenic in bacteria (Ames-Test) or clastogenic in V79 Chinese hamster lung cells in vitro or in the mouse micronucleus test in vivo.
/OTHER TOXICITY INFORMATION/ Rivaroxaban is a novel factor 10a inhibitor, where hepatic metabolism and renal clearance account for its overall disposition. Renal impairment is known to increase rivaroxaban-associated bleeding risk in patients. As renal rivaroxaban clearance exceeds glomerular filtration rate, we suggested that active secretion by efflux transporters P-glycoprotein (MDR1) and breast cancer resistance protein (BCRP) contributes to rivaroxaban clearance. The ability of MDR1 and BCRP efflux transporters to mediate rivaroxaban transport in vitro was assessed in polarized cell monolayers. A significantly greater vectorial transport of rivaroxaban was observed in the basal to apical direction in Caco-2 cells, which was attenuated in the presence of the selective inhibitors. After oral administration of rivaroxaban (2 mg/kg), plasma concentrations did not significantly differ between wild-type and Mdr1a(def) or Bcrp(-/-) mice (n = 6 per group). However, rivaroxaban clearance was significantly reduced in Mdr1a/Mdr1b(-/-)/Bcrp(-/-) mice. Interestingly, rivaroxaban brain-to-plasma ratio did not differ in mice lacking only Mdr1a or Bcrp, but more than two times higher in the Mdr1a/Mdr1b(-/-)/Bcrp(-/-) mice. Rivaroxaban is a shared substrate of MDR1 and BCRP. In vivo, MDR and BCRP function synergistically to modulate rivaroxaban disposition and appear to be particularly relevant to limiting its central nervous system entry. These data have important implications for safety and efficacy of anticoagulation therapy with rivaroxaban as many drugs in clinical use are known MDR1 inhibitors and loss-of-function polymorphisms in BCRP are common.
The drug should not be used in patients with a creatinine clearance of less than 15 mL/minute.1 Renal function should be periodically assessed as clinically indicated (i.e., more frequently in situations where renal function may decline) and therapy adjusted accordingly. Rivaroxaban should be discontinued if acute renal failure develops.
Use of rivaroxaban should be avoided in patients with moderate (Child-Pugh class B) or severe (Child-Pugh class C) hepatic impairment or with any hepatic disease associated with coagulopathy; systemic exposure and risk of bleeding may be increased in such patients.
EXPERIMENTAL: Rivaroxaban is an oral, direct factor Xa inhibitor for the management of thromboembolic disorders. Despite its short half-life, the ability to reverse rivaroxaban anticoagulation could be beneficial in life-threatening emergencies. The potential of prothrombin complex concentrate (PCC; Beriplex), activated PCC (aPCC; FEIBA) or recombinant activated factor VII (rFVIIa; NovoSeven) to reverse rivaroxaban in rats and baboons was investigated. Anaesthetised rats pre-treated with intravenous rivaroxaban (2 mg/kg) received intravenous rFVIIa (100/400 ug/kg), PCC (25/50 U/kg) or aPCC (50/100 U/kg) after initiation of bleeding. Clotting times and bleeding times (BTs) were recorded. Rivaroxaban was administered as an intravenous 0.6 mg/kg bolus followed by continuous 0.6 mg/kg/hour infusion in baboons. Animals received intravenous aPCC 50 U/kg (2 U/kg/minute) or rFVIIa 210 ug/kg. BT and clotting parameters were measured. In rats pretreated with high-dose rivaroxaban, PCC 50 U/kg, aPCC 100 U/kg and rFVIIa 400 ug/kg significantly reduced BT vs rivaroxaban alone (5.4 + or- 1.4-fold to 1.5 + or- 0.4-fold [p<0.05]; 3.0+ or- 0.4-fold to 1.4 + or- 0.1-fold [p<0.001]; and 3.5 + or- 0.7-fold to 1.7 + or- 0.2-fold [p<0.01] vs baseline, respectively). In baboons pre-infused with rivaroxaban and then given aPCC, BT increased by 2.0 + or- 0.2-fold and aPCC returned BT to baseline for the duration of its infusion. rFVIIa reduced BT from 2.5 + or- 0.3-fold over baseline to 1.7 + or- 0.3-fold over baseline. Prolongation of prothrombin time was reduced by PCC, aPCC and rFVIIa in both species. Rivaroxaban reduced thrombin-antithrombin levels; application of PCC and aPCC, but not rFVIIa, increased these levels. In conclusion, PCC, aPCC or rFVIIa have the potential to reverse the anticoagulant and anti-haemostatic effects of rivaroxaban.
Overdose of Xarelto may lead to hemorrhage. Discontinue Xarelto and initiate appropriate therapy if bleeding complications associated with overdosage occur. A specific antidote for rivaroxaban is not available. Rivaroxaban systemic exposure is not further increased at single doses >50 mg due to limited absorption. The use of activated charcoal to reduce absorption in case of Xarelto overdose may be considered. Due to the high plasma protein binding, rivaroxaban is not expected to be dialyzable.
/SRP:/ Immediate first aid: Ensure that adequate decontamination has been carried out. If patient is not breathing, start artificial respiration, preferably with a demand valve resuscitator, bag-valve-mask device, or pocket mask, as trained. Perform CPR if necessary. Immediately flush contaminated eyes with gently flowing water. Do not induce vomiting. If vomiting occurs, lean patient forward or place on the left side (head-down position, if possible) to maintain an open airway and prevent aspiration. Keep patient quiet and maintain normal body temperature. Obtain medical attention. /Poisons A and B/
/SRP:/ Basic treatment: Establish a patent airway (oropharyngeal or nasopharyngeal airway, if needed). Suction if necessary. Watch for signs of respiratory insufficiency and assist ventilations if needed. Administer oxygen by nonrebreather mask at 10 to 15 L/min. Monitor for pulmonary edema and treat if necessary ... . Monitor for shock and treat if necessary ... . Anticipate seizures and treat if necessary ... . For eye contamination, flush eyes immediately with water. Irrigate each eye continuously with 0.9% saline (NS) during transport ... . Do not use emetics. For ingestion, rinse mouth and administer 5 mL/kg up to 200 mL of water for dilution if the patient can swallow, has a strong gag reflex, and does not drool ... . Cover skin burns with dry sterile dressings after decontamination ... . /Poisons A and B/
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including rivaroxaban, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Xarelto is an orally bioavailable factor Xa inhibitor that selectively blocks the active site of factor Xa and does not require a cofactor (such as Anti-thrombin III) for activity. Activation of factor X to factor Xa (FXa) via the intrinsic and extrinsic pathways plays a central role in the cascade of blood coagulation.
The terminal half life is 5-9 hours in adults and 11-13 hours in the elderly.
The terminal elimination half-life is 11 to 13 hours in the elderly.
The terminal elimination half-life of rivaroxaban is 5 to 9 hours in healthy subjects aged 20 to 45 years.
Approximately two-thirds of the dose is metabolized. It is metabolized by CYP3A4, CYP3A5, CYP2J2 and CYP-independant mechanisms
Rivaroxaban undergoes oxidative degradation by cytochrome P-450 (CYP) isoenzymes 3A4/5 and 2J2 and hydrolysis; metabolites are subsequently eliminated through renal and fecal/biliary routes. No major circulating metabolites have been identified in plasma.
9NDF7JZ4M3
RIVAROXABAN
Mechanisms of Action [MoA] - Factor Xa Inhibitors
Established Pharmacologic Class [EPC] - Factor Xa Inhibitor
Rivaroxaban is a Factor Xa Inhibitor. The mechanism of action of rivaroxaban is as a Factor Xa Inhibitor.
RIVAROXABAN
Following oral administration, rivaroxaban is rapidly absorbed and reaches peak plasma concentration in 2-4 hours. Bioavailability of the 10 mg dose is >80%. However, the 15-20 mg dose have a lower bioavailability if taken in the fasted state and consequently should be taken with food.
Approximately two-thirds of rivaroxaban is excreted into urine (via active tubular secretion in which approximately 36% as unchanged drug and 30% as inactive metabolism). The remaining third of the administered dose is excreted via feces in which 7% is in the form of unchanged drug and 21% as inactive metabolites.
The steady state Vd is 50 L
Systemic clearance is approximately 10 L/h, so rivaroxaban is considered a drug with low clearance. Renal clearance is ~3-4 L/h.
Following oral administration, approximately one-third of the absorbed dose is excreted unchanged in the urine, with the remaining two-thirds excreted as inactive metabolites in both the urine and feces. In a Phase 1 study, following the administration of a (14)C-rivaroxaban dose, 66% of the radioactive dose was recovered in urine (36% as unchanged drug) and 28% was recovered in feces (7% as unchanged drug). Unchanged drug is excreted into urine, mainly via active tubular secretion and to a lesser extent via glomerular filtration (approximate 5:1 ratio). Rivaroxaban is a substrate of the efflux transporter proteins P-gp and ABCG2 (also abbreviated Bcrp). Rivaroxaban's affinity for influx transporter proteins is unknown.
Plasma protein binding of rivaroxaban in human plasma is approximately 92% to 95%, with albumin being the main binding component. The steady-state volume of distribution in healthy subjects is approximately 50 L.
MEDICATION
Anticoagulant
BeschreibungRivaroxaban is an orally active, direct inhibitor of Factor Xa (Ki = 0.4 nM), which is a crucial component of the intrinsic and extrinsic pathways of the blood coagulation cascade. It demonstrates >10,000-fold greater selectivity for Factor Xa compared to other related serine proteases (thrombin, trypsin, plasmin, FVIIa, FIXa, FXIa, urokinase, and activated protein C). In various animal arterial and venous thrombosis models, rivaroxaban is reported to inhibit thrombin formation without prolonging bleeding time and has been approved for clinical use as an anticoagulant in the prevention of stroke and the treatment of venous thromboembolisms.
VerwendenRivaroxaban is a novel antithrombotic agent. It is a novel, oral, selective direct inhibitor of factor Xa developed by Bayer Healthcare. It has been approved by the EMEA and FDA for the prevention ofvenous thromboembolism in adult patients after total hip replacement or total kneereplacement surgery.
DefinitionChEBI: Rivaroxaban is a monocarboxylic acid amide obtained by formal condensation of the carboxy group of 5-chlorothiophene-2-carboxylic acid with the amino group of 4-{4-[(5S)-5-(aminomethyl)-2-oxo-1,3-oxazolidin-3-yl]phenyl}morpholin-3-one. An anticoagulant used for prophylaxis of venous thromboembolism in patients with knee or hip replacement surgery. It has a role as an anticoagulant and an EC 3.4.21.6 (coagulation factor Xa) inhibitor. It is a member of thiophenes, an organochlorine compound, an oxazolidinone, a member of morpholines, a lactam, an aromatic amide and a monocarboxylic acid amide.
/SRP:/ Advanced treatment: Consider orotracheal or nasotracheal intubation for airway control in the patient who is unconscious, has severe pulmonary edema, or is in severe respiratory distress. Positive-pressure ventilation techniques with a bag valve mask device may be beneficial. Consider drug therapy for pulmonary edema ... . Consider administering a beta agonist such as albuterol for severe bronchospasm ... . Monitor cardiac rhythm and treat arrhythmias as necessary ... . Start IV administration of D5W /SRP: "To keep open", minimal flow rate/. Use 0.9% saline (NS) or lactated Ringer's if signs of hypovolemia are present. For hypotension with signs of hypovolemia, administer fluid cautiously. Watch for signs of fluid overload ... . Treat seizures with diazepam or lorazepam ... . Use proparacaine hydrochloride to assist eye irrigation ... . /Poisons A and B/