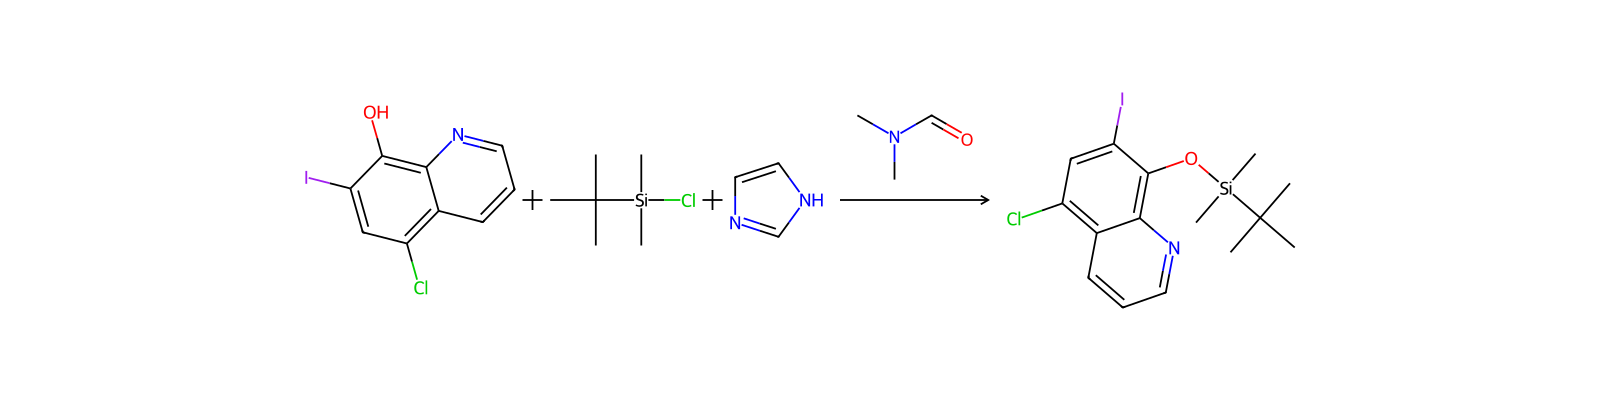
130-26-7Oc1c(I)cc(Cl)c2cccnc12QCDFBFJGMNKBDO-UHFFFAOYSA-NIodochlorohydroxyquinoline is a cream-colored to brownish-yellow powder. Practically odorless. Decomposes at 178-179 °C. Used as a topical anti-infective.
130-26-7DTXSID7022837CHEMBL497CHEBI:74460Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals
Practically odorless
Slight characteristic odor
Brownish-yellow, bulky powder
Yellow brown needles from alcohol, acetic acid.
A voluminous, spongy, yellowish to white brownish powder
less than 1 mg/mL at 68 °F (NTP, 1992)
One part dissolves in 43 parts of boiling alcohol, 128 parts chloroform, 17 parts of boiling ethyl acetate, 170 parts of cold acetic acid, 13 parts of boiling acetic acid. Almost insol in water, and alcohol, ether.
Practically insol water and in alcohol
0.8 [ug/mL] (The mean of the results at pH 7.4)
FDA approved drugs -> Active ingredient
Danger
H301 (41.5%): Toxic if swallowed [Danger Acute toxicity, oral]
P203, P260, P261, P264, P264+P265, P270, P271, P273, P280, P301+P316, P302+P352, P304+P340, P305+P351+P338, P318, P319, P321, P330, P332+P317, P337+P317, P362+P364, P391, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 147 reports by companies from 10 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Chemical: 8-Quinolinol, 5-chloro-7-iodo-
REACH registered substance: Clioquinol (EC: 204-984-4)
SYMPTOMS: Symptoms of exposure to this compound include changes in central nervous system electrical function and optic nerve damage. Other symptoms include abdominal discomfort, diarrhea, paresthesias in the legs (possibly progressing to paraplegia), loss of visual acuity (sometimes leading to irreversible blindness), characteristic green pigmentation of the tongue, feces and urine, sensory disturbances and subacute myelo-optic neuropathy. Irritation of the skin, eyes, mucous membranes and upper respiratory tract may occur.
Allergic contact dermatitis reported in patients using this antibiotic topically; [Marks, p. 123-4] An epidemic of subacute myelo-optico-neuropathy occurred in Japan from 1956 until 1970. Approximately 10,000 cases were reported with visual impairment, lower extremity paresthesias and weakness, and other symptoms. Symptoms resolved after the oral medication was discontinued. Neurotoxicity developed in patients who received total doses greater that 750 mg/day for four weeks. [HSDB]
S - Sensory organs
D - Dermatologicals
P - Antiparasitic products, insecticides and repellents
D - Dermatologicals
G - Genito urinary system and sex hormones
QS - Sensory organs
Clioquinol is a broad-spectrum antibacterial with antifungal properties. Application of clioquinol to extensive or eroded areas of the skin may lead to increased protein-bound iodine (PBI) levels within 1 week. In addition, elevated PBI levels may occur when relatively small areas of the skin are treated with clioquinol for more than 1 week.
7BHQ856EJ5
CLIOQUINOL
Established Pharmacologic Class [EPC] - Standardized Chemical Allergen
Physiologic Effects [PE] - Increased Histamine Release
Physiologic Effects [PE] - Cell-mediated Immunity
Chemical Structure [CS] - Allergens
Topical absorption is rapid and extensive, especially when the skin is covered with an occlusive dressing or if the medication is applied to extensive or eroded areas of the skin. Clioquinol is absorbed through the skin in sufficient amounts to affect thyroid function tests.
Clioquinol is absorbed systemically following topical application to the skin. In 2 studies in which clioquinol combined with a corticosteroid was applied topically to the skin as a cream or ointment, it was estimated that about 2-3% of the dose was absorbed systemically. However, in another study in which the drug was applied alone to the skin as a 3% cream and covered with an occlusive wrap for 12 hr, it was estimated that about 40% of the dose was absorbed percutaneously during this period.
Loading…
352 to 354 °F (NTP, 1992)
178-179 °C
Manufacturers, packers, and distributors of drug and drug products for human use are responsible for complying with the labeling, certification, and usage requirements as prescribed by the Federal Food, Drug, and Cosmetic Act, as amended (secs 201-902, 52 Stat. 1040 et seq., as amended; 21 U.S.C. 321-392).
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl clioquinol hydrocortisone and clioquinol nystatin, approved on the basis of safety and effectiveness by FDA under sections 505 and 507 of the Federal Food, Drug, and Cosmetic Act. /Clioquinol hydrocortisone and clioquinol nystatin/
EYES: First check the victim for contact lenses and remove if present. Flush victim's eyes with water or normal saline solution for 20 to 30 minutes while simultaneously calling a hospital or poison control center. Do not put any ointments, oils, or medication in the victim's eyes without specific instructions from a physician. IMMEDIATELY transport the victim after flushing eyes to a hospital even if no symptoms (such as redness or irritation) develop.
SMALL SPILLS AND LEAKAGE: If a spill of this chemical occurs, FIRST REMOVE ALL SOURCES OF IGNITION, then you should dampen the solid spill material with acetone and transfer the dampened material to a suitable container. Use absorbent paper dampened with acetone to pick up any remaining material. Seal your contaminated clothing and the absorbent paper in a vapor-tight plastic bag for eventual disposal. Solvent wash all contaminated surfaces with acetone followed by washing with a soap and water solution. Do not reenter the contaminated area until the Safety Officer (or other responsible person) has verified that the area has been properly cleaned.
RECOMMENDED RESPIRATOR: Where the neat test chemical is weighed and diluted, wear a NIOSH-approved half face respirator equipped with an organic vapor/acid gas cartridge (specific for organic vapors, HCl, acid gas and SO2) with a dust/mist filter. (NTP, 1992)
Beginning in 1956, an epidemic of a new GI neurologic syndrome, subacute myelo-optico-neuropathy, occurred in Japan. When it was publicly announced on August 7, 1970, approximately 10,000 cases had already been reported. Its etiologic agent was identified as iodochlorhydroxyquin. By September 8, 1970, all halogenated hydroxyquinolines were removed from the market in Japan. Since then, the epidemic has not recurred.
Criteria for the diagnosis of subacute myelo-optico-neuropathy. Cardiac Signs: Abdominal symptoms (abdominal pain, diarrhea, etc.) before the onset of neurological symptoms. Acute or subacute onset of bilateral ascending paresthesia and dysesthesia of the lower extremities. Other Major Signs: Impairment of deep sensation and weakness in the lower limbs, with or without pyramidal signs. Less commonly, sensorimotor disturbances in the upper limbs. Occasionally, one or more of the following: a. Bilateral impairment of vision. b. Disturbances of consciousness, convulsions, psychic symptoms, and other cerebral symptoms. c. Greenish discoloration of the tongue and feces. d. Sphincter disturbances. Protracted course with occasional relapses. No significant laboratory findings in blood and cerebrospinal fluid. Rare occurrence in children.
... There have been many similar cases of subacute myelo-optico-neuropathy scattered in various parts of the world affecting adults, with convincing histories relating clioquinol to disturbances of vision, with varying deg of spinal cord involvement. Visual disturbances have ranged from impairment of discrimination of colors to blindness from optic atrophy, with moderate involvement in the form of central scotomas with symmetrically reduced visual acuity. Clinical ophthalmoscopic abnormality appears to be limited to pallor of the disc in eyes with optic atrophy. In a number of cases there has been improvement of vision during several months after administration of clioquinol was discontinued. No treatment has been effective other than stopping administration of clioquinol.
Some of the earliest suspicions of toxicity affecting vision were in relation to children who were being treated for acrodermatitis enteropathica for long periods with large doses when their vision was found to be much impaired, and optic atrophy was diagnosed. Some children had difficulty in walking as well as poor vision. An investigating committee reported in 1974 knowledge of more than a dozen children with optic neuropathy from clioquinol. Less than half had symptoms of peripheral neuropathy.
A neurotoxicity dose response curve for iodochlorhydroxyquin can be constructed as follows: 750 mg/day for 4 wk or less little risk of toxic reactions. 750-1500 mg/day for less than 2 wk 1% have neurologic symptoms. 750-1,500 mg/day for over 2 wk 35% develop symptoms. 1800 mg/day for 5 days one patient developed symptoms. At higher doses onset of toxic reactions may begin within 24 hr after beginning therapy. The clinical symptoms associated with ingestion of halogenated hydroxyquinolines are primarily those of peripheral neuropathy or myelopathy, with occasional cerebral manifestations. Symptoms range from minimal dysesthesia to death and include optic atrophy.
In dogs, clioquinol caused decrease of visual acuity, with vacuolation and loss of axons in the optic tract. There seems to be agreement that peripheral nerves are not primarily affected, but that long tracts in the spinal cord show degeneration, and that the relatively short axons of the optic nerves are especially vulnerable. The seemingly unique distribution has been termed central distal axonopathy. Demyelination follows axon degeneration.
Emesis induction is indicated after adult ingestion of 1,500 to 1,800 mg of clioquinol if there is no coma, convulsions, or loss of gag reflex. Otherwise, gastric lavage with tracheal protection, activated charcoal, and cathartics. There are no data on the use of forced diuresis, hemodialysis, peritoneal dialysis, hemoperfusion, or exchange transfusion in the treatment of halogenated 8-hydroxyquinoline poisonings. There are no antidotes.
Manufacturers, packers, and distributors of drug and drug products for human use are responsible for complying with the labeling, certification, and usage requirements as prescribed by the Federal Food, Drug, and Cosmetic Act, as amended (secs 201-902, 52 Stat. 1040 et seq., as amended; 21 U.S.C. 321-392).
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl clioquinol hydrocortisone and clioquinol nystatin, approved on the basis of safety and effectiveness by FDA under sections 505 and 507 of the Federal Food, Drug, and Cosmetic Act. /Clioquinol hydrocortisone and clioquinol nystatin/
Patients with widespread dermatitis were treated with 15-20 g of 3% clioquinol ointment to 40% of the body area twice daily. The serum concentration increased to 0.8-1.2 ug/ml within 4 hr of application. In one patient, 15-20 mg was excreted in the urine daily mainly in the form of conjugated metabolites. This skin treatment resulted in a urinary excretion somewhat less than is obtained after a daily oral dose of 25 mg (one tablet) of clioquinol. Thus, 3-4% of the applied clioquinol was absorbed. 25% was excreted in the urine.
Used as a medicinal cream, ointment, or powder; [HSDB]
MEDICATION (VET)
MEDICATION
Use (kg; approx.) in Germany (2009): >250
Topical Cream 3%, Iodochlorhydroxyquin Cream, CMC.
Topical Cream, 3% with Hydrocortisone 0.5%, Ala-Quin, Del-Ray; Vioform -Hydrocortisone Mild, Ciba; 3% with Hydrocortisone 1%, Corque, Geneva; Cortin, C & M Pharmacal; Hysone, Mallard; Vioform -Hydrocortisone; Ciba 3% with Hydrocortisone 1% and Pramoxine Hydrochloride 1% 1 + 1-F, Dunhall Lotion, 0.75% with Hydrocortisone 0.25%, UAD Lotion (with parabens and propylene glycol), UAD Laboratories Ointment, 3% with Hydrocortisone 1%, Vioform-Hydrocortisone, Ciba.
Cream and ointment, 3%
Clipquinol is available in the United States and elsewhere as a 3% ointment or cream and a powder.
8-Quinolinol, 5-chloro-7-iodo-: ACTIVE
Sterilizable substitute for iodoform.
Usesalpha adrenergic blocker, mydriatic, antidepressant
UsesUsed as a topical antifungal treatment
UsesClioquinol is used as an anti-infective agent; antiamoebic agent; intravaginal trichomonacide; used to impregnate cotton bandages for antibacterial purposes; in animals as an intestinal anti-infective agent.
General DescriptionCream-colored to brownish-yellow powder. Practically odorless. Decomposes at 178-179°C. Used as a topical anti-infective.
DefinitionChEBI: A monohydroxyquinoline that is quinolin-8-ol in which the hydrogens at positions 5 and 7 are replaced by chlorine and iodine, respectively. It has antibacterial and atifungal properties, and is used in creams for the treatment of skin infections. It has al o been investigated as a chelator of copper and zinc ions for the possible treatment of Alzheimer's disease.