
HRID 28269As product

7235-40-7CC1=C(/C=C/C(C)=C/C=C/C(C)=C/C=C/C=C(C)/C=C/C=C(C)/C=C/C2=C(C)CCCC2(C)C)C(C)(C)CCC1OENHQHLEOONYIE-JLTXGRSLSA-NBeta-carotene is a cyclic carotene obtained by dimerisation of all-trans-retinol. A strongly-coloured red-orange pigment abundant in plants and fruit and the most active and important provitamin A carotenoid. It has a role as a ferroptosis inhibitor, an antioxidant, a cofactor, a biological pigment, a provitamin A, a mouse metabolite, a plant metabolite and a human metabolite. It is a carotenoid beta-end derivative and a cyclic carotene.
7235-40-7DTXSID3020253CHEMBL1293CHEBI:17579Foods, Drugs, Cosmetics -> FDA Regulatory Status of Color Additives
ANTIOXIDANT, COLOR OR COLORING ADJUNCT, FLAVOR ENHANCER, FLAVORING AGENT OR ADJUVANT, NUTRIENT SUPPLEMENT, PROCESSING AID, SURFACE-FINISHING AGENT -> FDA Substance added to food
Safety information is for reference only and does not replace the supplier’s Safety Data Sheet (SDS), applicable regulations, or professional assessment.
Not Classified
Aggregated GHS information provided per 368 reports by companies from 7 notifications to the ECHA C&L Inventory.
Chemical: .beta.,.beta.-Carotene
Regulation (EC) No 1333/2008 (amended)
REACH registered substance: β,β-carotene (EC: 230-636-6)
Beta Carotene: Does not have an individual approval but may be used under an appropriate group standard
No evidence of reproductive toxicity, embryotoxicity, or teratogenicity in experimental animals; [REPROTOX] Acceptable daily intake (ADI) of 0-5 mg/kg (applies to use as a coloring agent but not to use as a food supplement); [JECFA] May cause irritation; [Sigma-Aldrich MSDS] See Vitamin A.
Certification of this color additive when used as a food is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Certification of this color additive when used as a drug is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Certification of this color additive when used as a cosmetic is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Substance added directly to human food affirmed as generally recognized as safe (GRAS).
For more FDA Requirements (Complete) data for BETA-CAROTENE (7 total), please visit the HSDB record page.
D02BB01
A - Alimentary tract and metabolism
D - Dermatologicals
QA - Alimentary tract and metabolism
QD - Dermatologicals
Beta-carotene is a precursor to vitamin A, which is essential for normal function of the retina; in the form of retinal, it combines with opsin (red pigment in the retina) to form rhodopsin (visual purple), which is necessary for visual adaptation to darkness. It is also necessary for growth of bone, testicular and ovarian function, and embryonic development, and for regulation of growth and differentiation of epithelial tissues.
Of 600 carotenoids from natural sources that have been characterized, fewer than 10% serve as precursors of vitamin A. Many dietary carotenoids, both with and without provitamin A activity, are found in the blood and tissues of humans. beta-Carotene, the most nutritionally active carotenoid, comprises 15-30% of total serum carotenoids. Vitamin A is formed primarily by the oxygen-dependent central cleavage of beta-carotene and other provitamin A carotenoids.
Beta-carotene is thought to be highly bound to plasma proteins. It is registered to be retained by the chylomicron and transported in VLDL. After absorption, beta-carotene is rapidly transformed to retinol which is highly bound to a high number of plasma proteins.
Oral administration of beta-carotene increases the serum concentration of beta-carotene by 60% but it does not change the concentration found in the heart, liver or kidneys. In vitro studies in hepatocytes have shown that beta-carotene ameliorates oxidative stress, enhances antioxidant activity and decreases apoptosis. Other than the antioxidant activities, some other actions have been correlated to beta-carotene. It is thought to have detoxifying properties, as well as to help increase resistance to inflammation and infection and increase immune response and enhance RNA production.
Beta-carotene is an antioxidant that presents significant efficacy against the reactive oxygen species singlet oxygen. Beta-carotene acts as a scavenger of lipophilic radicals within the membranes of every cell compartments. It also presents an oxidative modification of LDL. The presence of long chains of conjugated double bonds is responsible for its antioxidative properties by allowing beta-carotene to chelate oxygen-free radicals and dissipate their energy. The chelation of free radicals inhibits the peroxidation of lipids. The effect of beta-carotene in the immune response is thought to be related to the direct effect on the thymus which increases the production of immune cells.


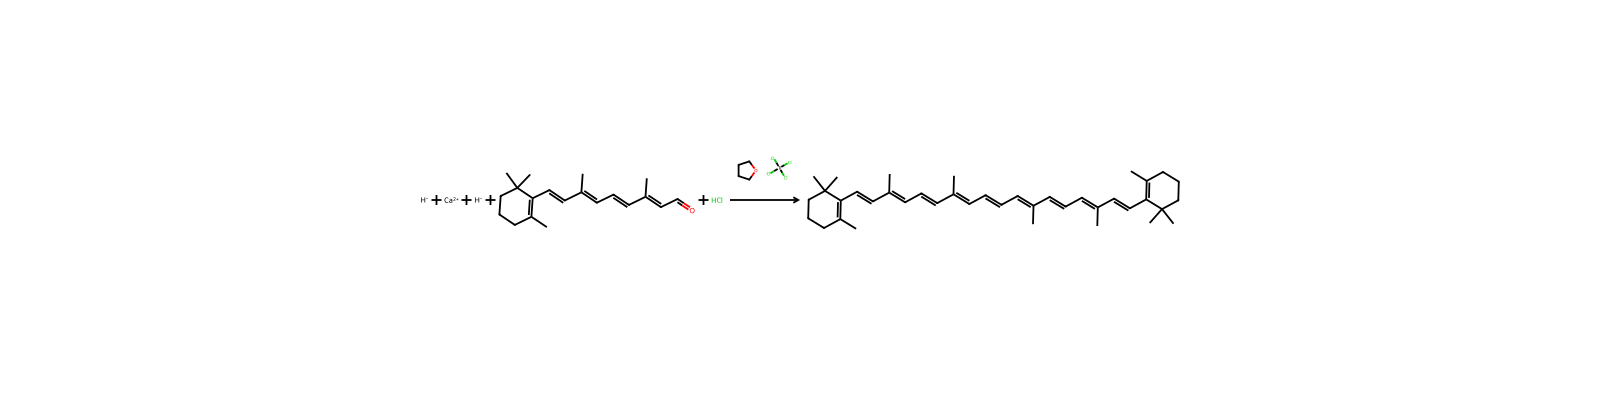


Deep purple, hexagonal prisms from benzene and methanol
Red, rhombic, almost square leaflets from petroleum ether; dil soln are yellow
CRYSTALLINE FORM APPEARS DEEP ORANGE OR COPPER-COLORED
Red-brown hexagonal prisms from benzene and methanol
Sol in benzene, chloroform, carbon disulfide; moderately sol in ether, petroleum ether, oils; 100 ml hexane dissolve 109 mg at 0 °C; very sparingly sol in methanol and ethanol; practically insol in water, acids, alkalies
SOL IN FAT SOLVENTS
Soluble in acetone
Soluble in vegetable oils
For more Solubility (Complete) data for BETA-CAROTENE (7 total), please visit the HSDB record page.
Breast Feeding; Lactation; Milk, Human; Complementary Therapies; Carotenoids; Food; Vitamins
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
633-577ºC
654.00 to 657.00 °C. @ 760.00 mm Hg
Bendich A; The Safety of beta-Carotene. Nutr Cancer 11 (4): 207-14 (1988). Epidemiological studies have associated low dietary and/or plasma level of carotenoids with higher incidences of certain cancers. This evidence has led the NCI to initiate more than a dozen prospective clinical trials in which supplements of beta-carotene alone, or in combination with other micronutrients, are being taken.
WHO/IPCS; Toxicological Evaluation of Certain Food Additives and Contaminants WHO Food Additives Series 32 (1993)
SRP: At the time of review, criteria for land treatment or burial (sanitary landfill) disposal practices are subject to significant revision. Prior to implementing land disposal of waste residue (including waste sludge), consult with environmental regulatory agencies for guidance on acceptable disposal practices.
Cigarette smoking is associated with decreased plasma levels of ascorbate and beta-carotene, which indicates that the smoking related chronic inflammatory response leads to an imbalance of oxidant/antioxidant homeostasis and possible predisposition to oxidant inflicted tissue damage and disease.
Weanling male Sprague-Dawley rats were pair-fed beta-carotene (56.5 mg/L of diet) for 8 weeks, with and without ethanol. As expected, ethanol increased CYP2E1 (measured by Western blots) from 67 + or - 8 to 317 + or - 27 densitometric units (p < 0.001). Furthermore, beta-carotene potentiated the ethanol induction to 442 + or - 38 densitometric units (p < 0.01) with a significant interaction (p = 0.012). The rise was confirmed by a corresponding increase in the hydroxylation of p-nitrophenol, a specific substrate for CYP2E1, and by the inhibition with diethyl dithiocarbamate (50 microM). Beta-carotene alone also significantly induced CYP4A1 protein (328 + or - 49 vs. 158 + or - 17 densitometric units, p < 0.05). The corresponding CYP4A1 mRNA (measured by Northern blots) was also increased (p < 0.05) and there was a significant interaction of the two treatments (p = 0.015). The combination of ethanol and beta-carotene had no significant effect on either total cytochrome P-450 or CYP1A1/2, CYP2B, CYP3A, and CYP4A2/3 contents. Beta-carotene potentiates the CYP2E1 induction by ethanol in rat liver and also increases CYP4A1, which may, at least in part, explain the associated hepatotoxicity.
AFLATOXIN B1 (4 MG/KG/DAY, ORALLY) ADMIN TO RATS FOR 26 DAYS INHIBITED THE FORMATION OF VITAMIN A FROM BETA-CAROTENE IN THE INTESTINAL MUCOSA.
SULFITE-MEDIATED BETA-CAROTENE DESTRUCTION WAS INVESTIGATED; IT WAS INHIBITED BY ALPHA-TOCOPHEROL, 1,2-DIHYDROXYBENZENE-3,5-DISULFONIC ACID & BUTYLATED HYDROXYTOLUENE
For more Interactions (Complete) data for BETA-CAROTENE (25 total), please visit the HSDB record page.
EXPERIMENTAL: This study investigated milk carotenoid concentrations during days 4-32 postpartum and assessed the effects of maternal beta-carotene supplementation. Subjects (n = 21; aged 19-39 y) were randomly assigned to receive beta-carotene (30 mg/d) or placebo from days 4 to 32 postpartum. Each subject provided 8 diet records and 8 milk samples during the study. Diet records were analyzed for energy, macronutrients, vitamins A and E, and carotenoids. Milk samples were analyzed with HPLC for concentrations of carotenoids, retinol, and alpha-tocopherol. Data were analyzed by using repeated-measures analysis and orthogonal contrasts. No significant differences in average dietary intakes, body mass index, age, or parity were found between groups at baseline or after supplementation. Milk carotenoid concentrations decreased over time (P < 0.01), as did retinol and alpha-tocopherol concentrations (P < 0.003). Concentrations of most carotenoids decreased to those reported for mature milk by day 32 postpartum. Milk lutein concentrations remained elevated throughout the study compared with values reported for mature milk, whereas plasma lutein concentrations decreased significantly over time. beta-carotene supplementation did not significantly change the milk concentrations of beta-carotene, the other carotenoids, retinol, or alpha-tocopherol. CONCLUSIONS: The lack of increase in milk beta-carotene despite supplementation suggests that transitional milk may be already nearly saturated with beta-carotene. The elevated milk lutein concentration and simultaneous decrease in plasma lutein suggest that lutein metabolism may be altered during early lactation.
ORANGE-YELLOW PIGMENT IN PLANTS, ALGAE, & SOME MARINE ANIMALS, ESP IN LEAVES, VEGETATION, & ROOT CROPS, IN TRACE CONCN. NOTABLY PRESENT IN BUTTER & CARROTS. /CAROTENE/
RICHEST SOURCES OF CAROTENE ARE YELLOW & GREEN (LEAFY) VEGETABLES & YELLOW FRUITS.
/SIGNS AND SYMPTOMS/ Two large studies have found an increased incidence in lung cancers when beta-carotene supplements were given to individuals with a history of smoking and/or asbestos exposure. One study of 29,000 males with a history of smoking found an 18% increase in the incidence of lung cancer in the group receiving 20 mg of beta-carotene a day for 5 to 8 years as compared with those receiving placebo . Another study of 18,000 individuals found 28% more lung cancers in individuals with a history of smoking and/or asbestos exposure who took 30 mg of beta-carotene in addition to 25,000 Units of retinol a day for 4 years as compared with those receiving placebo . However, one study of 22,000 male physicians, some of them smokers and former smokers, found no increased risk of lung cancer at doses of 50 mg of beta-carotene every other day for 12 years .
/EPIDEMIOLOGY STUDIES/ Epidemiological studies have suggested a protective effect of vegetables and fruits on urinary tract cancer but the possible protective nutrients are unknown. We studied the effect of alpha-tocopherol (a form of vitamin E) and beta-carotene supplementation on urinary tract cancer in the Alpha-Tocopherol, Beta-Carotene Cancer Prevention (ATBC) Study. A total of 29,133 male smokers aged 50-69 years from southwestern Finland were randomly assigned to receive alpha-tocopherol (50 mg), beta-carotene (20 mg), both agents, or a placebo daily for 5-8 years (median 6.1 years). Incident urothelial cancers (bladder, ureter, and renal pelvis; n = 169) and renal cell cancers (n = 102) were identified through the nationwide cancer registry. The diagnoses were centrally confirmed by review of medical records and pathology specimens. The supplementation effects were estimated using a proportional hazards model. Neither alpha-tocopherol nor beta-carotene affected the incidence of urothelial cancer, relative risk 1.1 (95% confidence interval (CI) 0.8-1.5) and 1.0 (95% CI 0.7-1.3), respectively, or the incidence of renal cell cancer, relative risk 1.1 (95% CI 0.7-1.6) and 0.8 95% CI 0.6-1.3), respectively. Long-term supplementation with alpha-tocopherol and beta-carotene has no preventive effect on urinary tract cancers in middle-aged male smokers.
/EPIDEMIOLOGY STUDIES/ The Beta-Carotene and Retinol Efficacy Trial (CARET) was terminated 21 months ahead of schedule due to an excess of lung cancers. Deaths from cardiovascular disease also increased (relative risk=1.26 (95% confidence interval (CI) 0.99-1.61)) in the group assigned to a combination of 30 mg beta-carotene and 25 000 IU retinyl palmitate (vitamin A) daily. The basis for increased cardiovascular mortality is unexplained. Data on serum lipids, available for 1474 CARET Vanguard participants who were enrolled in the two CARET pilot studies and transitioned to the Vanguard study /were analyzed/. Total cholesterol and triglycerides were measured 2 months prior to, 4 and 12 months following randomization, and annually thereafter for up to 7 y. In the asbestos-exposed pilot (N = 816), participants were assigned to beta-carotene and retinol or to placebo; in the smokers pilot (N = 1029), participants were assigned to beta-carotene, retinol, a combination, or placebo. Serum cholesterol showed a decline over time in both arms; serum triglycerides had a continuous decline over time in the placebo arm, but an initial increase that persisted in the active arm. Both serum cholesterol concentrations (P < 0.0003) and serum triglycerides (P < 0.0001) were significantly higher in the participants receiving vitamin A and/or a combination of vitamin A and beta-carotene (n = 863) as compared to the placebo group (n = 611). Those in this active intervention group had an average cholesterol concentration 5.3 mg/dl (0.137 mmol/l) higher than those in the placebo arm. /It was concluded/ the differences in cholesterol and triglyceride concentrations between the groups following randomization may account in part for the unexpected excess in cardiovascular deaths seen in the active intervention arm of CARET.
/LABORATORY ANIMALS: Subchronic or Prechronic Exposure/ The inhibitory effects of beta-carotene on preneoplastic lesions induced in male Wistar rats by the resistant hepatocyte model was investigated. Rats were divided into six groups. Initiation was performed in all animals by a single injection of diethylnitrosamine. During the selection/promotion period five doses of 2-acetylaminofluorene were administered to the rats and a partial hepatectomy was performed. To three different groups beta-carotene was given by gavage throughout the experiment, before the initiation or during the selection/promotion period respectively. Three other groups served as controls and received corn oil instead of the carotenoid. At the end of the study (8 weeks), beta- carotene administration throughout the experiment reduced the incidence (p< 0.005), multiplicity as well as the total number and size of hepatocyte nodules. Furthermore, it significantly decreased the number of foci per sq cm (p< 0.05), the average focal area (p< 0.01) and the percentage of liver parenchyma occupied (p< 0.01). Similar results were observed when beta-carotene was given only before the initiation. However, the administration of the carotenoid during the selection/promotion period did not result in significant decreases of these parameters. These results suggest that the inhibitory effects of beta-carotene are primarily exerted on the initiation phase of the hepatocarcinogenic process. Nevertheless, continuous long term exposure to the carotenoid would confer a greater degree of protection. In addition, by means of an analysis of correlation a positive relationship was found between the number of hepatocyte nodules and the hepatic concentration of beta-carotene. In contrast, an inverse relationship was observed between the number of nodules and the hepatic concentration of total vitamin A.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ In this study, the inhibitory effect of natural alpha-carotene, obtained from palm oil was compared with that of beta-carotene on spontaneous liver carcinogenesis in C3H/He male mice. The mean number of hepatomas per mouse was significantly decreased by alpha-carotene supplementation (oral administration in drinking water at a concentration of 0.05%, at pleasure) as compared with that in the control group (p< 0.001, Student's t test). On the other hand, beta-carotene, at the same dose as alpha-carotene, did not show any such significant difference from the control group.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ The effects of beta-carotene (BC) on ventricular remodeling after myocardial infarction /were studied/. Myocardial infarction was induced in Wistar rats that were then treated with a BC diet (500 mg/kg of diet per day; MI-BC; n = 27) or a regular diet (MI; n = 27). Hearts were analyzed in vivo and in vitro after 6 mo. BC caused decreased left ventricular wall thickness (MI = 1.49 + or - 0.3 mm, MI-BC = 1.23 + or - 0.2 mm, P = 0.027) and increased diastolic (MI = 0.83 + or - 0.15 cm2, MI-BC = 0.98 + or - 0.14 cm2, P = 0.020) and systolic (MI = 0.56 + or - 0.12 cm2, MI-BC = 0.75 + or - 0.13 cm2, P = 0.002) left ventricular chamber areas. With respect to systolic function, the BC group presented less change in fractional area than did controls (MI = 32.35 + or - 6.67, MI-BC = 23.77 + or - 6.06, P = 0.004). There was no difference in transmitral diastolic flow velocities between groups. In vitro results showed decreased maximal isovolumetric systolic pressure (MI = 125.5 + or - 24.1 mm Hg, MI-BC = 95.2 + or - 28.4 mmHg, P = 0.019) and increased interstitial myocardial collagen concentration (MI = 3.3 + or - 1.2%, MI-BC = 5.8 + or - 1.7%, P = 0.004) in BC-treated animals. Infarct sizes were similar between groups (MI = 45.0 + or - 6.6%, MI-BC = 48.0 + or - 5.8%, P = 0.246). Taken together, these data suggest that BC has adverse effects on ventricular remodeling after myocardial infarction.
Two large studies have found an increased incidence in lung cancers when beta-carotene supplements were given to individuals with a history of smoking and/or asbestos exposure. One study of 29,000 males with a history of smoking found an 18% increase in the incidence of lung cancer in the group receiving 20 mg of beta-carotene a day for 5 to 8 years as compared with those receiving placebo . Another study of 18,000 individuals found 28% more lung cancers in individuals with a history of smoking and/or asbestos exposure who took 30 mg of beta-carotene in addition to 25,000 Units of retinol a day for 4 years as compared with those receiving placebo . However, one study of 22,000 male physicians, some of them smokers and former smokers, found no increased risk of lung cancer at doses of 50 mg of beta-carotene every other day for 12 years .
/SRP:/ Basic treatment: Establish a patent airway (oropharyngeal or nasopharyngeal airway, if needed). Suction if necessary. Watch for signs of respiratory insufficiency and assist ventilations if needed. Administer oxygen by nonrebreather mask at 10 to 15 L/min. Monitor for pulmonary edema and treat if necessary ... . Monitor for shock and treat if necessary ... . Anticipate seizures and treat if necessary ... . For eye contamination, flush eyes immediately with water. Irrigate each eye continuously with 0.9% saline (NS) during transport ... . Do not use emetics. For ingestion, rinse mouth and administer 5 ml/kg up to 200 ml of water for dilution if the patient can swallow, has a strong gag reflex, and does not drool ... . Cover skin burns with dry sterile dressings after decontamination ... . /Poisons A and B/
/SRP:/ Advanced treatment: Consider orotracheal or nasotracheal intubation for airway control in the patient who is unconscious, has severe pulmonary edema, or is in severe respiratory distress. Positive-pressure ventilation techniques with a bag valve mask device may be beneficial. Consider drug therapy for pulmonary edema ... . Consider administering a beta agonist such as albuterol for severe bronchospasm ... . Monitor cardiac rhythm and treat arrhythmias as necessary ... . Start IV administration of D5W /SRP: "To keep open", minimal flow rate/. Use 0.9% saline (NS) or lactated Ringer's if signs of hypovolemia are present. For hypotension with signs of hypovolemia, administer fluid cautiously. Watch for signs of fluid overload ... . Treat seizures with diazepam or lorazepam ... . Use proparacaine hydrochloride to assist eye irrigation ... . /Poisons A and B/
Certification of this color additive when used as a food is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Certification of this color additive when used as a drug is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Certification of this color additive when used as a cosmetic is not necessary for the protection of the public health and therefore batches thereof are exempt from the requirements of section 706(c) of the Federal Food, Drug, and Cosmetic Act.
Substance added directly to human food affirmed as generally recognized as safe (GRAS).
For more FDA Requirements (Complete) data for BETA-CAROTENE (7 total), please visit the HSDB record page.
IN HEMATOPORPHYRIN PHOTOSENSITIZED MICE BETA-CAROTENE SHOWED PHOTOPROTECTION WAS DUE TO FREE RADICAL SCAVENGING OR SINGLET O QUENCHING BUT ALSO A POSSIBLE ROLE OF 400 NM LIGHT ABSORPTION, A PROPERTY OF BETA-CAROTENE.
Beta carotene protects patients with erythropoietic protoporphyria against severe photosensitivity reactions (burning sensation, edema, erythema, pruritus, and/or cutaneous lesions). The drug has no effect on the basic biochemical abnormality of erythropoietic protoporphyria (eg, erythrocyte, plasma, and stool concentrations of protoporphyrins are not altered by the drug). The precise mechanism by which the drug exerts photoprotection has not been established. There is some evidence that photosensitizers may act through the formation of singlet excited oxygen and/or free radicals. Since in vitro studies indicate that beta carotene can quench free radicals and singlet excited oxygen, this may be the mechanism by which the drug acts. It is unlikely that beta carotene acts simply as a filter for the wavelengths of light that induce phototoxic effects.
beta-Carotene inhibits UV-B carcinogenesis. beta-Carotene is an excellent quencher of singlet oxygen, and can quench free radicals. beta-Carotene has been shown to quench singlet oxygen/free radical reactions in the skin of porphyric mice, and has been found to quench excited species formed on irradiation of mouse skin by UV-B.
Beta-carotene is broken down in the mucosa of the small intestine and liver by beta-carotene dioxygenase to retinal which is a form of vitamin A. The function of this enzyme is vital as it decides if the beta-carotene is transformed to vitamin A or if it circulates in the plasma as beta-carotene. Less than a quarter of the ingested beta-carotene from root vegetables and about half of the beta-carotene from leafy green vegetables are converted to vitamin A.
A portion of the beta-carotene is converted to retinol in the wall of the small intestine, principally by its initial cleavage at the 15,15' double bond to form two molecules of retinal. Some of the retinal is further oxidized to retinoic acid; only one-half is reduced to retinol, which is then esterified and transported in the lymph. ...
Approximately 20 to 60% of beta-carotene is metabolized to retinaldehyde and then converted to retinol, primarily in the intestinal wall. A small amount of beta-carotene is converted to vitamin A in the liver. The proportion of beta-carotene converted to vitamin A diminishes inversely to the intake of beta-carotene, as long as the dosages are higher than one to two times the daily requirements. High doses of beta-carotene do not lead to abnormally high serum concentrations of vitamin A.
Beta carotene may be converted to 2 molecules of retinal by cleavage at the 15-15' double bond in the center of the molecule. Most of the retinal is reduced to retinol which is then conjugated with glucuronic acid and excreted in urine and feces. Some retinal may be further oxidized to retinoic acid which can be decarboxylated and further metabolized, secreted into bile, and excreted in feces as the glucuronide.
Two pathways have been suggested for the conversion of carotenoids to vitamin A in mammals, central cleavage and excentric cleavage. An enzyme, beta-carotenoid-15,15'-dioxygenase, has been partly purified from the intestines of several species and has been identified in several other organs and species. The enzyme, which converts beta-carotene into two molecules of retinal in good yield, requires molecular oxygen and is inhibited by sulfhydryl binding reagents and iron binding reagents. Most provitamin A carotenoids, including the beta-apo-carotenals, are cleaved to retinal by this enzyme. Its maximal activity in the rabbit is approximately 200 times that required to meet nutritional needs but is less than 50% of that expected to produce signs of vitamin A toxicity. Excentric cleavage unquestionably occurs in plants and some microorganisms and might occur in mammals. Thus far, however, carotenoid dioxygenase with excentric bond specificity has been identified in mammals, the yield of beta-apo-carotenals from beta-carotene in vivo and in vitro is very low, and beta-apo-carotenals are formed nonbiologically from beta-carotene.
The carotenes are not converted to retinol very rapidly, so that overdoses of the carotenes do not cause vitamin A toxicity. /Carotenes/
After administration of beta-carotene, some of the administered dose is absorbed into the circulatory system unchanged and stored in the fat tissue. The coadministration of beta-carotene and a high-fat content diet is correlated to a better absorption of beta-carotene. The absorption is also dependent on the isomeric form of the molecule where the cis conformation seems to present a higher bioavailability. The absorption of beta-carotene is thought to be performed in 6-7 hours. The reported AUC of beta-carotene when administered orally from 0 to 440 hours after initial administration was reported to be 26.3 mcg.h/L. The maximal concentration of beta-carotene is attained in a dual pharmacokinetic profile after 6 hours and again after 32 hours with a concentration of 0.58 micromol/L.
The unabsorbed carotene is excreted in feces. It is also excreted in feces and urine as metabolites. The consumption of dietary fiber can increase the fecal excretion of fats and other fat-soluble compounds such as beta-carotene.
No pharmacokinetic studies have been performed regarding the volume of distribution of beta-carotene.
The clearance rate of beta-carotene administered orally is 0.68 nmol/L each hour.
Carotenoids are absorbed and transported via lymphatics to the liver. They circulate in association with lipoproteins, and are found in liver, adrenal, testes, and adipose tissue, and can be converted to vitamin A in numerous tissues, including the liver. Some beta carotene is absorbed as such and circulates in association with lipoproteins; it apparently partitions into body lipids and can be converted to vitamin A in numerous tissues, including the liver.
Absorption of beta-carotene depends on the presence of dietary fat and bile in the intestinal tract.
The most important provitamin A; Found in plants and animals and used to color foods yellow, as an ultraviolet screen, and as a vitamin A precursor; [Merck Index] Used as flavoring agent, antioxidant, color, nutritional supplement, processing aid, and surface-finishing agent for foods; [FDA]
Yellow coloring agent for foods.
MEDICATION
Therapeutic Category: Vitamine A precursor. Ultraviolet screen.
Therapeutic Category (Vet): Vitamin A precursor for all species except cats.
Use (kg; approx.) in Germany (2009): >50
Beta-carotene supplements are available as synthetic beta-carotene and natural beta-carotene. Synthetic beta-carotene is comprised mainly of all-trans beta-carotene with small amounts of 13-cis beta-carotene and even smaller amounts of 9-cis beta-carotene. Natural beta-carotene is principally derived from the algae Dunaliella salina and is comprised of all-trans beta-carotene and 9-cis beta-carotene. Three mg of beta-carotene is equal to 5,000 UIs. Supplemental intake of beta-carotene ranges from 3-15 mg/day.
GRADES: ACCORDING TO USP, UNITS OF VIT A, SOLD AS PURE CRYSTALS, AS SOLN IN VARIOUS OILS, AS COLLOIDAL DISPERSION. ALSO 'FOOD CHEMICAL CODEX' /CAROTENE/
Oral: Capsules: 15 mg, 60 mg (available by nonproprietary name).
Food additives
Food additives
Food additives
Food additives
Fragrance Ingredients
Food Additives -> COLOUR -> JECFA Functional Classes
.beta.,.beta.-Carotene: ACTIVE
MOST IMPORTANT OF PROVITAMINS A. WIDELY DISTRIBUTED IN PLANT & ANIMAL KINGDOM. IN PLANTS IT OCCURS ALMOST ALWAYS TOGETHER WITH CHLOROPHYLL. ... COMMERCIAL CRYSTALLINE BETA-CAROTENE HAS A VIT A ACTIVITY OF 1.67 MILLION USP UNITS/G. THE IU OF 0.6 UG BETA-CAROTENE IS ALMOST EXACTLY EQUIV TO 0.3 UG VIT A.
ONE IU OF VITMIN A IS SPECIFIC BIOLOGICAL ACTIVITY OF 0.3 UG OF ALL-TRANS-RETINOL OR 0.6 UG OF BETA-CAROTENE. BECAUSE OF RELATIVELY INEFFICIENT DIETARY UTILIZATION OF BETA-CAROTENE COMPARED WITH RETINOL, NOMENCLATURE IS IN THE TERMS OF RETINOL EQUIVALENTS, WHICH REPRESENTS 1 UG OF ALL-TRANS-RETINOL, 6 UG OF DIETARY BETA-CAROTENE, OR 12 UG OF OTHER PROVITAMIN A CAROTENOIDS.
... CONSISTS OF 3 ISOMERS, APPROX 15% ALPHA, 85% BETA, & 0.1% GAMMA. /CAROTENE/
THEORETICALLY ONE MOLECULE OF BETA-CAROTENE SHOULD YIELD TWO MOLECULES OF VIT A1; HOWEVER, AVAILABILITY OF CAROTENE IN FOODS AS SOURCES OF VIT A FOR HUMANS IS LOW & EXTREMELY VARIABLE. ... UTILIZATION EFFICIENCY OF CAROTENE IS GENERALLY CONSIDERED TO BE 1/6 FOR HUMANS ... .
For more General Manufacturing Information (Complete) data for BETA-CAROTENE (6 total), please visit the HSDB record page.
Descriptionbeta-Carotene is widely distributed in both plant and animal kingdoms and is the most important pro-vitamin A. In plants, it is almost always found with chlorophyll.
OccurrenceBeta-carotene is available naturally in fruits and vegetables. Synthetically, it may be manufactured from fungi or algae.
UsesBeta-carotene is a known antioxidant, and antioxidants are substances that may protect your cells from free radicals, which may play a role in heart disease, cancer and other diseases. beta-carotene is a coloring agent used in margarine, cheese and pudding to produce the desired color, and is also used as an additive to yellow-orange color. beta-carotene is also a precursor to carotenoids and vitamin A It is beneficial in protecting the skin from dryness and peeling. It also slows cognitive decline and is beneficial to human health.
General Descriptionbeta-Carotene is an antioxidant and is one of the most important carotenoids and a source of vitamin A. It is abundantly present in fruits and vegetables which is also used as a food supplement and a colorant.
DefinitionChEBI: A cyclic carotene obtained by dimerisation of all-trans-retinol. A strongly-coloured red-orange pigment abundant in plants and fruit and the most active and important provitamin A carotenoid.
/EPIDEMIOLOGY STUDIES/ The Physicians' Health Study (PHS) was a randomized trial of beta-carotene (50 mg, alternate days) and aspirin in primary prevention of cancer and cardiovascular disease among 22,071 US male physicians. This report updates results for beta-carotene and examines effect modification by baseline characteristics. Beta-carotene's effect on cancer over nearly 13 years was examined overall and within subgroups defined by baseline characteristics using proportional-hazards models. 2667 incident cancers were confirmed, with 1117 prostate, 267 colon, and 178 lung cancers. There were no significant differences with supplementation in total (relative risk (RR) = 1.0, 95% confidence interval (CI) = 0.9-1.0); prostate (RR = 1.0, 95% CI = 0.9-1.1); colon (RR = 0.9, 95% CI = 0.7-1.2); or lung (RR = 0.9, 95% CI = 0.7-1.2) cancer, and no differences over time. In subgroup analyses, total cancer was modestly reduced with supplementation among those aged 70+ years (RR = 0.8, 95% CI = 0.7-1.0), daily drinkers of alcohol (RR = 0.9, 95% CI = 0.8-1.0), and those in the highest BMI quartile (RR = 0.9, 95% CI = 0.7-1.0). Prostate cancer was reduced with supplementation among those in the highest BMI quartile (RR = 0.8, 95% CI = 0.6-1.0), and colon cancer was reduced among daily drinkers of alcohol (RR = 0.5, 95% CI = 0.3-0.8). The PHS found no overall effect of beta-carotene on total cancer, or the three most common site-specific cancers. The possibility of risk reduction within specific subgroups remains.
For more Human Toxicity Excerpts (Complete) data for BETA-CAROTENE (15 total), please visit the HSDB record page.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ A 3 generation reproduction study in rats receiving beta carotene at a dietary concentration of 0.1% has revealed no evidence of harm to the fetus.
For more Non-Human Toxicity Excerpts (Complete) data for BETA-CAROTENE (12 total), please visit the HSDB record page.