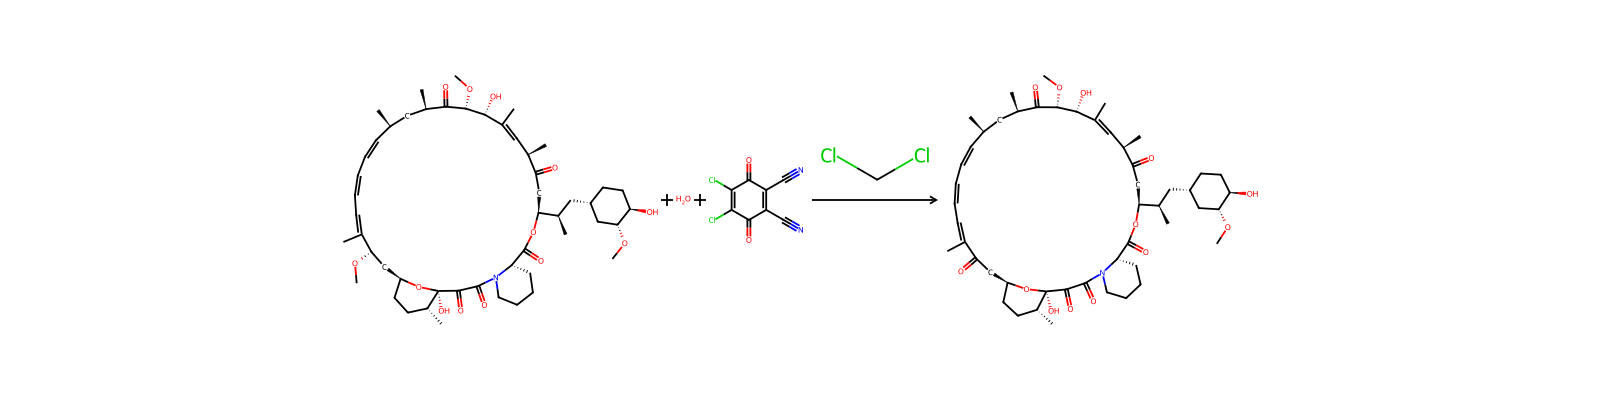
HRID 2147As reactant

53123-88-9CO[C@H]1C[C@@H]2CC[C@@H](C)[C@@](O)(O2)C(=O)C(=O)N2CCCC[C@H]2C(=O)O[C@H]([C@H](C)C[C@@H]2CC[C@@H](O)[C@H](OC)C2)CC(=O)[C@H](C)/C=C(\C)[C@@H](O)[C@@H](OC)C(=O)[C@H](C)C[C@H](C)/C=C/C=C/C=C/1CQFJCIRLUMZQUOT-HPLJOQBZSA-NSirolimus is a macrolide lactam isolated from Streptomyces hygroscopicus consisting of a 29-membered ring containing 4 trans double bonds, three of which are conjugated. It is an antibiotic, immunosupressive and antineoplastic agent. It has a role as an anticoronaviral agent, a geroprotector, an antineoplastic agent, an immunosuppressive agent, an antibacterial drug, a mTOR inhibitor and a bacterial metabolite. It is a macrolide lactam, an ether, an organic heterotricyclic compound, a secondary alcohol, a cyclic ketone, a cyclic acetal and an antibiotic antifungal drug.
53123-88-9DTXSID5023582CHEMBL413CHEBI:9168log Kow = 4.81 /Estimated/
4.3
Sol in ether, chloroform, acetone, methanol, and DMF; very sparingly sol in hexane and petr ether.
In water = 9.9X10⁻⁵ mg/L at 25 °C /Estimated/
1.73e-03 g/L
Breast Feeding; Lactation; Milk, Human; Immunosuppressive Agents
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine (Orphan designations)
FDA approved drugs -> Active ingredient
Safety information is for reference only and does not replace the supplier’s Safety Data Sheet (SDS), applicable regulations, or professional assessment.
This chemical does not meet GHS hazard criteria for 4.7% (2 of 43) of reports.
Danger
H341 (11.6%): Suspected of causing genetic defects [Warning Germ cell mutagenicity]
P203, P260, P264, P270, P280, P318, P319, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 43 reports by companies from 14 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
REACH registered substance: (3S,6R,7E,9R,10R,12R,14S,15E,17E,19E,21S,23S,26R,27R,34aS)-9,10,12,13,14,21,22,23,24,25,26,27,32,33,34,34a-hexadecahydro-9,27-dihydroxy-3-[(1R)-2-[(1S,3R,4R)-4-hydroxy-3-methoxycyclohexyl]-1-methylethyl]-10,21-dimethoxy-6,8,12,14,20,26-hexamethyl-23,27-epoxy-3H-pyrido[2,1-c][1,4]-oxaazacyclohentriacontine-1,5,11,28,29(4H,6H,31H)-pentone (EC: 610-965-5)
Rapamycin: Does not have an individual approval but may be used as a component in a product covered by a group standard. It is not approved for use as a chemical in its own right.
Emergency treatment: Tacrolimus and related agents; May cause tremors and seizures; Other adverse effects in treated patients include diarrhea, kidney injury, anemia, thrombocytopenia, rash, and hypertension. Acute overdoses of up to 120 mg are generally well tolerated in adults. [HSDB] May cause irritation; Targets the immune system; [MSDSonline]
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl sirolimus, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
L04AA10
S - Sensory organs
L - Antineoplastic and immunomodulating agents
L - Antineoplastic and immunomodulating agents
QC - Cardiovascular system
QL - Antineoplastic and immunomodulating agents
Sirolimus is an immunosuppressant drug with antifungal and antitumour effects. In animal models, sirolimus prolonged allograft survival following various organ transplants and reversed an acute rejection of heart and kidney allografts in rats. Upon oral administration of 2 mg/day and 5 mg/day, sirolimus significantly reduced the incidence of organ rejection in low- to moderate-immunologic risk renal transplant patients at six months following transplantation compared with either azathioprine or placebo. In some studies, the immunosuppressive effect of sirolimus lasted up to six months after discontinuation of therapy: this tolerization effect is alloantigen-specific. Sirolimus potently inhibits antigen-induced proliferation of T cells, B cells, and antibody production. In rodent models of autoimmune disease, sirolimus suppressed immune-mediated events associated with systemic lupus erythematosus, collagen-induced arthritis, autoimmune type I diabetes, autoimmune myocarditis, experimental allergic encephalomyelitis, graft-versus-host disease, and autoimmune uveoretinitis.
Sirolimus works by inhibiting T-lymphocyte activation and proliferation stimulated by antigens and cytokines such as interleukin (IL)-2, IL-4, and IL-15. In target cells, sirolimus binds to the cytoplasmic receptor FK506-binding protein-12 (FKBP12), an immunophilin, to form an immunosuppressive complex. FKBP12-sirolimus complex binds to and inhibits the activation of the mammalian target of rapamycin (mTOR), which is a serine/threonine-specific protein kinase that regulates cell growth, proliferation, survival, mobility, and angiogenesis. mTOR regulates the downstream signalling pathways involved in cell survival, such as the phosphatidylinositol-3 kinase (PI3K)/Akt signalling pathway. Inhibition of mTOR leads to the suppression of cytokine-driven T-cell proliferation, thus the progression from the G1 to the S phase of the cell cycle is inhibited. Sirolimus also inhibits antibody production. _In vitro_, sirolimus and other mTOR inhibitors inhibit the production of certain growth factors that may affect angiogenesis, fibroblast proliferation, and vascular permeability. Lymphangioleiomyomatosis is a disorder that primarily affects the lungs. It is characterized by lung tissue infiltration, unregulated alveolar smooth muscle proliferation, and cystic destruction of parenchyma. Although infrequent, it occurs as a symptomatic pulmonary complication in tuberous sclerosis complex (TSC), which is an inherited disorder caused by mutations in TSC genes. Loss of functional TSC gene leads to the aberrant activation of the mTOR signalling pathway, resulting in cellular proliferation and release of lymphangiogenic growth factors. Sirolimus inhibits the activated mTOR pathway and proliferation of alveolar smooth muscle cell proliferation.

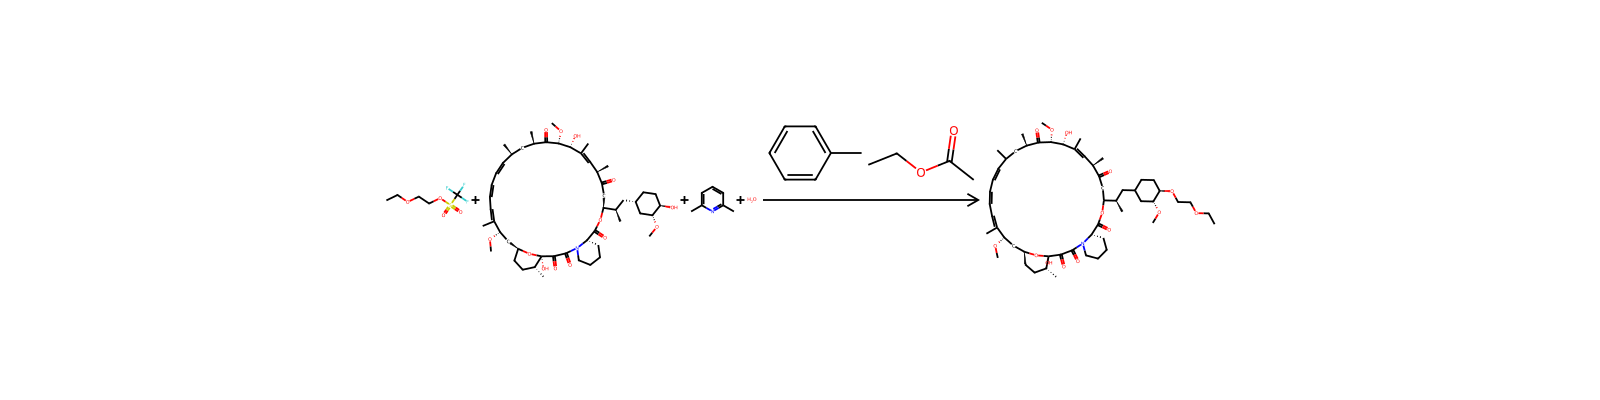


Colorless solid; [Merck Index]
Solid
SRP: The most favorable course of action is to use an alternative chemical product with less inherent propensity for occupational exposure or environmental contamination. Recycle any unused portion of the material for its approved use or return it to the manufacturer or supplier. Ultimate disposal of the chemical must consider: the material's impact on air quality; potential migration in soil or water; effects on animal, aquatic, and plant life; and conformance with environmental and public health regulations.
General supportive measures should be followed in all cases of overdose. Based on the low aqueous solubility and high erythrocyte and plasma protein binding of sirolimus, it is anticipated that sirolimus is not dialyzable to any significant extent. (L1712)
Because St. John's wort (hypericum perforatum) induces the activity of CYP3A4 and P-glycoprotein and sirolimus is a substrate of both, concurrent use of St. John's wort with sirolimus may result in decreased sirolimus concentrations.
/Concurrent use of sirolimus with tacrolimus/ may cause excess mortality, graft loss and hepatic artery thrombosis (HAT) in liver transplant patients, most cases of HAT occured within 30 days post-transplantation.
/Antibiotics such as: rifabutin or rifapentine; and anticonvulsants such as: carbamazepine, phenobarbital, or phenytoin/ may decrease sirolimus concentrations due to cytochrome p450 3A4 (CYP3 A4) isoenzyme induction.
Significant increases in sirolimus clearance occur when administered with rifampin due to CYP3A4 induction by rifampin; an alternative antibacterial agent with less enzyme induction potential should be considered.
For more Interactions (Complete) data for SIROLIMUS (11 total), please visit the HSDB record page.
Serum enzyme elevations occur in a proportion of patients taking sirolimus, but the abnormalities are usually mild, asymptomatic and self-limiting, rarely requiring dose modification or discontinuation. Rare instances of cholestatic hepatitis have been reported with sirolimus use, but the clinical features of the clinically apparent liver injury due to this agent have not been well defined. Most published cases of liver injury attributed to sirolimus occurred in patients exposed to other potentially hepatotoxic agents or who have other underlying possible causes of the abnormalities such as sepsis, cancer or parenteral nutrition. Hepatic artery thrombosis has been reported to be more common with sirolimus therapy after liver transplantation, but this association is still controversial.
Sirolimus inhibits T lymphocyte activation and proliferation that occurs in response to antigenic and cytokine (Interleukin IL-2, IL-4, and IL-15) stimulation by a mechanism that is distinct from that of other immunosuppressants. Sirolimus also inhibits antibody production. In cells, sirolimus binds to the immunophilin, FK Binding Protein-12 (FKBP-12), to generate an immunosuppressive complex. The sirolimus:FKBP-12 complex has no effect on calcineurin activity. This complex binds to and inhibits the activation of the mammalian Target Of Rapamycin (mTOR), a key regulatory kinase. This inhibition suppresses cytokine-driven T-cell proliferation, inhibiting the progression from the G1 to the S phase of the cell cycle.
The most common ( ≥ 30%) adverse reactions observed with Rapamune in clinical studies are: peripheral edema, hypertriglyceridemia, hypertension, hypercholesterolemia, creatinine increased, constipation, abdominal pain, diarrhea, headache, fever, urinary tract infection, anemia, nausea, arthralgia, pain, and thrombocytopenia. (L1874)
/SIGNS AND SYMPTOMS/ Grapefruit juice may inhibit CYP 3A4 enzymes, leading to decreased metabolism of sirolimus; must not be taken with or used to dilute sirolimus.
/CASE REPORTS/ Cases of bronchial anastomotic dehiscence, most of which were fatal, have been reported in de novo lung transplant patients who received sirolimus in combination with other immunosuppressants. Because safety and efficacy of sirolimus as immunosuppressive therapy in lung transplant patients have not been established, such use in not recommended by the manufacturer.
/CASE REPORTS/ Use of sirolimus in combination with other immunosuppressants (i.e., cyclosporine, tacrolimus) has been associated with an increased risk on hepatic artery thrombosis, graft loss, and death in de novo liver transplant recipients. Because safety and efficacy of sirolimus as immunosuppressive therapy in liver transplant patients have not been established, such use is not recommended by the manufacturer.
Drug Induced Liver Injury Rank (DILIrank 2.0)
Sirolimus
vLess-DILI-concern
8
Adverse reactions
DOI:10.1016/j.drudis.2016.02.015
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl sirolimus, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Sirolimus inhibits cytokine (Interleukin (IL)-2, IL-4, and IL-15) -- stimulated T lymphocyte activation and proliferation; it also inhibits antibody production. This may occur through formation of an immunosuppressive complex with FK Binding Protein-12 (FKBP-12). Although the sirolimus-(FKBP-12) complex is inactive against calcineurin activity, the complex binds to and inhibits activation of a key regulatory kinase, mammalian Target of Rapamycin (mTOR). This is believed to suppress cytokine-driven T-cell proliferation, inhibiting cell cycle progression from the G, to S phase.
The mean ± SD terminal elimination half-life (t½) of sirolimus after multiple dosing in stable renal transplant patients was estimated to be about 62 ± 16 hours.
The drug has an elimination half life of 57-63 hours in kidney transplant recipients.
Sirolimus undergoes extensive metabolism in the intestinal wall and liver. Sirolimus is primarily metabolized by O-demethylation and/or hydroxylation via CYP3A4 to form seven major metabolites, including hydroxy, demethyl, and hydroxydemethyl metabolites, which are pharmacologically inactive. Sirolimus also undergoes counter-transport from enterocytes of the small intestine into the gut lumen.
Sirolimus is a substrate for both cytochrome P450 IIIA4 (CYP3A4) and P-glycoprotein. Sirolimus is extensively metabolized by O-demethylation and/or hydroxylation. Seven major metabolites, including hydroxy, demethyl, and hydroxydemethyl, are identifiable in whole blood. Some of these metabolites are also detectable in plasma, fecal, and urine samples. Glucuronide and sulfate conjugates are not present in any of the biologic matrices.
Biotransformation: Hepatic, extensive, by cytochrome p450 3A enzymes. Major metabolites include hydroxysirolimus, demethylsirolimus, and hydroxydemethyl-sirolimus.
... After incubation of sirolimus with human and pig small intestinal microsomes, five metabolites were detected using high performance liquid chromatography/electrospray-mass spectrometry: hydroxy, dihydroxy, trihydroxy, desmethyl and didesmethyl sirolimus. The same metabolites were generated by human liver microsomes and pig small intestinal mucosa in the Ussing chamber. Anti-CYP3A antibodies, as well as the specific CYP3A inhibitors troleandomycin and erythromycin, inhibited small intestinal metabolism of sirolimus, confirming that, as in the liver, CYP3A enzymes are responsible for sirolimus metabolism in the small intestine. ...
Sirolimus has known human metabolites that include 16-O-Desmethylsirolimus, 39-O-Desmethylsirolimus, 24-Hydroxy-sirolimus, 11-Hydroxy-sirolimus, 25-Hydroxy-sirolimus, 46-Hydroxy-sirolimus, and 12-Hydroxy-sirolimus.
Half Life: 57-63 hours
W36ZG6FT64
SIROLIMUS
Physiologic Effects [PE] - Decreased Immunologic Activity
Established Pharmacologic Class [EPC] - mTOR Inhibitor Immunosuppressant
Mechanisms of Action [MoA] - mTOR Inhibitors
Established Pharmacologic Class [EPC] - Kinase Inhibitor
Chemical substances, produced by microorganisms, inhibiting or preventing the proliferation of neoplasms.
Substances that destroy fungi by suppressing their ability to grow or reproduce. They differ from FUNGICIDES, INDUSTRIAL because they defend against fungi present in human or animal tissues.
Agents that suppress immune function by one of several mechanisms of action. Classical cytotoxic immunosuppressants act by inhibiting DNA synthesis. Others may act through activation of T-CELLS or by inhibiting the activation of HELPER CELLS. While immunosuppression has been brought about in the past primarily to prevent rejection of transplanted organs, new applications involving mediation of the effects of INTERLEUKINS and other CYTOKINES are emerging.
Substances that inhibit the growth or reproduction of BACTERIA.
In adult renal transplant patients with low- to moderate-immunologic risk, oral administration of 2 mg sirolimus led to a Cmax of 14.4 ± 5.3 ng/mL for oral solution and 15.0 ± 4.9 ng/mL for oral tablets. The tmax was 2.1 ± 0.8 hours for oral solution and 3.5 ± 2.4 hours for oral tablets. In healthy subjects, the tmax is one hour. In a multi-dose study, steady-state was reached six days following repeated twice-daily administration without an initial loading dose, with the average trough concentration of sirolimus increased approximately 2- to 3-fold. It is suspected that a loading dose of three times the maintenance dose will provide near steady-state concentrations within one day in most patients. The systemic availability of sirolimus is approximately 14%. In healthy subjects, the mean bioavailability of sirolimus after administration of the tablet is approximately 27% higher relative to the solution. Sirolimus tablets are not bioequivalent to the solution; however, clinical equivalence has been demonstrated at the 2 mg dose level. Sirolimus concentrations, following the administration of Rapamune Oral Solution to stable renal transplant patients, are dose-proportional between 3 and 12 mg/m2.
Following oral administration of [<sup>14</sup>C] sirolimus in healthy subjects, about 91% of the radioactivity was recovered from feces and only 2.2% of the radioactivity was detected in urine. Some of the metabolites of sirolimus are also detectable in feces and urine.
The mean (± SD) blood-to-plasma ratio of sirolimus was 36 ± 18 L in stable renal allograft patients, indicating that sirolimus is extensively partitioned into formed blood elements. The mean volume of distribution (V<sub>ss/F</sub>) of sirolimus is 12 ± 8 L/kg.
In adult renal transplant patients with low- to moderate-immunologic risk, oral administration of 2 mg sirolimus led to oral clearance of 173 ± 50 mL/h/kg for oral solution and 139 ± 63 mL/h/kg for oral tablets.
Following administration of /Sirolimus/ Oral Solution, sirolimus is rapidly absorbed, with a mean time-to-peak concentration (t max ) of approximately 1 hour after a single dose in healthy subjects and approximately 2 hours after multiple oral doses in renal transplant recipients. The systemic availability of sirolimus was estimated to be approximately 14% after the administration of /Sirolimus/ Oral Solution. The mean bioavailability of sirolimus after administration of the tablet is about 27% higher relative to the oral solution.
In 22 healthy volunteers receiving Rapamune Oral Solution, a high-fat meal altered the bioavailability characteristics of sirolimus. Compared with fasting, a 34% decrease in the peak blood sirolimus concentration (C max ), a 3.5-fold increase in the time-to-peak concentration (t max ), and a 35% increase in total exposure (AUC) was observed. After administration of Rapamune Tablets and a high-fat meal in 24 healthy volunteers, C max , t max , and AUC showed increases of 65%, 32%, and 23%, respectively.
Triene macrolide antibiotic derived from Streptomyces hygroscopicus; Used in immunochemistry research and as a therapeutic immunosuppressant and antirestenotic (blocks reoccurrence of stenosis); [Merck Index]
Tool for immunochemistry.
Medication: Immunosuppressant
Used to prevent rejection in organ transplantation; it is especially useful in kidney transplants. [Wikipedia]
Rapamune
Rapamycin
Oral: Solution 1mg/mL Rapamune (Wyeth). Tablets: 1 mg Rapamune (with povidone), (Wyeth); 2 mg Rapamune (with Povidone), (Wyeth).
Information available in 2004 indicated that Sirolimus was used in the manufacture of pharmaceutical preparations in the following countries: Argentina, Australia, Austria, Belgium, Brazil, Canada, Chile, Colombia, Czech Republic, Denmark, Finland, France, Germany, Greece, Ireland, Israel, Italy, Mexico, New Zealand, Norway, Poland, Romania, Singapore, Spain, Sweden, Switzerland, Thailand, United Kingdom, USA (1,2)
DescriptionRapamycin is a member of the macrolide immunosuppressant family and a FRAP inhibitor. Rapamycin exhibits binding and inhibitory actions to the FK506 binding protein (FKBP5) proline rotamase via simultaneous binding by FKBP12 and FRAP. FRAP (RAFT1) proteins exhibit homology to PI 4- and PI 3-kinases, which have PI 4-kinase and autophosphorylating activities. The rapamycin/FKBP complex does not inhibit the FRAP PI 4-kinase activity, but does inhibit FRAP autophosphorylation. Rapamycin is unique in its ability to inhibit lymphokine induced cell proliferation at the G1 and S phase as well as an irreversible cellular arrest at the G1 phase in S. cerevisiae cells. Rapamycin also exhibits selective signal blocking leading to the activation of p70/85 S6 kinase, which is potentially due to the inhibition of FRAP autophosphorylation or protein kinase activity. Rapamycin also exhibits Angiogenesis inhibition, possibly through the inhibition of the Akt pathway. Rapamycin is an inhibitor of mTOR. Rapamycin is also known as Rapamune, 23,27-Epoxy-3H-pyrido[2,1-c] oxaazacyclohentriacontine, AY 22989, and mTOR Inhibitor I.
OccurrenceRapamycin was first discovered in 1972 in the soil of Easter Island produced by a bacterium called Streptomyces hygroscopicus. It takes its name from Rapa Nui, the indigenous name for the island. It is known clinically as sirolimus or Rapamune.
UsesRapamycin is a triene macrolide discovered in 1995 as a metabolite of Streptomyces hygroscopicus found in a soil obtained on Rapi Nui (Easter Island). Rapamycin displayed potent and selective antifungal activity, notably against Candida albicans. Interest in the metabolite waned until the structural relationship to the potent immunosuppressant fujimycin (Antibiotic FK506) was recognised in the mid-1980s. This recognition led to the re-discovery of rapamycin as a highly selective antitumour and immunosuppressant. Rapamycin inhibits the activity of the protein, mTOR (mammalian target of rapamycin) which functions in a signalling pathway to promote tumour growth. Rapamycin binds to a receptor protein (FKBP12). The rapamycin/FKB12 complex then binds to mTOR and prevents interaction of mTOR with target proteins in this signalling pathway.
UsesRapamycin is a triene macrolide discovered in 1974 as a metabolite of Streptomyces hygroscopicus found in a soil obtained on Rapa Nui (Easter Island). Rapamycin displayed potent and selective antifungal activity, notably against Candida albicans. Interest in the metabolite waned until the structural relationship to the potent immunosuppressant fujimycin (Antibiotic FK506) was recognised in the mid-1980s. This recognition led to the re-discovery of rapamycin as a highly selective antitumor and immunosuppressant. Rapamycin inhibits the activity of the protein, mTOR (mammalian target of rapamycin) which functions in a signalling pathway to promote tumor growth. Rapamycin binds to a receptor protein (FKBP12). The rapamycin/FKB12 complex then binds to mTOR and prevents interaction of mTOR with target proteins in this signalling pathway.
UsesLabelled Rapamycin. A triene macrolide antibiotic isolated from Streptomyces hygroscopicus. Name derived from the native word for Easter Island, RapaNui. Used as an immunosuppressant; antirestenotic. This compound contains aproximately 2% d0.;Labeled Sir
UsesRapamycin is an immunosuppressant that is used primarily to prevent the rejection of organ and bone marrow transplant. It was first described as a potent inhibitor of IL-2 activation of lymphocytes (IC50 = 5 pM). It is now known that rapamycin specifically interacts with the cytosolic FK-binding protein 12 (FKBP12) to form a complex which inhibits the mammalian target of rapamycin (mTOR) pathway by directly binding to mTOR Complex 1 (mTORC1). Rapamycin and other inhibitors of mTORC1 signaling show potential in treating cancer, adipogenesis, diabetes, tuberous sclerosis, and cardiovascular disease.[Cayman Chemical]
General DescriptionRapamycin is an anti-fungal antibiotic isolated from Streptomyces hygroscopicus. This antibiotic is active against all strains of Candida albicans. It blocks the signal transduction pathways required for the activation of T-helper cells.
DefinitionChEBI: A macrolide isolated from Streptomyces hygroscopicus consisting of a 29-membered ring containing 4 trans double bonds, three of which are conjugated. It is an antibiotic, immunosupressive and antineoplastic agent.