
HRID 1296As product
Completing data — refresh the page later to see the latest

27203-92-5COc1cccc(C2(O)CCCCC2CN(C)C)c1TVYLLZQTGLZFBW-UHFFFAOYSA-N2-[(dimethylamino)methyl]-1-(3-methoxyphenyl)cyclohexanol is a tertiary alcohol that is cyclohexanol substituted at positions 1 and 2 by 3-methoxyphenyl and dimethylaminomethyl groups respectively. It is a tertiary alcohol, an aromatic ether and a tertiary amino compound. It is functionally related to a cyclohexanol.
Tramadol modulates the descending pain pathways within the central nervous system through the binding of parent and M1 metabolite to μ-opioid receptors and the weak inhibition of the reuptake of norepinephrine and serotonin. Apart from analgesia, tramadol may produce a constellation of symptoms (including dizziness, somnolence, nausea, constipation, sweating and pruritus) similar to that of other opioids. **Central Nervous System** In contrast to [morphine], tramadol has not been shown to cause histamine release. At therapeutic doses, tramadol has no effect on heart rate, left-ventricular function or cardiac index. Orthostatic hypotension has been observed. Tramadol produces respiratory depression by direct action on brain stem respiratory centres. The respiratory depression involves both a reduction in the responsiveness of the brain stem centres to increases in CO2 tension and to electrical stimulation. Tramadol depresses the cough reflex by a direct effect on the cough centre in the medulla. Antitussive effects may occur with doses lower than those usually required for analgesia. Tramadol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origin may produce similar findings). Marked mydriasis rather than miosis may be seen with hypoxia in the setting of oxycodone overdose. Seizures have been reported in patients receiving tramadol within the recommended dosage range. Spontaneous post-marketing reports indicate that seizure risk is increased with doses of tramadol above the recommended range. Risk of convulsions may also increase in patients with epilepsy, those with a history of seizures or in patients with a recognized risk for seizure (such as head trauma, metabolic disorders, alcohol and drug withdrawal, CNS infections), or with concomitant use of other drugs known to reduce the seizure threshold. Tramadol can cause a rare but potentially life-threatening condition resulting from concomitant administration of serotonergic drugs (e.g., anti-depressants, migraine medications). Treatment with the serotoninergic drug should be discontinued if such events (characterized by clusters of symptoms such as hyperthermia, rigidity, myoclonus, autonomic instability with possible rapid fluctuations of vital signs, mental status changes including confusion, irritability, extreme agitation progressing to delirium and coma) occur and supportive symptomatic treatment should be initiated. Tramadol should not be used in combination with MAO inhibitors or serotonin-precursors (such as L-tryptophan, oxitriptan) and should be used with caution in combination with other serotonergic drugs (triptans, certain tricyclic antidepressants, lithium, St. John’s Wort) due to the risk of serotonin syndrome. **Gastrointestinal Tract and Other Smooth Muscle** Tramadol causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm resulting in constipation. Other opioid-induced effects may include a reduction in gastric, biliary and pancreatic secretions, spasm of the sphincter of Oddi, and transient elevations in serum amylase. **Endocrine System** Opioids may influence the hypothalamic-pituitary-adrenal or -gonadal axes. Some changes that can be seen include an increase in serum prolactin and decreases in plasma cortisol and testosterone. Clinical signs and symptoms may be manifest from these hormonal changes. Hyponatremia has been reported very rarely with the use of tramadol, usually in patients with predisposing risk factors, such as elderly patients and/or patients using concomitant medications that may cause hyponatremia (e.g., antidepressants, benzodiazepines, diuretics). In some reports, hyponatremia appeared to be the result of the syndrome of inappropriate antidiuretic hormone secretion (SIADH) and resolved with discontinuation of tramadol and appropriate treatment (e.g., fluid restriction). During tramadol treatment, monitoring for signs and symptoms of hyponatremia is recommended for patients with predisposing risk factors. **Cardiovascular** Tramadol administration may result in severe hypotension in patients whose ability to maintain adequate blood pressure is compromised by reduced blood volume, or concurrent administration of drugs such as phenothiazines and other tranquillizers, sedative/hypnotics, tricyclic antidepressants or general anesthetics. These patients should be monitored for signs of hypotension after initiating or titrating the dose of tramadol. **QTc-Interval Prolongation** The maximum placebo-adjusted mean change from baseline in the QTcF interval was 5.5 ms in the 400 mg/day treatment arm and 6.5 ms in the 600 mg/day mg treatment arm, both occurring at the 8h time point. Both treatment groups were within the 10 ms threshold for QT prolongation. Post-marketing experience with the use of tramadol containing products included rare reports of QT prolongation reported with an overdose. Particular care should be exercised when administering tramadol to patients who are suspected to be at an increased risk of experiencing torsade de pointes during treatment with a QTc-prolonging drug. **Abuse and Misuse** Like all opioids, tramadol has the potential for abuse and misuse, which can lead to overdose and death. Therefore, tramadol should be prescribed and handled with caution. **Dependence/Tolerance** Physical dependence and tolerance reflect the neuroadaptation of the opioid receptors to chronic exposure to an opioid and are separate and distinct from abuse and addiction. Tolerance, as well as physical dependence, may develop upon repeated administration of opioids, and are not by themselves evidence of an addictive disorder or abuse. Patients on prolonged therapy should be tapered gradually from the drug if it is no longer required for pain control. Withdrawal symptoms may occur following abrupt discontinuation of therapy or upon administration of an opioid antagonist. Some of the symptoms that may be associated with abrupt withdrawal of an opioid analgesic include body aches, diarrhea, gooseflesh, loss of appetite, nausea, nervousness or restlessness, anxiety, runny nose, sneezing, tremors or shivering, stomach cramps, tachycardia, trouble with sleeping, unusual increase in sweating, palpitations, unexplained fever, weakness and yawning.


27203-92-5、2914-77-4DTXSID00860388CHEMBL1237044CHEBI:75722Tramadol is a centrally acting μ-opioid receptor agonist and SNRI (serotonin/norepinephrine reuptake-inhibitor) that is structurally related to [codeine] and [morphine]. Tramadol binds weakly to κ- and δ-opioid receptors and to the μ-opioid receptor with 6000-fold less affinity than morphine. Tramadol exists as a racemic mixture consisting of two pharmacologically active enantiomers that both contribute to its analgesic property through different mechanisms: (+)-tramadol and its primary metabolite (+)-O-desmethyl-tramadol (M1) are agonists of the μ opioid receptor while (+)-tramadol inhibits serotonin reuptake and (-)-tramadol inhibits norepinephrine reuptake. These pathways are complementary and synergistic, improving tramadol's ability to modulate the perception of and response to pain. In animal models, M1 is up to 6 times more potent than tramadol in producing analgesia and 200 times more potent in μ-opioid binding. Tramadol has also been shown to affect a number of pain modulators including alpha2-adrenoreceptors, neurokinin 1 receptors, the voltage-gated sodium channel type II alpha subunit, transient receptor potential cation channel subfamily V member 1 (TRPV1 - also known as the capsaicin receptor), muscarinic receptors (M1 and M3), N-methyl-D-aspartate receptor (also known as the NMDA receptor or glutamate receptor), Adenosine A1 receptors, and nicotinic acetylcholine receptor. In addition to the above neuronal targets, tramadol has a number of effects on inflammatory and immune mediators involved in the pain response. This includes inhibitory effects on cytokines, prostaglandin E2 (PGE2), nuclear factor-κB, and glial cells as well as a change in the polarization state of M1 macrophages.
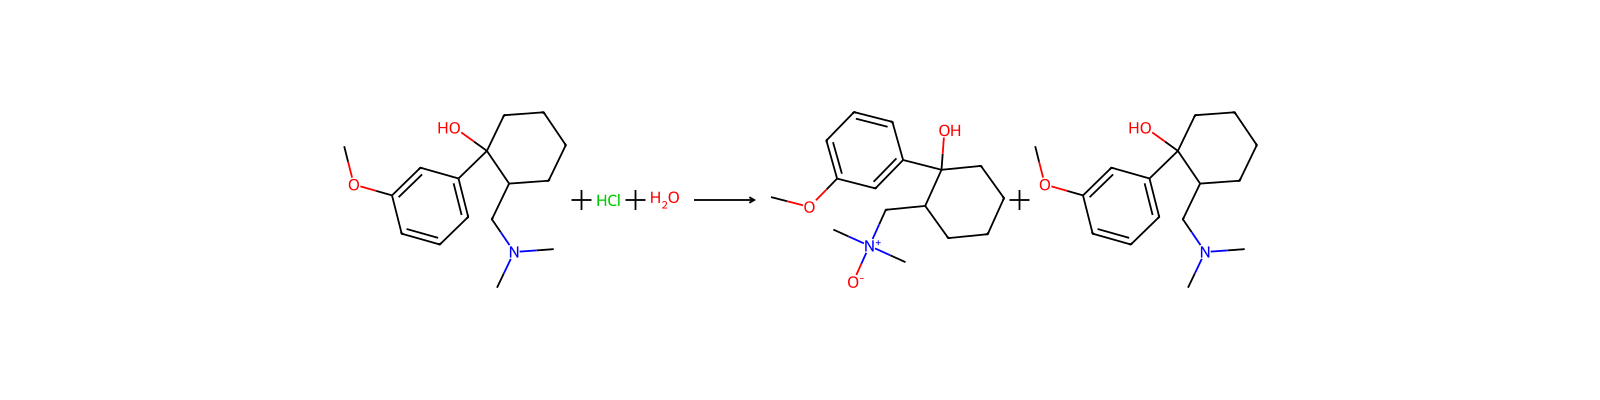
Tramadol undergoes extensive first-pass metabolism in the liver by N- and O- demethylation and conjugation. From the extensive metabolism, there have been identified at least 23 metabolites. There are two main metabolic pathways: the O-demethylation of tramadol to produce O-desmethyl-tramadol (M1) catalyzed by CYP2D6 and the N-demethylation to N-desmethyl-tramadol (M2) catalyzed by CYP3A4 and CYP2B6. The wide variability in the pharmacokinetic properties between patients can partly be ascribed to polymorphisms within the gene for CYP2D6 that determine its enzymatic activity. CYP2D6\*1 is considered the wild-type allele associated with normal enzyme activity and the "extensive metabolizer" phenotype; 90-95% of Caucasians are considered "extensive metabolizers" (with normal CYP2D6 function) while the remaining 5-10% are considered "poor metabolizers" with reduced or non-functioning enzyme. CYP2D6 alleles associated with non-functioning enzyme include *3, *4, *5, and *6 while alleles associated with reduced activity include *9, *10, *17, and *41. Poor metabolizers have reduced activity of the CYP2D6 enzyme and therefore less production of tramadol metabolites M1 and M2, which ultimately results in a reduced analgesic effect as tramadol interacts with the μ-opioid receptor primarily via M1. There are also large differences in the frequency of these alleles between different ethnicities: \*3, \*4, \*5, \*6, and \*41 are more common among Caucasians while \*17 is more common in Africans for example. Compared to 5-10% of Caucasians, only ~1% of Asians are considered poor metabolizers, however Asian populations carry a much higher frequency (51%) of the CYP2D6\*10 allele, which is relatively rare in Caucasian populations and results in higher exposure to tramadol. Some individuals are considered "ultra-rapid metabolizers", such as those carrying CYP2D6 gene duplications (CYP2D6*DUP) or multiplications. These individuals are at risk of intoxication or exaggerated effects of tramadol due to higher concentrations of its active metabolite (M1). The occurrence of this phenotype is seen in approximately 1% to 2% of East Asians (Chinese, Japanese, Korean), 1% to 10% of Caucasians, 3% to 4% of African-Americans, and may be >10% in certain racial/ethnic groups (ie, Oceanian, Northern African, Middle Eastern, Ashkenazi Jews, Puerto Rican). The FDA label recommends avoiding the use of tramadol in these individuals.
**Oral Administration** Tramadol is administered as a racemate, with both the [-] and [+] forms of both tramadol and the M1 metabolite detected in circulation. Following administration, racemic tramadol is rapidly and almost completely absorbed, with a bioavailability of 75%. This difference in absorption and bioavailability can be attributed to the 20-30% first-pass metabolism. Peak plasma concentrations of tramadol and the primary metabolite M1 occur at two and three hours, respectively. Following a single oral dose of 100mg of tramadol, the Cmax was found to be approximately 300μg/L with a Tmax of 1.6-1.9 hours, while metabolite M1 was found to have a Cmax of 55μg/L with a Tmax of 3 hours. Steady-state plasma concentrations of both tramadol and M1 are achieved within two days of dosing. There is no evidence of self-induction. Following multiple oral doses, Cmax is 16% higher and AUC is 36% higher than after a single dose, demonstrating a potential role of saturable first-pass hepatic metabolism in increasing bioavailability. **Intramuscular Administration** Tramadol is rapidly and almost completely absorbed following intramuscular administration. Following injection of 50mg of tramadol, Cmax of 166μg/L was found with a Tmax of 0.75 hours. **Rectal Administration** Following rectal administration with suppositories containing 100mg of tramadol, Cmax of 294μg/L was found with a Tmax of 3.3 hours. The absolute bioavailability was found to be higher than oral administration (77% vs 75%), likely due to reduced first-pass metabolism with rectal administration compared to oral administration.
Tramadol is eliminated primarily through metabolism by the liver and the metabolites are excreted primarily by the kidneys, accounting for 90% of the excretion while the remaining 10% is excreted through feces. Approximately 30% of the dose is excreted in the urine as unchanged drug, whereas 60% of the dose is excreted as metabolites. The mean terminal plasma elimination half-lives of racemic tramadol and racemic M1 are 6.3 ± 1.4 and 7.4 ± 1.4 hours, respectively. The plasma elimination half-life of racemic tramadol increased from approximately six hours to seven hours upon multiple dosing.
The volume of distribution of tramadol is reported to be in the range of 2.6-2.9 L/kg. Tramadol has high tissue affinity; the total volume of distribution after oral administration was 306L and 203L after parenteral administration. Tramadol crosses the blood-brain barrier with peak brain concentrations occurring 10 minutes following oral administration. It also crosses the placental barrier with umbilical concentrations being found to be ~80% of maternal concentrations.
In clinical trials, the clearance rate of tramadol ranged from 3.73 ml/min/kg in renal impairment patients to 8.50 ml/min/kg in healthy adults.
Uses1-(m-Methoxyphenyl)-2-[(dimethylamino)methyl]cyclohexanol-d6 is an intermediate in the synthesis of Tramadol (T712500), an analgesic.
DefinitionChEBI: A tertiary alcohol that is cyclohexanol substituted at positions 1 and 2 by 3-methoxyphenyl and dimethylaminomethyl groups respectively.