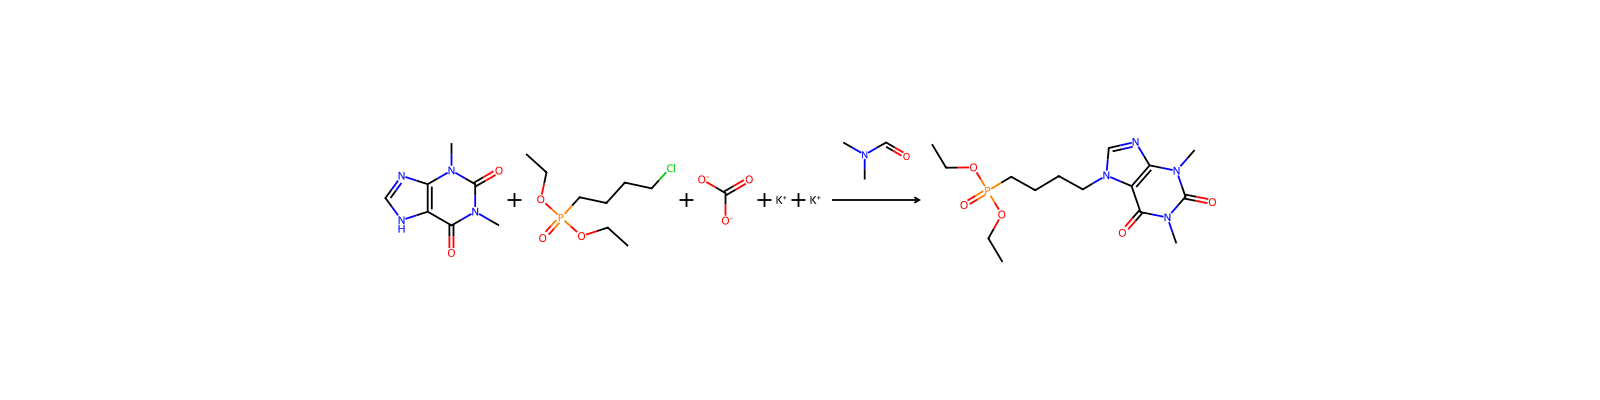

基本情報
- 標準SMILES
Cn1c(=O)c2[nH]cnc2n(C)c1=O- InChIKey
ZFXYFBGIUFBOJW-UHFFFAOYSA-N- 分子式
- C7H8N4O2
- 平均分子量
- 180.16 g/mol
- 単同位体質量
- 180.0647255
概要
Theophylline is an odorless white crystalline powder. Odorless. Bitter taste. (NTP, 1992)
名称と識別子
- 優先名称
- Theophylline
- IUPAC
- 1,3-dimethyl-7H-purine-2,6-dione
- 現地名
- テオフィリン
- 英語名
- Theophylline
- 分子式
- C7H8N4O2
- 分子量
- 180.16
名称と別名
theophylline58-55-91,3-DimethylxanthineElixophyllinTheophyllinTheolairNuelinTheophylline anhydrousElixophyllineLanophyllinPseudotheophyllineRespbid
名称をさらに表示
テオフィリンテオフォルユニコンテオフルマートLアーデフィリンエリクソフィリンヌエリンオプチフィリンアルモフィリンチルミンスロービッド1,3-ジメチルキサンチンプソイドテオフィリンテルダンLテオドリップユニフィルLAテオ-ヅルセキロイドテオシンテオナPTHEOPHYLINE1,3-Dimethyl-3,7-dihydro-1H-purine-2,6-dione1,3-DIMETHYL-7H-PURINE-2,6-DIONE3,7-DIHYDRO-1,3-DIMETHYL-1H-PURINE-2,6-DIONETeofilinaslo-bidtheo-24theobidaerolate
SolosinTheocinTheo-durLiquophyllineOptiphyllinParkophyllinTheofolTheograd
データベース識別子
- CAS
58-55-9、5967-84-0- PubChem CID
- 2153
- DTXSID
DTXSID5021336- ChEMBL
CHEMBL1355736、CHEMBL190- ChEBI
CHEBI:28177- UNII
- 0I55128JYK
- EC Number
- 200-385-7
- Nikkaji
- J2.333G、J492.514I
物性
構造計算による物性
- XLogP
- 0
- 極性表面積
- 69.3 Ų
- 水素結合供与体数
- 1
- 水素結合受容体数
- 3
- 回転可能結合数
- 0
- 重原子数
- 13
- 形式電荷
- 0
- 複雑度
- 267
実験および物理化学的性質
Chemical Classes
Stimulant
Pharmaceutical
Drugs
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Metabolite of Caffeine
Pharmaceuticals
Pharmaceuticals -> Bronchodilators
Cosmetics
Cosmetic ingredients (Theophylline) -> CIR (Cosmetic Ingredient Review)
Tonic
pHA saturated solution in water is faintly acid.
SpringerMaterials PropertiesFusion temperature
LogP
log Kow = - 0.02
-0.02
-0.02 (estimated)
-0.18
OdorOdorless
TasteBitter
Densityg/cm³
Color/Form
White, crystalline alkaloid
White crystalline powder
Needles or plates (water +1)
Solubility
1 to 5 mg/mL at 70.7 °F (NTP, 1992)
In water, 7,360 mg/L at 25 °C
Slightly soluble in water
Slightly soluble in ethanol, ether, chloroform
Slightly soluble in alcohol; more soluble in hot water; soluble in alkaline solutions
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anti-Asthmatic Agents; Bronchodilator Agents
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
物理化学的性質
- 融点
- 271 · 271-273 °C
- 沸点
- 312.97 °C · 312.97°C (rough estimate)
- 比重(密度)
- 1.364 · 1.3640 (rough estimate)
- 屈折率
- 1.67 · 1.6700 (estimate)
- 闪点
- 11 °C · 11 °C
- 貯蔵温度
- 2 · 2-8°C
- 溶解性
- 0.1 M · 0.1 M HCl: 可溶
- 外見
- 粉
- 酸解離定数(Pka)
- 8.77 · 8.77(at 25℃)
- 色
- 白い
- 水溶解度
- 8.3 g/L · 8.3g/L(20℃)
- Merck
- 14 · 14,9285
- BRN
- 13463 · 13463
- Henry's Law Constant
- 5.5 · 5.5×108 mol/(m3Pa) at 25℃, HSDB (2015)
- BCS Class
- 3 · 3,1
- 安定性
- 安定。強力な酸化剤とは相容れない。
- 化粧品成分の機能
- スキンコンディショニング - その他
- InChI
- 1S/C7H8N4O2/c1-10-5-4(8-3-9-5)6(12)11(2)7(10)13/h3H,1-2H3,(H,8,9)
- InChIKey
- ZFXYFBGIUFBOJW-UHFFFAOYSA-N
- SMILES
- CN1C(=O)N(C)c2[nH]cnc2C1=O
- LogP
- -0.02 · -0.020
- CAS データベース
- 58 · 58-55-9(CAS DataBase Reference)
- NISTの化学物質情報
- 1 · 1,3-Dimethylxanthine(58-55-9)
- EPAの化学物質情報
- Theophylline (58-55-9)
化学的性質
化学的特性white to light yellow crystal powder
安全と法規制
GHS分類
GHS Classification
Danger
H360D: May damage the unborn child [Danger Reproductive toxicity]
P203, P280, P318, P405, and P501 (click each P-code to see the statement)
This chemical does not meet GHS hazard criteria for 0.3% (1 of 308) of reports.
Danger
H301 (88%): Toxic if swallowed [Danger Acute toxicity, oral]
危険有害性情報
Regulatory Information
Chemical: 1H-Purine-2,6-dione, 3,7-dihydro-1,3-dimethyl-
Hazard Traits - Reproductive Toxicity
Status: Active Update: 07-04-2023 https://echa.europa.eu/registration-dossier/-/registered-dossier/11172
1H-Purine-2,6-dione, 3,7-dihydro-1,3-dimethyl-: Does not have an individual approval but may be used under an appropriate group standard
Other Safety InformationEvaluation - 1H-Purine-2,6-dione, 3,7-dihydro-1,3-dimethyl- (theophylline)
DOT LabelPoison
Fire Hazards
Flash point data for this chemical are not available, however it is probably combustible. (NTP, 1992)
Not combustible. Gives off irritating or toxic fumes (or gases) in a fire.
Health Hazards
SYMPTOMS: Symptoms of exposure to this compound include nausea, vomiting, epigastric pain, hematemesis, diarrhea, headaches, irritability, restlessness, insomnia, reflex hyperexcitability, muscle twitching, clonic and tonic generalized convulsions, palpitations, tachycardia, extrasystoles, potentiation of diuresis, hyperglycemia, flushing, hypotension, tachypnea, albuminuria, inappropriate ADH secretion and rash. Other symptoms include collapse, a fall in blood pressure; coma, hyperreflexia, ventricular arrythmias including fibrillation, hypotension, respiratory arrest, restlessness, fever, agitation and hyperventilation. It may also cause central nervous system stimulation, nervousness, insomnia, tremors, hyperesthesia, stimulation of the medullary respiratory centers; apnea, emesis, decreases in peripheral vascular resistance; increased perfusion of most organs and death.
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including theophylline, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Drug products containing certain active ingredients offered over-the-counter (OTC) for certain uses. A number of active ingredients have been present in OTC drug products for various uses, as described below. However, based on evidence currently available, there are inadequate data to establish general recognition of the safety and effectiveness of these ingredients for the specified uses: theophylline, anhydrous; theophylline calcium salicylate; and theophylline sodium glycinate are included in bronchodilator drug products.
Drug products containing certain active ingredients offered over-the-counter (OTC) for certain uses. A number of active ingredients have been present in OTC drug products for various uses, as described below. However, based on evidence currently available, there are inadequate data to establish general recognition of the safety and effectiveness of these ingredients for the specified uses: theophylline is included in orally administered menstrual drug products.
Reactive GroupAmides and Imides
UN ClassificationUN Hazard Class: 6.1; UN Pack Group: III
Special Reports
Upton RA; Pharmacokinetic Interactions Between Theophylline and Other Medication (Part I); Clin Pharmacokinet 20 (1): 66-80 (1991).
Parr MJ et al; Theophylline Poisoning -- A Review of 64 Cases; Intensive Care Med 16 (6): 394-8 (1990). Sixty-four cases of theophylline poisoning were reviewed. The results support the use of a management regimen which emphasizes intensive supportive therapy and restricts the use of charcoal hemoperfusion.
Sessler CN; Theophylline Toxicity: Clinical Features of 116 Consecutive Cases; Am J Med 88 (6): 567-76 (1990).
Boreus LO; The Role of Therapeutic Drug Monitoring in Children; Clin Pharmacokinet 17 (1): 4-12 (1989).
For more Special Reports (Complete) data for THEOPHYLLINE (12 total), please visit the HSDB record page.
Reactivity Profile
THEOPHYLLINE neutralizes acids in exothermic reactions to form salts plus water. May be incompatible with isocyanates, halogenated organics, peroxides, phenols (acidic), epoxides, anhydrides, and acid halides. Flammable gaseous hydrogen may be generated in combination with strong reducing agents, such as hydrides.
Chemical DangersDecomposes on heating. This produces toxic fumes including nitrogen oxides.
Packaging and LabellingDo not transport with food and feedstuffs.
安全と保護具
Fire Fighting
Fires involving this compound can be controlled using a dry chemical, carbon dioxide or Halon extinguisher. (NTP, 1992)
In case of fire in the surroundings, use appropriate extinguishing media.
First Aid Measures
Fresh air, rest.
Remove contaminated clothes. Rinse skin with plenty of water or shower.
Rinse with plenty of water for several minutes (remove contact lenses if easily possible).
Rinse mouth. Give a slurry of activated charcoal in water to drink. Refer for medical attention .
First Aid
EYES: First check the victim for contact lenses and remove if present. Flush victim's eyes with water or normal saline solution for 20 to 30 minutes while simultaneously calling a hospital or poison control center. Do not put any ointments, oils, or medication in the victim's eyes without specific instructions from a physician. If symptoms (such as redness or irritation) develop, immediately transport the victim to a hospital.
Safe StorageSeparated from food and feedstuffs.
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical, or carbon dioxide.
Advice for firefighters: Wear self-contained breathing apparatus for firefighting if necessary.
Storage Conditions
Store at 20 deg -25 °C (68 deg - 77 °F); excursions permitted between 15 deg - 30 °C (59 deg - 86 °F).
Keep container tightly closed in a dry and well-ventilated place. Storage class (TRGS 510): Non-combustible, acute toxic Cat.3 / toxic hazardous materials or hazardous materials causing chronic effects.
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Wear respiratory protection. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Evacuate personnel to safe areas. Avoid breathing dust. Environmental precautions: Prevent further leakage or spillage if safe to do so. Do not let product enter drains. Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal.
Nonfire Spill Response
SMALL SPILLS AND LEAKAGE: If you spill this chemical, you should dampen the solid spill material with water, then transfer the dampened material to a suitable container. Use absorbent paper dampened with water to pick up any remaining material. Seal your contaminated clothing and the absorbent paper in a vapor-tight plastic bag for eventual disposal. Wash all contaminated surfaces with a soap and water solution. Do not reenter the contaminated area until the Safety Officer (or other responsible person) has verified that the area has been properly cleaned.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company. Contact a licensed professional waste disposal service to dispose of this material. Dissolve or mix the material with a combustible solvent and burn in a chemical incinerator equipped with an afterburner and scrubber; Contaminated packaging: Dispose of as unused product.
Spillage Disposal
Personal protection: particulate filter respirator adapted to the airborne concentration of the substance. Sweep spilled substance into sealable containers. If appropriate, moisten first to prevent dusting. Then store and dispose of according to local regulations.
Preventive Measures
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Wear respiratory protection. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Evacuate personnel to safe areas. Avoid breathing dust. Environmental precautions: Prevent further leakage or spillage if safe to do so. Do not let product enter drains.
Precautions for safe handling: Avoid contact with skin and eyes. Avoid formation of dust and aerosols. Further processing of solid materials may result in the formation of combustible dusts. The potential for combustible dust formation should be taken into consideration before additional processing occurs. Provide appropriate exhaust ventilation at places where dust is formed.
Appropriate engineering controls: Avoid contact with skin, eyes and clothing. Wash hands before breaks and immediately after handling the product.
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands.
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Isolation and EvacuationExcerpt from ERG Guide 151 [Substances - Toxic (Non-Combustible)]:
毒性情報
Interactions
Theophylline interacts with a wide variety of drugs. The interaction may be pharmacodynamic, i.e., alterations in the therapeutic response to theophylline or another drug or occurrence of adverse effects without a change in serum theophylline concentration. More frequently, however, the interaction is pharmacokinetic, i.e., the rate of theophylline clearance is altered by another drug resulting in increased or decreased serum theophylline concentrations. Theophylline only rarely alters the pharmacokinetics of other drugs. The drugs listed in Table have the potential to produce clinically significant pharmacodynamic or pharmacokinetic interactions with theophylline. The information in the "Effect" column of Table assumes that the interacting drug is being added to a steady-state theophylline regimen. If theophylline is being initiated in a patient who is already taking a drug that inhibits theophylline clearance (e.g., cimetidine, erythromycin), the dose of theophylline required to achieve a therapeutic serum theophylline concentration will be smaller. Conversely, if theophylline is being initiated in a patient who is already taking a drug that enhances theophylline clearance (e.g., rifampin), the dose of theophylline required to achieve a therapeutic serum theophylline concentration will be larger. Discontinuation of a concomitant drug that increases theophylline clearance will result in accumulation of theophylline to potentially toxic levels, unless the theophylline dose is appropriately reduced. Discontinuation of a concomitant drug that inhibits theophylline clearance will result in decreased serum theophylline concentrations, unless the theophylline dose is appropriately increased.
Cimetidine, high-dose allopurinol (e.g., 600 mg daily), oral contraceptives, propranolol, ciprofloxacin, erythromycin, and troleandomycin may increase serum theophylline concentrations by decreasing theophylline's hepatic clearance.
Methotrexate may decrease clearance of theophylline; plasma theophylline concentrations should be monitored in patients receiving theophylline concomitantly with methotrexate.
Rifampin may decrease serum theophylline concentrations by increasing theophylline's hepatic clearance.
For more Interactions (Complete) data for THEOPHYLLINE (19 total), please visit the HSDB record page.
Hepatotoxicity
Prospective studies have shown that ALT elevations occur in less than 1% of patients receiving long term oral therapy with theophylline, making it unlikely that such elevations are more common than might occur by chance. No instances of clinically apparent liver injury have been convincingly linked to theophylline use. Liver injury may occur as a part of generalized toxicity from high doses of theophylline probably as a result of hepatic complications of hypotension or anoxia from seizures or cardiac arrhythmias caused by the drug. Theophylline actually has been shown to attenuate several forms of experimental acute liver injury, and chronic caffeine (another xanthine) intake has been associated with decreased rates of chronic liver disease, cirrhosis and liver cancer.
Ecotoxicity Values
LC50; Species: Streptocephalus proboscideus (Fairy Shrimp); Conditions: freshwater; Concentration: 2360 umol/L for 24 hr /97->99% purity/
LC50; Species: Artemia salina (Brine Shrimp); Conditions: saltwater; Concentration: 45800 umol/L for 24 hr /97->99% purity/
EC50; Species: Daphnia pulex (Water Flea) age <24 hr; Conditions: freshwater, static, 20 °C, pH 7.6; Concentration: 1.82 mM for 24 hr; Effect: intoxication, immobilization /formulation/
EC50; Species: Daphnia magna (Water Flea) age <24 hr neonate; Conditions: freshwater, static, 21 °C, pH 7.6; Concentration: 0.861 mM for 24 hr; Effect: intoxication, immobilization
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 10(SRC), determined from a structure estimation method(2), indicates that theophylline is expected to have very high mobility in soil(SRC). The pKa of theophylline is 8.81(3), indicating that this compound will exist partially in the cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization of the neutral species of theophylline from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 1.8X10⁻¹⁴ atm-cu m/mole(SRC), using a fragment constant estimation method(5). Theophylline is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 5.1X10⁻⁹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2). Theophylline has been categorized as readily biodegradable in screening tests(6), suggesting that biodegradation may be an important environmental fate process in soil(SRC).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 10(SRC), determined from a structure estimation method(2), indicates that theophylline is not expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(3) based upon an estimated Henry's Law constant of 1.8X10⁻¹⁴ atm-cu m/mole(SRC), developed using a fragment constant estimation method(4). According to a classification scheme(5), an estimated BCF of 3(SRC), from its log Kow of 0.02(6) and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is low(SRC). Theophylline has been categorized as readily biodegradable in screening tests(7), suggesting that biodegradation may be an important environmental fate process in water(SRC).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), theophylline, which has an estimated vapor pressure of 5.1X10⁻¹⁹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase theophylline may be removed from the air by wet and dry deposition(SRC). Theophylline contains chromophores that absorb at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Food Survey ValuesTheophylline occurrence in plants(1).[Table#4567]
Adverse Effects
Theophylline has a very narrow therapeutic window, and its interaction with various other drugs has led to the limitation of its use. The serum theophylline concentrations require monitoring directly to avoid toxicity as the adverse effects of theophylline are related to its plasma concentration and have been observed when plasma concentrations exceed 20 mg/L. Some patients have also experienced adverse effects at low plasma concentrations. The dose gradually increases until achieving therapeutic plasma concentrations. This approach reduces side effects.
Exposure Routes
The substance can be absorbed into the body in hazardous amounts by ingestion.
Theophylline is rapidly and completely absorbed after oral administration in solution or immediate-release solid oral dosage form.
Toxicity Summary
Safe in the present practices of use and concentration. Ingredient, concentration, and use information are available in documents discoverable at https://cir-reports.cir-safety.org
IDENTIFICATION AND USE: Theophylline is a white, crystalline alkaloid. It is used as bronchodilator agent. Theophylline is an old drug experiencing a renaissance owing to its beneficial antiinflammatory effects in chronic respiratory diseases, such as asthma and chronic obstructive pulmonary disease. HUMAN EXPOSURE AND TOXICITY: Theophylline has a low therapeutic index. Theophylline toxicity is most likely to occur when serum concentrations exceed 20 ug/mL and becomes progressively more severe at higher serum concentrations. Tachycardia, in the absence of hypoxia, fever, or administration of sympathomimetic drugs, may be an indication of theophylline toxicity. Anorexia, nausea and occasional vomiting, diarrhea, insomnia, irritability, restlessness, and headache commonly occur. Other symptoms of toxicity may include agitated maniacal behavior, frequent vomiting, extreme thirst, slight fever, tinnitus, palpitation, and arrhythmias, delirium, muscle twitching, severe dehydration, albuminuria, emesis of a "coffee ground" material, hyperthermia, and profuse diaphoresis. Seizures may occur even without other preceding symptoms of toxicity and often result in death. Fatalities in adults have generally occurred during or following IV administration of large doses of aminophylline in patients with renal, hepatic, or cardiovascular complications. In other patients, the rapidity of the injection, rather than the dose used, appears to be the more important factor precipitating acute hypotension, seizures, coma, cardiac standstill, ventricular fibrillation, and death. IV theophylline should therefore be given slowly. In children, fatalities usually are a result of overdosage and marked sensitivity to the CNS stimulation of theophylline. Acute single overdose is usually a result of a suicide attempt or accidental childhood ingestion but may also be caused by accidental or iatrogenic misuse (therapeutic overdose). Usual manifestations include vomiting (sometimes with hematemesis), tremor, anxiety, and tachycardia. Metabolic effects include pronounced hypokalemia, hypophosphatemia, hyperglycemia, and metabolic acidoses. With serum levels above 90-100 mg/L, hypotension, ventricular arrhythmias, and seizures are common; status epilepticus is frequently resistant to anticonvulsant drugs. Seizures and other manifestations of severe toxicity may be delayed 12-16 hr or more after ingestion, in part owing to delayed absorption of drug from sustained-release preparations. Theophylline also inhibited DNA synthesis in human fibroblastoid EUE cells, and the shape of the dose-response curves and the absence of theophylline-induced DNA strand breaks indicated that theophylline does not directly damage the DNA but acts as a metabolic inhibitor. The results of a study with synchronized HeLa S3 cells exposed to theophylline indicate that the block in DNA replication results from inhibition of histone 1 phosphorylation, which prevents the normal release of chromatin structure between G1 and S phases. ANIMAL STUDIES: In tests performed in rabbits, undiluted theophylline induced mean scores of 0.6 for cornea opacity, 1.8 for conjunctival redness, and 0.6 for swelling. On day 8, one of 3 animals showed opacity grade 1 and conjunctivitis grade 2. The animal showing slight corneal opacity had also keratitis. The effects could possibly be due to mechanical irritation by the crystalline test substance. A single oral dose of 400 mg/kg bw theophylline was acutely toxic to rats and mice. Administration of the same daily dose as two separate doses of 200 mg/kg bw was acutely toxic to rats but not to mice. In dogs, the minimal oral toxic concentration of theophylline appears to be higher (37-60 ug/mL plasma) than in man ( > 20 g/mL). Theophylline has been reported to be more toxic than caffeine or theobromine to the heart, bronchi and kidneys. Groups of female mice 25 days of age, received a single subcutaneous injection of 0.1 mg/g bw urethane followed immediately by seven intraperitoneal injections (0.05 umol/g bw) of theophylline at 6-hr intervals up to 36 hr after urethane treatment, to give a total dose of 63 ug/g bw theophylline. Mice were killed five months after urethane treatment. No significant difference was noted in the numbers of mice with lung tumors or in the numbers of tumors/lung. In a reproductive study, mice were administered 0.075, 0.15 or 0.30% theophylline in the diet (average daily doses, 125, 265 or 530 mg/kg bw) for one week before mating and during 13 weeks of cohabitation. Among all treated groups, there was a dose-related decrease in the number of live pups per litter; in the high-dose groups, there was a significant decrease in the number of litters per breeding pair and a significant decrease in live pup weight. In the high- and mid-dose groups, a significant decrease in the percentage of pups born alive was observed. Only mild toxicity was observed in adults at these doses. In a cross-over mating trial at the end of a 19-week exposure to 0.3% theophylline, animals of each sex were found to be affected, although females were more severely affected than males. Feeding theophylline to immature (five to six weeks old) rats at 0.5% in the diet (approximately 300 mg/kg bw per day) for 75 weeks produced severe testicular atrophy in 50% of animals, oligo-spermatogenesis and aspermatogenesis. Theophylline has been studied in Ames Salmonella test, in vivo and in vitro cytogenetics, micronucleus and Chinese hamster ovary test systems and has not been shown to be genotoxic.
As with other methylxanthines, theophylline toxicity can lead to gastrointestinal distress, insomnia, and tremor. Reports also exist of severe nausea and vomiting, cardiac arrhythmias, hypotension, and convulsions, more commonly in cases of overdosage. Very large overdoses, such as those during suicide attempts, could potentially be lethal because of the development of arrhythmias and convulsions.
Theophylline relaxes the smooth muscle of the bronchial airways and pulmonary blood vessels and reduces airway responsiveness to histamine, methacholine, adenosine, and allergen. Theophylline competitively inhibits type III and type IV phosphodiesterase (PDE), the enzyme responsible for breaking down cyclic AMP in smooth muscle cells, possibly resulting in bronchodilation. Theophylline also binds to the adenosine A2B receptor and blocks adenosine mediated bronchoconstriction. In inflammatory states, theophylline activates histone deacetylase to prevent transcription of inflammatory genes that require the acetylation of histones for transcription to begin.
Signs and Symptoms
See Ingestion.
Headache. Nausea. Vomiting. Irritability. Palpitations. Convulsions.
Symptoms of overdose include seizures, arrhythmias, and GI effects.
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of July 7, 2016: http://actor.epa.gov/dashboard/]
The following link will take the user to the National Toxicology Program (NTP) Test Agent Search Results page, which tabulates all of the "Standard Toxicology & Carcinogenesis Studies", "Developmental Studies", and "Genetic Toxicity Studies" performed with this chemical. Clicking on the "Testing Status" link will take the user to the status (i.e., in review, in progress, in preparation, on test, completed, etc.) and results of all the studies that the NTP has done on this chemical.[Available from: http://ntp-apps.niehs.nih.gov/ntp_tox/index.cfm?fuseaction=ntpsearch.searchresults&searchterm=58-55-9]
Effluent ConcentrationsTheophylline has been reported in final effluent water samples from wastewater treatment plants the UK at a range of 1,220-3,169 ng/L. Influent concentrations ranged from 9,467-20,400, indicating a >80% treatment removal(1).
Soil Adsorption/Mobility
Using a structure estimation method based on molecular connectivity indices(1), the Koc of theophylline can be estimated to be 10(SRC). According to a classification scheme(2), this estimated Koc value suggests that theophylline is expected to have very high mobility in soil. The pKa of theophylline is 8.81(3), indicating that this compound will exist partially in the cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4).
法規制情報
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including theophylline, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Drug products containing certain active ingredients offered over-the-counter (OTC) for certain uses. A number of active ingredients have been present in OTC drug products for various uses, as described below. However, based on evidence currently available, there are inadequate data to establish general recognition of the safety and effectiveness of these ingredients for the specified uses: theophylline, anhydrous; theophylline calcium salicylate; and theophylline sodium glycinate are included in bronchodilator drug products.
Drug products containing certain active ingredients offered over-the-counter (OTC) for certain uses. A number of active ingredients have been present in OTC drug products for various uses, as described below. However, based on evidence currently available, there are inadequate data to establish general recognition of the safety and effectiveness of these ingredients for the specified uses: theophylline is included in orally administered menstrual drug products.
安全データ
- F
- 10-23
- wgk
- 1
- tsca
- TSCA listed
- rtecs
- XH3850000
- ridadr
- UN 2811 6.1/PG 3
- 毒性
- LD50 oral in rabbit: 350mg/kg
- hs_code
- 29395900
- risk_code
- 22-39/23/24/25-23/24/25-11-36/37/38
- hazard_code
- Xn,T,F,Xi
- safety_code
- 7-16-36/37-45-36-26-24/25
- hazard_class
- 6.1(b)
- packing_group
- III
- Hazard Classifications
- Acute Tox. 3 OralRepr. 1B
- ストレージクラス
- 6.1C - Combustible acute toxic Cat.3toxic compounds or compounds which causing chronic effects
- 有毒物質データの
- 58-55-9(Hazardous Substances Data)
化学と産業
薬理情報
ATC Code
R03DA04
R - Respiratory system
QR - Respiratory system
Protein Binding40%, primarily to albumin.
Pharmacodynamics
Theophylline, an xanthine derivative chemically similar to caffeine and theobromine, is used to treat asthma and bronchospasm. Theophylline has two distinct actions in the airways of patients with reversible (asthmatic) obstruction; smooth muscle relaxation (i.e., bronchodilation) and suppression of the response of the airways to stimuli (i.e., non-bronchodilator prophylactic effects).
Mechanism of Action
Theophylline relaxes the smooth muscle of the bronchial airways and pulmonary blood vessels and reduces airway responsiveness to histamine, methacholine, adenosine, and allergen. Theophylline competitively inhibits type III and type IV phosphodiesterase (PDE), the enzyme responsible for breaking down cyclic AMP in smooth muscle cells, possibly resulting in bronchodilation. Theophylline also binds to the adenosine A2B receptor and blocks adenosine mediated bronchoconstriction. In inflammatory states, theophylline activates histone deacetylase to prevent transcription of inflammatory genes that require the acetylation of histones for transcription to begin.
Theophylline is an old drug experiencing a renaissance owing to its beneficial antiinflammatory effects in chronic respiratory diseases, such as asthma and chronic obstructive pulmonary disease. Multiple modes of antiinflammatory action have been reported, including inhibition of the enzymes that degrade cAMP-phosphodiesterase (PDE). Using primary cultures of airway smooth muscle (ASM) cells, we recently revealed that PDE4 inhibitors can potentiate the antiinflammatory action of beta2-agonists by augmenting cAMP-dependent expression of the phosphatase that deactivates mitogen-activated protein kinase (MAPK)-MAPK phosphatase (MKP)-1. Therefore, the aim of this study was to address whether theophylline repressed cytokine production in a similar, PDE-dependent, MKP-1-mediated manner. Notably, theophylline did not potentiate cAMP release from ASM cells treated with the long-acting beta2-agonist formoterol. Moreover, theophylline (0.1-10 uM) did not increase formoterol-induced MKP-1 messenger RNA expression nor protein up-regulation, consistent with the lack of cAMP generation. However, theophylline (at 10 uM) was antiinflammatory and repressed secretion of the neutrophil chemoattractant cytokine IL-8, which is produced in response to TNF-a. Because theophylline's effects were independent of PDE4 inhibition or antiinflammatory MKP-1, we then wished to elucidate the novel mechanisms responsible. We investigated the impact of theophylline on protein phosphatase (PP) 2A, a master controller of multiple inflammatory signaling pathways, and show that theophylline increases TNF-a-induced PP2A activity in ASM cells. Confirmatory results were obtained in A549 lung epithelial cells. PP2A activators have beneficial effects in ex vivo and in vivo models of respiratory disease. Thus, our study is the first to link theophylline with PP2A activation as a novel mechanism to control respiratory inflammation.
Theophylline has two distinct actions in the airways of patients with reversible obstruction; smooth muscle relaxation (i.e., bronchodilation) and suppression of the response of the airways to stimuli (i.e., non-bronchodilator prophylactic effects). While the mechanisms of action of theophylline are not known with certainty, studies in animals suggest that bronchodilatation is mediated by the inhibition of two isozymes of phosphodiesterase (PDE III and, to a lesser extent, PDE IV) while non-bronchodilator prophylactic actions are probably mediated through one or more different molecular mechanisms, that do not involve inhibition of PDE III or antagonism of adenosine receptors. Some of the adverse effects associated with theophylline appear to be mediated by inhibition of PDE III (e.g., hypotension, tachycardia, headache, and emesis) and adenosine receptor antagonism (e.g., alterations in cerebral blood flow). Theophylline increases the force of contraction of diaphragmatic muscles. This action appears to be due to enhancement of calcium uptake through an adenosine-mediated channel.
Lung deflation and inflation during cardiac surgery with cardiopulmonary bypass contributes to pulmonary dysfunction postoperatively. Theophylline treatment for lung diseases has traditionally been thought to act by phosphodiesterase inhibition; however, increasing evidence has suggested other plausible mechanisms. We investigated the effects of deflation and reinflation on signaling pathways (p38-mitogen-activated protein kinase [MAPK], extracellular signal-regulated kinase 1 and 2 [ERK1/2], and Akt) and whether theophylline influences the deflation-induced lung injury and associated signaling. Isolated rat lungs were perfused (15 mL/min) with deoxygenated rat blood in bicarbonate buffer and ventilated. After 20 minutes' equilibration, the lungs were deflated (60 minutes, aerobic perfusion 1.5 mL/min), followed by reinflation (60 minutes, anaerobic reperfusion 15 mL/min). Compliance, vascular resistance, and kinase phosphorylation were assessed during deflation and reinflation. The effects of SB203580 (50 uM), a p38-MAPK inhibitor, and theophylline (0.083 mM [therapeutic] or 3 mM [supratherapeutic]) on physiology and signaling were studied. Deflation reduced compliance by 44% compared with continuously ventilated lungs. p38-MAPK and Akt phosphorylation increased (three to fivefold) during deflation and reinflation, and ERK1/2 phosphorylation increased (approximately twofold) during reinflation. SB203580 had no effect on lung physiology or ERK1/2 and Akt activation. Both theophylline doses increased cyclic adenosine monophosphate, but only 3 mM theophylline improved compliance. p38-MAPK phosphorylation was not affected by theophylline; 0.083 mM theophylline inhibited reinflation-induced ERK1/2 phosphorylation (72% + or - 3%); and 3 mM theophylline inhibited Akt phosphorylation during deflation (75% + or - 5%) and reinflation (87% + or - 4%). Lung deflation and reinflation stimulates differential p38-MAPK, ERK1/2, and Akt activation, suggesting a role in lung injury during cardiopulmonary bypass. However, p38-MAPK was not involved in the compromised compliance. A supratherapeutic theophylline dose protected lungs against deflation-induced injury and was associated with inhibition of phosphoinositide 3-kinase/Akt rather than phosphodiesterase.
Theophylline and aminophylline have been widely used as inhibitors of phosphodiesterase when examining the role of cAMP in regulating cell function. In reality, however, these phosphodiesterase inhibitors may have additional sites of action that could complicate the interpretation of the results. These additional sites of action could include antagonism of inhibitory adenosine autoreceptors and release of intracellular calcium. The purpose of the present study was to determine which of the above three is the primary mechanism by which theophylline and aminophylline affect transmitter release at the mammalian neuromuscular junction. Quantal release measurements were made using intracellular recording techniques. A variety of drugs were used to elucidate this pathway. Isoproterenol, an adenylate cyclase activator, was first used to establish the effect of enhanced levels of cAMP. Theophylline application on its own or in the presence of a drug combination that blocked the adenosine receptor and phosphodiesterase pathways caused significant release depression, opposite to what is expected if it was functioning to enhance cAMP levels. However, when applied in the presence of a drug combination that blocked the adenosine receptor, phosphodiesterase and intracellular ryanodine calcium pathways, theophylline was unable to depress release. Therefore, it was concluded that the major mechanism of action of theophylline is depression of transmitter release by causing the release of intracellular calcium. Aminophylline application alone resulted in a significant enhancement of release. However, when coupled with an adenosine receptor blocker, the ability of aminophylline to enhance transmitter release was blocked, suggesting that its dominant mechanism of action is adenosine receptor inhibition. Taken together, these results indicate that the use of theophylline and aminophylline is inappropriate when examining the role of cAMP at the mammalian neuromuscular junction.
Biological Half-Life
8 hours
In maintenance-dose theophylline schedules, serum concentrations among patients vary at least sixfold and serum half-lives exhibit wide interpatient variation because of differences in rate of metabolism. Serum half lives ranges from about 3-12.8 (average 7-9) hours in otherwise healthy, nonsmoking asthmatic adults, from about 1.5-9.5 hours in children, and from about 15-58 hours in premature infants. ... When compared with that of otherwise healthy, nonsmoking asthmatic adults, the serum half life of theophylline may be increased and total body clearance decreased in patients with congestive heart failure, chronic obstructive pulmonary disease, cor pulmonale, or liver disease, and in geriatric patients. In cigarette and/or marijuana smokers, theophylline serum half life averages 4-5 hours and total body clearance is increased compared with nonsmokers.
Theophylline is distributed rapidly within the body, and plasma half-times were 5.7-11.5 hr in dogs, 11 hr in pigs, 7.8 hr in cats, 3.8-5.5 hr in rabbits and 1.2-4 hr in rats. At higher doses, rats had longer half-times probably because of a combination of increased diuresis and saturation of the metabolism.
Metabolism/Metabolites
Hepatic. Biotransformation takes place through demethylation to 1-methylxanthine and 3-methylxanthine and hydroxylation to 1,3-dimethyluric acid. 1-methylxanthine is further hydroxylated, by xanthine oxidase, to 1-methyluric acid. About 6% of a theophylline dose is N-methylated to caffeine. Caffeine and 3-methylxanthine are the only theophylline metabolites with pharmacologic activity.
Both the N-demethylation and hydroxylation pathways of theophylline biotransformation are capacity-limited. Due to the wide intersubject variability of the rate of theophylline metabolism, non-linearity of elimination may begin in some patients at serum theophylline concentrations <10 ug/mL. Since this non-linearity results in more than proportional changes in serum theophylline concentrations with changes in dose, it is advisable to make increases or decreases in dose in small increments in order to achieve desired changes in serum theophylline concentrations. Accurate prediction of dose-dependency of theophylline metabolism in patients a priori is not possible, but patients with very high initial clearance rates (i.e., low steady-state serum theophylline concentrations at above average doses) have the greatest likelihood of experiencing large changes in serum theophylline concentration in response to dosage changes.
Caffeine and 3-methylxanthine are the only theophylline metabolites with pharmacologic activity. 3-methylxanthine has approximately one tenth the pharmacologic activity of theophylline and serum concentrations in adults with normal renal function are <1 ug/mL. In patients with end-stage renal disease, 3-methylxanthine may accumulate to concentrations that approximate the unmetabolized theophylline concentration. Caffeine concentrations are usually undetectable in adults regardless of renal function. In neonates, caffeine may accumulate to concentrations that approximate the unmetabolized theophylline concentration and thus, exert a pharmacologic effect.
Theophylline is metabolized by the liver to 1,3-dimethyluric acid, 1-methyluric acid, and 3-methylxanthine. ... Individuals metabolize theophylline at different rates; however, individual metabolism of the drug is generally reproducible. Theophylline and its metabolites are excreted mainly by the kidneys. Renal clearance of the drug, however, contributes only 8-12% of the overall plasma clearance of theophylline. Small amounts of theophylline are excreted in feces unchanged.
Unchanged theophylline (35% of urinary radioactivity) and 1,3-dimethyluric acid (34%) are the main compounds excreted in urine, followed by 1-methyluric acid (18%), 3-methylxanthine (3%) and unidentified polar metabolites (4.8%). Theophylline metabolism was impaired in rats at day 18 of gestation, as shown by increased excretion of theophylline (73%); this was explained by a decreased formation of 1,3-dimethyluric acid (-68%) and 1-methyluric acid (-30%). Essentially similar results were obtained with pregnant baboons. Each animal species is characterized by differences in the profile of the metabolites recovered in urine; in addition, quantitative differences in theophylline metabolic pathways were seen even in different strains of mice.
For more Metabolism/Metabolites (Complete) data for THEOPHYLLINE (7 total), please visit the HSDB record page.
FDA Pharmacological Classification
0I55128JYK
THEOPHYLLINE ANHYDROUS
Established Pharmacologic Class [EPC] - Methylxanthine
Chemical Structure [CS] - Xanthines
Theophylline anhydrous is a Methylxanthine.
THEOPHYLLINE
MeSH Pharmacological Classification
Agents that cause an increase in the expansion of a bronchus or bronchial tubes.
Compounds which inhibit or antagonize the biosynthesis or actions of phosphodiesterases.
Drugs used to cause dilation of the blood vessels.
Compounds that bind to and block the stimulation of PURINERGIC P1 RECEPTORS.
Absorption, Distribution and Excretion
Theophylline is rapidly and completely absorbed after oral administration in solution or immediate-release solid oral dosage form.
Theophylline does not undergo any appreciable pre-systemic elimination, distributes freely into fat-free tissues and is extensively metabolized in the liver. Renal excretion of unchanged theophylline in neonates amounts to about 50% of the dose, compared to about 10% in children older than three months and in adults.
0.3 to 0.7 L/kg
0.29 mL/kg/min [Premature neonates, postnatal age 3-15 days]
When administered IM, theophylline is usually absorbed slowly and incompletely. Rectal suppositories (no longer commercially available in the US) are slowly and erratically absorbed, regardless of whether the suppository base is hydrophilic or lipophilic.
In neonates, approximately 50% of the theophylline dose is excreted unchanged in the urine. Beyond the first three months of life, approximately 10% of the theophylline dose is excreted unchanged in the urine.
Tissue LocationsAdipose Tissue
Cellular LocationsCytoplasm
Metabolite PathwaysCaffeine Metabolism
用途と製造
Uses
CIR ingredient: Theophylline
MEDICATION (VET)
MEDICATION
Theophylline is an old drug experiencing a renaissance owing to its beneficial antiinflammatory effects in chronic respiratory diseases, such as asthma and chronic obstructive pulmonary disease. Multiple modes of antiinflammatory action have been reported, including inhibition of the enzymes that degrade cAMP-phosphodiesterase (PDE).
Bronchodilator Agents; Phosphodiesterase Inhibitors; Purinergic P1 Receptor Antagonists; Vasodilator Agents
Use (kg; approx.) in Germany (2009): >250
U.S. Production
1H-Purine-2,6-dione, 3,7-dihydro-1,3-dimethyl- is listed as a High Production Volume (HPV) chemical (65FR81686). Chemicals listed as HPV were produced in or imported into the U.S. in >1 million pounds in 1990 and/or 1994. The HPV list is based on the 1990 Inventory Update Rule. (IUR) (40 CFR part 710 subpart B; 51FR21438).
Methods of Manufacturing
Present in tea but in too small an amount to make it an economical source. It has been made from caffeine but is produced more successfully by total synthesis.
By extraction from tea leaves, synthetically from ethyl cyanoacetate.
Formulations/Preparations
Grade: Technical, NF /National Formulary/.
Oxtriphylline, also called choline theophyllinate contains 64% anhydrous theophylline ... elixir and tablets are available. /Oxtriphylline/
Table: Theophylline (Anhydrous) Preparations [Table#4568]
Table: Theophylline (Anhydrous) in Dextrose Preparations [Table#4569]
Table: Theophylline and Guaifenesin Preparations [Table#4570]
Use Classification
Pharmaceuticals -> Animal Drugs -> Approved in Taiwan
Natural products -> Stimulants -> Respiratory system -> Transformation products
Cosmetics -> Tonic
General Manufacturing Information1H-Purine-2,6-dione, 3,9-dihydro-1,3-dimethyl-: ACTIVE
応用分野
解説テオフィリン,無色の針状晶.融点270~274 ℃.pKa 8.77(25 ℃).昇華性がある.酸やアルカリに可溶,アルコール類に微溶,エーテルに不溶.N-メチル化によりカフェインとなる.利尿薬として使われるが,その作用はテオブロミンやカフェインより強い.森北出版「化学辞典(第2版)
用途ホスホジエステラーゼ阻害作 用を示します。
用途気管支拡張薬 強心薬 血管拡張薬 抗喘息薬 利尿薬
説明Theophylline is a methylxanthine that acts as a weak bronchodilator. It is useful for chronic therapy and is not helpful in acute exacerbations.Theophylline is a methylxanthine alkaloid that is a competitive inhibitor of phosphodiesterase (PDE; Ki = 100 μM). It is also a non-selective antagonist of adenosine A receptors (Ki = 14 μM for A1 and A2). Theophylline induces relaxation of feline bronchiole smooth muscle precontracted with acetylcholine (EC40 = 117 μM; EC80 = 208 μM). Formulations containing theophylline have been used in the treatment of asthma and chronic obstructive pulmonary disease (COPD).
使用theophylline is tonic and skin conditioning. Its cosmetic activity is not clearly or definitively established. It is most often found in anti-cellulite products. Theophylline is in the same family of bio chemicals as caffeine. It is naturally occurring in tea.
一般的な説明Odorless white crystalline powder. Odorless. Bitter taste.
調製方法
純化方法It crystallises from H2O as the monohydrate which becomes anhydrous above 100o. It is freely soluble in hot H2O, but its solubility at 15o is 0.44%. It complexes with heavy metals. It is a diuretic, vasodilator and a cardiac stimulant. [Lister Purines Part II, Fused Pyrimidines Brown Ed, Wiley-Interscience pp253-254 1971, ISBN 0-471-38205-1, Beilstein 26 H 455, 26 I 134, 26 II 263, 26 III/IV 2331.]
上流・下流製品情報
上流原料
下流製品
サプライヤー50 社
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
上海如吉生物科技发展有限公司+86-21-65211385-8001 36031160 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
Syntechem Co.,Ltd[email protected]
上海迈瑞尔生化科技有限公司4006356688 18621169109 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
北京绿百草科技发展有限公司010-61136123 · [email protected]
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
上海柯维化学技术有限公司021-64609169 18901607656 · [email protected]
上海诗丹德标准技术服务有限公司021-021-57127007-6622-6622 17621252073 · [email protected]
成都普思生物科技股份有限公司028-85370565-229 18080489829 · [email protected]
成都普菲德生物技术有限公司028-82610909 13388174823 · [email protected]
深圳虹彩祥根生物科技有限公司+86-0755-89668383 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
山东西亚化学有限公司13355009207 13355009207 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
天津希恩思生化科技有限公司400 638 7771 · [email protected]
上海拓朴医药科技有限公司+86 (21) 5196-9732
成都健腾生物技术有限公司86-28-85159085 · [email protected]
斯百全化学(上海)有限公司021-021-021-67601398-809-809-809 15221380277 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
艾科试剂4008-755-333 18080918076 · [email protected]
成都锦然生物科技有限公司028-83311324 1278112614 · [email protected]
上海思域化工科技有限公司86-21-34053660 · [email protected]
赛默飞世尔科技(中国)有限公司800-810-5118 · [email protected]
上海遐瑞医药科技有限公司+86 21 61551611
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
南京杜莱生物技术有限公司025-84699383-8003;025-846993838003-8003 18013301590 · [email protected]
Clearsynth Labs Limited+91-22-26355700 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
深圳市石金谷科技有限公司(0086)755-61930359 (0086)18038192047 · [email protected]
上海汇凯化学科技有限公司021-61995394 18916691159 · [email protected]
上海倍卓生物科技有限公司021-61119791,13386096464 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
成都零六生物科技有限公司400-1166-196 13458535857 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
上海卓因生物科技有限公司021-61317773 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
上海永叶生物科技有限公司86-021-61559134 15921386130 · [email protected]
江苏艾康生物医药研发有限公司025-66028182 17714375163 · [email protected]
成都润泽本土化工有限公司13096311329 028-88469284 616445927 · [email protected]
凯试(上海)科技有限公司021-50135380 · [email protected]
補足説明
定義本品は、次の化学式で表されるキサンチン誘導体である。
定義ChEBI: Theophylline is a dimethylxanthine having the two methyl groups located at positions 1 and 3. It is structurally similar to caffeine and is found in green and black tea. It has a role as a vasodilator agent, a bronchodilator agent, a muscle relaxant, an EC 3.1.4.* (phosphoric diester hydrolase) inhibitor, an anti-asthmatic drug, an anti-inflammatory agent, an immunomodulator, an adenosine receptor antagonist, a drug metabolite, a fungal metabolite and a human blood serum metabolite.
関連反応
105 件


関連ノート
読み込み中…