

基本情報
- 標準SMILES
CC(C)c1nc(CN(C)C(=O)N[C@H](C(=O)N[C@@H](Cc2ccccc2)C[C@H](O)[C@H](Cc2ccccc2)NC(=O)OCc2cncs2)C(C)C)cs1- InChIKey
NCDNCNXCDXHOMX-XGKFQTDJSA-N- 分子式
- C37H48N6O5S2
- 平均分子量
- 720.9 g/mol
- 単同位体質量
- 720.31276064
概要
Ritonavir is an L-valine derivative that is L-valinamide in which alpha-amino group has been acylated by a [(2-isopropyl-1,3-thiazol-4-yl)methyl]methylcarbamoyl group and in which a hydrogen of the carboxamide amino group has been replaced by a (2R,4S,5S)-4-hydroxy-1,6-diphenyl-5-{[(1,3-thiazol-5-ylmethoxy)carbonyl]amino}hexan-2-yl group. A CYP3A inhibitor and antiretroviral drug from the protease inhibitor class used to treat HIV infection and AIDS, it is often used as a fixed-dose combination with another protease inhibitor, lopinavir. Also used in combination with dasabuvir sodium hydrate, ombitasvir and paritaprevir (under the trade name Viekira Pak) for treatment of chronic hepatitis C virus genotype 1 infection as well as cirrhosis of the liver. It has a role as a HIV protease inhibitor, a xenobiotic, an antiviral drug and an environmental contaminant. It is a carbamate ester, a carboxamide, a member of 1,3-thiazoles, a member of ureas and a L-valine derivative.
名称と識別子
- 優先名称
- Ritonavir
- IUPAC
- 1,3-thiazol-5-ylmethyl N-[(2S,3S,5S)-3-hydroxy-5-[[(2S)-3-methyl-2-[[methyl-[(2-propan-2-yl-1,3-thiazol-4-yl)methyl]carbamoyl]amino]butanoyl]amino]-1,6-diphenylhexan-2-yl]carbamate
- 現地名
- リトナビル
- 英語名
- Ritonavir
- 分子式
- C37H48N6O5S2
- 分子量
- 720.94
名称と別名
ritonavir155213-67-5NorvirABT-538A-84538Abbott 84538ABBOTT-84538EmpetusRitomuneRitovirViekiraxViriton
名称をさらに表示
リトナビルリトナビル (JAN)[(1S,2S,4S)-1-ベンジル-2-ヒドロキシ-4-[[(2S)-2-[3-[(2-イソプロピル-4-チアゾリル)メチル]-3-メチルウレイド]-3-メチルブチリル]アミノ]-5-フェニルペンチル]カルバミド酸5-チアゾリルメチルN-[(1S,2S,4S)-1-ベンジル-2-ヒドロキシ-4-[[(S)-2-[3-メチル-3-[(2-イソプロピル-4-チアゾリル)メチル]ウレイド]-1-オキソ-3-メチルブチル]アミノ]-5-フェニルペンチル]カルバミン酸5-チアゾリルメチルノービア(1,3-チアゾール-5-イル)メチル N-[(2S,3S,5S)-3-ヒドロキシ-5-[(2S)-3-メチル-2-{[メチル({[2-(プロパン-2-イル)-1,3-チアゾール-4-イル]メチル})カルバモイル]アミノ}ブタンアミド]-1,6-ジフェニルヘキサン-2-イル]カルバマートRitonaviTHIAZOL-5-YL-METHANOLRitonavir for peak identification CRSRARECHEM AL BD 12611,3-THIAZOL-5-YLMETHANOLthiazol-5-ylMethyl ((2S,3S,5R)-3-hydroxy-5-((S)-2-(3-((2-isopropylthiazol-4-yl)Methyl)-3-Methylureido)-3-MethylbutanaMido)-1,6-diphenylhexan-2-yl)carbaMatethiazol-5-ylmethyl ((2S,3S,5S)-3-hydroxy-5-((S)-2-(3-((2-isopropylthiazol-4-yl)methyl)-3-methylureido)-3-methylbutanamido)-1,6-diphenylhexan-2-yl)carbamate1,3-Thiazol-5-ylmethyl N-[(2S,3S,5S)-3-hydroxy-5-[[(2S)-3-methyl-2-[[methyl-[(2-propan-2-yl-1,3-thiazol-4-yl)methyl]carbamoyl]amino]butanoyl]amino]-1,6-diphenylhexan-2-yl]carbamate1,3-thiazol-5-ylmethyl n-[(2s,3s,5r)-3-hydroxy-5-[[(2s)-3-methyl-2-[[methyl-[(2-propan-2-yl-1,3-thiazol-4-yl)methyl]carbamoyl]amino]butanoyl]amino]-1,6-diphenyl-hexan-2-yl]carbamate
RitonavirumABT538DTXSID1048627CHEBI:45409NSC-693184O3J8G9O825NSC693184DTXCID8028553
データベース識別子
- CAS
155213-67-5- PubChem CID
- 392622
- DTXSID
DTXSID1048627- ChEMBL
CHEMBL163- ChEBI
CHEBI:45409- UNII
- O3J8G9O825
- EC Number
- 605-001-5
- Nikkaji
- J659.314C
物性
構造計算による物性
- XLogP
- 6
- 極性表面積
- 202 Ų
- 水素結合供与体数
- 4
- 水素結合受容体数
- 9
- 回転可能結合数
- 18
- 重原子数
- 50
- 形式電荷
- 0
- 複雑度
- 1,040
実験および物理化学的性質
Drugs
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Used in Switzerland
LogP
log Kow = 6.27 /Estimated/
3.9
3.9
Color/FormWhite to light tan powder
Solubility
Practically insoluble
Freely soluble in methanol and ethanol; soluble in isopropanol.
In water, 1.1X10⁻⁴ mg/L @ 25 °C /Estimated/
1.26e-03 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anti-Infective Agents; Antiviral Agents; Anti-HIV Agents; Anti-Retroviral Agents; HIV Protease Inhibitors
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
FDA approved drugs -> Active ingredient
Antiretrovirals > Protease inhibitors
Vapor Pressure1.1X10-27 mm Hg @ 25 °C /Estimated/
Henry's Law ConstantHenry's Law constant = 2.7X10⁻³³ atm-cu m/mol @ 25 °C /Estimated/
Physical DescriptionSolid
Other Experimental PropertiesHydroxyl radical reaction rate constant = 9.7X10⁻¹¹ cu cm/molec-sec @ 25 °C /Estimated/
物理化学的性質
- 融点
- 120 · 120-122°C
- 沸点
- 947 · 947.0±65.0 °C(Predicted)
- 比重(密度)
- 1.239 · 1.239±0.06 g/cm3(Predicted)
- 蒸気圧
- 1e-7 kPa · <0.0000001 kPa ( 25 °C)
- 闪点
- 2 ℃ · 2℃
- 貯蔵温度
- room temp
- 溶解性
- 10 mg/mL · DMSO: 可溶10mg/mL (透明溶液、加温)
- 外見
- 粉
- 酸解離定数(Pka)
- 11.47 · 11.47±0.46(Predicted)
- 色
- 白からベージュ
- 由来生物
- synthetic
- 水溶解度
- 5 mg/L · 5mg/L(ミリ秒)
- Merck
- 14 · 14,8238
- BCS Class
- 2 · 2,4
- 安定性
- -20 °C · -20°C の DMSO またはエタノール溶液で最大 2 か月間保存できます。
- InChIKey
- NCDNCNXCDXHOMX-XGKFQTDJSA-N
- SMILES
- O=C(OCC1=CN=CS1)N[C@H]([C@@H](O)C[C@@H](NC([C@@H](NC(N(CC2=CSC(C(C)C)=N2)C)=O)C(C)C)=O)CC3=CC=CC=C3)CC4=CC=CC=C4
- CAS データベース
- 155213 · 155213-67-5(CAS DataBase Reference)
化学的性質
化学的特性Ritonavir is a white-to-light-tan powder with a bitter metallic taste. It is freely soluble in methanol and ethanol, soluble in isopropanol and practically insoluble in water. It is an inhibitor of HIV protease with activity against the Human Immunodeficiency Virus (HIV).
安全と法規制
GHS分類
GHS Classification
Warning
H302+H312+H332 (41.7%): Harmful if swallowed, in contact with skin or if inhaled [Warning Acute toxicity, oral; acute toxicity, dermal; acute toxicity, inhalation]
P203, P261, P264, P264+P265, P270, P271, P280, P301+P317, P302+P352, P304+P340, P305+P351+P338, P317, P318, P321, P330, P337+P317, P362+P364, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 96 reports by companies from 10 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
危険有害性情報
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl ritonavir, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Hazard Classes and CategoriesAcute Tox. 4 (88.5%)
安全と保護具
Storage Conditions
Commercially available ritonavir oral solution should be stored at room temperature at 20-25C; the oral solution should not be refrigerated. Exposure to excessive heat should be avoided. Ritonavir oral solution should be stored in the manufacturer-provided amber bottle and protected from light.
Ritonavir liquid-filled (soft gelatin) capsules should be refrigerated at 28 °C until dispensed. Once dispensed, the liquid-filled capsules should be refrigerated, but may be stored at a temperature lower than 25 °C for up to 30 days. The capsules should be protected from light and excessive heat.
Disposal Methods
SRP: The most favorable course of action is to use an alternative chemical product with less inherent propensity for occupational exposure or environmental contamination. Recycle any unused portion of the material for its approved use or return it to the manufacturer or supplier. Ultimate disposal of the chemical must consider: the material's impact on air quality; potential migration in soil or water; effects on animal, aquatic, and plant life; and conformance with environmental and public health regulations.
毒性情報
Interactions
These medications /amiodarone, astemizole, bepridil, bupropion, cisapride, clozapine, dihydroergotamine, encainide, ergotamine, flecainide, meperidine, pimozide, piroxicam, propafenone, propoxyphene, quinidine, rifabutin or terfenadine/ should not be administered concurrently with ritonavir; concurrent administration with ritonavir is likely to produce a large increase in the plasma concentrations of these medications, which may increase the risk of arrhythmias, hematologic abnormalities, seizures, or other potentially serious adverse effects.
In one study, concurrent administration /with clarithromycin/ increased the AUC of clarithromycin by 77% and the peak plasma concentration by 31%; dosing does not need to be adjusted in patients with normal renal function; however, for patients with a creatinine clearance of 30 to 60 ml/minute (0.5 to 1 ml/second), the dose of clarithromycin should be reduced by 50%, and for patients with a creatinine clearance of less than 30 ml/minute (0.5 ml/second), the dose of clarithromycin should be reduced by 75%.
These medications /clorazepate, diazepam, estazolam, flurazepam, midazolam, triazolam, or zolpidem/ should not be administered concurrently with ritonavir; concurrent administration with ritonavir is likely to produce a large increase in the plasma concentrations of these medications, which may produce extreme sedation and respiratory depression.
In one study, concurrent administration /with estrogen-containing oral contraceptive/ decreased the AUC of ethinyl estradiol by 40%; an oral contraceptive with a higher estrogen content or an alternative method of contraception should be considered.
For more Interactions (Complete) data for RITONAVIR (14 total), please visit the HSDB record page.
Hepatotoxicity
Some degree of serum aminotransferase elevations occurs in a high proportion of patients taking ritonavir containing antiretroviral regimens. Moderate-to severe elevations in serum aminotransferase levels (>5 times the upper limit of normal) are found in up to 15% of patients treated with full doses of ritonavir and are more common in patients with HIV-HCV coinfection. With low “booster” doses, ritonavir does not appear to increase the frequency or severity of serum enzyme elevations, and those that occur are usually asymptomatic and self-limited, resolving even with continuation of ritonavir. Clinically apparent liver injury from full doses of ritonavir has been reported, but hepatotoxicity from low dose ritonavir has not been clearly linked to acute liver injury. In many situations, the liver injury is difficult to attribute to ritonavir because it is used in combination with higher doses of other protease inhibitors. HIV protease inhibitors have been associated with acute liver injury arising 1 to 8 weeks after onset, with variable patterns of liver enzyme elevation, from hepatocellular to cholestatic. Immunoallergic features (rash, fever, eosinophilia) are uncommon as is autoantibody formation. Ritonavir in combination with saquinavir has also been associated with a rapid onset (1 to 4 days) acute hepatic injury in patients who are taking rifampin and perhaps other agents that affect CYP 450 activity, such as phenobarbital. Finally, initiation of ritonavir based highly active antiretroviral therapy can lead to exacerbation of an underlying chronic hepatitis B or C in coinfected individuals, typically arising 2 to 12 months after starting therapy and associated with a hepatocellular pattern of serum enzyme elevations and increases followed by falls in serum levels of hepatitis B virus (HBV) DNA or hepatitis C virus (HCV) RNA. Ritonavir therapy has not been clearly linked to lactic acidosis and acute fatty liver that is reported in association with several nucleoside analogue reverse transcriptase inhibitors.
Adverse Effects
Ritonavir has several constitutional side effects, including malaise, dizziness, and insomnia, gastrointestinal side effects including nausea, vomiting, abdominal pain, and diarrhea, and metabolic side effects such as hyperlipidemia, hypertriglyceridemia, transaminitis, and rhabdomyolysis. Although there are reports of QT prolongation with the use of protease inhibitors, studies have not established them as independent culprits.
Toxicity Summary
Because there is a small quantity of ritonavir in the combination of lopinavir/ritonavir, there are few reports of ritonavir toxicity. However, a few case reports have suggested retinal toxicity secondary to ritonavir. One such case showed an improvement after discontinuing ritonavir after 2 and 4 weeks.
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ Overdosage of ritonavir would be expected to produce manifestations that are principally extensions of the adverse reactions reported with the drug. Paresthesia occurred in one patient who ingested 1.5 g of ritonavir daily for 2 days; this adverse effect resolved once the ritonavir dosage was decreased. Renal failure with eosinophilia has occurred in association with an overdosage of ritonavir.
/HUMAN EXPOSURE STUDIES/ Hepatic coma, hepatitis, hepatomegaly, hepatosplenomegaly, or liver damage have been reported in less than 2% of patients receiving ritonavir in clinical studies. There have been postmarketing reports of hepatic dysfunction, including some fatalities, in patients receiving ritonavir. These generally occurred in patients receiving multiple drugs and/or with advanced AIDS.
/HUMAN EXPOSURE STUDIES/ Adverse hematologic effects reported in less than 2% of patients receiving ritonavir alone or with other antiretroviral agents include anemia, ecchymosis, leukopenia, lymphadenopathy, lymphocytosis, myeloproliferative disorder, and thrombocytopenia.
/HUMAN EXPOSURE STUDIES/ Pancreatitis, including some fatalities, has been reported in patients receiving ritonavir, including some patients who developed hypertriglyceridemia. Pancreatitis has been reported in less than 2% of patients receiving ritonavir in clinical studies. Fatal pancreatitis has been reported in a few patients receiving didanosine, stavudine, and an HIV protease inhibitor (i.e., indinavir, nelfinavir). Pancreatorenal syndrome consisting of acute pancreatitis in conjunction with acute renal failure has been reported in at least one patient receiving a multiple-drug regimen that included ritonavir; this syndrome also has been reported rarely in patients receiving regimens that did not include ritonavir.
For more Human Toxicity Excerpts (Complete) data for RITONAVIR (9 total), please visit the HSDB record page.
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Ritonavir
vMost-DILI-concern
8
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Non-Human Toxicity Excerpts
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ Reproduction studies in rats or rabbits at ritonavir exposure levels calculated to be equivalent to or twice the usual human dosage, respectively, did not reveal evidence of embryotoxicity or teratogenicity. In rats, developmental toxicity (i.e., early resorptions, decreased fetal body weight, ossification delays, developmental variations) occurred at a maternally toxic dosage (i.e., ritonavir exposure level equivalent to 30% of that attained with the usual human dosage); a slight increase in the incidence of cryptorchidism was observed in rats at a ritonavir exposure level equivalent to 22% of that achieved with the usual human dosage. In rabbits, developmental toxicity (i.e., resorptions, decreased litter size, decreased fetal body weight) occurred at a maternally toxic dosage (i.e., ritonavir exposure level equivalent to 1.8 times that attained with the usual human dosage based on a body surface area conversion factor).
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ There was no evidence that ritonavir affected fertility when the drug was given to male or female rats at exposure levels equivalent to 40 or 60%, respectively, of those expected with the usual human dosage. Higher ritonavir doses were not studied in these animals due to hepatic toxicity.
/GENOTOXICITY/ Ritonavir was not mutagenic or clastogenic in vitro and in vivo studies, including bacterial reverse mutation (Ames) assays using Salmonella typhimurium and Escherichia coli, the mouse lymphoma cell test, and the mouse micronucleus assay.
Antidote and Emergency Treatment
To enhance elimination: Administration of activated charcoal. Monitoring: Monitoring of vital signs and observation of the clinical status of the patient. Supportive care: Patients in whom intentional overdose is known or suspected should be referred for psychiatric consultation.
Basic treatment: Establish a patent airway. Suction if necessary. Watch for signs of respiratory insufficiency and assist ventilations if needed. Administer oxygen by nonrebreather mask at 10 to 15 L/min. Monitor for pulmonary edema and treat if necessary ... . Monitor for shock and treat if necessary ... . Anticipate seizures and treat if necessary ... . For eye contamination, flush eyes immediately with water. Irrigate each eye continuously with normal saline during transport ... . Do not use emetics. For ingestion, rinse mouth and administer 5 ml/kg up to 200 ml of water for dilution if the patient can swallow, has a strong gag reflex, and does not drool ... . Cover skin burns with dry sterile dressings after decontamination ... . /Poison A and B/
Advanced treatment: Consider orotracheal or nasotracheal intubation for airway control in the patient who is unconscious, has severe pulmonary edema, or is in respiratory arrest. Positive pressure ventilation techniques with a bag valve mask device may be beneficial. Monitor cardiac rhythm and treat arrhythmias as necessary ... . Start an IV with D5W /SRP: "To keep open", minimal flow rate/. Use lactated Ringer's if signs of hypovolemia are present. Watch for signs of fluid overload. Consider drug therapy for pulmonary edema ... . For hypotension with signs of hypovolemia, administer fluid cautiously. Watch for signs of fluid overload ... . Treat seizures with diazepam (Valium) ... . Use proparacaine hydrochloride to assist eye irrigation ... . /Poison A and B/
Treatment of overdose: To decrease absorption: Patients may benefit from treatment with activated charcoal. Monitoring: Patient's vital signs should be monitored. Supportive care: Patients in whom intentional overdose is confirmed or suspected should be referred for psychiatric consultation.
Maintain an open airway and assist ventilation if needed. Treat coma, seizures, hypotension or anaphylaxis if they occur. replace fluid losses resulting from gastroenteritis with intravenous crystalloids. Maintain steady urine flow with intravenous fluids to alleviate crystalluria and reverse renal dysfunction. Treat lactic acidosis with judicious doses of sodium bicarbonate and by withdrawal of the offending drug. There are no specific antidotes for these agents. Administer activated charcoal.
Effects During Pregnancy and Lactation◉ Summary of Use during Lactation
法規制情報
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, incl ritonavir, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
安全データ
- wgk
- 3
- rtecs
- XA5310000
- ridadr
- UN 1648 3 / PGII
- hs_code
- 29341000
- risk_code
- 36/38-20/21/22-41
- hazard_code
- Xi,Xn
- safety_code
- 26-37/39-36/37-39
- Hazard Classifications
- Acute Tox. 4 DermalAcute Tox. 4 InhalationAcute Tox. 4 Oral
- ストレージクラス
- 11 - Combustible Solids
- 有毒物質データの
- 155213-67-5(Hazardous Substances Data)
化学と産業
薬理情報
ATC Code
J05AE03
J - Antiinfectives for systemic use
QJ - Antiinfectives for systemic use
J05AE03
Protein BindingRitonavir is highly protein-bound in plasma (~98-99%), primarily to albumin and alpha-1 acid glycoprotein over the standard concentration range.
Pharmacodynamics
Ritonavir is a protease inhibitor with activity against Human Immunodeficiency Virus Type 1 (HIV-1). Protease inhibitors block the part of HIV called protease. HIV-1 protease is an enzyme required for the proteolytic cleavage of the viral polyprotein precursors into the individual functional proteins found in infectious HIV-1. Ritonavir binds to the protease active site and inhibits the activity of the enzyme. This inhibition prevents cleavage of the viral polyproteins resulting in the formation of immature non-infectious viral particles. Protease inhibitors are almost always used in combination with at least two other anti-HIV drugs. Modern protease inhibitors require the use of low-dose ritonavir to boost pharmacokinetic exposure through inhibition of metabolism via the cytochrome P450 3A4 enzyme pathway.
Mechanism of Action
Ritonavic inhibits the HIV viral proteinase enzyme that normally cleaves the structural and replicative proteins that arise from major HIV genes, such as *gag* and *pol*. *Gag* encodes proteins involved in the core and the nucleocapsid, while *pol* encodes the the HIV reverse transcriptase, ribonuclease H, integrase, and protease. The *pol*-encoded proteins are initially translated in the form of a larger precursoe polypeptide, *gag-pol*, and needs to be cleaved by HIV protease to form other complement proteins. Ritonavir prevents the cleavage of the *gag-pol* polyprotein, which results in noninfectious, immature viral particles. Ritonavir is a potent inhibitor of cytochrome P450 CYP3A4 isoenzyme present both in the intestinal tract and liver. It is a type II ligand that perfectly fits into the CYP3A4 active site cavity and irreversibly binds to the heme iron via the thiazole nitrogen, which decreases the redox potential of the protein and precludes its reduction with the redox partner, cytochrome P450 reductase. Ritonavir may also play a role in limiting cellular transport and efflux of other protease inhibitors via the P-glycoprotein and MRP efflux channels.
Unlike nucleoside antiretroviral agents, the antiviral activity of ritonavir does not depend on intracellular conversion to an active metabolite. Ritonavir and other HIV protease inhibitors (e.g., amprenavir, indinavir, lopinavir, nelfinavir, saquinavir) act at a different stage of the HIV replication cycle than nucleoside and nonnucleoside reverse transcriptase inhibitors, and results of in vitro studies indicate that the antiretroviral effects of HIV protease inhibitors and some nucleoside or nonnucleoside antiretroviral agents may be additive or synergistic.
Ritonavir is a selective, competitive, reversible inhibitor of HIV protease. HIV protease, an aspartic endopeptidase that functions as a homodimer, plays an essential role in the HIV replication cycle and the formation of infectious virus. During HIV replication, HIV protease cleaves viral polypeptide products of the gag and gag-pol genes (i.e., p55 and p160) to form structural proteins of the virion core (i.e., p17, p24, p9, and p7) and essential viral enzymes (i.e., reverse transcriptase, integrase, and protease). By interfering with the formation of these essential proteins and enzymes, ritonavir blocks maturation of the virus and causes formation of nonfunctional, immature, noninfectious virions. Ritonavir is active in both acutely and chronically infected cells since it targets the HIV replication cycle after translation and before assembly. Thus, the drug is active in chronically infected cells (e.g., monocytes and macrophages) that generally are not affected by nucleoside reverse transcriptase inhibitors (e.g., didanosine, lamivudine, stavudine, zalcitabine, zidovudine). Ritonavir does not affect early stages of the HIV replication cycle; however, the drug interferes with production of infectious HIV and limits further infectious spread of the virus.
While the complete mechanisms of antiviral activity of ritonavir have not been fully elucidated, ritonavir apparently inhibits replication of retroviruses, including human immunodeficiency virus type 1 (HIV-1) and 2 (HIV-2), by interfering with HIV protease. The drug, therefore, exerts a virustatic effect against retroviruses by acting as an HIV protease inhibitor.
Biological Half-Life
The approximate half-life of ritonavir is 3-5 hours.
The clinically relevant t1/2 beta is about 3 to 5 hours.
Metabolism/Metabolites
Ritonavir circulates in the plasma predominantly as unchanged drug. Five metabolites have been identified. The isopropylthiazole oxidation metabolite (M-2) is the major metabolite in low plasma concentrations and retains similar antiviral activity to unchanged ritonavir. The cytochrome P450 enzymes CYP3A and CYP2D6 are the enzymes primarily involved in the metabolism of ritonavir.
... Ritonavir is primarily metabolised by cytochrome P450 (CYP) 3A isozymes and, to a lesser extent, by CYP2D6. Four major oxidative metabolites have been identified in humans, but are unlikely to contribute to the antiviral effect. ...
Five ritonavir metabolites have been identified in human urine and feces. The isopropylthiazole oxidation metabolite (M2) appears to be the major metabolite. M2 (but not other metabolites) has antiviral activity similar to that of ritonavir; however, only very low concentrations of this metabolite are present in plasma. Other metabolites identified in in vitro studies include a decarbamoylated metabolite (M1) and a product of N-dealkylation at the urea terminus (M11).
FDA Pharmacological Classification
O3J8G9O825
RITONAVIR
Mechanisms of Action [MoA] - HIV Protease Inhibitors
Established Pharmacologic Class [EPC] - Cytochrome P450 3A Inhibitor
Established Pharmacologic Class [EPC] - Protease Inhibitor
Mechanisms of Action [MoA] - Cytochrome P450 3A Inhibitors
MeSH Pharmacological Classification
Inhibitors of HIV PROTEASE, an enzyme required for production of proteins needed for viral assembly.
Drugs and compounds which inhibit or antagonize the biosynthesis or actions of CYTOCHROME P-450 CYP3A.
Absorption, Distribution and Excretion
The absolute bioavailability of ritonavir has not been determined. Following oral administration, peak concentrations are reached after approximately 2 hours and 4 hours (Tmax) after dosing under fasting and non-fasting conditions, respectively. It should be noted that ritonavir capsules and tablets are not considered bioequivalent.
Ritonavir is primarily eliminated in the feces. Following oral administration of a single 600mg dose of radiolabeled ritonavir, approximately 11.3 ± 2.8% of the dose was excreted into the urine, of which 3.5 ± 1.8% was unchanged parent drug. The same study found that 86.4 ± 2.9% of the dose was excreted in the feces, of which 33.8 ± 10.8% was unchanged parent drug.
The estimated volume of distribution of ritonavir is 0.41 ± 0.25 L/kg.
The apparent oral clearance at steady-state is 8.8 ± 3.2 L/h. Renal clearance is minimal and estimated to be <0.1 L/h.
Ritonavir and its metabolites are eliminated from the body predominantly in the feces (86% of unchanged drug and metabolites), with minor urinary elimination (11%, mostly metabolites).
Absorption of ritonavir is only slightly affected by diet, and this is somewhat dependent on the formulation. The overall absorption of ritonavir from the capsule formulation may increase by 15% when taken with meals. ... There is greater than sixfold variability in drug trough concentrations among patients given 600 mg of ritonavir every 12 hours.
Cellular LocationsCytoplasm
用途と製造
Uses
MEDICATION
Antiviral
Use (kg) in Switzerland (2009): >100
Methods of ManufacturingPreparation: ... D.J. Kempf et al, US 5541206 (1994, 1996 both to Abbott)
Formulations/PreparationsOral: Capsules, liquid-filled, 100 mg, Norvir Softgel (with alcohol and polyoxyl 35 castor oil), Abbott; Solution 80 mg/ml, Norvir (with alcohol polyoxyl 35 castor oil, and propylene glycol), Abbott
応用分野
用途HIV プロテアーゼ阻害剤です。 タンパク質前駆体の開裂に関与する HIV プロ テアーゼを阻害することにより、成熟ウイル スの産生を阻害します。
説明Ritonavir (brand name: Norvir) was launched in Germany, the UK and US for treatment of advanced HIV in combination with antiretroviral nucleoside analogs in a record 72 days by the FDA. It is an inhibitor of HIV aspartic protease which is critical in the processing of a propeptide into the gag, gag-pol gene products and the protease itself. This inhibition results in the release of non-infectous immature virus particles. It is greater than 500-fold more selective for viral aspartic protease than the human version, has good oral bioavailability and may increase the bioavailability of other protease inhibitors. Ritonavir was able to increase the CD4 and CD8 lymphocyte count as well as reduce viral RNA. It is more potent than saqunavir and comparible in potency to zidovudine and lamivudine.
来歴Ritonavir is an antiretroviral drug discovered by Abbott Laboratories to treat acquired immunodeficiency syndrome (AIDS). It was approved by the Food and Drug Administration (FDA) in 1996, and was marketed in semi-solid capsule form under the brand name Norvir. Although it was originally developed for use as a protease inhibitor in a three-drug combination, today ritonavir is used in low doses to boost the effect (blood levels) of one of the other protease inhibitors.
使用Ritonavir is indicated in combination with other antiretroviral agents for the treatment of HIV-1-infected patients. Ritonivir is an HIV protease inhibitor (EC50 = 25 nM) that also inhibits CYP3A4, the primary cytochrome P450 isoform that metabolizes protease inhibitors. Through CYP3A4 inhibition, low doses of ritonivir can reduce the metabolism of concomitantly administered protease inhibitiors, enhancing their bioavailability and efficacy.
一般的な説明Ritonavir belongs to the group of protease inhibitors, which block the part of HIV called protease. Its mode of action involves binding to the protease active site and inhibiting the activity of the enzyme.
上流・下流製品情報
上流原料
サプライヤー50 社
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
VDM Biochemicals0330-2528181 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
合肥天健化工有限公司551-65418679 15856988503;15837135945 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
杭州东帆化学有限公司86-0571-85151182
安徽海康药业有限责任公司86-0556-5800026 17709662922 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
济南精合医药科技有限公司0531-88811783 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
上海思域化工科技有限公司86-21-34053660 · [email protected]
上海特伯化学科技有限公司+86-21-60341587 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
上海遐瑞医药科技有限公司+86 21 61551611
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
上海诺宝化工有限公司+86(0)21 60484900
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
ApexBio Technology LLC+1-832-696-8203 · [email protected]
济南铭雅医药科技有限公司0531-85828981 · [email protected]
武汉恒和达生物医药有限公司027-84888681 18086046872 · [email protected]
湖北威德利化学试剂有限公司186-02735115 18602735115 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
上海湄水化工科技有限公司021-60549325 18616193163
泰州同新生物医药科技有限公司0523-86818997 18652728585 · [email protected]
上海将来实业股份有限公司021-61552785 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
湖南华腾制药有限公司400-8592883 · [email protected]
上海御略医药科技有限公司021-60345187 13671753212 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
南京百鑫德诺生物科技有限公司025-58849295 · [email protected]
凯试(上海)科技有限公司021-50135380 · [email protected]
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
扬州聚和昌科技有限公司0514-0514-83662002 13073488988 · [email protected]
Sigma-Aldrich西格玛奥德里奇(上海)贸易有限公司021-61415566 800-8193336 · [email protected]
上海泽涵生物医药科技有限公司021-61350663 13052117465 · [email protected]
江苏倍达医药科技有限公司0512-63009836 18994340901 · [email protected]
補足説明
定義ChEBI: Ritonavir is an L-valine derivative that is L-valinamide in which alpha-amino group has been acylated by a [(2-isopropyl-1,3-thiazol-4-yl)methyl]methylcarbamoyl group and in which a hydrogen of the carboxamide amino group has been replaced by a (2R,4S,5S)-4-hydroxy-1,6-diphenyl-5-{[(1,3-thiazol-5-ylmethoxy)carbonyl]amino}hexan-2-yl group. A CYP3A inhibitor and antiretroviral drug from the protease inhibitor class used to treat HIV infection and AIDS, it is often used as a fixed-dose combination with another protease inhibitor, lopinavir. Also used in combination with dasabuvir sodium hydrate, ombitasvir and paritaprevir (under the trade name Viekira Pak) for treatment of chronic hepatitis C virus genotype 1 infection as well as cirrhosis of the liver. It has a role as an antiviral drug, a HIV protease inhibitor, an environmental contaminant and a xenobiotic. It is a member of 1,3-thiazoles, a L-valine derivative, a carbamate ester, a member of ureas and a carboxamide.
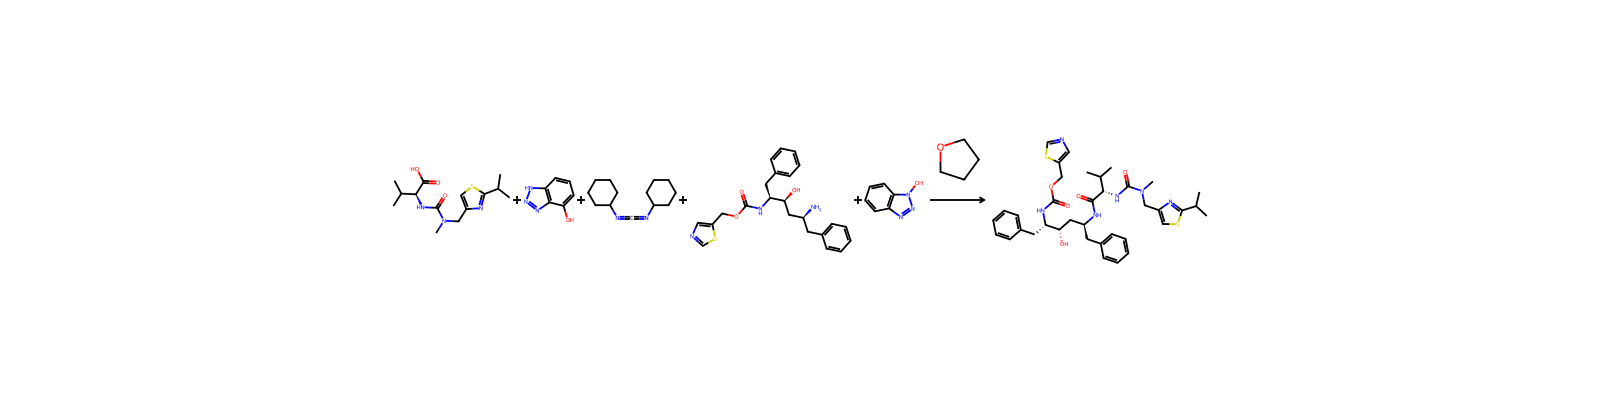
関連反応
60 件




関連ノート
読み込み中…