

基本情報
- 標準SMILES
CN1C(=O)C(O)N=C(c2ccccc2)c2cc(Cl)ccc21- InChIKey
SEQDDYPDSLOBDC-UHFFFAOYSA-N- 分子式
- C16H13ClN2O2
- 平均分子量
- 300.74 g/mol
- 単同位体質量
- 300.06655534
概要
Temazepam can cause developmental toxicity according to state or federal government labeling requirements.
名称と識別子
- 優先名称
- Temazepam
- IUPAC
- 7-chloro-3-hydroxy-1-methyl-5-phenyl-3H-1,4-benzodiazepin-2-one
- 現地名
- テマゼパム
- 英語名
- TEMAZEPAM
- 分子式
- C16H13ClN2O2
- 分子量
- 300.74
名称と別名
temazepamRestorilHydroxydiazepamMethyloxazepamOxydiazepamNormison846-50-4N-Methyloxazepam3-HydroxydiazepamTemazNocturneTemtabs
名称をさらに表示
1-メチル-3-ヒドロキシ-5-フェニル-7-クロロ1H-1,4-ベンゾジアゼピン-2(3H)-オンレバンキソールヒドロキシジアゼパムノルミソンメチルオキサゼパム7-クロロ-1,3-ジヒドロ-3-ヒドロキシ-1-メチル-5-フェニル-2H-1,4-ベンゾジアゼピン-2-オンシグノパムテムプゼパムプラヌムレストリル7-クロロ-5-フェニル-1-メチル-3-ヒドロキシ-1H-1,4-ベンゾジアゼピン-2(3H)-オン7-クロロ-1,3-ジヒドロ-1-メチル-3-ヒドロキシ-5-フェニル-2H-1,4-ベンゾジアゼピン-2-オン7-クロロ-3-ヒドロキシ-1-メチル-5-フェニル-1,3-ジヒドロ-2H-1,4-ベンゾジアゼピン-2-オン1-メチル-3-ヒドロキシ-5-フェニル-7-クロロ-1,3-ジヒドロ-2H-1,4-ベンゾジアゼピン-2-オンオキシジアゼパム3-ヒドロキシジアゼパムテマゼパムエウヒプノス7-クロロ-3-ヒドロキシ-1-メチル-5-フェニル-1H-1,4-ベンゾジアゼピン-2(3H)-オン7-クロロ-5-(フェニル)-1-メチル-3-ヒドロキシ-1H-1,4-ベンゾジアゼピン-2(3H)-オンer115k3917wy3917wy2917PlanumER 115K-3917WY 2917Cerepax
Wy-3917Temazepamum(RS)-TemazepamRo 5-5345Temazepam civWY 3917DTXSID80213092H-1,4-Benzodiazepin-2-one, 7-chloro-1,3-dihydro-3-hydroxy-1-methyl-5-phenyl-
データベース識別子
- CAS
846-50-4- PubChem CID
- 5391
- DTXSID
DTXSID8021309- ChEMBL
CHEMBL967- ChEBI
CHEBI:9435- UNII
- CHB1QD2QSS
- EC Number
- 212-688-1
- Nikkaji
- J7.138B
物性
構造計算による物性
- XLogP
- 2.2
- 極性表面積
- 52.9 Ų
- 水素結合供与体数
- 1
- 水素結合受容体数
- 3
- 回転可能結合数
- 1
- 重原子数
- 21
- 形式電荷
- 0
- 複雑度
- 434
実験および物理化学的性質
Chemical ClassesPharmaceutical
Drugs
DEA NFLIS-Drug Category -> Benzodiazepines
DEA Schedule IV Controlled Substance -> Depressants
Pharmaceuticals
Pharmaceuticals -> Hypnotic
Pharmaceuticals -> Synthetic Cannabinoids or Psychoactive Compounds
LogP3
Solubility5.34e-02 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Hypnotics and Sedatives; Anti-Anxiety Agents; Benzodiazepines
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Pharmaceuticals
Melting Point
119-121 °C
119 - 121 °C
Physical DescriptionSolid
Collision Cross Section166.1 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
物理化学的性質
- 融点
- 119 · 119-121°C
- 沸点
- 211 °C · 211°C (rough estimate)
- 比重(密度)
- 1.2682 · 1.2682 (rough estimate)
- 屈折率
- 1.52 · 1.5200 (estimate)
- 闪点
- 11 °C · 11 °C
- 貯蔵温度
- 2 · 2-8°C
- 溶解性
- 水にほとんど溶けず、ジクロロメタンに溶けやすく、エタノールに溶けにくい(96%)。
- 酸解離定数(Pka)
- 1.6 · pKa 1.6 (Uncertain)
- BCS Class
- 2 · 2
- CAS データベース
- 846 · 846-50-4(CAS DataBase Reference)
- EPAの化学物質情報
- Temazepam (846-50-4)
化学的性質
化学的特性Crystalline Solid
安全と法規制
GHS分類
GHS Classification
Warning
H302 (100%): Harmful if swallowed [Warning Acute toxicity, oral]
P264, P270, P301+P317, P330, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 52 reports by companies from 7 notifications to the ECHA C&L Inventory.
危険有害性情報
Regulatory Information
Hazard Traits - Developmental Toxicity
DEA schedule IV controlled substance
Temazepam: Does not have an individual approval but may be used under an appropriate group standard
Other Safety InformationIMAP assessments - 2H-1,4-Benzodiazepin-2-one, 7-chloro-1,3-dihydro-3-hydroxy-1-methyl-5-phenyl-: Environment tier I assessment
Hazard Classes and CategoriesAcute Tox. 4 (100%)
毒性情報
Treatment
If the patient is conscious, vomiting should be induced mechanically or with emetics. Gastric lavage should be employed utilizing concurrently a cuffed endotracheal tube if the patient is unconscious to prevent aspiration and pulmonary complications. Maintenance of adequate pulmonary ventilation is essential. The use of pressor agents intravenously may be necessary to combat hypotension. Fluids should be administered intravenously to encourage diuresis. (L1712)
Health EffectsThey cause slurred speech, disorientation and "drunken" behavior. They are physically and psychologically addictive.
Hepatotoxicity
Temazepam, like other benzodiazepines, is rarely associated with serum ALT elevations, and clinically apparent liver injury from temazepam is extremely rare, if it occurs at all. There have been no case reports of symptomatic, acute liver injury from temazepam. Isolated single cases of clinically apparent liver injury have been reported with other benzodiazepines including alprazolam, chlordiazepoxide, clonazepam, diazepam, flurazepam, lorazepam, and triazolam. The clinical pattern of acute liver injury from benzodiazepines is typically cholestatic and mild-to-moderate in severity with a latency of 1 to 6 months and rapid resolution with discontinuation. Fever and rash are uncommon as is autoantibody formation.
Adverse EffectsAdverse Drug Reactions
Exposure RoutesOral, well absorbed, minimal first-pass metabolism.
Toxicity Summary
Signs and Symptoms of Overdose
Benzodiazepines bind nonspecifically to benzodiazepine receptors, which affects muscle relaxation, anticonvulsant activity, motor coordination, and memory. As benzodiazepine receptors are thought to be coupled to gamma-aminobutyric acid-A (GABA<sub>A</sub>) receptors, this enhances the effects of GABA by increasing GABA affinity for the GABA receptor. Binding of the inhibitory neurotransmitter GABA to the site opens the chloride channel, resulting in a hyperpolarized cell membrane that prevents further excitation of the cell.
Carcinogen Classification
Temazepam
Group 3: Not classifiable as to its carcinogenicity to humans
Volume 66: (1996) Some Pharmaceutical Drugs
1996
1996
3, not classifiable as to its carcinogenicity to humans. (L135)
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Temazepam
Ambiguous-DILI-concern
3
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Effects During Pregnancy and Lactation
◉ Summary of Use during Lactation
◈ What is temazepam?
Toxicity DataLD50: 1963 mg/kg (oral, mice) (L1338)
LD50: 1833 mg/kg (oral, rat) (L1338)
LD50: >2400 mg/kg (oral, rabbit) (L1338)
USGS Health-Based Screening Levels for Evaluating Water-Quality
Temazepam
Pharmaceutical
Smith, C.D. and Nowell, L.H., 2024. Health-Based Screening Levels for evaluating water-quality data (3rd ed.). DOI:10.5066/F71C1TWP
安全データ
- wgk
- 3
- rtecs
- DF1225000
- ridadr
- UN 1230 3/PG 2
- 毒性
- LD50 oral in rat: 2gm/kg
- hs_code
- 2933910000
- risk_code
- 22-39/23/24/25-23/24/25-11
- hazard_code
- Xn,T,F
- safety_code
- 16-36/37-45-7
化学と産業
薬理情報
ATC Code
N - Nervous system
QN - Nervous system
Protein BindingIt has been recorded that about 96% of unchanged temazepam is bound to plasma proteins.
Pharmacodynamics
Temazepam is a benzodiazepine used as a hypnotic agent in the management of insomnia. Temazepam produces CNS depression at limbic, thalamic, and hypothalamic levels of the CNS. Temazepam increases the affinity of the neurotransmitter gamma-aminobutyric acid (GABA) for GABA receptors by binding to benzodiazepine receptors. Results are sedation, hypnosis, skeletal muscle relaxation, anticonvulsant activity, and anxiolytic action. In sleep laboratory studies, the effect of temazepam was compared to placebo during a two week period. The studies demonstrated a linear dose-response improvement in total sleep time and sleep latency with substantial drug-placebo differences apparent for total sleep time and for sleep latency at higher doses of temazepam. Regardless, REM sleep was ultimately unchanged but slow wave sleep was decreased. Moreover, a transient syndrome, known as "rebound insomnia", wherein the symptoms that led to treatment with temazepam in the first place recur in an enhanced form, may happen on withdrawal of temazepam treatment. The possibility of this occurrence is in part why long term use of temazepam is not recommended due to worries over tolerance and dependence wherein patients' bodies become physiologically accustomed to the regular presence and pharmacological effect of higher and higher doses of the benzodiazepine used. The duration of hypnotic effect and the profile of unwanted adverse effects may be influenced by the distribution and elimination half-lives of the administered temazepam and any active metabolites that may be formed. When such half-lives are long, the drug or its metabolite(s) may accumulate during periods of nightly administration and be associated with impairments of cognitive and motor performance during waking hours. Conversely, if half-lives are short, the drug and metabolites would be cleared before the next dose is ingested, and carry-over effects related to sedation or CNS depression should be minimal or not present at all. However, during nightly use and for an extended period, pharmacodynamic tolerance or adaptation to some effects of benzodiazepine hypnotics may develop - which may also contribute to the possibility of 'rebound insomnia'. Consequently, if the drug has a very short elimination half-life, it is possible that a relative deficiency (for example, in relation to benzodiazepine GABA(a) receptor sites) may occur at some point in the interval between each night's use. This sequence of events may account for certain clinical findings reported happening after several weeks of nightly use of rapidly eliminated benzodiazepine hypnotics, including increased wakefulness during the last third of the night and the appearance of increased daytime anxiety.
Mechanism of Action
Gamma-Aminobutyric acid (GABA) is considered the principal inhibitory neurotransmitter in the human body. When GABA binds to GABA(a) receptors found in neuron synapses, chloride ions are conducted across neuron cell membranes via an ion channel in the receptors. With enough chloride ions conducted, the local, associated neuron membrane potentials are hyperpolarized - making it more difficult or less likely for action potentials to fire, ultimately resulting in less excitation of the neurons. Subsequently, benzodiazepines like temazepam can bind to benzodiazepine receptors that are components of various varieties of GABA(a) receptors. This binding acts to enhance the effects of GABA by increasing GABA affinity for the GABA(a) receptor, which ultimately enhances GABA ligand binding at the receptors. This enhanced ligand binding of the inhibitory neurotransmitter GABA to the receptors increases the aforementioned chloride ion conduction (perhaps reportedly via an increase in the frequency of the chloride channel opening), resulting in a hyperpolarized cell membrane that prevents further excitation of the associated neuron cells. Combined with the notion that such benzodiazepine receptor associated GABA(a) receptors exist both peripherally and in the CNS, this activity consequently facilitates various effects like sedation, hypnosis, skeletal muscle relaxation, anticonvulsant activity, and anxiolytic action.
Biological Half-LifeThe terminal half-life determined for temazepam is recorded as being between 3.5-18 hours, with a mean of 9 hours.
Metabolism/Metabolites
First-pass metabolism of temazepam is minimal at approximately 5-8% of an administered dose. Nevertheless, temazepam is principally metabolized in the liver where most of the unchanged drug is directly conjugated to glucuronide and excreted in the urine. In particular, the primary metabolite present in the blood is the O-conjugate of temazepam. Less than 5% of the drug is demethylated to oxazepam and subsequently eliminated as the glucuronide. Regardless, the glucuronides of temazepam have no demonstrable CNS activity and it is believed that no active metabolites are formed in general. Since temazepam mainly undergoes Phase II conjugation reactions, it is proposed that it is devoid of CYP450 interactions.
Temazepam is a known human metabolite of diazepam.
Hepatic. Temazepam is completely metabolized through conjugation prior to excretion. The major metabolite is the O-conjugate of temazepam (90%). Route of Elimination: Temazepam was completely metabolized through conjugation prior to excretion; 80% to 90% of the dose appeared in the urine. Half Life: 10-20 hours
FDA Pharmacological Classification
CHB1QD2QSS
TEMAZEPAM
Established Pharmacologic Class [EPC] - Benzodiazepine
Chemical Structure [CS] - Benzodiazepines
Temazepam is a Benzodiazepine.
TEMAZEPAM
MeSH Pharmacological Classification
Drugs used to induce drowsiness or sleep or to reduce psychological excitement or anxiety.
Agents that alleviate ANXIETY, tension, and ANXIETY DISORDERS, promote sedation, and have a calming effect without affecting clarity of consciousness or neurologic conditions. ADRENERGIC BETA-ANTAGONISTS are commonly used in the symptomatic treatment of anxiety but are not included here.
Substances that do not act as agonists or antagonists but do affect the GAMMA-AMINOBUTYRIC ACID receptor-ionophore complex. GABA-A receptors (RECEPTORS, GABA-A) appear to have at least three allosteric sites at which modulators act: a site at which BENZODIAZEPINES act by increasing the opening frequency of GAMMA-AMINOBUTYRIC ACID-activated chloride channels; a site at which BARBITURATES act to prolong the duration of channel opening; and a site at which some steroids may act. GENERAL ANESTHETICS probably act at least partly by potentiating GABAergic responses, but they are not included here.
Absorption, Distribution and Excretion
Studies demonstrate that between 90 to 100% of an orally administered temazepam dose is absorbed, making the medication very well absorbed. The oral administration of 15 to 45 mg temazepam resulted in rapid absorption with significant blood levels achieved in 30 minutes and peak levels at 2-3 hours. In particular, direct studies following the oral ingestion of 30 mg of temazepam revealed measurable plasma concentrations were obtained 10-20 minutes after dosing with peak plasma levels ranging between 666-982 ng/mL (with a mean of 865 ng/mL) presenting approximately 1.2-1.6 hours (with a mean of 1.5 hours) after the dosing. Finally, a dose-proportional relationship was established for the area under the plasma concentration/time curve over the 15 to 30 mg dose range.
Following a single dose, 80-90% of the dose appears in the urine, predominantly as the O-conjugate metabolite, and 3-13% of the dose appears in the faeces. Less than 2% of the dose is excreted unchanged or as N-desmethyltemazepam in the urine.
The volume of distribution documented for temazepam is 1.3-1.5 L/kg body weight - and in particular, 43-68 L/kg for the unbound fraction.
Studies regarding the clearance of temazepam have recorded the values of 1.03 ml/min/kg and 31 ml/min/kg for the clearance of total temazepam and the clearance of unbound temazepam, respectively.
Tissue LocationsKidney
Cellular LocationsCytoplasm
用途と製造
Uses
Use (kg; approx.) in Germany (2009): >250
Officially indicated for severe insomnia and other severe or disabling sleep disorders. For the short-term treatment of insomnia (generally 7-10 days).
Use ClassificationPharmaceuticals
応用分野
使用Temazepam, is pharmacologically active metabolite of Diazepam (D416855). It is Sedative, and hypnotic. Controlled substance (depressant).
一般的な説明Temazepam, 7-chloro-1,3-dihydro-3-hydroxy-1-methyl-5-phenyl -2H-1,4-benzodiazepine-2-one(Restoril), also occurs as a minor metabolite of diazepam.It can be visualized as N-methyl oxazepam, and indeed, asmall amount of N-demethylation occurs slowly. However,metabolism proceeds mainly through glucuronidationof the 3-hydroxyl group, thus, it is intermediate acting andmarketed as a hypnotic said to have little or no residualeffect.
上流・下流製品情報
上流原料
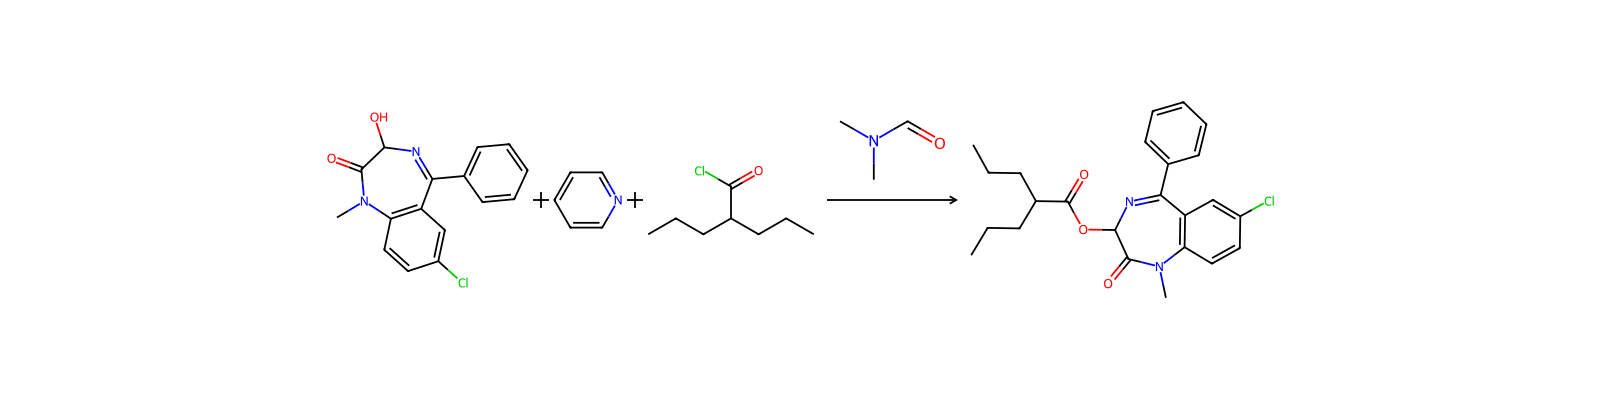
関連反応
5 件


関連ノート
読み込み中…