

기본 정보
- 표준 SMILES
CN1C(=O)CN=C(c2ccccc2)c2cc(Cl)ccc21- InChIKey
AAOVKJBEBIDNHE-UHFFFAOYSA-N- 분자식
- C16H13ClN2O
- 평균 분자량
- 284.74 g/mol
- 단동위원소 질량
- 284.07164072
개요
Diazepam can cause developmental toxicity according to state or federal government labeling requirements.
이름 및 식별자
- 우선 이름
- Diazepam
- IUPAC
- 7-chloro-1-methyl-5-phenyl-3H-1,4-benzodiazepin-2-one
- 현지명
- 다이아제팜
- 영어명
- Diazapam
- 분자식
- C16H13ClN2O
- 분자량
- 284.74
이름 및 동의어
diazepamValium439-14-5AnsiolisinaDiazemulsApaurinFaustanRelaniumSeduxenSibazonStesolidBialzepam
이름 더 보기
디아제팜다이아제팜DiazepanCondition7-chloro-1,3-dihydro-1-methyl-5-phenyl-2h-1,4-benzodiazepin-2-oneVivalQ-pamDialarcristalia
CeregulartNeurolytrilSerenaminValreleaseAlboralAnsiolinApozepamAtensine
데이터베이스 식별자
- CAS
439-14-5- PubChem CID
- 3016
- DTXSID
DTXSID4020406- ChEMBL
CHEMBL12- ChEBI
CHEBI:49575- UNII
- Q3JTX2Q7TU
- EC Number
- 207-122-5
- Nikkaji
- J2.044C
물성
구조 계산 물성
- XLogP
- 3
- 극성 표면적
- 32.7 Ų
- 수소 결합 공여자 수
- 0
- 수소 결합 수용자 수
- 2
- 회전 가능 결합 수
- 1
- 무거운 원자 수
- 20
- 형식 전하
- 0
- 복잡도
- 403
실험 및 물리화학적 성질
Chemical ClassesPharmaceutical
Drugs
DEA NFLIS-Drug Category -> Benzodiazepines
DEA Schedule IV Controlled Substance -> Depressants
Pharmaceuticals
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Synthetic Cannabinoids or Psychoactive Compounds
Pharmaceuticals -> Benzodiazepines
SpringerMaterials Properties15N nuclear magnetic resonance spectrum
LogP
log Kow = 2.82
2.9
OdorPractically no odor
Color/Form
Colorless to light yellow crysytals
Colorless to light yellow crystalline compound. Prisms from ethanol
Slightly yellowish crystalline powder
Solubility
less than 1 mg/mL at 68 °F (NTP, 1992)
1 g/2 mL chloroform; 1 g/39 mL ether
Sparingly soluble in propylene glycol; approx 62.5 mg/mL alcohol at 25 °C
Soluble in DMF benzene, acetone
One gram of diazepam dissolves in about 350 mL of water, in approximately 15 mL of 95% ethanol, or in approximately 2 mL of chloroform.
Human Drugs
Breast Feeding; Lactation; Milk, Human; Anticonvulsants; Hypnotics and Sedatives; Anti-Anxiety Agents; Benzodiazepines
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Pharmaceuticals
Antiseizure medicines
Animal Drugs
Active Ingredients (Diazepam) -> FDA Greenbook
Pharmaceuticals -> UK Veterinary Medicines Directorate List
DecompositionWhen heated to decomp it emits very toxic fumes of hydrogen chloride and NO(x)
Melting Point
257 to 259 °F (NTP, 1992)
125-126
132 °C
125 - 126 °C
Physical Description
Diazepam is an off-white to yellow crystalline powder. Practically odorless. Tasteless at first with a bitter aftertaste. (NTP, 1992)
Solid
물리화학적 성질
- 녹는점
- 131.5 · 131.5-134.5°C
- 끓는 점
- 497.4 · 497.4±45.0 °C(Predicted)
- 밀도
- 1.2245 · 1.2245 (rough estimate)
- 굴절률
- 1.633 · 1.6330 (estimate)
- 인화점
- 11 °C · 11 °C
- 저장 조건
- 2 · 2-8°C
- 용해도
- 45 % · 45%(w/v) 수성 2-히드록시프로필-β-시클로덱스트린: 1.6mg/mL
- 물리적 상태
- A neat solid
- 산도 계수 (pKa)
- 3.4 · 3.4(at 25℃)
- 수용성
- 50 mg/L · 50mg/L(25℃)
- Henry's Law Constant
- 2.7 · 2.7×103 mol/(m3Pa) at 25℃, HSDB (2015)
- BCS Class
- 1 · 1
- 안정성
- 안정적인. 감광성. 강한 산화제와 호환되지 않습니다.
- 주요 응용
- 의약품(소분자)
- InChI
- 1S/C16H13ClN2O/c1-19-14-8-7-12(17)9-13(14)16(18-10-15(19)20)11-5-3-2-4-6-11/h2-9H,10H2,1H3
- InChIKey
- AAOVKJBEBIDNHE-UHFFFAOYSA-N
- SMILES
- CN1C(=O)CN=C(c2ccccc2)c3cc(Cl)ccc13
- NIST
- 2 H-1,4-benzodiazepin-2-one, · 2H-1,4-benzodiazepin-2-one, 7-chloro-1,3-dihydro-1-methyl-5-phenyl-(439-14-5)
- EPA
- Diazepam (439-14-5)
화학적 성질
Light Yellow Crystalline Solid
안전 및 규제
GHS 분류
GHS Classification
Danger
H301 (96.5%): Toxic if swallowed [Danger Acute toxicity, oral]
P262, P264, P270, P280, P301+P316, P302+P352, P316, P321, P330, P361+P364, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 85 reports by companies from 14 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
유해성 정보
Regulatory Information
Hazard Traits - Developmental Toxicity
DEA schedule IV controlled substance
Diazepam: Does not have an individual approval but may be used under an appropriate group standard
Other Safety InformationIMAP assessments - 2H-1,4-Benzodiazepin-2-one, 7-chloro-1,3-dihydro-1-methyl-5-phenyl-: Human health tier I assessment
Fire HazardsFlash point data for this chemical are not available; however, it is probably combustible. (NTP, 1992)
Health Hazards
SYMPTOMS: Symptoms of exposure to this compound may include drowsiness, ataxia, skin rash, dysarthria, nausea, diplopia, anxiety, depression, constipation, changes in salivation, blurred vision, urinary retention, incontinence, tremor, headache, confusion, slurred speech, vertigo, changes in libido and jaundice. Other symptoms of exposure include fatigue, dizziness, respiratory depression, nystagmus, incoordination of the upper extremities, cardiac arrest, hyporeflexia, muscular weakness, agitation, insomnia, grand mal seizures, organic brain syndrome, paradoxical excitement, delirium, coma, hallucinations, vomiting, lethargy and respiratory failure or arrest. It can cause tinnitus, excitability, rage reaction, phlebitis and lactic acidosis. It can also cause central nervous depression, brown discoloration of the lenses, lightheadedness, amnesia, mental depression, blood disorders, dysphoria, slight wheezing, cyanosis, increased respiratory rate, abnormal blood gases, convulsions, increase in chromosomal aberrations, aplastic anemia, leukopenia, leukocytosis, encephalopathy, bilateral gynecomastia, allergic conjunctivitis, angle closure glaucoma, reduction of cardiac output and stroke volume, increase in heart rate and peripheral resistance, cholestasis, disorganization of thought, depressed pupillary response, inhibited performance recall, improved recall of information, reduced reaction time, apprehension, vascular disease, bronchopneumonia, bullous and vesicular skin eruptions, eccrine sweat gland and sweat duct necrosis, skin pallor and death. Exposure can cause decreased blood pressure, increase in hostility and irritability, and vivid or disturbing dreams. Exposure can also lead to hypotension, increased muscle spasticity, sleep disturbances, stimulation, neutropenia, hypoactivity, syncope, bradycardia, urticaria, cardiovascular collapse and hiccups. Damage to the eyes, central nervous system and pulmonary tract may occur. It may also cause dryness of the mouth, aggressive behavior, blood dyscrasias and hepatic dysfunction. If exposure occurs during pregnancy, it may cause lethargy and hypotonia in the offspring. The neonate may also experience apneic attacks. Symptoms may include hypertonia, hyperreflexis, difficulty in sucking, hypothermia and midline cleft deformities of the lip and palate. Depressed central nervous system function may also occur in the neonate.
FDA Requirements
Schedule IV shall consist of the drugs and other substances, by whatever official name, common or usual name, chemical name, or brand name designated, listed in this section. Each drug or substance has been assigned the DEA Controlled Substances Code Number set forth opposite it. Depressants. Unless specifically excepted or unless listed in another schedule, any material, compound, mixture, or preparation which contains any quantity of the following substances, including its salts, isomers, and salts of isomers whenever the existence of such salts, isomers, and salts of isomers is possible within the specific chemical designation: Diazepam (DEA Code Number: 2765) is included on this list.
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, including diazepam, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Reactive GroupAmines, Phosphines, and Pyridines
Special Reports
DHHS/NIDA; Research Monograph Series 52: Testing Drugs for Physical Dependence Potential and Abuse Liability (1984) DHHS Pub No. (ADM)87-1332
DHHS/NIDA; Research Monograph Series 54: Mechanisms of Tolerance and Dependence (1984) DHHS Pub No. (ADM)88-1330
DHHS/NIDA; Research Monograph Series 56: Etiology of Drug Abuse: Implications for Prevention (1987) DHHS Pub No. (ADM)87-1335
DHHS/NIDA; Research Monograph Series 59: Current Research on the Consequences of Maternal Drug Abuse (1985) DHHS Pub No. (ADM)85-1400
For more Special Reports (Complete) data for DIAZEPAM (8 total), please visit the HSDB record page.
Air and Water ReactionsHydrolysis occurs in aqueous solutions with a maximum stability around pH 5. (NTP, 1992). Insoluble in water.
Hazard Classes and CategoriesAcute Tox. 3 (96.5%)
Skin, Eye, and Respiratory IrritationsPossible eye, skin, ... and/or respiratory tract irritation.
Hazardous Reactivities and IncompatibilitiesA significant interaction exists between diazepam and infusion fluid containers constructed of pvc plastics, due to absorption of diazepam into the pvc matrix.
안전 및 보호
Fire FightingFires involving this material can be controlled with a dry chemical, carbon dioxide or Halon extinguisher. (NTP, 1992)
First Aid
EYES: First check the victim for contact lenses and remove if present. Flush victim's eyes with water or normal saline solution for 20 to 30 minutes while simultaneously calling a hospital or poison control center. Do not put any ointments, oils, or medication in the victim's eyes without specific instructions from a physician. IMMEDIATELY transport the victim after flushing eyes to a hospital even if no symptoms (such as redness or irritation) develop.
Fire Fighting Procedures
Water spray, dry chemical, carbon dioxide, or foam as appropriate for surrounding fire and materials. ... As with all fires, evacuate personnel to a safe area. Firefighters should use self-contained breathing equipment and protective clothing.
Storage Conditions
Store in tight container as defined in the USP-NF. This material should be handled and stored per label instructions to ensure product integrity.
Diazepam injection should be protected from light and stored at 15-30 °C; freezing should be avoided. Diazepam tablets and extended-release capsules should be stored in tight, light-resistant containers at 15-30 °C. Diazepam oral solution and oral concentrate solution should be stored at 15-30 °C. ... Diazepam rectal gel should be stored at a controlled room temperature of 25 deg but may be exposed to temperatures ranging from 15-30 °C.
Cleanup Methods
Wear approved respiratory protection, chemically compatible gloves, and protective clothing. Wipe up spillage or collect spillage using a high-efficiency vacuum cleaner. Avoid breathing dust. Place spillage in appropriately labeled container for disposal. Wash spill site.
Nonfire Spill Response
SMALL SPILLS AND LEAKAGE: Should a spill occur while you are handling this chemical, FIRST REMOVE ALL SOURCES OF IGNITION, then you should dampen the solid spill material with 60-70% ethanol and transfer the dampened material to a suitable container. Use absorbent paper dampened with 60-70% ethanol to pick up any remaining material. Seal the absorbent paper, and any of your clothes, which may be contaminated, in a vapor-tight plastic bag for eventual disposal. Solvent wash all contaminated surfaces with 60-70% ethanol followed by washing with a soap and water solution. Do not reenter the contaminated area until the Safety Officer (or other responsible person) has verified that the area has been properly cleaned.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
SRP: At the time of review, regulatory criteria for small quantity disposal are subject to significant revision, however, household quantities of waste pharmaceuticals may be managed as follows: Mix with wet cat litter or coffee grounds, double bag in plastic, discard in trash.
Preventive Measures
This material is assumed to be combustible. As with all dry powders, it is advisable to ground mechanical equipment in contact with dry material to dissipate the potential buildup of static electricity.
As a general rule, when handling USP Reference Standards, avoid all contact and inhalation of dust, mists, and/or vapors associated with the material. Clean equipment and work surfaces with suitable detergent or solvent after use. After removing gloves, wash hands and other exposed skin thoroughly.
SRP: Wastewater from contaminant suppression, cleaning of protective clothing/equipment, or contaminated sites should be contained and evaluated for subject chemical or decomposition product concentrations. Concentrations shall be lower than applicable environmental discharge or disposal criteria. Alternatively, pretreatment and/or discharge to a permitted wastewater treatment facility is acceptable only after review by the governing authority and assurance that "pass through" violations will not occur. Due consideration shall be given to remediation worker exposure (inhalation, dermal and ingestion) as well as fate during treatment, transfer and disposal. If it is not practicable to manage the chemical in this fashion, it must be evaluated in accordance with EPA 40 CFR Part 261, specifically Subpart B, in order to determine the appropriate local, state and federal requirements for disposal.
SRP: Contaminated protective clothing should be segregated in a manner that results in no direct personal contact by personnel who handle, dispose of, or clean the clothing. Quality assurance procedures to confirm the efficacy of the cleaning procedures should be implemented prior to the decontaminated protective clothing being returned for reuse by the workers. Contaminated clothing (including shoes/socks) should not be taken home at end of shift, but should remain at employee's place of work for cleaning.
For more Preventive Measures (Complete) data for DIAZEPAM (9 total), please visit the HSDB record page.
Personal Protective Equipment (PPE)
RECOMMENDED RESPIRATOR: Where the neat test chemical is weighed and diluted, wear a NIOSH-approved half face respirator equipped with an organic vapor/acid gas cartridge (specific for organic vapors, HCl, acid gas and SO2) with a dust/mist filter. (NTP, 1992)
Safety glasses with sideshields are recommended. Face shields or goggles may be required if splash potential exists or if corrosive materials are present. Approved eye protection (eg, baring the ANSI Z87 or CSA stamp) is preferred.
Where respirators are deemed necessary to reduce or control occupational exposures, use NIOSH-approved respiratory protection and have an effective respirator program in place.
For handling of laboratory scale quantities, a cloth lab coat is recommended. Where significant quantities are handled, work clothing may be necessary to prevent take-home contamination.
독성 정보
Body Burden
Diazepam is excreted in the breast milk in significant amounts ...
Diazepam concentration measured in sweat was 0.1-6 ng per sweat patch total after one dose; it was first detected 2-4 hours after dose(1).
Treatment
General supportive measures should be employed, along with intravenous fluids, and an adequate airway maintained. Hypotension may be combated by the use of norepinephrine or metaraminol. Dialysis is of limited value. Flumazenil, a specific benzodiazepine receptor antagonist, is indicated for the complete or partial reversal of the sedative effects of benzodiazepines and may be used in situations when an overdose with a benzodiazepine is known or suspected. (L1712)
Interactions
... Acetaminophen (3.0 g/day for 5 days) somewhat reduced the 96 hr urinary excretion of diazepam and its metabolites following a single 10 mg dose of diazepam.
... The increase in serum diazepam following food is related to the secretion of the drug in gastric fluid with subsequent reabsorption and/or enterohepatic circulation of the drug.
... One levodopa-treated patient ... manifested deterioration of his parkinsonism when diazepam was started.
A patient repeatedly became hypothermic while taking lithium and diazepam but did not manifest hypothermia when taking either drug alone.
For more Interactions (Complete) data for DIAZEPAM (15 total), please visit the HSDB record page.
Health Effects
They cause slurred speech, disorientation and "drunken" behavior. They are physically and psychologically addictive. May cause a potentially dangerous rash that may develop into Stevens Johnson syndrome, an extremely rare but potentially fatal skin disease.
Ecotoxicity Values
LD50; Species: Peromyscus maniculatus (Deer mouse) oral via capsule 1070 mg/kg
EC50; Species: Daphnia magna (Water flea, <24 hr neonate); Conditions: freshwater, static, 21 °C, pH 7.6; Concentration: 0.015 mM for 24 hr; Effect: increased intoxication, immobilization
LC50; Species: Daphnia magna (Water flea, neonate); Conditions: freshwater, static; Concentration: 49.4 uM for 24 hr /formulation/
EC50; Species: Daphnia pulex (Water flea, <24 hr); Conditions: freshwater, static, 20 °C, pH 7.6; Concentration: 0.042 mM for 24 hr; Effect: increased intoxication, immobilization /formulation/
For more Ecotoxicity Values (Complete) data for DIAZEPAM (7 total), please visit the HSDB record page.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), Koc values from 192(2) to 630(3) indicate that diazepam is expected to have moderate to low mobility in soil(SRC). Volatilization of diazepam from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 3.6X10⁻⁹ atm-cu m/mole(SRC), using a fragment constant estimation method(4). Diazepam is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 2.8X10⁻⁸ mm Hg at 25 °C(SRC), determined from a fragment constant method(5). 14C-Labeled diazepam exhibited a biodegradation half-life of greater than 365 days when incubated using a water/sediment sample(3) which suggests that biodegradation is not an important environmental fate process in soil(SRC).
AQUATIC FATE: Based on a classification scheme(1), Koc values from 192(2) to 630(3) indicate that diazepam is expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(4) based upon an estimated Henry's Law constant of 3.6X10⁻⁹ atm-cu m/mole(SRC), developed using a fragment constant estimation method(5). According to a classification scheme(6), an estimated BCF of 33(SRC), from its log Kow of 2.82(7) and a regression-derived equation(8), suggests the potential for bioconcentration in aquatic organisms is moderate(SRC). 14C-Labeled diazepam exhibited a biodegradation half-life of greater than 365 days when incubated using a water/sediment sample(9) which suggests that biodegradation is not an important environmental fate process in water(SRC).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), diazepam, which has an estimated vapor pressure of 2.8X10⁻⁸ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), will exist in both the vapor and particulate phases in the ambient atmosphere. Vapor-phase diazepam is degraded in the atmosphere by reaction with photochemically-produced hydroxyl radicals(SRC); the half-life for this reaction in air is estimated to be 40 hours(SRC), calculated from its rate constant of 9.9X10⁻¹² cu cm/molecule-sec at 25 °C(SRC) that was derived using a structure estimation method(3). Particulate-phase diazepam may be removed from the air by wet or dry deposition(SRC). Diazepam does not contain chromophores that absorb at wavelengths >290 nm(4), and therefore is not expected to be susceptible to direct photolysis by sunlight(SRC).
Adverse EffectsLike most benzodiazepines, the adverse reactions of diazepam include CNS and respiratory depression, dependence, and benzodiazepine withdrawal syndrome.
Exposure RoutesParenteral (intramuscular); oral; enteral(rectal).Essentially complete, with a bioavailability of 93%.
Milk Concentrations
EXPERIMENTAL: Diazepam is excreted in the breast milk in significant amounts ...
The excretion of diazepam, N-desmethyldiazepam, temazepam and oxazepam in breast milk was studied during withdrawal of a 22-year-old patient from combined high dose diazepam and oxazepam therapy. Concentrations of these benzodiazepines in plasma from both the women and her nursing infant (1 year old) were also documented. Diazepam, N-desmethyldiazepam, temazepam and oxazepam were found in the maternal plasma and milk with mean milk: plasma ratios of 0.2, 0.13, 0.14 and 0.10 respectively. It was calculated on a mg/kg basis that the infant received some 4.7% of the maternal dose. Diazepam could not be detected in the infant's plasma, but low levels of N-desmethyldiazepam (20 and 21 ug/L), temazepam (7 ug/L) and oxazepam (7.5 and 9.6 ug/L) were present. The infant showed no overt physical or mental symptoms of benzodiazepine intoxication.
Toxicity Summary
IDENTIFICATION: Diazepam is classified as a psycholeptic, anxiolytic benzodiazepine derivative. Diazepam is a crystalline solid. Diazepam is very slightly soluble in water, soluble in alcohol and freely soluble in chloroform. Indications: Treatment of anxiety disorders, seizures and status epilepticus. Symptoms of drug withdrawal associated with the chronic abuse of ethanol, benzodiazepines, barbiturates, and other CNS depressants. Skeletal muscle spasticity and acute muscular spasms, including tetanus and cerebral palsy. Treatment of insomnia: Anxiety and/or desire for producing amnesia prior to surgery, dental, and endoscopic procedures. Conscious sedation for short anesthesia, alone or in combination with an opioid. Continuous infusion for sedation or seizures in the intensive care setting. HUMAN EXPOSURE: Main risks and target organs: Central nervous system, causing depression of respiration and consciousness. Summary of clinical effects: Central nervous system (CNS) depression and coma, or paradoxical excitation, but deaths are rare when benzodiazepines are taken alone. Deep coma and other manifestations of severe CNS depression are rare. Sedation, somnolence, diplopia, dysarthria, ataxia and intellectual impairment are the most common adverse effects of benzodiazepines. Overdose in adults frequently involves co-ingestion of other CNS depressants, which act synergistically to increase toxicity. Elderly and very young children are more susceptible to the CNS depressant action. Intravenous administration of even therapeutic doses of benzodiazepines may produce apnea and hypotension. Dependence may develop with regular use of benzodiazepines, even in therapeutic doses for short periods. If benzodiazepines are discontinued abruptly after regular use, withdrawal symptoms may develop. Contraindications: The primary absolute contraindication is an allergy to diazepam or other benzodiazepines, or the constituents of the parenteral formulation. There are relative contraindications, which require more careful monitoring of patients after receiving diazepam, and stronger consideration of alternative drug therapy. In these patients, the initial dose should be decreased: Chronic obstructive respiratory disease; neonates and infants up to 6 months of age; myasthenia gravis patients, close angle glaucoma, poisoning by other CNS depressants; breast feeding; geriatric patients, patients with severe liver failure and pregnancy. Routes of entry: Oral: This is the most frequent route of diazepam administration for therapeutic use as well as accidental poisonings, intentional overdoses, and abuse. Inhalation: The administration of diazepam solution into the lungs via an endotracheal tube has been demonstrated to produce therapeutic serum diazepam concentrations in animal models. Histologic examination of the lung demonstrated pneumonitis. These results suggest adequate absorption, however, the increased pulmonary toxicity indicates that this route should not be used in clinical practice. Dermal: Diazepam is absorbed through the skin, however, this route of administration is not used clinically. Parenteral: The preferred route of parenteral administration is intravenous. Indications include severe anxiety, excitation, alcohol and drug withdrawal syndrome, and seizures. The intramuscular route of diazepam administration should be avoided because absorption is erratic, and may be significantly delayed. Parenteral diazepam is irritating, and intravenous administration should be into a large peripheral vein. The rate of administration should be no faster than 5 mg per minute, and be followed by a saline flush to decrease local venous irritation. Significant adverse effects of intravenous diazepam include coma, hypotension, bradycardia, and respiratory failure. Such effects usually occur in the setting of rapid administration, administration of excessive doses, or administration to high-risk patients (the elderly, infants, patients with chronic respiratory disease) Other: Administration of diazepam rectally as either suppositories or solution results in good absorption. This route of administration is primarily used in convulsing children with no route of parenteral access. Absorption by route of exposure: Oral: Diazepam is absorbed rapidly following oral administration; with peak plasma concentrations generally being achieved within 1.0 hour (range 0.08 to 2.5 hours). The absorption rate is slowed by food and antacids. Absorption is almost complete with bioavailability. Parenteral: Intramuscular: Absorption is poor and erratic after intramuscular injection; plasma levels attained are equal to 60% of those reached after the same oral dose. The use of intramuscular diazepam has been described, however, this route should only be considered when other routes of administration or benzodiazepines are not available. Intravenous: Blood concentrations of 400 ng/mL and 1,200 ng/mL were measured 15 minutes after intravenous bolus doses of 10 and 20 mg, respectively Chronic administration of daily doses ranging from 2 mg to 30 mg result in plasma diazepam concentrations of 20 ng/mL to 1,010 ng/mL, and concentrations of desmethyldiazepam, an active metabolite, of 55 ng/mL to 1,765 ng/mL. Distribution by route of exposure: In human volunteers, the plasma protein binding of diazepam is greater than 95%. The concentration in the CSF appears to approximately correlate with the plasma free fraction. Patients with low serum albumin concentrations may have greater CNS effects secondary to an increased free fraction of diazepam. Following intravenous administration, diazepam concentrations can be described by a 2 compartment kinetic model. An initial rapid decline in serum concentrations associated with distribution into tissue, is followed by a slower decline reflecting the terminal elimination half-life. Due to its high lipid solubility diazepam passes rapidly into the brain, and other well perfused organs, and is afterwards redistributed to muscle and adipose tissue. Enterohepatic circulation is minimal. Diazepam crosses the placental barrier to the fetus and is present in breast milk. Biological half-life by route of exposure: The terminal elimination half-life of diazepam ranges from approximately 24 hours to more than two days. With chronic dosing, steady state concentrations of diazepam are achieved between 5 days to 2 weeks. The half-life is prolonged in the elderly and in patients with cirrhosis or hepatitis. It is shortened in patients taking drugs which induce hepatic enzymes, included anticonvulsants. The active metabolite desmethyldiazepam has a longer half-life than diazepam, and takes longer to reach steady state concentrations. Metabolism: Diazepam is primarily metabolized by hepatic enzymes, with very little unchanged drug eliminated in the urine. The hepatic cytochrome enzyme isozyme responsible for S- mephenytoin hydroxylation polymorphism is most likely the hepatic enzyme species responsible for diazepam metabolism. Hepatic n-demethylation results in the formation of the active metabolite desmethyldiazepam (also known as nordiazepam). This metabolite is hydroxylated to form oxazepam, which is conjugated to oxazepam glucuronide. A minor active metabolite is temazepam. The main active substances found in blood are diazepam and desmethyldiazepam. Elimination and excretion: A two-compartment open model is usually used to describe elimination kinetics of diazepam, after a single intravenous dose has been determined. Urinary excretion of diazepam is primarily in the form of sulphate and glucuronide conjugates, and accounts for the majority of the ingested dose. There is some evidence that the disposition of diazepam is slowed by chronic dosing and by plasma desmethyldiazepam levels. There is some evidence for species differences in biliary excretion. Studies suggest that biliary excretion of diazepam is probably clinically unimportant in man. Mode of action: Toxicodynamics: The toxic and therapeutic effects of diazepam are a result of its effect on CNS GABA activity. GABA (gamma-aminobutyric acid) is an important inhibitory neurotransmitter which mediates pre- and post-synaptic inhibition in all regions of the central nervous system. Diazepam and the other benzodiazepines appear to either enhance or facilitate GABA activity by binding to the benzodiazepine receptor, which is part of a complex including an aminobutyric acid receptor, benzodiazepine receptor, and barbiturate receptor. Binding at the complex results in increased CNS inhibition by GABA. The anticonvulsant and other effects of diazepam are believed to be produced by a similar mechanism, possibly involving various subtypes of the receptor. Pharmacodynamics: The pharmacodynamic effects of diazepam are also produced primarily by its actions with the result being enhancement of the inhibitory effects of GABA on the CNS. Two different zones have been described for the benzodiazepine binding at receptor sites and they have been classified as type I (chloride independent) and type II (chloride dependent. Type I receptor stimulation is believed to be responsible for anxiolysis, and Type II receptors responsible for sedation and ataxia. Similar to other sedative hypnotic drugs, preanesthetic doses of diazepam produce anterograde amnesia in the presence of therapeutic concentrations of diazepam, probably by impairing the establishment of the memory trace in the CNS. Tolerance to its anticonvulsant effects of diazepam generally develop within the first 6 to 12 months of therapy, which result in loss of anticonvulsant effects. For this reason diazepam is not commonly utilised for the chronic treatment of seizure disorders. The neonate is very sensitive to the effects of benzodiazepine. Teratogenicity: There is a some evidence that diazepam and other benzodiazepines are teratogenic in humans, increasing the risk of congenital malformations when ingested by the mother during the first trimester of pregnancy. Metabolic interactions: Diazepam does not induce or inhibit hepatic enzyme activity, and does not alter the metabolism of other agents. As diazepam is primarily dependent on hepatic metabolism for elimination, numerous agents which either induce or inhibit hepatic cytochrome P450 pathways or conjugation can alter the rate of diazepam metabolism. Agents inhibiting diazepam metabolism: Cimetidine, oral contraceptives, disulfiram, erythromycin, isoniazid, probenecid, propranolol, fluvoxamine, imipramine, fluoxetine and ciprofloxacin. Agents inducing diazepam metabolism: Rifampin, phenytoin, carbamazepine and phenobarbital. The major dynamic interactions with diazepam involve the synergistic increase in CNS depression (including central respiratory depression and hemodynamic depression) associated with other CNS depressant agents, including ethanol, non-benzodiazepine sedative hypnotics, barbiturates, drugs with CNS anticholinergic effects such as the antihistamines and tricyclic antidepressants, and opioids. These interactions increase synergistically the CNS depression, respiratory depression, and hemodynamic depression produced by each agent involved. Diazepam can decrease the efficacy of L-dopa used for the treatment of Parkinsonism. The effect is reversible. The anticonvulsant action of diazepam antagonizes the pro-convulsant activity of certain agents, including cocaine and strychnine. The primary adverse effects are secondary to the pharmacologic action of enhanced CNS GABA activity. Cognitive and psychomotor abilities may be impaired at therapeutic doses. Additional adverse effects include dizziness and prolonged reaction time, motor incoordination, ataxia, mental confusion, dysarthria, anterograde amnesia, somnolence, vertigo, and fatigue. Dysarthria and dystonia occur much less frequently. Paradoxical reactions of CNS hyperactivity occur rarely and manifest primarily as aggressive behaviour, irritability, and anxiety. Intravenous injection can produce local phlebitis and thrombophlebitis. Intra-articular injection may produce arterial necrosis. Diazepam and other benzodiazepines can cause physical and psychological dependence when administered at high doses for prolonged periods of time. The clinical manifestations of the withdrawal syndrome are similar to those associated with withdrawal of other sedative hypnotic and CNS depressants drugs. The long half-life and presence of active metabolites result in delayed onset of symptoms. The symptoms include anxiety, insomnia, irritability, confusion, anorexia, nausea and vomiting, tremors, hypotension, hyperthermia, and muscular spasm. Severe withdrawal symptoms include seizures and death. The treatment to prevent withdrawal and minimize any symptoms is to slowly reduce the dose of diazepam over 2 to 4 weeks. ANIMAL/PLANT STUDIES: A number of repeated dose studies have been carried out. In general, toxic effects have not been remarkable. In a three-month study in rats and a six-month study in dogs, some increase in liver size was seen, together with an increase in blood cholesterol; in the dogs an elevation of plasma alanine aminotransferase activity was observed. There was no increase in tumour frequency after feeding diazepam to rats and mice for 104 and 80 weeks, respectively. There is no evidence of carcinogenicity in humans. Mutagenicity: Diazepam has been reported to have mutagenic activity in the Salmonella typhimurium tester train TA100 in the Ames test, and to be genotoxic in a mouse bone marrow micronucleus test. Little or no effect was seen in an assay for chromosomal aberrations, performed in Chinese hamster cells in vitro.
Diazepam Overdose
Benzodiazepines bind nonspecifically to benzodiazepine receptors which mediate sleep, affects muscle relaxation, anticonvulsant activity, motor coordination, and memory. As benzodiazepine receptors are thought to be coupled to gamma-aminobutyric acid-A (GABA<sub>A</sub>) receptors, this enhances the effects of GABA by increasing GABA affinity for the GABA receptor. Binding of GABA to the site opens the chloride channel, resulting in a hyperpolarized cell membrane that prevents further excitation of the cell.
Signs and SymptomsSymptoms of overdose include somnolence, confusion, coma, and diminished reflexes. Respiration, pulse and blood pressure should be monitored.
Effluent Concentrations
A maximum diazepam concentration of 0.04 ug/L was reported in the effluent of a POTW (publicly-owned treatment works)(1). A diazepam concentration of less than 1 ng/L in an unspecified sewage effluent sample has been measured(2).
Diazepam median and range concentration loads in six Italian sewage treatment plants using primary settling and secondary activated sludge treatment processes were reported in influent as 0.4 and not detected to 1.4 mg/day/1000 inhabitants; loads in effluent were 0.5 and not detected to 1.0 mg/day/1000 inhabitants. The characteristics of the six sewage treatment plants are as follows: Cagliari (pop: 270,000; flow rate: 86,700 cu m/day; waste: domestic; discharge: Mediterranean Sea; sampling: summer, 2004); Naples (pop: 840,000; flow rate: 181,000 cu m/day; waste: domestic; discharge: Mediterranean Sea; sampling: winter, 2004); Latina (pop: 45,000; flow rate: 19,000 cu m/day; waste: domestic; discharge: Mediterranean Sea; sampling: summer, 2004); Cuneo (pop: 140,000; flow rate: 31,000 cu m/day; waste: domestic; discharge: River Po; sampling: summer, 2004); Varese Olona (pop: 120,000; flow rate: 23,000 cu m/day; waste: domestic; discharge: River Olona; sampling: summer and winter, 2004); and Varese Lago (pop: 110,000; flow rate: 40,000 cu m/day; waste: domestic and industrial; discharge: Lake Maggiore; sampling: winter, 2004)(1). A maximum diazepam concentration of 0.04 ug/cu cm was reported in wastewater sampled in Germany from 1996-1998(2). Diazipam was detected at a concentration of 400 ng/L in industrial effluents discharged into the North Sea from the Netherlands in 2002(3).
Diazepam was detected in three wastewater treatment plant effluents associated with facilities involved in the manufacture of pharmaceuticals in New York; 35-38 samples were collected from each plant between 2004 and 2009. The maximum concentrations of diazepam were 0% detection; 2 ug/L (100% detection) and 0.5 ug/L (18% detection) in the three New York sample, respectively; the latter receives 20% of its discharge from a pharmaceutical formulation facility. It was detected in 8.7% of samples (maximum concentration = 0.5 ug/L) from twenty-three plants across the US that were analyzed once between 2004 and 2009 as part of a National Survey; more than half of these plants receive hospital discharge. Detection limit = 0.011 ug/L(1).
규제 정보
FDA Requirements
Schedule IV shall consist of the drugs and other substances, by whatever official name, common or usual name, chemical name, or brand name designated, listed in this section. Each drug or substance has been assigned the DEA Controlled Substances Code Number set forth opposite it. Depressants. Unless specifically excepted or unless listed in another schedule, any material, compound, mixture, or preparation which contains any quantity of the following substances, including its salts, isomers, and salts of isomers whenever the existence of such salts, isomers, and salts of isomers is possible within the specific chemical designation: Diazepam (DEA Code Number: 2765) is included on this list.
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed prescription drug products, including diazepam, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
안전 데이터
- wgk
- 2
- tsca
- TSCA listed
- rtecs
- DF1575000
- ridadr
- UN 2811 6.1/PG 3
- 독성
- LD50 oral in rabbit: 328mg/kg
- HS 번호
- 2933910000
- risk_code
- 21/22-39/23/24/25-23/24/25-11-36/37/38
- hazard_code
- Xn,T,F,Xi
- safety_code
- 36/37-45-36-26-16-7
- 포장분류
- III
- 위험 등급
- 6.1(b)
- 기존화학 물질
- KE-05605
- Hazard Classifications
- Acute Tox. 3 DermalAcute Tox. 3 InhalationAcute Tox. 3 OralFlam. Liq. 2STOT SE 1
- 스토리지 클래스
- 3 - Flammable liquids
- 유해 물질 데이터
- 439-14-5(Hazardous Substances Data)
화학 및 산업
약리 정보
ATC Code
N05BA01
N05BA01
N - Nervous system
QN - Nervous system
N05BA01
Protein Binding
Despite high binding to plasma proteins (98-99%) - mainly albumin and to a lesser extent α1-acid glycoprotein - diazepam is widely distributed into tissues and crosses the blood-brain barrier and is highly lipid soluble, which causes the initial effects to decrease rapidly as it is redistributed into fat deposits and tissues.
Pharmacodynamics
Diazepam is a benzodiazepine that exerts anxiolytic, sedative, muscle- relaxant, anticonvulsant and amnestic effects. Most of these effects are thought to result from facilitation of the action of gamma aminobutyric acid (GABA), an inhibitory neurotransmitter in the central nervous system.
Mechanism of Action
Diazepam is a benzodiazepine tranquilliser with anticonvulsant, sedative, muscle relaxant and amnesic properties. Benzodiazepines, such as diazepam, bind to receptors in various regions of the brain and spinal cord. This binding increases the inhibitory effects of gamma-aminobutyric acid (GABA). GABAs functions include CNS involvement in sleep induction. Also involved in the control of hypnosis, memory, anxiety, epilepsy and neuronal excitability.
Diazepam is a benzodiazepine that exerts anxiolytic, sedative, muscle-relaxant, anticonvulsant and amnestic effects. Most of these effects are thought to result from a facilitation of the action of gamma aminobutyric acid (GABA), an inhibitory neurotransmitter in the central nervous system.
Benzodiazepines are widely used in clinical anesthesia as premedication, but also to induce general anesthesia. Recent in vitro studies suggest that gamma-aminobutyric acid type A receptors, harboring a classical high-affinity benzodiazepine binding site, possess another "nonclassical" binding site for benzodiazepines. At present, it is unclear if, and to what extent, this novel nonclassical binding site is of relevance for the actions of benzodiazepines in the central nervous system. Because neocortex is involved in mediating the sedative and hypnotic properties of general anesthetics, ... the actions of diazepam /were quantified/ over a wide range of concentrations (from 10 nM up to 100 uM) in organotypic slice cultures using extracellular multiunit recordings of spontaneous action potential activity. Up to a concentration of 6.25 uM, diazepam reduced the activity of neocortical neurons, approaching a maximum of approximately 20%. This action was nullified by the benzodiazepine antagonist flumazenil. At concentrations >12.5 uM, diazepam evoked a second concentration-dependent dampening of network activity. Unlike the low concentration effect, this high concentration component was resistant to flumazenil. Diazepam induced a biphasic attenuation of spontaneous action potential firing of neocortical neurons. Low to moderate concentrations caused a monotonic, mild depression that is mediated via the classical binding site as it is antagonized by flumazenil. However, the effects of diazepam observed at high concentrations were not affected by flumazenil. Hence, these findings support the concept of at least 2 different binding sites for benzodiazepines on gamma-aminobutyric acid type A receptors. Furthermore, /these/ results are consistent with the hypothesis that the classical high-affinity binding site mediates low-dose diazepam actions, such as amnesia, anxiolysis, and sedation, while a second, nonclassical and independent site contributes to the anesthetic effects of diazepam, such as hypnosis and immobility.
Benzodiazepine site agonists or inverse agonists enhance or reduce gamma-aminobutyric acid(A) (GABA(A)) receptor-mediated inhibition of neurons, respectively. Recently, it was demonstrated that the point mutation gamma 2F77I causes a drastic change in the affinity of a variety of benzodiazepine agonists or inverse agonists in receptor binding studies. Here we investigated the potency and efficacy of 10 benzodiazepine site ligands from 6 structural classes in wild-type and gamma 2F77I point mutated recombinant GABA(A) receptors composed of alpha 1 beta 3 gamma 2, alpha 2 beta 3 gamma 2, alpha 3 beta 3 gamma 2, alpha 4 beta 3 gamma 2, alpha 5 beta 3 gamma 2, and alpha 6 beta 3 gamma 2 subunits. Results indicate that the effects of the benzodiazepine site ligands zolpidem, zopiclone, Cl218872, L-655,708 and DMCM were nearly completely eliminated in all mutated receptors up to a 1 microM concentration. The effects of bretazenil, Ro15-1788 or abecarnil were eliminated in some, but not all mutated receptors, suggesting that the gamma 2F77I mutation differentially influences the actions of these ligands in different receptor subtypes. In addition, this point mutation also influences the efficacy of diazepam for enhancing GABA-induced chloride flux, suggesting that the amino acid residue gamma 2F77 might also be involved in the transduction of the effect of benzodiazepines from binding to gating.
Although the precise mechanism by which diazepam exerts its antiseizure effects is unknown, animal and in vitro studies suggest that diazepam acts to suppress seizures through an interaction with gamma-aminobutyric acid (GABA) receptors of the A-type (GABAA). GABA, the major inhibitory neurotransmitter in the central nervous system, acts at this receptor to open the membrane channel allowing chloride ions to flow into neurons. Entry of chloride ions causes an inhibitory potential that reduces the ability of neurons to depolarize to the threshold potential necessary to produce action potentials. Excessive depolarization of neurons is implicated in the generation and spread of seizures. It is believed that diazepam enhances the actions of GABA by causing GABA to bind more tightly to the GABAA receptor
For more Mechanism of Action (Complete) data for DIAZEPAM (8 total), please visit the HSDB record page.
Biological Half-Life
Diazepam has a biphasic half-life with an initial rapid distribution phase followed by a prolonged terminal elimination phase of 1 or 2 days; its action is further prolonged by the even longer half-life of 2-5 days of its principal active metabolite, desmethyldiazepam (nordiazepam), the relative proportion of which increases in the body on long-term administration. The plasma half-life of diazepam is prolonged in neonates, in the elderly, and in patients with kidney or liver disease.
... The distributive (alpha) half-life of diazepam is about 1 hr, while the elimination (beta) half-life is about 1.5 days initially and even longer after prolonged treatment.
In full term infants, elimination half-lives around 30 hours have been reported, with a longer average half-life of 54 hours reported in premature infants of 28 - 34 weeks gestational age and 8 - 81 days post-partum. In both premature and full term infants the active metabolite desmethyldiazepam shows evidence of continued accumulation compared to children. Longer half-lives in infants may be due to incomplete maturation of metabolic pathways
Elimination half-life increases by approximately 1 hour for each year of age beginning with a half-life of 20 hours at 20 years of age.
In mild and moderate cirrhosis, average half-life is increased. The average increase has been variously reported from 2-fold to 5-fold, with individual half-lives over 500 hours reported. ... Mean half-life is also prolonged with hepatic fibrosis to 90 hours (range 66 - 104 hours), with chronic active hepatitis to 60 hours (range 26 - 76 hours), and with acute viral hepatitis to 74 hours (range 49 - 129).
For more Biological Half-Life (Complete) data for DIAZEPAM (7 total), please visit the HSDB record page.
Metabolism/Metabolites
Diazepam is N-demethylated by CYP3A4 and 2C19 to the active metabolite N-desmethyldiazepam, and is hydroxylated by CYP3A4 to the active metabolite temazepam. N-desmethyldiazepam and temazepam are both further metabolized to oxazepam. Temazepam and oxazepam are further largely eliminated by way of conjugation to glucuronic acid via glucuronidation. Furthermore, oxidation of diazepam is mediated by cytochrome P450 isozymes; formation of desmethyl-diazepam mainly by CYP2C19 and CYP3A and 3-hydroxy-diazepam (temazepam) and oxazepam by CYP3A. Because CYP2C19 is polymorphic, extensive metabolizers (EMs), and poor metabolizers (PMs) of diazepam can be distinguished. PMs of diazepam showed significantly lower clearance (12 vs 26 mL/min) and longer elimination half-life (88 vs 41 h) of diazepam than EMs after a single oral dose. Also, PMs had lower clearance, higher AUC and longer elimination half-life of desmethyl-diazepam.
Diazepam is N-demethylated by CYP3A4 and 2C19 to the active metabolite N-desmethyldiazepam, and is hydroxylated by CYP3A4 to the active metabolite temazepam. N-desmethyldiazepam and temazepam are both further metabolized to oxazepam. Temazepam and oxazepam are largely eliminated by glucuronidation.
/Investigators/ observed variations in the metabolism of diazepam in Wistar rats. /The authors/ studied these variations carefully, and found that the variations are dimorphic and about 17% of male Wistar rats examined showed two times higher diazepam metabolic activities in their liver microsomes than the rest of animals at the substrate concentrations less than 5 uM. /They were/ classified as extensive metabolizer and poor metabolizer of diazepam. No sex difference was observed in the frequency of appearance of extensive metabolizer. Activities of the primary metabolic pathways of diazepam were examined to elucidate the cause of this polymorphism in male Wistar rats. No significant differences were observed in activities of neither diazepam 3-hydroxylation or N-desmethylation between extensive metabolizer and poor metabolizer rats, while activity of diazepam p-hydroxylation was markedly (more than 200 times) higher in extensive metabolizer rats, indicating that this reaction is responsible for the polymorphism of diazepam metabolism in Wistar rats. We examined the expression levels of CYP2D1, which was reported to catalyze diazepam p-hydroxylation in Wistar rats to find no differences in the expression levels of CYP2D1 between extensive metabolizer and PM rats. The kinetic study on diazepam metabolism in male Wistar rats revealed that extensive metabolizer rats had markedly higher V(max) and smaller K(m) in diazepam p-hydroxylation than those of poor metabolizer rats, indicating the presence of high affinity high capacity p-hydroxylase enzyme in extensive metabolizer rats. As a consequence, at low concentrations of diazepam, major pathways of diazepam metabolism were p-hydroxylation and 3-hydroxylation in male extensive metabolizer rats, while in male poor metabolizer rats, 3-hydroxylation followed by N-desmethylation. Due to this kinetic nature of p-hydroxylase activity, extensive metabolizer rats had markedly higher total CL(int) of diazepam than that of poor metabolizer rats. Polymorphism in diazepam metabolism in humans is well documented, but this is the first report revealing the presence of the polymorphism in diazepam metabolism in rats. The current results infer polymorphic expression of new diazepam p-hydroxylating enzyme with lower K(m) than CYP2D1 in extensive metabolizer Wistar rats.
Diazepam has known human metabolites that include Temazepam and nordiazepam.
Hepatic via the Cytochrome P450 enzyme system. The main active metabolite is desmethyldiazepam, in addition to minor active metabolites including temazepam and oxazepam. Route of Elimination: Diazepam and its metabolites are excreted mainly in the urine, predominantly as their glucuronide conjugates. Half Life: Biphasic 1-2 days and 2-5 days, active metabolites with long half lives.
FDA Pharmacological Classification
Q3JTX2Q7TU
DIAZEPAM
Established Pharmacologic Class [EPC] - Benzodiazepine
Chemical Structure [CS] - Benzodiazepines
Diazepam is a Benzodiazepine.
DIAZEPAM
MeSH Pharmacological Classification
Agents that are administered in association with anesthetics to increase effectiveness, improve delivery, or decrease required dosage.
Drugs used to prevent SEIZURES or reduce their severity.
Drugs used to prevent NAUSEA or VOMITING.
Drugs used to induce drowsiness or sleep or to reduce psychological excitement or anxiety.
A heterogeneous group of drugs used to produce muscle relaxation, excepting the neuromuscular blocking agents. They have their primary clinical and therapeutic uses in the treatment of muscle spasm and immobility associated with strains, sprains, and injuries of the back and, to a lesser degree, injuries to the neck. They have been used also for the treatment of a variety of clinical conditions that have in common only the presence of skeletal muscle hyperactivity, for example, the muscle spasms that can occur in MULTIPLE SCLEROSIS. (From Smith and Reynard, Textbook of Pharmacology, 1991, p358)
Agents that alleviate ANXIETY, tension, and ANXIETY DISORDERS, promote sedation, and have a calming effect without affecting clarity of consciousness or neurologic conditions. ADRENERGIC BETA-ANTAGONISTS are commonly used in the symptomatic treatment of anxiety but are not included here.
Absorption, Distribution and Excretion
After oral administration, it is considered that diazepam is rapidly and completely absorbed from the gastrointestinal tract as >90% of diazepam is absorbed and the average time to achieve peak plasma concentrations is 1 – 1.5 hours with a range of 0.25 to 2.5 hours. Absorption is delayed and decreased when administered with a moderate fat meal. In the presence of food mean lag times are approximately 45 minutes as compared with 15 minutes when fasting. There is also an increase in the average time to achieve peak concentrations to about 2.5 hours in the presence of food as compared with 1.25 hours when fasting. This results in an average decrease in Cmax of 20% in addition to a 27% decrease in AUC (range 15% to 50%) when administered with food.
Diazepam and its metabolites are excreted mainly in the urine, predominantly as their glucuronide conjugates.
In young healthy males, the volume of distribution at steady-state is 0.8 to 1.0 L/kg.
The clearance of diazepam is 20 to 30 mL/min in young adults.
Diazepam rectal gel is well absorbed following rectal administration, reaching peak plasma concentrations in 1.5 hours. The absolute bioavailability of Diazepam rectal gel relative to Valium injectable is 90%. The volume of distribution of Diazepam rectal gel is calculated to be approximately 1 L/kg. ... Both diazepam and its major active metabolite desmethyldiazepam bind extensively to plasma proteins (95-98%).
The concentration of diazepam in plasma and saliva and its binding to plasma protein was determined in normal subjects receiving 10 mg single oral dose over an 8 hr period. A linear relationship was found between diazepam concentration in plasma and that in both mixed and parotid saliva, over plasma concentrations ranging from 196-74.8 ug/mL. Results indicate that there is no significant difference between parotid saliva and mixed saliva concentrations over a period of 8 hr after a single oral dose of diazepam and that appearance of diazepam in saliva may provide an alternate, noninvasive method of determining plasma diazepam levels.
Cellular LocationsCytoplasm
용도 및 제조
Uses
Diazepam is a Schedule IV controlled substance.
MEDICATION
MEDICATION (VET)
Use (kg) in Switzerland (2009): >25
Used in the treatment of severe anxiety disorders, as a hypnotic in the short-term management of insomnia, as a sedative and premedicant, as an anticonvulsant, and in the management of alcohol withdrawal syndrome.
Impurities... Diazepam is available in the USA as a National Formulary or USP grade containing 98.5-101.0% active ingredient on a dried basis with a maximum of 0.002% heavy metals.
U.S. Imports
(1974) 3.3X10+4 G (PRINCPL CUSTOMS DISTS)
(1983) 22 lb
U.S. Production(1975) PROBABLY GREATER THAN 4.54X10+5 G
Consumption Patterns
NEARLY 100% AS MEDICINAL (1976)
Number of prescriptions of diazepam in the U.S.: 13,056 (1990) vs. 12,475 (1995) /From table/
Methods of Manufacturing
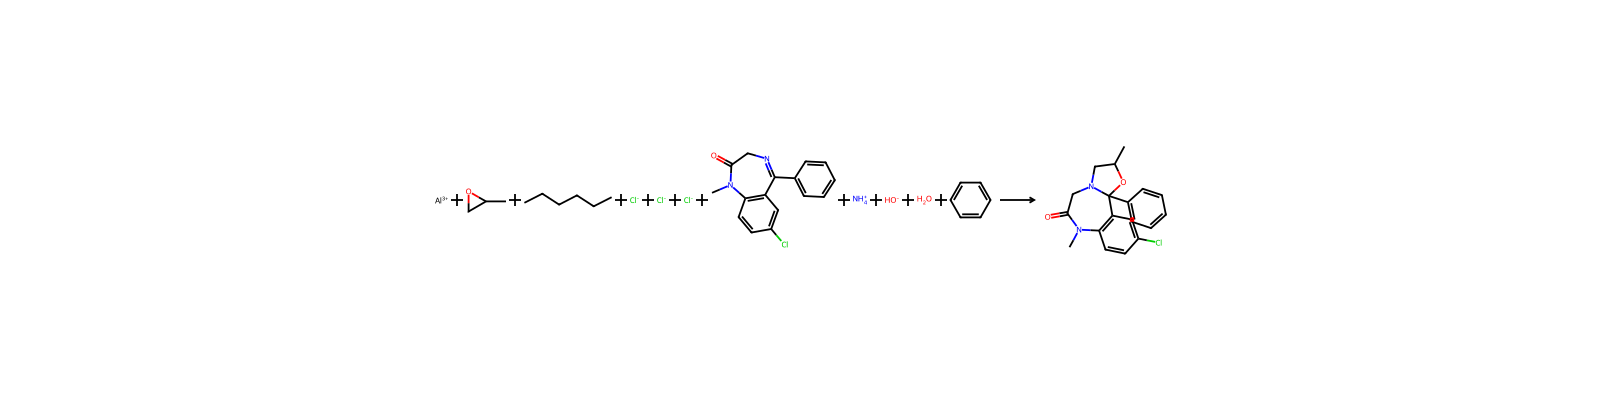
By the reaction of 2-methylamino-5-chlorobenzophenone with ethyl glycinate or with bromoacetyl bromide followed by reaction with ammonia
Benzoyl chloride is reacted with para-chloroaniline in the presence of a zinc chloride catalyst. The resulting 2-amino-5-chlorobenzophenone is converted to the oxime with hydroxylamine and then cyclized to the chloromethylquinazoline-3- oxide by treatment with chloroacetyl chloride. When this is treated with alkali, ring enlargement occurs, giving 7-chloro-1,3-dihydro-5-phenyl-2H-1,4- benzodiazepin-2-one-4-oxide. Raney nickel reduction of the oxide followed by methylation with dimethyl sulfate gives diazepam.
Diazepam can be prepared by several routes, eg, treatment of amino oxime, first with chloroacetyl chloride, then with base, /followed/ by reduction of the N-oxide with hydrogen.
Prepn: Sternbach, Reeder, J. Org. Chem. 26, 4936 (1961); Reeder, Sternbach, U.S. patent 3,371,085 (1968 to Hoffmann-La Roche); prepd but not claimed: eidem, U.S. patents 3,109,843 and 3,136,815 (1963, 1964 to Hoffman-La Roche): M. Gates, J. Or. Chem. 45, 1675 (1980); M. Ishikura et al., ibid. 47, 2456 (1982).
For more Methods of Manufacturing (Complete) data for DIAZEPAM (6 total), please visit the HSDB record page.
Formulations/PreparationsTable: Diazepam Preparations [Table#4376]
Use Classification
Animal Drugs -> FDA Approved Animal Drug Products (Green Book) -> Active Ingredients
Pharmaceuticals -> Nervous System -> Psycholeptics -> Anxiolytics -> Benzodiazepine derivatives -> Anticonvulsives
Pharmaceuticals
General Manufacturing Information
2H-1,4-Benzodiazepin-2-one, 7-chloro-1,3-dihydro-1-methyl-5-phenyl-: ACTIVE
A significant interaction exists between diazepam and infusion fluid containers constructed of pvc plastics, due to absorption of diazepam into the pvc matrix.
The manufacturers state that diazepam injection should not be mixed with other drugs or iv fluids. Although some studies indicate that diazepam injection may be compatible with various drugs and iv fluids (eg, diluted to a concn of 5 mg/50 ml to 5 mg/100 mL with 0.9% sodium chloride, 5% dextrose, Ringer's, or lactated Ringer's injection), compatibility may depend on several factors (eg, the concn of the drugs, resulting pH, temp).
This is a controlled substance (depressant): 21 CFR 1308.14
응용 분야
용도Anxiolitic; muscle relaxant (skeletal); anticonvulsant. Controlled substance (depressant)
일반 설명Off-white to yellow crystalline powder. Practically odorless. Tasteless at first with a bitter aftertaste.
상·하류 제품 정보
상류 원료
하류 제품
관련 반응
39건




연결된 노트
불러오는 중…