

기본 정보
- 표준 SMILES
COc1ccc2c(c1)c(CC(=O)O)c(C)n2C(=O)c1ccc(Cl)cc1- InChIKey
CGIGDMFJXJATDK-UHFFFAOYSA-N- 분자식
- C19H16ClNO4
- 평균 분자량
- 357.8 g/mol
- 단동위원소 질량
- 357.0767857
이름 및 식별자
- 우선 이름
- Indomethacin
- IUPAC
- 2-[1-(4-chlorobenzoyl)-5-methoxy-2-methylindol-3-yl]acetic acid
- 현지명
- 인드메타신
- 영어명
- Indometacin
- 분자식
- C19H16ClNO4
- 분자량
- 357.79
이름 및 동의어
indomethacin53-86-1indometacinIndomethacineIndometacineIndocidMetindolReumacideIndomethazineIdomethineImbrilonMikametan
이름 더 보기
인도메타신인드메타신2-(1-(4-chlorobenzoyl)-5-Methoxy-2-Methyl-1H-indol-3-yl)acetic acidndomethacinINDOCINCatlepSadoreumndometacin
IndacinMobilanTannexAmunoInteban spArtrinovoConfortidIndomecol
데이터베이스 식별자
- CAS
53-86-1- PubChem CID
- 3715
- DTXSID
DTXSID9020740- ChEMBL
CHEMBL6- ChEBI
CHEBI:49662- UNII
- XXE1CET956
- EC Number
- 200-186-5
- Nikkaji
- J1.368D
물성
구조 계산 물성
- XLogP
- 4.3
- 극성 표면적
- 68.5 Ų
- 수소 결합 공여자 수
- 1
- 수소 결합 수용자 수
- 4
- 회전 가능 결합 수
- 4
- 무거운 원자 수
- 25
- 형식 전하
- 0
- 복잡도
- 506
실험 및 물리화학적 성질
LogP
4.27
log Kow = 0.91 at pH 7.4; 4.27 at pH 2.0
3.4
LogS-4.62
OdorOdorless, or has slight odor
TasteSlight, bitter
Color/Form
Pale-yellow to yellow-tan, crystalline powder
Crystals exhibit polymorphism
Solubility
0.937
In water, 0.937 mg/L at 25 °C
Soluble in ethanol, ether, acetone, castor oil; practically insoluble in water
1 g in about 30 mL chloroform
2.40e-03 g/L
Melting Point
311 or 323.6 °F (NTP, 1992)
151
One form of polymorphic crystals melts at about 155 °C, the other at about 162 °C
MP: 160 °C
158 °C
Caco2 Permeability-4.69
Physical Description
Crystals. (NTP, 1992)
Solid
Stability/Shelf Life
Light. Stable under recommended storage conditions.
SENSITIVE TO LIGHT
Stable in neutral or slightly acidic media, decomp by strong alkali.
STABLE IN AIR AND IN HEAT UNDER USUAL PREVAILING TEMP CONDITIONS
COMPRESSED TABLETS HARDEN ON STORAGE
Dissociation Constants
4.42
4.5
4.5
4.5
pKa = 4.50
Kovats Retention Index2680;2685
물리화학적 성질
- 녹는점
- 158 · 158-162 °C
- 끓는 점
- 499.4 · 499.4±45.0 °C(Predicted)
- 밀도
- 1.2135 · 1.2135 (rough estimate)
- 굴절률
- 1.68 · 1.6800 (estimate)
- 저장 조건
- Store at RT
- 용해도
- 50 mg/mL, · 에탄올: 50mg/mL, 투명, 황록색
- 산도 계수 (pKa)
- 4.5 · 4.5(at 25℃)
- 물리적 상태
- 백색 내지 회백색 분말
- 색상
- White to Light yellow to Light orange
- 생물학적 소스
- synthetic
- 수용성
- Soluble in acetone (40 mg/mL - clear, yellow solution), ethanol (20 mg/mL), ether, castor oil; Soluble in chloroform (50 mg/mL - clear, yellow, extremely viscous solution); decomposed by strong alkali but stable in neutral or slightly acidic media; insoluble in water.
- Merck
- 14 · 14,4968
- BRN
- 497341 · 497341
- BCS Class
- 2 · 2
- 안정성
- 안정적인. 강한 산화제와 호환되지 않습니다.
- InChI
- 1S/C19H16ClNO4/c1-11-15(10-18(22)23)16-9-14(25-2)7-8-17(16)21(11)19(24)12-3-5-13(20)6-4-12/h3-9H,10H2,1-2H3,(H,22,23)
- InChIKey
- CGIGDMFJXJATDK-UHFFFAOYSA-N
- SMILES
- COc1ccc2n(c(C)c(CC(O)=O)c2c1)C(=O)c3ccc(Cl)cc3
- NIST
- Indomethacin(53-86-1)
- EPA
- Indomethacin (53-86-1)
화학적 성질
Crystalline Solid
안전 및 규제
GHS 분류
GHS Classification
Danger
H300 (81%): Fatal if swallowed [Danger Acute toxicity, oral];H301 (19%): Toxic if swallowed [Danger Acute toxicity, oral];H317 (24.9%): May cause an allergic skin reaction [Warning Sensitization, Skin];H318 (18.5%): Causes serious eye damage [Danger Serious eye damage/eye irritation];H335 (18.5%): May cause respiratory irritation [Warning Specific target organ toxicity, single exposure; Respiratory tract irritation];H336 (18.5%): May cause drowsiness or dizziness [Warning Specific target organ toxicity, single exposure; Narcotic effects];H360 (25.4%): May damage fertility or the unborn child [Danger Reproductive toxicity];H373 (19%): May causes damage to organs through prolonged or repeated exposure [Warning Specific target organ toxicity, repeated exposure];H413 (19%): May cause long lasting harmful effects to aquatic life [Hazardous to the aquatic environment, long-term hazard]
P203, P260, P261, P264, P264+P265, P270, P271, P272, P273, P280, P301+P316, P302+P352, P304+P340, P305+P354+P338, P317, P318, P319, P321, P330, P333+P317, P362+P364, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 189 reports by companies from 24 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.;Information may vary between notifications depending on impurities, additives, and other factors. The percentage value in parenthesis indicates the notified classification ratio from companies that provide hazard codes. Only hazard codes with percentage values above 10% are shown. For more detailed information, please visit ECHA C&L website.
유해성 정보
Regulatory Information
Status: Active Update: 28-03-2018 https://echa.europa.eu/registration-dossier/-/registered-dossier/12427
Indomethacin: Does not have an individual approval but may be used under an appropriate group standard
Other Safety InformationIMAP assessments - 1H-Indole-3-acetic acid, 1-(4-chlorobenzoyl)-5-methoxy-2-methyl-: Environment tier I assessment;IMAP assessments - 1H-Indole-3-acetic acid, 1-(4-chlorobenzoyl)-5-methoxy-2-methyl-: Human health tier I assessment
DOT LabelPoison
Fire Hazards
Excerpt from ERG Guide 154 [Substances - Toxic and/or Corrosive (Non-Combustible)]:;Non-combustible, substance itself does not burn but may decompose upon heating to produce corrosive and/or toxic fumes. Some are oxidizers and may ignite combustibles (wood, paper, oil, clothing, etc.). Corrosives in contact with metals may evolve flammable hydrogen gas. Containers may explode when heated. For electric vehicles or equipment, ERG Guide 147 (lithium ion or sodium ion batteries) or ERG Guide 138 (sodium batteries) should also be consulted. (ERG, 2024)
Health Hazards
SYMPTOMS: May cause gastrointestinal discomfort and possibly ulcerations. May aggravate psychiatric disturbances, epilepsy, and parkinsonism. May cause drowsiness and headache.;ACUTE/CHRONIC HAZARDS: Very toxic. Hazardous decomposition products. May aggravate central nervous system disorders. Suspected teratogen. (NTP, 1992)
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including indomethacin, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including indomethacin sodium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Indomethacin/
Reactive GroupAcids, Carboxylic;Amides and Imides;Hydrocarbons, Aromatic;Aryl Halides
Special Reports
REVIEW WITH 144 REFERENCES DISCUSSING GI EFFECTS OF NONSTEROIDAL ANTI-INFLAMMATORY AGENTS COMPARED WITH THOSE OF ASPIRIN, INDOMETHACIN & PHENYLBUTAZONE.[PEMBERTON RE, STRAND LJ; REVIEW OF THE UPPER GASTROINTESTINAL EFFECTS OF THE NEWER NONSTEROIDAL ANTI-INFLAMMATORY AGENTS; DIG DIS 24 (JAN): 53 (1979)]
Lione A, Scialli AR; Reprod Toxicol 9 (1): 7-20 (1995). The developmental toxicity of indomethacin and sulindac.
Reactivity ProfileA weak organic acid.
Air and Water ReactionsPractically insoluble in water. Decomposes in alkali.
Toxic Combustion ProductsSpecial hazards arising from the substance or mixture: Carbon oxides, nitrogen oxides (NOx), Hydrogen chloride gas
Hazard Classes and CategoriesAcute Tox. 2 (81%);Acute Tox. 3 (19%);Skin Sens. 1 (24.9%);Eye Dam. 1 (18.5%);STOT SE 3 (18.5%);Repr. 1A (25.4%);STOT RE 2 (19%);Aquatic Chronic 4 (19%)
안전 및 보호
Fire Fighting
This compound is not very flammable but any fire involving this compound may produce dangerous vapors. You should evacuate the area. All firefighters should wear full-body protective clothing and use self-contained breathing apparatuses. You should extinguish any fires involving this chemical with a dry chemical, carbon dioxide, foam, or halon extinguisher. (NTP, 1992)
First Aid
EYES: First check the victim for contact lenses and remove if present. Flush victim's eyes with water or normal saline solution for 20 to 30 minutes while simultaneously calling a hospital or poison control center. Do not put any ointments, oils, or medication in the victim's eyes without specific instructions from a physician. IMMEDIATELY transport the victim after flushing eyes to a hospital even if no symptoms (such as redness or irritation) develop.;SKIN: IMMEDIATELY flood affected skin with water while removing and isolating all contaminated clothing. Gently wash all affected skin areas thoroughly with soap and water. If symptoms such as redness or irritation develop, IMMEDIATELY call a physician and be prepared to transport the victim to a hospital for treatment.;INHALATION: IMMEDIATELY leave the contaminated area; take deep breaths of fresh air. IMMEDIATELY call a physician and be prepared to transport the victim to a hospital even if no symptoms (such as wheezing, coughing, shortness of breath, or burning in the mouth, throat, or chest) develop. Provide proper respiratory protection to rescuers entering an unknown atmosphere. Whenever possible, Self-Contained Breathing Apparatus (SCBA) should be used; if not available, use a level of protection greater than or equal to that advised under Protective Clothing.;INGESTION: If the victim is conscious and not convulsing, give 1 or 2 glasses of water to dilute the chemical and IMMEDIATELY call a hospital or poison control center. Generally, the induction of vomiting is NOT recommended outside of a physician's care due to the risk of aspirating the chemical into the victim's lungs. However, if the victim is conscious and not convulsing and if medical help is not readily available, consider the risk of inducing vomiting because of the high toxicity of the chemical ingested. Ipecac syrup or salt water may be used in such an emergency. IMMEDIATELY transport the victim to a hospital. If the victim is convulsing or unconscious, do not give anything by mouth, ensure that the victim's airway is open and lay the victim on his/her side with the head lower than the body. DO NOT INDUCE VOMITING. IMMEDIATELY transport the victim to a hospital. (NTP, 1992)
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide.
Advice for firefighters: Wear self contained breathing apparatus for fire fighting if necessary.
Storage Conditions
Keep container tightly closed in a dry and well-ventilated place. Keep in a dry place.
Indomethacin capsules should be stored in well-closed containers at a temperature less than 40 °C, preferably at 15 to 30 °C. Indomethacin oral suspension should be stored in tight, light-resistant containers at a temperature less than 30 °C; exposure to temperatures greater than 50 °C should be avoided, and the suspension should be protected from freezing. Indomethacin suppositories should be stored at a temperature less than 30 °C; exposure to temperatures greater than 40 °C (even transiently) should be avoided.
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Wear respiratory protection. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Evacuate personnel to safe areas. Avoid breathing dust; Environmental precautions: Prevent further leakage or spillage if safe to do so. Do not let product enter drains; Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal.
Nonfire Spill Response
SMALL SPILLS AND LEAKAGE: Should a spill occur while you are handling this chemical, you should dampen the solid spill material with alcohol, then transfer the dampened material to a suitable container. Use absorbent paper dampened with alcohol to pick up any remaining material. Seal the absorbent paper, and any of your clothes, which may be contaminated, in a vapor-tight plastic bag for eventual disposal. Solvent wash all contaminated surfaces with alcohol followed by washing with a strong soap and water solution. Do not reenter the contaminate area until the Safety Officer (or other responsible person) has verified that the area has been properly cleaned. (NTP, 1992)
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company. Contact a licensed professional waste disposal service to dispose of this material. Dissolve or mix the material with a combustible solvent and burn in a chemical incinerator equipped with an afterburner and scrubber; Contaminated packaging: Dispose of as unused product.
Preventive Measures
Precautions for safe handling: Avoid contact with skin and eyes. Avoid formation of dust and aerosols. Provide appropriate exhaust ventilation at places where dust is formed. Normal measures for preventive fire protection.
Appropriate engineering controls: Avoid contact with skin, eyes and clothing. Wash hands before breaks and immediately after handling the product.
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands.
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Isolation and Evacuation
Excerpt from ERG Guide 154 [Substances - Toxic and/or Corrosive (Non-Combustible)]:;IMMEDIATE PRECAUTIONARY MEASURE: Isolate spill or leak area in all directions for at least 50 meters (150 feet) for liquids and at least 25 meters (75 feet) for solids.;SPILL: Increase the immediate precautionary measure distance, in the downwind direction, as necessary.;FIRE: If tank, rail tank car or highway tank is involved in a fire, ISOLATE for 800 meters (1/2 mile) in all directions; also, consider initial evacuation for 800 meters (1/2 mile) in all directions. (ERG, 2024)
Personal Protective Equipment (PPE)
RECOMMENDED RESPIRATOR: Where the neat test chemical is weighed and diluted, wear a NIOSH-approved half face respirator equipped with a combination filter cartridge, i.e. organic vapor/acid gas/HEPA (specific for organic vapors, HCl, acid gas, SO2 and a high efficiency particulate filter).;RECOMMENDED GLOVE MATERIALS: Permeation data indicate that nitrile gloves may provide protection to contact with this compound. Nitrile over latex gloves is recommended. However, if this chemical makes contact with your gloves, or if a tear, hole or puncture develops, remove them at once. (NTP, 1992)
Eye/face protection: Face shield and safety glasses Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU).
Skin protection: Handle with gloves.
Body Protection: Complete suit protecting against chemicals. The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace.
Respiratory protection: Where risk assessment shows air-purifying respirators are appropriate use a full-face particle respirator type N100 (US) or type P3 (EN 143) respirator cartridges as a backup to engineering controls. If the respirator is the sole means of protection, use a full-face supplied air respirator. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU).
독성 정보
Treatment
Treatment is symptomatic and supportive. The stomach should be emptied as quickly as possible if the ingestion is recent. If vomiting has not occurred spontaneously, the patient should be induced to vomit with syrup of ipecac. If the patient is unable to vomit, gastric lavage should be performed. Once the stomach has been emptied, 25 or 50 g of activated charcoal may be given. Depending on the condition of the patient, close medical observation and nursing care may be required. The patient should be followed for several days because gastrointestinal ulceration and hemorrhage have been reported as adverse reactions of indomethacin. Use of antacids may be helpful. (L1712)
Interactions
Severe, sometimes fatal, toxicity has occurred following administration of a NSAIA (e.g., indomethacin, ketoprofen) concomitantly with methotrexate (principally high-dose therapy) in patients with various malignant neoplasms or rheumatoid arthritis. The toxicity was associated with elevated and prolonged blood concentrations of methotrexate. The exact mechanism of the interaction remains to be established, but it has been suggested that NSAIAs may inhibit renal elimination of methotrexate, possibly by decreasing renal perfusion via inhibition of renal prostaglandin synthesis or by competing for renal elimination. Further studies are needed to evaluate the interaction between NSAIAs and methotrexate. Caution is advised if methotrexate and a NSAIA are administered concomitantly.
A patient experienced a transient deterioration of renal function induced by indomethacin during recovery from idiosyncratic phenylbutazone-associated renal failure. Since both drugs inhibit prostaglandin synthesis, this patient may illustrate a unique enhancement of the more common and clinically unimportant effect of altered glomerular filtration rate induced by such drugs. The renal insufficiency per se associated with the idiosyncratic reaction to phenylbutazone may have also enhanced this patient's reaction to indomethacin. Careful observation of patients during administration of such drugs in this and other settings of acute renal failure appears warranted.
The effects of warfarin and NSAIAs on GI bleeding are synergistic.420 Concomitant use of indomethacin and warfarin is associated with a higher risk of GI bleeding compared with use of either agent alone. It appears that indomethacin has little, if any, direct influence on the hypoprothrombinemic effect of warfarin or other oral anticoagulants when these drugs are administered concurrently. Because indomethacin may cause GI bleeding and may inhibit platelet aggregation, the drug should be used with caution in patients receiving any anticoagulant or thrombolytic agent (e.g., streptokinase).
Severe systemic hypertension developed in a patient who took indomethacin shortly after ingesting an appetite suppressant ('Trimolets') containing phenylpropanolamine. The hypertension was attributed to a drug interaction whereby the inhibition of prostaglandin synthesis by indomethacin exacerbated the sympathomimetic effects of phenylpropanolamine. ...
For more Interactions (Complete) data for INDOMETHACIN (40 total), please visit the HSDB record page.
Hepatotoxicity
Mild and transient elevations in serum aminotransferase levels are found in up to 15% of patients taking indomethacin chronically. Moderate ALT elevations (>3 times ULN) occur in less than 1% of patients. Frank liver injury with jaundice from indomethacin is rare (estimated at 1.1 per 100,000 prescriptions), and fewer than a dozen cases have been reported in the literature. The latency to onset of symptoms or jaundice is variable, but is usually within 1 to 8 weeks of starting, although instances of latency of 4 to 6 months have been reported. Patients present with anorexia, nausea and vomiting followed by jaundice. Hepatocellular patterns of enzyme elevations are most common, but cholestatic and mixed patterns have been reported. Allergic manifestations and autoimmune features are not common. The injury is usually self-limited, resolving in 1 to 3 months, but several fatal cases have been reported (Case 1), particularly after use of high doses in patients with juvenile rheumatoid arthritis or Still disease. Many of the reported cases of severe indomethacin associated hepatotoxicity have occurred in patients with a pre-existing, underlying chronic liver disease.;Likelihood score: C (probable rare cause of clinically apparent liver injury).
Ecotoxicity Values
LC50; Species: Thamnocephalus platyurus (Fairy Shrimp) age <24 hr posthatch, nauplii; Conditions: freshwater, static, 25 °C; Concentration: 16140 ug/L for 24 hr (95% confidence interval: 12590-20960 ug/L) />98.0% purity/
LC50; Species: Oryzias latipes (Japanese Medaka) age <24 hr posthatch larva; Conditions: freshwater, static, 25 °C; Concentration: 81920 ug/L for 96 hr (95% confidence interval: 75000-90530 ug/L) />98.0% purity/
EC50; Species: Danio rerio (Zebra Danio) age 4 hr postfertilization, embryo, wild-type; Conditions: freshwater, static, 25 °C, pH 6.8-8, hardness 217-235 mg/L CaCO3, dissolved oxygen >80%; Concentration: 0.12 mM for 140 hr; Effect: increased abnormal development /formulation/
EC50; Species: Danio rerio (Zebra Danio) age 4 hr postfertilization, embryo, wild-type; Conditions: freshwater, static, 25 °C, pH 6.8-8, hardness 217-235 mg/L CaCO3, dissolved oxygen >80%; Concentration: 0.31 mM for 44 hr; Effect: increased abnormal development /formulation/
For more Ecotoxicity Values (Complete) data for INDOMETHACIN (9 total), please visit the HSDB record page.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), a Koc value of 1300(2) indicates that indomethacin is expected to have low mobility in soil(SRC). The pKa of indomethacin is 4.50(3), indicating that this compound will exist almost entirely in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization from moist soil is not expected because the compound exists as an anion and anions do not volatilize. Indomethacin is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 9.9X10⁻¹¹ mm Hg at 25 °C(SRC), determined from a fragment constant method(5). Utilizing batch-activated sewage treatment, 31% biodegradation was observed(2) suggesting that biodegradation may be an important environmental fate process in soil(SRC).
AQUATIC FATE: Based on a classification scheme(1), a Koc value of 1300(2) indicates that indomethacin is expected to adsorb to suspended solids and sediment(SRC). A pKa of 4.50(3) indicates indomethacin will exist almost entirely in the anion form at pH values of 5 to 9 and, therefore, volatilization from water and moist soil surfaces is not expected to be an important fate process(SRC). Bioconcentration is not expected to be an important fate process as anions do not bioconcentrate. Utilizing the DOC river die-away test, biodegradation half-lives of 430 and 410 hours were obtained(2) suggesting that biodegradation may be an important environmental fate process in water(SRC).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), indomethacin, which has an estimated vapor pressure of 9.9X10⁻¹¹ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase indomethacin may be removed from the air by wet and dry deposition(SRC). Indomethacin exhibited an aquatic photodegradation half-lives of 16 and 21 hours(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Adverse Effects
As a commonly used drug, researchers have conducted numerous studies on the adverse effects. Adverse reactions from the product label are mentioned. Indomethacin (and most other NSAIDs) can impact most body organ systems, including the gastrointestinal, neurological, renal, hematological, and cardiopulmonary systems.;* The most common adverse reactions to indomethacin include headache, dizziness, dyspepsia, and nausea. Despite its use in treating various headache disorders, one of the most frequently reported adverse reactions is a headache.;* Hypersensitivity reactions to indomethacin can occur and include anaphylaxis, urticaria, and angioedema.;* As previously mentioned, indomethacin is a nonselective COX inhibitor, and COX-1 produces prostaglandins crucial for maintaining the gastric mucosa. Inhibition of this process can lead to dyspepsia (indigestion), nausea, constipation, and diarrhea. However, the most severe gastric adverse reaction to indomethacin involves the formation of peptic ulcers, which can manifest as mid-epigastric pain either relieved or exacerbated by eating. Gastric ulcers typically worsen with eating, while the pain associated with duodenal ulcers is alleviated by food intake. Ulcers have the potential to rupture, leading to an acute surgical abdomen.;* Indomethacin can also affect the liver, resulting in elevated liver enzymes and jaundice.;* Indomethacin can also affect the neurological system, potentially resulting in tinnitus, vertigo, depression, dizziness, and headaches. Severe adverse reactions, including aseptic meningitis, psychosis, and cognitive dysfunction, have also been reported.;* COX enzymes are responsible for the synthesis of prostaglandins involved in renal function. Inhibition of this process can result in renal insufficiency. Indomethacin can also result in hyperkalemia and acute interstitial nephritis. Therefore, older individuals and patients with conditions such as dehydration, hypovolemia, renal dysfunction, heart failure, impaired liver function, and those taking diuretics, angiotensin-converting enzyme (ACE) inhibitors, or angiotensin II receptor blockers (ARBs) are at higher risk of experiencing adverse events.;* Indomethacin can have several effects on the hematologic system, including agranulocytosis, aplastic and hemolytic anemia, leukopenia, thrombocytopenia, and thrombocytopenic purpura. In addition, cases of indomethacin-induced leukocytoclastic vasculitis have been reported.;* Indomethacin can affect the cardiopulmonary system and result in acute respiratory distress, pulmonary edema, and congestive heart failure.;* Arachidonic acid is the precursor to prostaglandin synthesis via the action of COX enzymes. Inhibition of COX enzymes can divert arachidonic acid to the leukotriene synthesis pathway, potentially leading to the formation of nasal polyps in response to indomethacin. This condition may also manifest as respiratory difficulties. Additionally, indomethacin use can result in generalized fatigue and somnolence.;Drug-Drug Interactions;* Indomethacin may reduce the efficacy of various medications used to manage cardiovascular conditions (eg, ACE inhibitors, ARB inhibitors, or diuretics). Moreover, patients taking NSAIDs, including indomethacin, have reported fluid retention and edema.;* NSAIDs can increase lithium levels; thus, concurrent use of indomethacin with lithium should be avoided.;* The concurrent use of NSAIDs, including indomethacin, with oral apixaban is associated with an elevated risk of bleeding. Therefore, it is advisable to avoid combining these medications.;* Concomitant use of indomethacin and methotrexate can increase methotrexate plasma levels. Therefore, monitoring for signs of methotrexate toxicity is recommended.;* Indomethacin can decrease the natriuretic effect of furosemide and thiazide, reducing their efficacy. Combining NSAIDs with diuretics increases the risk of acute kidney injury.
Exposure RoutesParenteral(intravenous); enteral(rectal); oral.
Bioavailability is approximately 100% following oral administration and 80-90% following rectal administration.
Toxicity Summary
IDENTIFICATION AND USE: Indomethacin is a pale-yellow to yellow-tan, crystalline powder. It is an anti-inflammatory drug. It is also indicated to close a hemodynamically significant patent ductus arteriosus in premature infants weighing between 500 and 1,750 g when 48 hours usual medical management is ineffective. HUMAN EXPOSURE AND TOXICITY: Nonsteroidal anti-inflammatory drugs (NSAIDs) such as indomethacin cause an increased risk of serious gastrointestinal adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal. Elderly patients are at greater risk for serious gastrointestinal events. NSAIDs may also cause an increased risk of serious cardiovascular thrombotic events, myocardial infarction, and stroke. Severe reactions, including jaundice and fatal fulminant hepatitis, liver necrosis, and hepatic failure (sometimes fatal), have been reported in patients receiving NSAIDs. Serious skin reactions (e.g., exfoliative dermatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis) can occur in patients receiving indomethacin. Drowsiness, lethargy, mental confusion, nausea, vomiting, paresthesia, numbness, aggressive behavior, disorientation, and seizures have been reported following acute overdosage of the drug. Exposure of the fetus to indomethacin by administration of the drug to the mother may cause many side effects, including premature closure of the ductus arteriosus. Short-term indomethacin administered within 4 days prior to delivery resulted in a transient, yet significant renal dysfunction. ANIMAL STUDIES: Acute oral administration of indomethacin to rats induced macroscopic and microscopic damage to the small intestine, increased translocation of enterobacteria from lumen into the mucosa, myeloperoxidase activity and lipid peroxidation. After subchronic exposure to indomethacin for six to 12 weeks, rats displayed microcytic anemia, hypoalbuminemia, small intestinal ulceration, cecal ulceration and inc
Signs and Symptoms of Overdose ;Indomethacin toxicity is rare, with only a few cases reported in the literature. Documented cases have demonstrated symptoms such as headache, tinnitus, dizziness, lethargy, drowsiness, confusion, disorientation, restlessness, and acute kidney injury secondary to indomethacin toxicity.;Management of Overdose;Healthcare providers should offer patients supportive and symptomatic care following indomethacin dosage. A specific antidote for indomethacin toxicity is not available. For adult patients, administering 60 to 100 g of activated charcoal should be considered to decrease the absorption of NSAIDs from the upper gastrointestinal tract. Osmotic cathartics may be used in symptomatic patients observed within 4 hours of overdose or in patients who ingested 5 to 10 times the recommended dosage of indomethacin. The local poison control center should be contacted for detailed information on the treatment protocol.
Antiinflammatory effects of Indomethacin are believed to be due to inhibition of cylooxygenase in platelets which leads to the blockage of prostaglandin synthesis. Antipyretic effects may be due to action on the hypothalamus, resulting in an increased peripheral blood flow, vasodilation, and subsequent heat dissipation. Indomethacin is a prostaglandin G/H synthase (also known as cyclooxygenase or COX) inhibitor that acts on both prostaglandin G/H synthase 1 and 2 (COX-1 and -2). Prostaglandin G/H synthase catalyzes the conversion of arachidonic acid to a number of prostaglandins involved in fever, pain, swelling, inflammation, and platelet aggregation. Indomethacin antagonizes COX by binding to the upper portion of the active site, preventing its substrate, arachidonic acid, from entering the active site. Indomethacin, unlike other NSAIDs, also inhibits phospholipase A2, the enzyme responsible for releasing arachidonic acid from phospholipids. Indomethacin is more selective for COX-1 than COX-2, which accounts for its increased adverse gastric effects relative to other NSAIDs. COX-1 is required for maintaining the protective gastric mucosal layer. The analgesic, antipyretic and anti-inflammatory effects of indomethacin occur as a result of decreased prostaglandin synthesis. Its antipyretic effects may be due to action on the hypothalamus, resulting in an increased peripheral blood flow, vasodilation, and subsequent heat dissipation.
Signs and SymptomsThe following symptoms may be observed following overdosage: nausea, vomiting, intense headache, dizziness, mental confusion, disorientation, or lethargy. There have been reports of paresthesias, numbness, and convulsions.
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of December 17, 2015: http://actor.epa.gov/dashboard/]
Effluent Concentrations
72 samples from three conventional wastewater treatment plants in Spain were studied in 8 campaigns over 2 years starting in 2008. Indomethacin exhibited a 65, 58 and 0% frequency of detection in influent, effluent and sludge samples, respectively; detection limit = 3.0, 2.0 ng/L and 1.0 ng/g, respectively. Overall removal was attributed to chemical and physical transformation, biodegradation and sorption to sludge(1). Indomethacin, influent load of approximately 20 g/day, was 75% removed during a 6-day passage through a municipal treatment plant near Frankfurt/Main, Germany(2). Indomethacin was detected in 21 of 21 influent samples from the Pinedo and Quart-Benager wastewater treatment plants on the Turia River, Valencia Spain, sampled in March 2013 at an average concentration of 0.6 ng/L. It was not detected in the 21 effluent samples(3). The compound was present at 100% frequency (0.1 ug/L median concentration) in influent and 36% detection frequency in effluent (0.06 ug/L median concentration) water from a wastewater treatment plant in A Coruna, Galicia (NW Spain) sampled from November 2007 - September 2008(4). The compound was been detected not quantified in a wastewater treatment work in Ouse, West Sussex, UK(5). Indomethacin was detected, not quantified in surface water downstream from wastewater treatment plants on the Detroit River (Lake Erie) and the Little River (Windsor, Ontario, Canada) sampled in the summer of 2000(6). Based on an average from 7 wastewater treatment plants, an overall removal of 44% has been reported(7).
Indomethacin concentration ranged from 10.4 to 80 ug/kg (8.3% frequency of detection) in 45 Chinese municipal sewage sludge samples from 20 cities in 13 provinces throughout the country(1).
Soil Adsorption/Mobility
Using an Eliot silt loam soil (2.2% organic carbon, pH 6.6), a Koc of 1300 was reported(1). A log Koc of 2.95 (Kd = 32 L/kg), corresponding to a Koc of 891 , was measured using an agricultural soil (pH 6.3) from Corrstown, Co Dublin, Ireland(2). According to a classification scheme(3), these Koc values suggest that indomethacin is expected to have low mobility in soil. The pKa of indomethacin is 4.50(4), indicating that this compound will exist almost entirely in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(5). A Kd value of 214 L/kg was reported using a digester sludge from wastewater treatment plant, Dublin Ireland (pH 6.3)(2). Koc values of 160, 160 and 400 were reported using river sediments from the Akui, Tamiya and Tatara rivers, Japan, respectively(1).
규제 정보
Regulatory Information
Status: Active Update: 28-03-2018 https://echa.europa.eu/registration-dossier/-/registered-dossier/12427
Indomethacin: Does not have an individual approval but may be used under an appropriate group standard
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including indomethacin, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including indomethacin sodium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Indomethacin/
안전 데이터
- wgk
- 3
- tsca
- TSCA listed
- rtecs
- NL3500000
- ridadr
- UN 2811 6.1/PG 1
- 독성
- LD50 i.p. in rats: 13 mg/kg (Klaassen)
- HS 번호
- 29339900
- risk_code
- 28-36/37/38-39/23/24/25-23/24/25
- hazard_code
- T+,Xi,T
- safety_code
- 28-36/37-45-36-26
- 포장분류
- I
- 위험 등급
- 6.1
- 기존화학 물질
- KE-05544
- F 고인화성물질
- 8-10
- Hazard Classifications
- Acute Tox. 1 Oral
- 스토리지 클래스
- 6.1A - Combustible acute toxic Cat. 1 and 2very toxic hazardous materials
- 유해 물질 데이터
- 53-86-1(Hazardous Substances Data)
화학 및 산업
약리 정보
ATC Code
M01AB01
C - Cardiovascular system;C01 - Cardiac therapy;C01E - Other cardiac preparations;C01EB - Other cardiac preparations;C01EB03 - Indometacin
S - Sensory organs;S01 - Ophthalmologicals;S01B - Antiinflammatory agents;S01BC - Antiinflammatory agents, non-steroids;S01BC01 - Indometacin
M - Musculo-skeletal system;M02 - Topical products for joint and muscular pain;M02A - Topical products for joint and muscular pain;M02AA - Antiinflammatory preparations, non-steroids for topical use;M02AA23 - Indometacin
M - Musculo-skeletal system;M01 - Antiinflammatory and antirheumatic products;M01A - Antiinflammatory and antirheumatic products, non-steroids;M01AB - Acetic acid derivatives and related substances;M01AB01 - Indometacin
QM - Musculo-skeletal system;QM02 - Topical products for joint and muscular pain;QM02A - Topical products for joint and muscular pain;QM02AA - Antiinflammatory preparations, non-steroids for topical use;QM02AA23 - Indometacin
Protein BindingIndometacin is a weak organic acid that is 90-99% bound to protein in plasma over the expected range of therapeutic plasma concentrations. Like other NSAIDs, indometacin is bound to plasma albumin but it does not bind to red blood cells.
Pharmacodynamics
Indometacin is an NSAID with analgesic and antipyretic properties that exerts its pharmacological effects by inhibiting the synthesis of factors involved in pain, fever, and inflammation. Its therapeutic action does not involve pituitary-adrenal stimulation. Indometacin primarily works by suppressing inflammation in rheumatoid arthritis by providing relief of pain as well as reducing fever, swelling, and tenderness. This effectiveness has been demonstrated by a reduction in the extent of joint swelling, the average number of joints displaying symptoms of inflammation, and the severity of morning stiffness. Increased mobility was demonstrated by a decrease in total walking time and by improved functional capability seen as an increase in grip strength. In clinical trials, indometacin was shown to be effective in relieving the pain, reducing the fever, swelling, redness, and tenderness of acute gouty arthritis. Due to its pharmacological actions, the use of indometacin is associated with the risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, as well as gastrointestinal effects such as bleeding, ulceration, and perforation of the stomach or intestines. In a study of healthy individuals, acute oral and intravenous indometacin therapy resulted in a transiently diminished basal and CO2 stimulated cerebral blood flow; this effect disappeared in one study after one week of oral treatment. The clinical significance of this effect has not been established. Compared to other NSAIDs, it is suggested that indometacin is a more potent vasoconstrictor that is more consistent in decreasing cerebral blood flow and inhibiting CO2 reactivity. There have been studies that show indometacin directly inhibiting neuronal activity to some extent in the trigeminocervical complex after either superior salivatory nucleus or dural stimulation.
Mechanism of Action
Indometacin is a nonspecific and reversible inhibitor of the cyclo-oxygenase (COX) enzyme or prostaglandin G/H synthase. There are two identified isoforms of COX: COX-1 is universally present in most body tissues and is involved in the synthesis of the prostaglandins and thromboxane A2, while COX-2 is expressed in response to injury or inflammation. Constitutively expressed, the COX-1 enzyme is involved in gastric mucosal protection, platelet, and kidney function by catalyzing the conversion of arachidonic acid to prostaglandin (PG) G2 and PGG2 to PGH2. COX-2 is constitutively expressed and highly inducible by inflammatory stimuli. It is found in the central nervous system, kidneys, uterus, and other organs. COX-2 also catalyzes the conversion of arachidonic acid to PGG2 and PGG2 to PGH2. In the COX-2-mediated pathway, PGH2 is further converted to PGE2 and PGI2 (also known as prostacyclin). PGE2 is involved in mediating inflammation, pain, and fever. Decreasing levels of PGE2 leads to reduced inflammatory reactions. Indometacin is known to inhibit both isoforms of COX, however, with greater selectivity for COX-1, which accounts for its increased adverse gastric effects relative to other NSAIDs. It binds to the enzyme's active site and prevents the interaction between the enzyme and its substrate, arachidonic acid. Indometacin, unlike other NSAIDs, also inhibits phospholipase A2, the enzyme responsible for releasing arachidonic acid from phospholipids. The analgesic, antipyretic and anti-inflammatory effects of indomethacin as well as adverse reactions associated with the drug occur as a result of decreased prostaglandin synthesis. Its antipyretic effects may be due to action on the hypothalamus, resulting in increased peripheral blood flow, vasodilation, and subsequent heat dissipation. The exact mechanism of action of indometacin in inducing closure of a patent ductus arteriosus is not fully understood; however, it is thought to be through inhibition of prostaglan
The anti-inflammatory, analgesic, and antipyretic effects of indomethacin and other nonsteroidal anti-inflammatory drugs (NSAIDs), including selective inhibitors of cyclooxygenase-2 (COX-2) (e.g., celecoxib), appear to result from inhibition of prostaglandin synthesis. While the precise mechanism of the anti-inflammatory and analgesic effects of NSAIAs continues to be investigated, these effects appear to be mediated principally through inhibition of the COX-2 isoenzyme at sites of inflammation with subsequent reduction in the synthesis of certain prostaglandins from their arachidonic acid precursors. This effect may be related to inhibition of the synthesis of prostaglandins that are believed to play a role in modulating the rate and extent of leukocyte infiltration during inflammation. Indomethacin also inhibits lysosomal enzyme release from polymorphonuclear leukocytes. Although the mechanism has not been determined, this effect appears to depend on the nature of the stimulus and may not be related to inhibition of prostaglandin synthesis. It has also been postulated that indomethacin, as an inhibitor of phosphodiesterase, may increase intracellular concentrations of cyclic adenosine monophosphate (AMP) which may play a role in the inflammatory response. In supratherapeutic concentrations, indomethacin depresses the synthesis of mucopolysaccharides through uncoupling of oxidative phosphorylation. By inhibiting cyclooxygenase, indomethacin and some other NSAIAs may also interfere with prostaglandin-mediated formation of autoantibodies that are involved in the inflammatory process.
This article reviews the pathogenic mechanism of non-steroidal anti-inflammatory drug (NSAID)-induced gastric damage, focusing on the relation between cyclooxygenase (COX) inhibition and various functional events. NSAIDs, such as indomethacin, at a dose that inhibits prostaglandin (PG) production, enhance gastric motility, resulting in an increase in mucosal permeability, neutrophil infiltration and oxyradical production, and eventually producing gastric lesions. These lesions are prevented by pretreatment with PGE2 and antisecretory drugs, and also via an atropine-sensitive mechanism, not related to antisecretory action. Although neither rofecoxib (a selective COX-2 inhibitor) nor SC-560 (a selective COX-1 inhibitor) alone damages the stomach, the combined administration of these drugs provokes gastric lesions. SC-560, but not rofecoxib, decreases prostaglandin E2 (PGE2) production and causes gastric hypermotility and an increase in mucosal permeability. COX-2 mRNA is expressed in the stomach after administration of indomethacin and SC-560 but not rofecoxib. The up-regulation of indomethacin-induced COX-2 expression is prevented by atropine at a dose that inhibits gastric hypermotility. In addition, selective COX-2 inhibitors have deleterious influences on the stomach when COX-2 is overexpressed under various conditions, including adrenalectomy, arthritis, and Helicobacter pylori-infection. In summary, gastric hypermotility plays a primary role in the pathogenesis of NSAID-induced gastric damage, and the response, causally related with PG deficiency due to COX-1 inhibition, occurs prior to other pathogenic events such as increased mucosal permeability; and the ulcerogenic properties of NSAIDs require the inhibition of both COX-1 and COX-2, the inhibition of COX-1 upregulates COX-2 expression in association with gastric hypermotility, and PGs produced by COX-2 counteract the deleterious effect of COX-1 inhibition.
Biological Half-Life
Indometacin disposition from the plasma is reported to be biphasic, with a half-life of 1 hour during the initial phase and 2.6–11.2 hours during the second phase. Interindividual and intraindividual variations are possible due to the extensive and sporadic nature of the enterohepatic recycling and biliary discharge of the drug. The mean half-life of oral indomethacin is estimated to be about 4.5 hours. The disposition of intravenous indometacin in preterm neonates was shown to vary across premature infants. In neonates older than 7 days, the mean plasma half-life of intravenous indometacin was approximately 20 hours, ranging from 15 hours in infants weighing more than 1000 g and 21 hours in infants weighing less than 1000 g.
Plasma concentrations of indomethacin have been studied in 5 healthy volunteers after single and multiple doses (25 mg intravenously [iv], 25, 50, and 100 mg orally, 100 mg rectally, and 25 mg three times daily [tid]. In 8 other normal subjects and in 5 patients a 50-mg oral dose of indomethacin was given and the indomethacin concentration was followed from 8 to 32 hr after dosing. ... The half-life of the beta-phase varied between 2.6 and 11.2 hr.
In premature neonates, the serum or plasma elimination half-life of indomethacin is inversely related to postnatal age. In a limited number of neonates, the mean plasma half-life of indomethacin has been reported to be about 20-28 hours in those receiving the drug during the first week of life, compared to about 12-19 hours in those receiving the drug after the first week. The elimination half-life in neonates may also be inversely related to body weight. In one study, the plasma indomethacin half-life showed considerable interindividual variation but averaged 21 hours in neonates weighing less than 1 kg and 15 hours in those weighing more than 1 kg. Total body clearance of indomethacin increases with increasing postnatal age. It was suggested that extensive enterohepatic circulation may commonly occur in premature neonates and may contribute to the relatively long half-life of elimination.
In studies in healthy adults or patients with rheumatoid arthritis, the disappearance of indomethacin from plasma appears to be biphasic with a half-life of approximately 1 hour during the initial phase and 2.6-11.2 hours during the second phase; variations in terminal plasma half-life may be due to individual differences in enterohepatic circulation of the drug. There appears to be no difference between plasma half-life in healthy adults and in rheumatoid arthritis patients.
In one study in healthy adults and patients with arthritis, the half-life for disappearance of indomethacin from synovial fluid was 9 hours.
... Twenty premature infants with gestational age 30.3 +/- 0.3 wk and birth weight, 1209.8 +/- 39.5 g; admitted to the neonatal unit of the Nehru Hospital, Postgraduate Institute of Medical Education and Research (PGIMER), Chandigarh were enrolled in the study. Indomethacin was administered in a single oral dose of 0.2 mg/kg and blood samples were collected through an indwelling vascular catheter at 0 and 1, 2, 4, 8 and 12 hr after administration of indomethacin. Plasma indomethacin concentrations were assayed by spectrofluorometric technique. Large interindividual variability was observed for peak plasma concentrations (Cmax; 137.9 +/- 14.0 ng/mL), elimination half-life (t1/2 el; 21.4 +/- 1.7 hr) and area under the plasma concentrations time curve (AUC0-infinity;4172 +/- 303 ng.hr/mL) in these infants. Variables like birth weight, and sex did not have any sigiificant effect on indomethacin pharmacokinetics. However, the plasma t1/2 el of indomethacin was significantly (P < 0.01) larger in older infants (gestational age > 30 wk) in comparison to younger ones (gestational age </= 30 wk). There was a negative correlation between gestational age and elimination t1/2 (r = -0.77). ...
Metabolism/Metabolites
Indometacin undergoes hepatic metabolism involving glucuronidation, O-desmethylation, and N-deacylation. O-desmethyl-indomethacin, N-deschlorobenzoyl-indomethacin, and O-desmethyl-N-deschlorobenzoyl-indomethacin metabolites and their glucuronides are primarily inactive and have no pharmacological activity. Unconjugated metabolites are also detected in the plasma. Its high bioavailability indicates that indometacin is unlikely to be subject to the first-pass metabolism.
Indomethacin is metabolized in the liver to its glucuronide conjugate and to desmethyl, desbenzoyl, and desmethyl-desbenzoyl metabolites and their glucuronides. These metabolites do not appear to possess anti-inflammatory activity. A portion of the drug is also N-deacylated by a nonmicrosomal system.
Indomethacin has known human metabolites that include (2S,3S,4S,5R)-6-[2-[1-(4-chlorobenzoyl)-5-methoxy-2-methylindol-3-yl]acetyl]oxy-3,4,5-trihydroxyoxane-2-carboxylic acid and O-Desmethylindomethacin.
Hepatic. Route of Elimination: Indomethacin is eliminated via renal excretion, metabolism, and biliary excretion. Half Life: 4.5 hours
FDA Pharmacological Classification
XXE1CET956
INDOMETHACIN
Mechanisms of Action [MoA] - Cyclooxygenase Inhibitors
Chemical Structure [CS] - Anti-Inflammatory Agents, Non-Steroidal
Established Pharmacologic Class [EPC] - Nonsteroidal Anti-inflammatory Drug
Indomethacin is a Nonsteroidal Anti-inflammatory Drug. The mechanism of action of indomethacin is as a Cyclooxygenase Inhibitor.
MeSH Pharmacological Classification
Anti-inflammatory agents that are non-steroidal in nature. In addition to anti-inflammatory actions, they have analgesic, antipyretic, and platelet-inhibitory actions. They act by blocking the synthesis of prostaglandins by inhibiting cyclooxygenase, which converts arachidonic acid to cyclic endoperoxides, precursors of prostaglandins. Inhibition of prostaglandin synthesis accounts for their analgesic, antipyretic, and platelet-inhibitory actions; other mechanisms may contribute to their anti-inflammatory effects.
Agents that affect the rate or intensity of cardiac contraction, blood vessel diameter, or blood volume.
Agents that increase uric acid excretion by the kidney (URICOSURIC AGENTS), decrease uric acid production (antihyperuricemics), or alleviate the pain and inflammation of acute attacks of gout.
Drugs that prevent preterm labor and immature birth by suppressing uterine contractions (TOCOLYSIS). Agents used to delay premature uterine activity include magnesium sulfate, beta-mimetics, oxytocin antagonists, calcium channel inhibitors, and adrenergic beta-receptor agonists. The use of intravenous alcohol as a tocolytic is now obsolete.
Compounds or agents that combine with cyclooxygenase (PROSTAGLANDIN-ENDOPEROXIDE SYNTHASES) and thereby prevent its substrate-enzyme combination with arachidonic acid and the formation of eicosanoids, prostaglandins, and thromboxanes.
Absorption, Distribution and Excretion
Indometacin displays a linear pharmacokinetics profile where the plasma concentrations and area under the curve (AUC) are dose-proportional, whereas half-life (T1/2) and plasma and renal clearance are dose-dependent. Indometacin is readily and rapidly absorbed from the gastrointestinal tract. The bioavailability is virtually 100% following oral administration and about 90% of the dose is absorbed within 4 hours. The bioavailability is about 80-90% following rectal administration. The peak plasma concentrations following a single oral dose were achieved between 0.9 ± 0.4 and 1.5 ± 0.8 hours in a fasting state. Despite large intersubject variation as well using the same preparation, peak plasma concentrations are dose-proportional and averaged 1.54 ± 0.76 μg/mL, 2.65 ± 1.03 μg/mL, and 4.92 ± 1.88 μg/mL following 25 mg, 50 mg, and 75 mg single doses in fasting subjects, respectively. With a typical therapeutic regimen of 25 or 50 mg t.i.d., the steady-state plasma concentrations of indomethacin are an average 1.4 times those following the first dose.
Indometacin is eliminated via renal excretion, metabolism, and biliary excretion. It is also subject to enter the enterohepatic circulation through excretion of its glucuronide metabolites into bile followed by resorption of indometacin after hydrolysis. The extent of involvement in the enterohepatic circulation ranges from 27 to 115%. About 60 percent of an oral dosage is recovered in urine as drug and metabolites (26 percent as indomethacin and its glucuronide), and 33 percent in the feces (1.5 percent as indomethacin).
The volume of distribution ranged from 0.34 to 1.57 L/kg following oral, intravenous, or rectal administration of single and multiple doses of indometacin in healthy individuals. Indometacin is distributed into the synovial fluid and is extensively bound to tissues. It has been detected in human breast milk and placenta. Although indometacin has been shown to cross the blood-brain barrier (BBB), its extensive plasma protein binding allows only the small fraction of free or unbound indometacin to diffuse across the BBB.
In a clinical pharmacokinetic study, the plasma clearance of indometacin was reported to range from 1 to 2.5 mL/kg/min following oral administration.
Patent ductus arteriosus (PDA) is a frequent complication in premature infants. Intravenous indomethacin is the standard mode of medical therapy and has been shown to be efficacious in closing the ductus. In our setup, oral indomethacin is being regularly used for medical treatment of suspected or clinically diagnosed PDA. Non-availability of the parenteral preparation and lack of information regarding the pharmacokinetic disposition of indomethacin in the premature infants in north Indian population led us to conduct this pharmacokinetic study with oral indomethacin. Twenty premature infants with gestational age 30.3 +/- 0.3 wk and birth weight, 1209.8 +/- 39.5 g; admitted to the neonatal unit of the Nehru Hospital, Postgraduate Institute of Medical Education and Research (PGIMER), Chandigarh were enrolled in the study. Indomethacin was administered in a single oral dose of 0.2 mg/kg and blood samples were collected through an indwelling vascular catheter at 0 and 1, 2, 4, 8 and 12 hr after administration of indomethacin. Plasma indomethacin concentrations were assayed by spectrofluorometric technique. Large interindividual variability was observed for peak plasma concentrations (Cmax; 137.9 +/- 14.0 ng/mL), elimination half-life (t1/2 el; 21.4 +/- 1.7 hr) and area under the plasma concentrations time curve (AUC0-infinity;4172 +/- 303 ng.hr/mL) in these infants. Variables like birth weight, and sex did not have any sigiificant effect on indomethacin pharmacokinetics. However, the plasma t1/2 el of indomethacin was significantly (P < 0.01) larger in older infants (gestational age > 30 wk) in comparison to younger ones (gestational age < or = 30 wk). There was a negative correlation between gestational age and elimination t1/2 (r = -0.77). In conclusion, indomethacin pharmacokinetics showed a wide variability in premature infants. In view of these findings it can be suggested that infants of smaller gestational age are at greater risk of cumulative toxicity if more t
Approximately 33% or more of a 25-mg oral dose of indomethacin is excreted in feces principally as demethylated metabolites in their unconjugated forms; 1.5% of fecal drug excretion occurs as indomethacin. Indomethacin and its conjugates undergo enterohepatic circulation.
Cellular LocationsCytoplasm;Extracellular;Membrane
Metabolite PathwaysIndomethacin Action Pathway
용도 및 제조
Uses
MEDICATION
Anti-Inflammatory Agents, Non-Steroidal; Cardiovascular Agents; Cyclooxygenase Inhibitors; Gout Suppressants; Tocolytic Agents
Use (kg) in Switzerland (2009): >100;Use (kg; approx.) in Germany (2009): >1000;Use (kg) in USA (2002): 4630;Consumption (g per capita) in Switzerland (2009): 0.013;Consumption (g per capita; approx.) in Germany (2009): 0.012;Consumption (g per capita) in the USA (2002): 0.016;Excretion rate: 0.275;Calculated removal (%): 78.5
For moderate to severe rheumatoid arthritis including acute flares of chronic disease, ankylosing spondylitis, osteoarthritis, acute painful shoulder (bursitis and/or tendinitis) and acute gouty arthritis.
Methods of Manufacturing
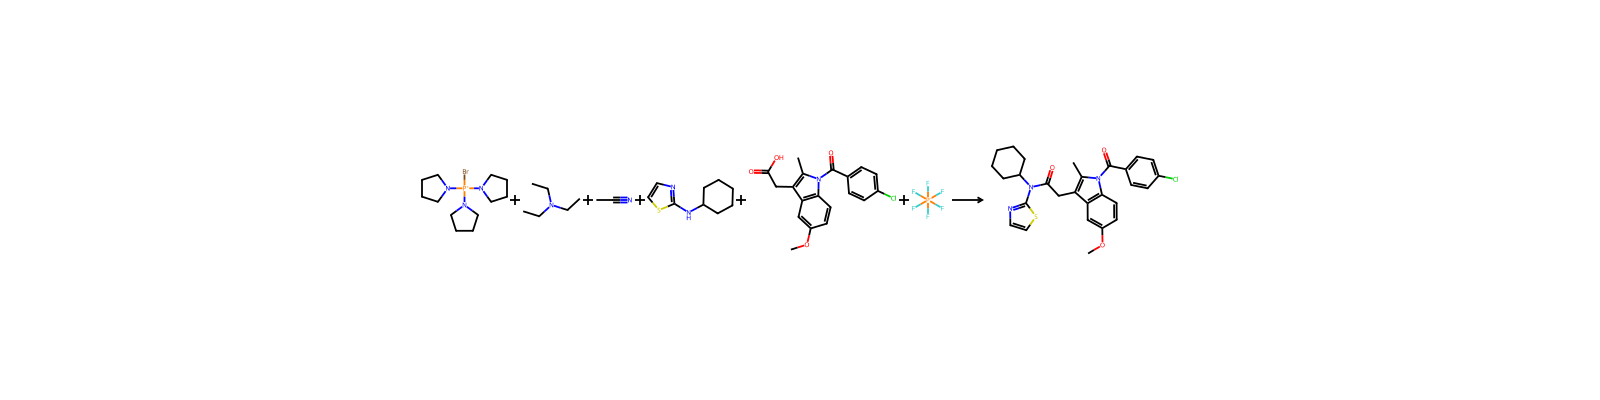
p-Anisidine + ethyl levulinate + p-chlorobenzoyl chloride (diazotisation/hydrogenation/Fischer indole synthesis/amide formation/saponification).
Acylation of sodium 2-(4-methoxy-phenyl)hydrazine-1-sulfonate with 4-chlorobenzoyl chloride followed by heating yields 1-(4- chlorobenzoyl)-1-(4-methoxyphenyl)hydrazine. Condensation with levulinic acid in a Fischer indole synthesis affords indomethacin.
Formulations/Preparations
Table: Indomethacin Preparations [Table#4437]
Table: Indomethacin Sodium Preparations [Table#4438]
Use ClassificationPharmaceuticals
General Manufacturing Information
1H-Indole-3-acetic acid, 1-(4-chlorobenzoyl)-5-methoxy-2-methyl-: ACTIVE
TRANSDERMAL INDOMETHACIN PHARMACEUTICALS CONTAIN POLYOXYETHYLENE ALKYL ETHERS AND/OR POLYOXYETHYLENE ALKYLPHENYL ESTERS (WHICH ARE LIQ AT 25 DEG) AND ACRYLIC ADHESIVES.
응용 분야
개요Aqueous solutions of indomethacin are not stable because of the ease of hydrolysis of the p-chlorobenzoyl group. The original synthesis of indomethacin by Shen et al. involved the formation of 2-methyl-5-methoxyindole acetic acid and subsequent acylation after protection of the carboxyl group as the t-butyl ester. It was introduced in the United States in 1965. It is still one of the most potent NSAIDs in use. It also is a more potent antipyretic than either aspirin or acetaminophen, and it possesses approximately 10 times the analgetic potency of aspirin.
용도Inhibits cyclooxygenase (IC50=0.1uM) selectively over liposygenases (IC50=100uM for 5-,12- and 15-LO). A clinically useful NAISD
일반 설명Crystals.
제조 방법
acylation of sodium 2-(4- methoxyphenyl)hydrazine-1-sulfonate with 4-chlorobenzoyl chloride followed by heating yields 1-(4- chlorobenzoyl)-1-(4- methoxyphenyl)hydrazine. Condensation with levulinic acid in a Fischer indole synthesis affords indomethacin.
상·하류 제품 정보
상류 원료
하류 제품
공급사50 곳
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
湖北威德利化学试剂有限公司181-6332-1995 18062128043 · [email protected]
T&W GROUP021-61551611 13296011611 · [email protected]
上海如吉生物科技发展有限公司+86-21-65211385-8001 36031160 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
Syntechem Co.,Ltd[email protected]
上海迈瑞尔生化科技有限公司4006356688 18621169109 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
阿法埃莎(中国)化学有限公司400-6106006 · [email protected]
太原市瑞和丰科贸有限公司+86 351 7031519 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
武汉菲越生物科技有限公司027-87002654 15827563343
上海柯维化学技术有限公司021-64609169 18901607656 · [email protected]
上海相辉医药科技有限公司13761987713 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
大赛璐药物手性技术(上海)有限公司021-50460086-9 15921403865 · [email protected]
玛雅试剂+86 (573) 82222445 (0)18006601000 452520369 · [email protected]
四川库利南科技有限公司400-1166-196 18981987031 · [email protected]
天津希恩思生化科技有限公司400 638 7771 · [email protected]
湖南汇百侍生物科技有限公司0731-85526065 13308475853 · [email protected]
斯百全化学(上海)有限公司021-021-021-67601398-809-809-809 15221380277 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
艾科试剂4008-755-333 18080918076 · [email protected]
上海思域化工科技有限公司86-21-34053660 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
TCI AMERICA800-4238616 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
TCI Europe320-37350700 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
越林试剂021-62960152 · [email protected]
南京杜莱生物技术有限公司025-84699383-8003;025-846993838003-8003 18013301590 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
深圳市石金谷科技有限公司(0086)755-61930359 (0086)18038192047 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
上海将来实业股份有限公司021-61552785 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
上海笛柏生物科技有限公司400-008-9730,021-54359730 400-008-9730 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
成都零六生物科技有限公司400-1166-196 13458535857 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
추가 설명
정의The antiinflammatory drug indomethacin.
관련 반응
1,025건




연결된 노트
불러오는 중…