
기본 정보
- CAS
61337-67-5- 표준 SMILES
CN1CCN2c3ncccc3Cc3ccccc3C2C1- InChIKey
RONZAEMNMFQXRA-UHFFFAOYSA-N- 분자식
- C17H19N3
- 평균 분자량
- 265.35 g/mol
- 단동위원소 질량
- 265.15789761
개요
Mirtazapine is a benzazepine and a tetracyclic antidepressant. It has a role as a oneirogen, an anxiolytic drug, an alpha-adrenergic antagonist, a H1-receptor antagonist, a histamine antagonist and a serotonergic antagonist.
이름 및 식별자
- 우선 이름
- Mirtazapine
- IUPAC
- 5-methyl-2,5,19-triazatetracyclo[13.4.0.02,7.08,13]nonadeca-1(15),8,10,12,16,18-hexaene
- 영어명
- Mirtazapine
- 분자식
- C17H19N3
- 분자량
- 265.35
이름 및 동의어
mirtazapine85650-52-8RemeronMepirzepine6-AzamianserinRemergonZispinPromyrtilRemergilRexerAvanzaNorset
이름 더 보기
Mirtazapine AnhydrousMIRTAZEPINEMirtazapine CRSMIRTAZANINEMirtazapine-d7
Remeron SolTabMirtazapinaORG 3770MirtazapinumOrg-37702-Methyl-1,2,3,4,10,14b-hexahydropyrazino[2,1-a]pyrido[2,3-c][2]benzazepineMiratazMirtazapin
데이터베이스 식별자
- CAS
61337-67-5、85650-52-8- PubChem CID
- 4205
- DTXSID
DTXSID0023325- ChEMBL
CHEMBL654- ChEBI
CHEBI:6950- UNII
- A051Q2099Q
- EC Number
- 288-060-6、641-354-1
- Nikkaji
- J22.953I
물성
구조 계산 물성
- XLogP
- 3.3
- 극성 표면적
- 19.4 Ų
- 수소 결합 공여자 수
- 0
- 수소 결합 수용자 수
- 3
- 회전 가능 결합 수
- 0
- 무거운 원자 수
- 20
- 형식 전하
- 0
- 복잡도
- 345
실험 및 물리화학적 성질
Drugs
DEA NFLIS-Drug Category -> Antidepressants
Pharmaceuticals
Pharmaceuticals -> Used in Switzerland
Pharmaceuticals -> Tetracyclic Antidepressants (TeCAs)
LogP
2.9
2.82
Solubility
slightly soluble in water
1.10e+00 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Antidepressive Agents; Antidepressive Agents, Second-Generation; Adrenergic alpha-2 Receptor Antagonists; Serotonin 5-HT2 Receptor Antagonists; Serotonin 5-HT3 Receptor Antagonists
FDA approved drugs -> Active ingredient
FDA approved drugs -> Active ingredient
Pharmaceuticals
Animal Drugs
EMA approved medicines: Veterinary medicine
Active Ingredients (Mirtazapine) -> FDA Greenbook
Melting Point
114-116 °C
114 - 116 °C
Physical DescriptionSolid
Dissociation Constants
7.3
7.7
Collision Cross Section161 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
물리화학적 성질
- 녹는점
- 114 · 114-116°C
- 끓는 점
- 432.4 · 432.4±45.0 °C(Predicted)
- 밀도
- 1.22 · 1.22±0.1 g/cm3(Predicted)
- 인화점
- 9 °C · 9°C
- 저장 조건
- 2 · 2-8°C
- 용해도
- 8 mg/mL, · DMSO: ~8mg/mL, 가용성
- 물리적 상태
- 고체
- 산도 계수 (pKa)
- 8.1 · 8.10±0.20(Predicted)
- 색상
- 하얀색
- BCS Class
- 1 · 1
- 주요 응용
- 의약품(소분자)
- InChI
- InChI=1S/C17H19N3/c1-19-9-10-20-16(12-19)15-7-3-2-5-13(15)11-14-6-4-8-18-17(14)20/h2-8,16H,9-12H2,1H3
- InChIKey
- RONZAEMNMFQXRA-UHFFFAOYSA-N
- SMILES
- N12CCN(C)CC1C1=CC=CC=C1CC1=CC=CN=C21
화학적 성질
White Solid
안전 및 규제
안전 정보는 참고용이며, 공급업체의 물질안전보건자료(SDS), 관련 법규 및 전문가 평가를 대체하지 않습니다.
GHS 분류
GHS Classification
Warning
H302 (100%): Harmful if swallowed [Warning Acute toxicity, oral]
P203, P260, P261, P264, P270, P271, P273, P280, P301+P317, P304+P340, P318, P319, P330, P391, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 60 reports by companies from 7 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Warning
H302 (100%): Harmful if swallowed [Warning Acute toxicity, oral]
유해성 정보
Regulatory InformationMirtazapine: Does not have an individual approval but may be used as a component in a product covered by a group standard. It is not approved for use as a chemical in its own right.
Hazard Classes and Categories
Acute Tox. 4 (100%)
Acute Tox. 4 (100%)
독성 정보
Treatment
Treatment should consist of those general measures employed in the management of overdose with any drug effective in the treatment of major depressive disorder. Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm and vital signs. General supportive and symptomatic measures are also recommended. Induction of emesis is not recommended. Gastric lavage with a large-bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion, or in symptomatic patients. Activated charcoal should be administered. There is no experience with the use of forced diuresis, dialysis, hemoperfusion or exchange transfusion in the treatment of mirtazapine overdosage. No specific antidotes for mirtazapine are known. (L1712)
Hepatotoxicity
Liver test abnormalities have been reported to occur in up to 10% of patients on mirtazapine, but elevations are usually modest and rarely require dose modification or discontinuation. Rare instances of acute, clinically apparent episodes of liver injury with marked liver enzyme elevations with or without jaundice have been reported in patients on mirtazapine. The onset of injury has varied greatly from several months to several years. The pattern of serum enzyme elevations is usually hepatocellular, but mixed forms have also been described. Autoimmune (autoantibodies) and immunoallergic features (rash, fever, eosinophilia) are uncommon.
Adverse EffectsMirtazapine has several significant side effects. The adverse effects known to occur in >10% of patients receiving this drug are listed below.
Exposure RoutesOral.
Rapid and complete, but, due to first-pass metabolism, absolute bioavailability is 50%.
Toxicity Summary
Mirtazapine is a relatively safe drug, although it is slightly more toxic than most SSRIs (except citalopram). Few fatalities have been attributed to an overdose of mirtazapine. The reported fatal toxicity index for mirtazapine is 3.1 deaths per million prescriptions (95% CI), which is relatively similar to that observed with SSRIs. One study involving mirtazapine overdose in 267 patients reported that tachycardia, mild hypertension, and mild CNS depression are associated with overdose, and patients ingesting other substances with mirtazapine experienced more severe toxicity.
Mirtazapine acts as an antagonist at central pre-synaptic alpha(2)-receptors, inhibiting negative feedback to the presynaptic nerve and causing an increase in NE release. Blockade of heteroreceptors, alpha(2)-receptors contained in serotenergic neurons, enhances the release of 5-HT, increasing the interactions between 5-HT and 5-HT<sub>1</sub> receptors and contributing to the anxiolytic effects of mirtazapine. Mirtazapine also acts as a weak antagonist at 5-HT<sub>1</sub> receptors and as a potent antagonist at 5-HT<sub>2</sub> (particularly subtypes 2A and 2C) and 5-HT<sub>3</sub> receptors. Blockade of these receptors may explain the lower incidence of adverse effects such as anxiety, insomnia, and nausea. Mirtazapine also exhibits significant antagonism at H1-receptors, resulting in sedation. Mirtazapine has no effects on the reuptake of either NE or 5-HT and has only minimal activity at dopaminergic and muscarinic receptors.
Signs and SymptomsSymptoms of overdose include disorientation, drowsiness, impaired memory, and tachycardia.
Carcinogen ClassificationNo indication of carcinogenicity to humans (not listed by IARC).
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Mirtazapine
vLess-DILI-concern
3
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Effects During Pregnancy and Lactation
◉ Summary of Use during Lactation
◈ What is mirtazapine?
Toxicity DataLD50: 600-720mg/kg (oral, mice) (L1855)
LD50: 320-490mg/kg (oral, rat) (L1855)
안전 데이터
- wgk
- 3
- rtecs
- UQ4410250
- ridadr
- UN1230 - class 3 - PG 2 - Methanol, solution
- HS 번호
- 29339900
- risk_code
- 22
- hazard_code
- Xn
- safety_code
- 22-24/25
- Hazard Classifications
- Acute Tox. 4 OralSTOT SE 3
- 스토리지 클래스
- 11 - Combustible Solids
화학 및 산업
약리 정보
ATC Code
N06AX11
N - Nervous system
QN - Nervous system
Protein BindingMirtazapine is about 85% bound to plasma proteins.
Pharmacodynamics
**General effects and a note on suicidality** Mirtazapine is effective in treating moderate to severe depression and treats many symptoms normally associated with this condition. These symptoms may include disturbed sleep, lack of appetite, and anhedonia, in addition to anxiety.. It is important to note that suicidal ideation and behavior may emerge or increase during treatment with mirtazapine, as with any other antidepressant. This risk is especially pronounced in younger individuals. Patients, medical professionals, and families should monitor for suicidal thoughts, worsening depression, anxiety, agitation, sleep changes, irritable behavior, aggression, impulsivity, restlessness, and other unusual behavior when this drug is taken or the dose is adjusted. Do not administer mirtazapine to children. When deciding to prescribe this drug, carefully consider the increased risk of suicidal thoughts and behavior, especially in young adults. **Effects on appetite and weight gain** In addition to the above effects, mirtazapine exerts stimulating effects on appetite, and has been used for increasing appetite and decreasing nausea in cancer patients. Some studies and case reports have shown that this drug improves eating habits and weight gain in patients suffering from anorexia nervosa when administered in conjunction with psychotherapy and/or other psychotropic drugs. In a clinical trial, women with depression experienced a clinically significant mean increase in body weight, fat mass, and concentrations of leptin when treated with mirtazapine for a 6-week period, with a lack of effect on glucose homeostasis. **Effects on sleep** The use of mirtazapine to treat disordered sleep has been leveraged from its tendency to cause somnolence, which is a frequently experienced adverse effect by patients taking this drug. Mirtazapine has been shown to exert beneficial effects on sleep latency, duration, and quality due to its sedating properties. Insomnia is a common occurrence in patients with depression, and mirtazapine has been found to be efficacious in treating this condition.
Mechanism of Action
**Summary** The mechanism of action of mirtazapine is not fully understood but may be explained by its effects on central adrenergic and serotonergic activity. This drug exhibits a fast onset of action, a high level of response, a manageable side-effect profile, and dual noradrenergic and serotonergic effects that are unique from the effects of other antidepressants. **Effects on various receptors** It has been shown that both noradrenergic and serotonergic activity increase following mirtazapine administration. The results of these studies demonstrate mirtazapine exerts antagonist activity at presynaptic α2-adrenergic inhibitory autoreceptors and heteroreceptors in the central nervous system. This is thought to lead to enhanced noradrenergic and serotonergic activity, which are known to improve the symptoms of depression and form the basis of antidepressant therapy. Mirtazapine is a strong antagonist of serotonin 5-HT2 and 5-HT3 receptors. It has not been found to bind significantly to the serotonin 5-HT1A and 5-HT1B receptors but indirectly increases 5-HT1A transmission. In addition to the above effects, mirtazapine is a peripheral α1-adrenergic antagonist. This action may explain episodes of orthostatic hypotension that have been reported after mirtazapine use. Mirtazapine is a potent histamine (H1) receptor antagonist, which may contribute to its powerful sedating effects. The pain-relieving effects of mirtazapine may be explained by its effects on opioid receptors.
Biological Half-Life20-40 hours
Metabolism/Metabolites
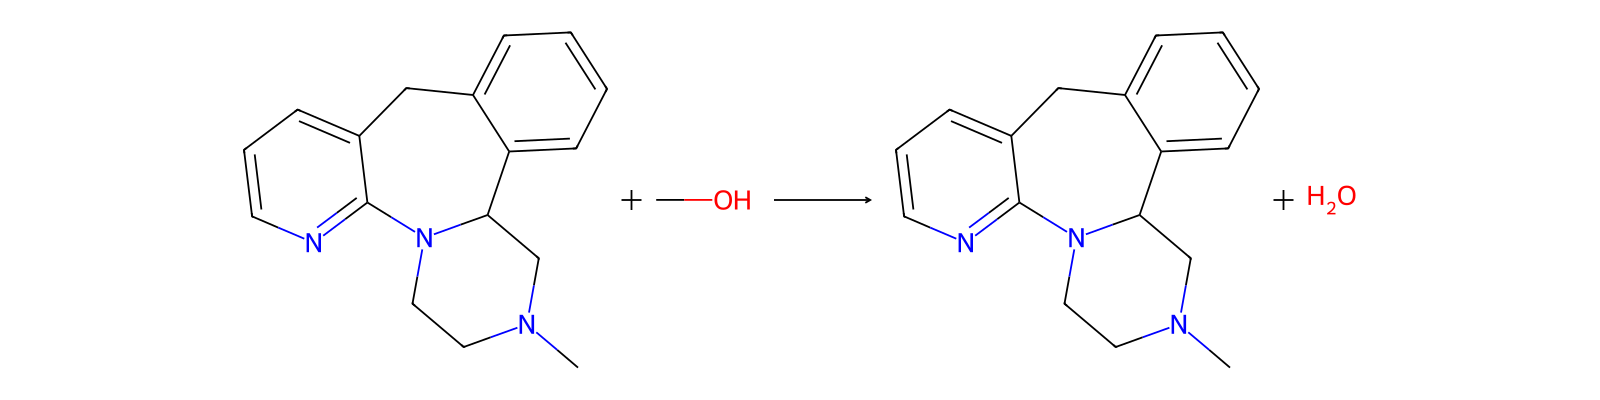
Mirtazapine is heavily metabolized in humans. Demethylation and hydroxylation and subsequent glucuronide conjugation are the major pathways by which mirtazapine is metabolized. Data from in vitro studies on human liver microsomes show that cytochrome 2D6 and 1A2 lead to the formation of the _8-hydroxy metabolite_ of mirtazapine. The CYP3A enzyme metabolizes this drug into its _N-desmethyl and N-oxide_ metabolites. There are various other unconjugated metabolites of this drug that are pharmacologically active, but are measured in the blood at limited concentrations.
Mirtazapine has known human metabolites that include N-Desmethylmirtazapine, Mirtazapine N-oxide, and 8-hydroxy-mirtazapine.
Mirtazapine is extensively metabolized by demethylation and hydroxylation followed by glucuronide conjugation. Cytochrome P450 2D6 and cytochrome P450 1A2 are involved in formation of the 8-hydroxy metabolite of mirtazapine, and cytochrome P450 3A4 is responsible for the formation of the N-desmethyl and N-oxide metabolites. Several metabolites possess pharmacological activity, but plasma levels are very low. Route of Elimination: This drug is known to be substantially excreted by the kidney (75%). Half Life: 20-40 hours
MeSH Pharmacological Classification
Mood-stimulating drugs used primarily in the treatment of affective disorders and related conditions. Several MONOAMINE OXIDASE INHIBITORS are useful as antidepressants apparently as a long-term consequence of their modulation of catecholamine levels. The tricyclic compounds useful as antidepressive agents (ANTIDEPRESSIVE AGENTS, TRICYCLIC) also appear to act through brain catecholamine systems. A third group (ANTIDEPRESSIVE AGENTS, SECOND-GENERATION) is a diverse group of drugs including some that act specifically on serotonergic systems.
Drugs that selectively bind to but do not activate histamine H1 receptors, thereby blocking the actions of endogenous histamine. Included here are the classical antihistaminics that antagonize or prevent the action of histamine mainly in immediate hypersensitivity. They act in the bronchi, capillaries, and some other smooth muscles, and are used to prevent or allay motion sickness, seasonal rhinitis, and allergic dermatitis and to induce somnolence. The effects of blocking central nervous system H1 receptors are not as well understood.
Agents that alleviate ANXIETY, tension, and ANXIETY DISORDERS, promote sedation, and have a calming effect without affecting clarity of consciousness or neurologic conditions. ADRENERGIC BETA-ANTAGONISTS are commonly used in the symptomatic treatment of anxiety but are not included here.
Drugs that bind to and block the activation of ADRENERGIC ALPHA-2 RECEPTORS.
Drugs that bind to but do not activate SEROTONIN 5-HT2 RECEPTORS, thereby blocking the actions of SEROTONIN or SEROTONIN 5-HT2 RECEPTOR AGONISTS. Included under this heading are antagonists for one or more specific 5-HT2 receptor subtypes.
Drugs that bind to but do not activate SEROTONIN 5-HT3 RECEPTORS, thereby blocking the actions of SEROTONIN or SEROTONIN 5-HT3 RECEPTOR AGONISTS.
Absorption, Distribution and Excretion
The absorption of this drug is rapid and complete. Due to first pass metabolism in the liver and metabolism in the gut wall, absolute bioavailability is about 50%. Peak blood concentrations are attained within about 2 hours after an oral dose. Food has little effect on the absorption of mirtazapine, and no dose adjustment is required if it is taken with food. Steady-state levels are achieved by about 5 days after the initial dose. Mirtazapine pharmacokinetics vary across gender and age range. Females and the elderly population have been shown to have higher blood concentrations in comparison to males and younger adults.
This drug is mainly excreted by the kidney. It is 75% eliminated in the urine and 15% eliminated in the feces.
The volume of distribution after an oral steady-state dose was measured to be 107 ± 42L in a pharmacokinetic study.
Total body clearance in males was found to be 31 L/h in a clinical pharmacokinetics study after intravenous administration. **Clearance in elderly patients*
Cellular LocationsMembrane
Metabolite PathwaysMirtazapine H1-Antihistamine Action
용도 및 제조
Uses
Use (kg; approx.) in Germany (2009): >2500
For the treatment of major depressive disorder.
Use Classification
Animal Drugs -> FDA Approved Animal Drug Products (Green Book) -> Active Ingredients
Pharmaceuticals -> Nervous System -> Antidepressants
Pharmaceuticals
응용 분야
용도Mirtazapine (Remeron, Avanza) is a potent tetracyclic antidepressant. Mirtazapine (Remeron, Avanza) used primarily in the treatment of depression. It is also sometimes used as a hypnotic, antiemetic, and appetite stimulant, and for the treatment of anxiet
일반 설명Mirtazapine is a tetracyclic antidepressant marketed under the trade names Remeron, Avanza, or Zispin for treatment of depression.This Certified Spiking Solution is suitable for LC/MS or GC/MS applications in forensic analysis, clinical toxicology, or urine drug testing.
상·하류 제품 정보
상류 원료
공급사100 곳
北京华美互利生物化工010-56205725 · [email protected]
湖北永阔科技有限公司027-59223108 15972152991 · [email protected]
湖北万得化工有限公司15377098680 15377098680 · [email protected]
武汉英诺医药科技有限公司+86-027-59232304 15387063101 · [email protected]
深圳市健竹科技有限公司0755-89218110 13480856786
山东海舟生物工程有限公司130-0567-0367 13006570367 · [email protected]
河南赢创生物科技有限公司16650615803 · [email protected]
咸宁深蓝生物医药研发有限公司18171815831 · [email protected]
湖北海克斯生化有限公司17362916295; 17362916295 · [email protected]
普善实业(陕西)有限公司029-81310890 18165209495 · [email protected]
湖北海克斯生化有限公司18696113233 · [email protected]
Baoji Guokang Healthchem co.,ltd+8615604608665 15604608665 · [email protected]
湖北科乐精细化工有限公司027-59101668 19945030958 · [email protected]
Dayang Chem (Hangzhou) Co.,Ltd.+86-0571-88938639 17705817739 · [email protected]
南京世洲生物科技有限公司025-025-85560043 17301488900 · [email protected]
Hangzhou Verychem Science And Technology Co.Ltd+86-86-57188162785 +8613606544505 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
湖北辰心化工有限公司18696113233 · [email protected]
石家庄感拓生物科技有限公司[email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
广州蒂嚎医药科技有限公司18602015453 · [email protected]
武汉菲越生物科技有限公司027-87002654 15827563343 · [email protected]
广州旺晟生物科技有限公司020-87317062 13048089691 · [email protected]
Ascent Scientific4401179829988 · [email protected]
上海泰坦科技股份有限公司4006009262 13023226327 · [email protected]
湖北广奥生物科技有限公司027-02702759223056 18162699093 · [email protected]
Zhejiang J&C Biological Technology Co.,Limited+1-2135480471 · [email protected]
武汉市皇臻生物化工有限公司13795480948 · [email protected]
河北茹麒科技有限公司176-03256889 17603256889 · [email protected]
湖北成海化工有限公司027-59220433 18327245847 · [email protected]
Xiamen AmoyChem Co., Ltd+86-86-5926051114 · [email protected]
Hubei Datong Bio-Chemical Technology Co.,Ltd027-87666700 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
上海陶素生化科技有限公司021-33632979 · [email protected]
南京世洲生物科技有限公司13675144456 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
上海石洋化工有限公司021-56795766 · [email protected]
天津普西唐生物医药科技有限公司010-60605840 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
上海永叶生物科技有限公司86-021-61559134 15921386130 · [email protected]
上海孚一生物科技有限公司+86 (21) 61124340
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
江苏倍达医药科技有限公司0512-63009836 18994340901 · [email protected]
上海昕凯医药科技有限公司21-619849051-1 18521059765 · [email protected]
西安美川生物科技有限公司029-89275612 +8618991951683 · [email protected]
武汉鑫儒化工有限公司15927387915 15337108568 · [email protected]
厦门志信化学有限公司+86-5922680277 +86-13806087780 · [email protected]
湖北辰心化工有限公司17362916295 · [email protected]
관련 반응
6건


화합물 노트
불러오는 중…