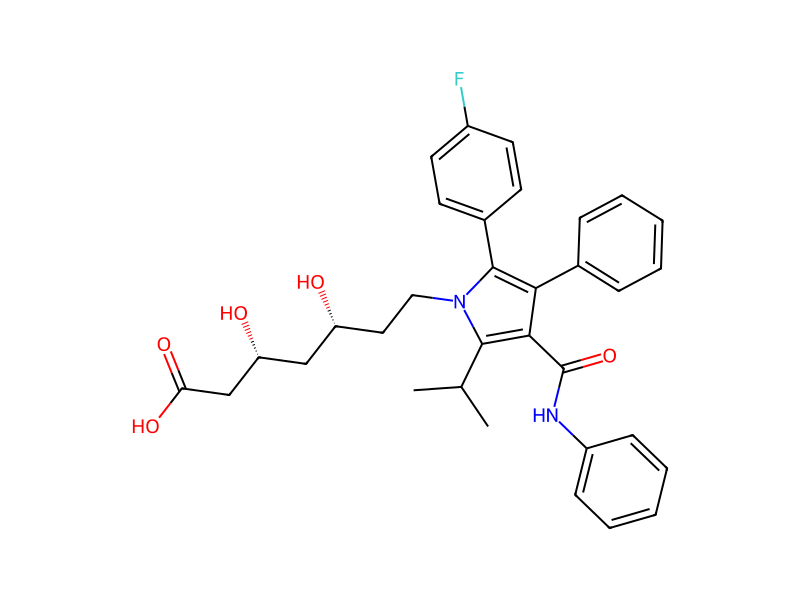
기본 정보
- 표준 SMILES
CC(C)c1c(C(=O)Nc2ccccc2)c(-c2ccccc2)c(-c2ccc(F)cc2)n1CC[C@@H](O)C[C@@H](O)CC(=O)O- InChIKey
XUKUURHRXDUEBC-KAYWLYCHSA-N- 분자식
- C33H35FN2O5
- 평균 분자량
- 558.6 g/mol
- 단동위원소 질량
- 558.25300038
이름 및 식별자
- 우선 이름
- Atorvastatin
- IUPAC
- (3R,5R)-7-[2-(4-fluorophenyl)-3-phenyl-4-(phenylcarbamoyl)-5-propan-2-ylpyrrol-1-yl]-3,5-dihydroxyheptanoic acid
- 현지명
- 아토르바스타틴
- 영어명
- Atorvastatin
- 분자식
- C33H35FN2O5
- 분자량
- 558.65
이름 및 동의어
atorvastatin134523-00-5CardylatorvastatinaatorvastatineSortis(3R,5R)-7-(2-(4-Fluorophenyl)-5-isopropyl-3-phenyl-4-(phenylcarbamoyl)-1H-pyrrol-1-yl)-3,5-dihydroxyheptanoic acidatorvastatinumPrevencorZaratorDTXSID8029868A0JWA85V8F
이름 더 보기
아토르바스타틴ATORVASTATIN CAAtorvastatin (Subject to Patent free)ATORVASTATIN CALCIUM SALTAtorvastatin acidATORVASTATIN DIPROTECTEDAtorvastatin CalciuM Tablets(3r,5r)-7-[2-(4-fluorophenyl)-3-phenyl-4-(phenylcarbamoyl)-5-propan-2-yl-pyrrol-1-yl]-3,5-dihydroxy-heptanoic acidAtrovastitne025-83371857
(3R,5R)-7-[2-(4-fluorophenyl)-3-phenyl-4-(phenylcarbamoyl)-5-(propan-2-yl)-1H-pyrrol-1-yl]-3,5-dihydroxyheptanoic acidDTXCID509868(betaR,deltaR)-2-(p-Fluorophenyl)-beta,delta-dihydroxy-5-isopropyl-3-phenyl-4-(phenylcarbamoyl)pyrrole-1-heptanoic acid(R-(R*,R*))-2-(4-Fluorophenyl)-beta,delta-dihydroxy-5-(1-methylethyl)-3-phenyl-4-((phenylamino)carbonyl)-1H-pyrrole-1-heptanoic acidCHEBI:395481H-Pyrrole-1-heptanoic acid, 2-(4-fluorophenyl)-beta,delta-dihydroxy-5-(1-methylethyl)-3-phenyl-4-((phenylamino)carbonyl)-, (R-(R*,R*))-1H-Pyrrole-1-heptanoic acid, 2-(4-fluorophenyl)-beta,delta-dihydroxy-5-(1-methylethyl)-3-phenyl-4-((phenylamino)carbonyl)-, (betaR,deltaR)-CI981
데이터베이스 식별자
- CAS
134523-00-5、134523-03-8- PubChem CID
- 60823
- DTXSID
DTXSID8029868- ChEMBL
CHEMBL1487- ChEBI
CHEBI:39548- UNII
- A0JWA85V8F
- EC Number
- 806-698-0
- Nikkaji
- J596.930A
물성
구조 계산 물성
- XLogP
- 5
- 극성 표면적
- 112 Ų
- 수소 결합 공여자 수
- 4
- 수소 결합 수용자 수
- 6
- 회전 가능 결합 수
- 12
- 무거운 원자 수
- 41
- 형식 전하
- 0
- 복잡도
- 822
실험 및 물리화학적 성질
LogP6.36
SolubilityPractically insoluble
Boiling Point722
Melting Point
176
159.1 - 190.6 °C
Optical Rotation
White to off-white crystalline powder. Specific optical rotation at 25 °C for D (sodium) line = -7.4 deg (c = 1 in DMSO). Freely soluble in methanol; slightly soluble in ethanol; very slightly soluble in acetonitrile, distilled water, phosphate buffer (pH 7.4). Insoluble in aqueous solutions of pH 4 and below. /Atorvastatin calcium salt trihydrate/
Physical DescriptionSolid
Stability/Shelf LifeStable under recommended storage conditions. /Atorvastatin calcium salt trihydrate/
Dissociation Constants
4.46
4.54
4.46
Collision Cross Section
224.3 Ų [M]+ [CCS Type: DT; Buffer gas: N2; Ionization: APCI+; Dataset: TOXCAST; Source Identifier: DTXSID6044303];231.4 Ų [M+Na]+ [CCS Type: DT; Buffer gas: N2; Ionization: ESI+; Dataset: TOXCAST; Source Identifier: DTXSID8029868];229.7 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: ESI+; Dataset: TOXCAST; Source Identifier: DTXSID8029868];232.2 Ų [M+Na]+ [CCS Type: DT; Buffer gas: N2; Ionization: ESI+; Dataset: TOXCAST; Source Identifier: DTXSID6044303];229.1 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: APCI+; Dataset: TOXCAST; Source Identifier: DTXSID8029868];228.4 Ų [M-H]- [CCS Type: DT; Buffer gas: N2; Ionization: ESI-; Dataset: TOXCAST; Source Identifier: DTXSID8029868];228.6 Ų [M-H]- [CCS Type: DT; Buffer gas: N2; Ionization: ESI-; Dataset: TOXCAST; Source Identifier: DTXSID6044303];229.8 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: APCI+; Dataset: TOXCAST; Source Identifier: DTXSID6044303];230.3 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: ESI+; Dataset: TOXCAST; Source Identifier: DTXSID6044303]
213.25 Ų [M+H-H2O]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards];229.87 Ų [M+Na]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards];231.37 Ų [M+K]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards];231.29 Ų [M+H]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
233 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
233.34 Ų [M+H]+;231.92 Ų [M-H]-;233.2 Ų [M+Na]+
Other Experimental Properties
pKa= 4.46. Solubility in water (30 °C) = 20.4 ug/mL (pH 2.1); 1.23 mg/mL (pH 6.0) /Atorvastatin sodium salt/
MP: 159.2-160.7 °C. Specific optical rotation: +26.05 deg at 25 °C/D (c = 1 in chloroform) /Atorvastatin lactone/
물리화학적 성질
- 녹는점
- 176 · 176-178°C
- 끓는 점
- 722.2 · 722.2±60.0 °C(Predicted)
- 밀도
- 1.23 · 1.23±0.1 g/cm3(Predicted)
- 저장 조건
- 2 · 2-8°C
- 용해도
- 100 mg/mL · DMSO: 100 mg/mL (179.01 mM)
- 물리적 상태
- Solid
- 산도 계수 (pKa)
- 4.46 · pKa 4.46(H2O t=30 Iuncontrolled) (Uncertain)
- 색상
- White to light yellow
- 주요 응용
- 제약
- InChIKey
- XUKUURHRXDUEBC-FQWVHLSFNA-N
- SMILES
- C(C1=C(N(CC[C@@H](O)C[C@@H](O)CC(=O)O)C(C2C=CC(F)=CC=2)=C1C1C=CC=CC=1)C(C)C)(=O)NC1C=CC=CC=1 |&1:6,9,r|
- EPA
- 1 H-Pyrrole-1-heptanoic · 1H-Pyrrole-1-heptanoic acid, 2-(4-fluorophenyl)-?,?-dihydroxy-5-(1-methylethyl)-3-phenyl-4-[(phenylamino)carbonyl]-, (?R,?R)- (134523-00-5)
화학적 성질
white Crystalline powder
안전 및 규제
GHS 분류
GHS Classification
Warning
H315 (66.7%): Causes skin irritation [Warning Skin corrosion/irritation];H319 (66.7%): Causes serious eye irritation [Warning Serious eye damage/eye irritation];H335 (66.7%): May cause respiratory irritation [Warning Specific target organ toxicity, single exposure; Respiratory tract irritation];H361 (33.3%): Suspected of damaging fertility or the unborn child [Warning Reproductive toxicity];H361f (33.3%): Suspected of damaging fertility [Warning Reproductive toxicity];H361fd (33.3%): Suspected of damaging fertility; Suspected of damaging the unborn child [Warning Reproductive toxicity];H362 (66.7%): May cause harm to breast-fed children [Reproductive toxicity, effects on or via lactation]
P203, P260, P261, P263, P264, P264+P265, P270, P271, P280, P302+P352, P304+P340, P305+P351+P338, P318, P319, P321, P332+P317, P337+P317, P362+P364, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 3 reports by companies from 3 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.;Information may vary between notifications depending on impurities, additives, and other factors. The percentage value in parenthesis indicates the notified classification ratio from companies that provide hazard codes. Only hazard codes with percentage values above 10% are shown. For more detailed information, please visit ECHA C&L website.
유해성 정보
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including atorvastatin calcium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Atorvastatin calcium/
Toxic Combustion ProductsSpecial hazards arising from the substance or mixture: Carbon oxides, nitrogen oxides (NOx), hydrogen fluoride, calcium oxide /Atorvastatin calcium salt trihydrate/
Hazard Classes and CategoriesSkin Irrit. 2 (66.7%);Eye Irrit. 2 (66.7%);STOT SE 3 (66.7%);Repr. 2 (33.3%);Repr. 2 (33.3%);Lact. (66.7%)
Hazardous Reactivities and IncompatibilitiesIncompatible materials: Strong oxidizing agents. /Atorvastatin calcium salt trihydrate/
안전 및 보호
Fire Fighting Procedures
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide. /Atorvastatin calcium salt trihydrate/
Advice for firefighters: Wear self-contained breathing apparatus for firefighting if necessary. /Atorvastatin calcium salt trihydrate/
Storage Conditions
Keep container tightly closed in a dry and well-ventilated place. Light sensitive. /Atorvastatin calcium salt trihydrate/
Store at controlled room temperature 20-25 °C.
Cleanup Methods
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Use personal protective equipment. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Avoid breathing dust. Environmental precautions: Do not let product enter drains. Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal. /Atorvastatin calcium salt trihydrate/
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company; Contaminated packaging: Dispose of as unused product. /Atorvastatin calcium salt trihydrate/
Preventive Measures
ACCIDENTAL RELEASE MEASURES: Personal precautions, protective equipment and emergency procedures: Use personal protective equipment. Avoid dust formation. Avoid breathing vapors, mist or gas. Ensure adequate ventilation. Avoid breathing dust. Environmental precautions: Do not let product enter drains. /Atorvastatin calcium salt trihydrate/
Precautions for safe handling: Avoid contact with skin and eyes. Avoid formation of dust and aerosols. Provide appropriate exhaust ventilation at places where dust is formed. /Atorvastatin calcium salt trihydrate/
Appropriate engineering controls: Handle in accordance with good industrial hygiene and safety practice. Wash hands before breaks and at the end of workday. /Atorvastatin calcium salt trihydrate/
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands. /Atorvastatin calcium salt trihydrate/
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Personal Protective Equipment (PPE)
Eye/face protection: Safety glasses with side-shields conforming to EN166. Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU). /Atorvastatin calcium salt trihydrate/
Skin protection: Handle with gloves. /Atorvastatin calcium salt trihydrate/
Body Protection: Impervious clothing. The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace. /Atorvastatin calcium salt trihydrate/
Respiratory protection: For nuisance exposures use type P95 (US) or type P1 (EU EN 143) particle respirator. For higher level protection use type OV/AG/P99 (US) or type ABEK-P2 (EU EN 143) respirator cartridges. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU). /Atorvastatin calcium salt trihydrate/
독성 정보
Interactions
Concomitant use of atorvastatin with efavirenz may result in reductions in plasma concentrations of atorvastatin. Following concomitant use of atorvastatin (10 mg daily for 3 days) and efavirenz (600 mg once daily for 14 days), atorvastatin peak plasma concentration and AUC were decreased by 1 and 41%, respectively.
Concomitant use of atorvastatin (80 mg once daily for 14 days) and digoxin (0.25 mg once daily for 20 days) resulted in 20 and 15% increases in digoxin peak plasma concentration and AUC, respectively. Therefore, patients receiving such concomitant therapy should be monitored appropriately.
Concomitant use of atorvastatin and azole antifungals (e.g., itraconazole) increases the risk of myopathy or rhabdomyolysis. Following concomitant use of atorvastatin (40 mg as a single dose) and itraconazole (200 mg once daily for 4 days), atorvastatin peak plasma concentration and area under the plasma concentration-time curve (AUC) were increased by 20% and 3.3-fold, respectively. Clinicians considering concomitant use of atorvastatin and itraconazole or other azole antifungals should weigh the benefits and risks of such concomitant therapy. During concomitant therapy with itraconazole, the lowest necessary dosage of atorvastatin should be employed, and dosage of atorvastatin should not exceed 20 mg daily. Patients receiving concomitant therapy with atorvastatin and azole antifungals should be monitored for manifestations of muscle pain, tenderness, or weakness, particularly during the initial months of therapy and following an increase in dosage of either drug.
Concomitant use of atorvastatin and cyclosporine increases the risk of myopathy or rhabdomyolysis. Following concomitant use of atorvastatin (10 mg daily for 28 days) and cyclosporine (5.2 mg/kg daily), atorvastatin peak plasma concentration and AUC were increased by 10.7- and 8.7-fold, respectively. Concomitant use of atorvastatin and cyclosporine should be avoided.
For more Interactions (Complete) data for ATORVASTATIN (27 total), please visit the HSDB record page.
Hepatotoxicity
Atorvastatin therapy is associated with mild, asymptomatic and usually transient serum aminotransferase elevations in 1% to 3% of patients but levels above 3 times ULN in less than 1%. In summary analyses of large scale studies with prospective monitoring, ALT elevations above 3 times the upper limit of normal (ULN) occurred in 0.7% of atorvastatin treated versus 0.3% of placebo recipients. These elevations were more common with higher doses of atorvastatin, being 2.3% with 80 mg daily. Most elevations were self-limited and did not require dose modification.;Atorvastatin is also associated with frank, clinically apparent hepatic injury but this is rare, occurring in approximately 1 in 10,000 treated patients. The clinical presentation of atorvastatin hepatotoxicity varies greatly from simple cholestatic hepatitis to mixed forms, to frankly hepatocellular injury. The latency to onset of injury is also highly variable ranging from 1 month to several years. However, most cases arise within 6 months of starting atorvastatin or several months after a dose escalation. The most common presentation is a cholestatic hepatitis that tends to be mild-to-moderate in severity and self-limiting in course (Cases 1 and 2). Atorvastatin hepatotoxicity can also present with a distinctly hepatocellular pattern of injury with marked elevations in serum aminotransferase levels and minimal or no increase in alkaline phosphatase. Rash, fever and eosinophilia are uncommon, but at least one-third of hepatocellular cases have features of autoimmunity, marked by high immunoglobulin levels, ANA or SMA positivity and liver biopsy findings that resemble autoimmune hepatitis (Cases 3 and 4). These autoimmune cases usually resolve once atorvastatin is stopped, although they may require corticosteroid therapy for resolution. Strikingly, however, some cases of apparent autoimmune hepatitis caused by atorvastatin do not resolve with stopping the medication but are self-sustained and require long term immunosuppressive therapy. It is unclear whether these cases of persistent autoimmune hepatitis are caused by the statin therapy or are triggered by statin in a susceptible host. Another possibility is that the association is coincidental and represents a de novo onset of autoimmune hepatitis in someone who happens to be taking a statin.;Likelihood score: A (well known cause of clinically apparent liver injury).
Ecotoxicity Values
EC50; Species: Xenopus laevis (African Clawed Frog) blastula; Conditions: freshwater, renewal, 23 °C, pH 6.5-9, hardness 16-400 mg/L CaCO3; Concentration: 23100 ug/L for 96 hr; Effect: development, increased deformation /98.0% purity/
EC50; Species: Hyalella azteca (Scud) age 7-14 days; Conditions: freshwater, renewal, 22.4 °C, pH 7.7, hardness 0.13 mmol, dissolved oxygen 6.5 mg/L; Concentration: 2400 ug/L for 10 days (95% confidence interval: 1300-3560 ug/L); Effect: growth, decreased weight /> or=99% purity/
LC50; Species: Hyalella azteca (Scud) age 7-14 days; Conditions: freshwater, renewal, 22.4 °C, pH 7.7, hardness 0.13 mmol, dissolved oxygen 6.5 mg/L; Concentration: 1500 ug/L for 10 days (95% confidence interval: 1100-1970 ug/L) /> or=99% purity/
EC50; Species: Lemna gibba (Inflated Duckweed); Conditions: freshwater, renewal, 25 °C; Concentration: 214 ug/L for 7 days (95% confidence interval: 157-272 ug/L); Effect: growth, decreased biomass /98% purity/
For more Ecotoxicity Values (Complete) data for ATORVASTATIN (10 total), please visit the HSDB record page.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 400(SRC), determined from an estimated log Kow of 6.36(2) and a regression-derived equation(2), indicates that atorvastatin is expected to have moderate mobility in soil(SRC). The estimated pKa1 of atorvastatin is 4.3(3), indicating that this compound will exist partially in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization of atorvastatin from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 2.4X10⁻²³ atm-cu m/mole(SRC), using a fragment constant estimation method(5). Atorvastatin is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 7.0X10⁻²⁵ mm Hg at 25 °C(SRC), determined from a fragment constant method(2). 80-90% removal during aerobic wastewater treatment(6) suggests that biodegradation may be an important environmental fate process in soil(SRC).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 400(SRC), determined from an estimated log Kow of 6.36(2) and a regression-derived equation(2), indicates that atorvastatin is expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(3) based upon an estimated Henry's Law constant of 2.4X10⁻²³ atm-cu m/mole(SRC), developed using a fragment constant estimation method(4). According to a classification scheme(5), an estimated BCF of 60(SRC), from its estimated log Kow(2) and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is moderate(SRC). 80-90% removal during aerobic wastewater treatment(6) suggests that biodegradation may be an important environmental fate process in water(SRC).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), atorvastatin, which has an estimated vapor pressure of 7.0X10⁻²⁵ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase atorvastatin may be removed from the air by wet and dry deposition(SRC). Atorvastatin contains chromophores that absorb at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Adverse Effects
Common adverse effects for patients taking atorvastatin include arthralgia, dyspepsia, diarrhea, nausea, nasopharyngitis, insomnia, urinary tract infection, and pain in the extremities.;Myopathies have occurred in patients taking atorvastatin, including muscle aches, muscle tenderness, or muscle weakness, with elevated creatine phosphokinase greater than ten times the upper limit of normal. Rhabdomyolysis has been reported in patients using atorvastatin. Patients with impaired renal function may be at increased risk of developing rhabdomyolysis. Using atorvastatin in combination with other medications that increase atorvastatin plasma concentrations increases the risk for myopathies and rhabdomyolysis. Management of statin-induced myopathies includes temporarily holding therapy, switching to an alternative statin, or reducing the dose.;Some data suggest that statins may increase the risk of developing diabetes mellitus. In 2012, the FDA added safety label changes to statin safety labeling, indicating that these medications have been shown to increase glycosylated hemoglobin and fasting serum glucose levels. The ACC/AHA guidelines group and other experts state that the risk-reducing benefits of statin therapy outweigh the generally mild rise in serum glucose levels or new-onset diabetes. Clinicians are encouraged to use this opportunity to discuss healthy lifestyle measures with their patients, including weight loss, engaging in regular exercise, and maintaining a balanced diet.;Atorvastatin can cause abnormalities in liver function tests. If patients develop serum transaminases that are more than three times the upper limit of normal, plasma concentrations require more frequent monitoring until normalized, or atorvastatin therapy should undergo dose reduction or be discontinued.;Drug-Drug Interactions;* Using atorvastatin with potent CYP3A4 inhibitors can lead to increased plasma concentrations, which may enhance adverse events, including myopathy. OATP1B1 inhibitors can increase the bioavailability of atorvastatin.;* CYP3A4 inducers may cause decreased plasma concentrations of atorvastatin.;* Patients taking digoxin should undergo monitoring when starting atorvastatin, as plasma concentrations of digoxin may increase.;* Atorvastatin may also increase drug concentrations of norethindrone and ethinyl estradiol.
Exposure Routes
Atorvastatin is rapidly absorbed after oral administration with maximum plasma concentrations achieved in 1 to 2 hours. The absolute bioavailability of atorvastatin (parent drug) is approximately 14% and the systemic availability of HMG-CoA reductase inhibitory activity is approximately 30%. The low systemic bioavailability is due to presystemic clearance by gastrointestinal mucosa and first-pass metabolism in the liver.
Toxicity Summary
IDENTIFICATION AND USE: Atorvastatin is anticholesteremic agent and hydroxymethylglutaryl-CoA reductase inhibitor. HUMAN EXPOSURE AND TOXICITY: Cases of fatal and nonfatal hepatic failure have been reported rarely in patients receiving statins, including atorvastatin. Rhabdomyolysis with acute renal failure secondary to myoglobinuria also has been reported rarely in patients receiving statins, including atorvastatin. Lipid lowering drugs offer no benefit during pregnancy because cholesterol and cholesterol derivatives are needed for normal fetal development. Atherosclerosis is a chronic process, and discontinuation of lipid-lowering drugs during pregnancy should have little impact on long-term outcomes of primary hypercholesterolemia therapy. The occurrence of neuropsychiatric reactions is associated with statin treatment. They include behavioral alterations; cognitive and memory impairments; sleep disturbance; and sexual dysfunction. ANIMAL STUDIES: In a 2-year carcinogenicity study in rats at dose levels of 10, 30, and 100 mg/kg/day, 2 rare tumors were found in muscle in high-dose females: in one, there was a rhabdomyosarcoma, and in another, there was a fibrosarcoma. Atorvastatin caused no adverse effects on semen parameters, or reproductive organ histopathology in dogs given doses of 10, 40, or 120 mg/kg for two years. Male rats given 100 mg/kg/day for 11 weeks prior to mating had decreased sperm motility, spermatid head concentration, and increased abnormal sperm. Studies in rats performed at doses up to 175 mg/kg produced no changes in fertility. There was aplasia and aspermia in the epididymis of 2 of 10 rats treated with 100 mg/kg/day of atorvastatin for 3 months; testis weights were significantly lower at 30 and 100 mg/kg and epididymal weight was lower at 100 mg/kg. In a study in rats given 20, 100, or 225 mg/kg/day, from gestation day 7 through to lactation day 21 (weaning), there was decreased pup survival at birth, neonate, weaning, and maturity in pups
Signs and Symptoms of Overdose;A retrospective pharmacovigilance study analyzed 311 pediatric ICSRs related to statin use from the WHO VigiBase, identifying 712 adverse drug reactions (ADRs). Musculoskeletal and general disorders were the most common. About 43% of reports were classified as serious, including rhabdomyolysis and hepatocellular injury. Eleven fatalities occurred, primarily in adolescents, following intentional overdose, often with other drugs. Overdose, accidental exposure, and off-label use were also frequent. These findings suggest that while statins in the pediatric population, especially adolescents, require careful monitoring due to rare but serious risks, they emphasize the need for psychosocial evaluation and safe prescribing practices. Rhabdomyolysis is a rare but serious adverse effect of statins, especially when combined with drugs that increase statin exposure. Laboratory investigations include increased CPK and myoglobinuria. Rhabdomyolysis can lead to acute kidney injury; therefore, serum creatinine levels and electrolytes should be obtained.;Management of Overdose;There are no antidotes available for atorvastatin overdose. Patients should be monitored for adverse events and provided with supportive care. Management of statin-induced rhabdomyolysis involves prompt discontinuation of the statin and initiation of intravenous hydration to prevent acute kidney injury. Correct electrolyte disturbances, and if hyperkalemia is present (potassium >6 mmol/L), begin electrocardiogram monitoring and treat with insulin-dextrose therapy. Continue follow-up to assess for acute kidney injury and electrolyte balance. If statin-associated autoimmune myopathy develops, treat with corticosteroids, methotrexate, intravenous immunoglobulin, or rituximab. Correct electrolyte disturbances, and if hyperkalemia is present (potassium >6 mmol/L), begin electrocardiogram monitoring and treat with insulin-dextrose therapy. Continue follow-up to assess for acute kidney injury and electrolyte balance. Once stable, consider restarting a statin, such as pravastatin, at the lowest effective dose, only with clinical caution. Avoid the concomitant use of fibrates.;If statin-associated immune-mediated necrotizing myopathy develops, treat with steroids, rituximab, methotrexate, and intravenous immunoglobulin. In severe cases, contact the Poison Control Center at 1-800-222-1222 for the latest information.
Atorvastatin selectively and competitively inhibits the hepatic enzyme HMG-CoA reductase. As HMG-CoA reductase is responsible for converting HMG-CoA to mevalonate in the cholesterol biosynthesis pathway, this results in a subsequent decrease in hepatic cholesterol levels. Decreased hepatic cholesterol levels stimulates upregulation of hepatic LDL-C receptors which increases hepatic uptake of LDL-C and reduces serum LDL-C concentrations.
Ecotoxicity Excerpts
/AQUATIC SPECIES/ The presence of pharmaceutical substances in the municipal effluents is currently considered the principal source of bio-active molecule emissions into aquatic environments. This study analyzes the genotoxic damage caused by gemfibrozil and atorvastatin, two regulators of the hematic level of lipids, and sildenafil citrate, a vasodilator, on the teleost Danio rerio. The genotoxicity of these three compounds was evaluated using the comet assay, diffusion assay, and RAPD-PCR. The alkaline version (pH 12.1) of the comet assay was used for the erythrocytes of the zebrafish to evaluate the presence of single strand DNA breaks. Furthermore, the diffusion assay was used to estimate the number of apoptotic cells. The fish were treated with the three pharmacological agents at the average concentrations previously found at some Italian treatment plants and were then sacrificed from 5 to 35 days after exposure. The data of the comet assay showed a statistically significant loss of DNA integrity after 5 days of exposure to atorvastatin and after one week of exposure to gemfibrozil. This damage was, however, repaired after 14 days. Sildenafil citrate produced, instead, a statistically significant loss of DNA integrity at the concentrations found only after 35 days of exposure. The genotoxicity at the molecular level was tested by RAPD-PCR. The results from this investigation are in agreement with those from two other tests, confirming the efficacy of the use of the three experimental approaches for the complete evaluation of genotoxic damage.
/AQUATIC SPECIES/ ...The toxicity of four /pharmaceuticals and personal care products/ (PPCPs)-the lipid regulator atorvastatin (ATO), the antiepileptic drug carbamazepine (CBZ), the synthetic hormone 17a-ethinylestradiol (EE2), and the antimicrobial triclosan (TCS)-to the midge Chironomus tentans and the freshwater amphipod Hyalella azteca /was examined/ in 10-day waterborne exposures. The toxicity of the four compounds varied between 0.20 and 47.3 mg/L (median lethal concentration), with a relative toxicity ranking of TCS > EE2 > ATO > CBZ. Hyalella azteca was more sensitive than C. tentans to these compounds. The toxicity data were used in a hazard quotient approach to evaluate the risk posed by the four PPCPs to benthic invertebrates and other aquatic organisms. For each compound, a hazard quotient was calculated by dividing the lowest toxicity value by the highest exposure value found in the literature, to which an uncertainty factor was applied. With hazard quotients of 3.55 to 11.5, we conclude that potential risks exist toward benthic invertebrates for the toxicity of TCS and CBZ and that further investigations of these compounds are required to characterize more completely the risks to benthic organisms. In contrast, our data also indicate that considering the low concentrations currently detected in the environment, ATO and EE2 pose negligible risks to benthic invertebrates.
/AQUATIC SPECIES/ ...The aim of the present study was to quantify the cytotoxic effects of acid and lactone forms of two statins, atorvastatin and simvastatin, as well as selected metabolites (ortho- and para-hydroxy atorvastatin acid, ortho-hydroxy atorvastatin lactone, simvastatin hydroxyl carboxylic acid, and 3''hydroxy simvastatin lactone) to hepatocytes from rainbow trout (Oncorhynchus mykiss). Hepatocytes were exposed for 24, 48, and 72 hr to different concentrations of each test substance (0.4-400 uM). Cytotoxicity was measured as metabolic inhibition and loss of membrane integrity with the fluorescent probes alamar blue (AB) and 5-carboxyfluorescein diacetate, acetoxymethyl ester (CFDA-AM), respectively. Atorvastatin, simvastatin, and ortho-hydroxy atorvastatin lactone had dose-dependent cytotoxic effects on hepatocytes. Simvastatin was more toxic than atorvastatin and the lactone form more toxic than the acid form. Exposure time affected atorvastatin and ortho-hydroxy atorvastatin lactone but not simvastatin toxicity.
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of October 28, 2016: http://actor.epa.gov/dashboard/]
Effluent Concentrations
Atorvastatin concentrations of 1.56 and 0.21 ug/L were reported in influent and effluent, respectively, at a wastewater treatment plant in southeastern US(1). Based on an annual consumption of 6496.94 kg/yr, the estimated atovastatin elimination from primary and secondary treatment processes was 56.25 and 58%, respectively, from wastewater facilities in Spain in 2009, giving a predicted environmental occurrence of 15.31 ng/L(2).
Medical Surveillance
Primarily because of the safety data from the clinical trials, it is reasonable to measure alanine aminotransferase (ALT) at baseline at 3-6 months after therapy is initiated or after increasing the dose. If the ALT values are normal, it is not necessary to repeat the ALT test more than every 6-12 months. /Statins/
Soil Adsorption/Mobility
The Koc of atorvastatin is estimated as 400(SRC), using an estimated log Kow of 6.36(1) and a regression-derived equation(1). According to a classification scheme(2), this estimated Koc value suggests that atorvastatin is expected to have moderate mobility in soil. The estimated pKa1 of atorvastatin is 4.3(3), indicating that this compound will exist partially in the anion form in the environment and anions generally do not adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4).
규제 정보
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including atorvastatin calcium, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Atorvastatin calcium/
안전 데이터
- wgk
- WGK 3
- HS 번호
- 35040000
- risk_code
- 20/21/22-36/37/38
- hazard_code
- Xn
- safety_code
- 26-36
- Hazard Classifications
- Repr. 2
- 스토리지 클래스
- 11 - Combustible Solids
- 유해 물질 데이터
- 134523-00-5(Hazardous Substances Data)
화학 및 산업
약리 정보
ATC Code
C10AA05
C - Cardiovascular system;C10 - Lipid modifying agents;C10A - Lipid modifying agents, plain;C10AA - Hmg coa reductase inhibitors;C10AA05 - Atorvastatin
QC - Cardiovascular system;QC10 - Lipid modifying agents;QC10A - Lipid modifying agents, plain;QC10AA - Hmg coa reductase inhibitors;QC10AA05 - Atorvastatin
Protein BindingAtorvastatin is highly bound to plasma proteins and over 98% of the administered dose is found in a bound form.
Pharmacodynamics
Atorvastatin is an oral antilipemic agent that reversibly inhibits HMG-CoA reductase. It lowers total cholesterol, low-density lipoprotein-cholesterol (LDL-C), apolipoprotein B (apo B), non-high density lipoprotein-cholesterol (non-HDL-C), and triglyceride (TG) plasma concentrations while increasing HDL-C concentrations. High LDL-C, low HDL-C and high TG concentrations in the plasma are associated with increased risk of atherosclerosis and cardiovascular disease. The total cholesterol to HDL-C ratio is a strong predictor of coronary artery disease, and high ratios are associated with a higher risk of disease. Increased levels of HDL-C are associated with lower cardiovascular risk. By decreasing LDL-C and TG and increasing HDL-C, atorvastatin reduces the risk of cardiovascular morbidity and mortality. Elevated cholesterol levels (and high low-density lipoprotein (LDL) levels in particular) are an important risk factor for the development of CVD. Clinical studies have shown that atorvastatin reduces LDL-C and total cholesterol by 36-53%. In patients with dysbetalipoproteinemia, atorvastatin reduced the levels of intermediate-density lipoprotein cholesterol. It has also been suggested that atorvastatin can limit the extent of angiogenesis, which can be useful in the treatment of chronic subdural hematoma. **Myopathy/Rhabdomyolysis** Atorvastatin, like other HMG-CoA reductase inhibitors, is associated with a risk of drug-induced myopathy characterized by muscle pain, tenderness, or weakness in conjunction with elevated levels of creatine kinase (CK). Myopathy often manifests as rhabdomyolysis with or without acute renal failure secondary to myoglobinuria. The risk of statin-induced myopathy is dose-related, and the symptoms of myopathy are typically resolved upon drug discontinuation. Results from observational studies suggest that 10-15% of people taking statins may experience muscle aches at some point during treatment. **Liver Dysfunction** Statins, like some o
Mechanism of Action
Atorvastatin is a statin medication and a competitive inhibitor of the enzyme HMG-CoA (3-hydroxy-3-methylglutaryl coenzyme A) reductase, which catalyzes the conversion of HMG-CoA to mevalonate, an early rate-limiting step in cholesterol biosynthesis. Atorvastatin acts primarily in the liver, where decreased hepatic cholesterol concentrations stimulate the upregulation of hepatic low-density lipoprotein (LDL) receptors, which increases hepatic uptake of LDL. Atorvastatin also reduces Very-Low-Density Lipoprotein-Cholesterol (VLDL-C), serum triglycerides (TG) and Intermediate Density Lipoproteins (IDL), as well as the number of apolipoprotein B (apo B) containing particles, but increases High-Density Lipoprotein Cholesterol (HDL-C). _In vitro_ and _in vivo_ animal studies also demonstrate that atorvastatin exerts vasculoprotective effects independent of its lipid-lowering properties, also known as the pleiotropic effects of statins. These effects include improvement in endothelial function, enhanced stability of atherosclerotic plaques, reduced oxidative stress and inflammation, and inhibition of the thrombogenic response. Statins were also found to bind allosterically to β2 integrin function-associated antigen-1 (LFA-1), which plays an essential role in leukocyte trafficking and T cell activation.
In animal models, Lipitor lowers plasma cholesterol and lipoprotein levels by inhibiting 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase and cholesterol synthesis in the liver and by increasing the number of hepatic low-density lipoprotein (LDL) receptors on the cell surface to enhance uptake and catabolism of LDL; Lipitor also reduces LDL production and the number of LDL particles. Lipitor reduces LDL-cholesterol (LDL-C) in some patients with homozygous familial hypercholesterolemia (FH), a population that rarely responds to other lipid-lowering medication(s).
Lipitor is a selective, competitive inhibitor of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl-coenzyme A to mevalonate, a precursor of sterols, including cholesterol. Cholesterol and triglycerides circulate in the bloodstream as part of lipoprotein complexes. With ultracentrifugation, these complexes separate into HDL (high-density lipoprotein), IDL (intermediate-density lipoprotein), LDL (low-density lipoprotein), and VLDL (very-low-density lipoprotein) fractions. Triglycerides (TG) and cholesterol in the liver are incorporated into VLDL and released into the plasma for delivery to peripheral tissues. LDL is formed from VLDL and is catabolized primarily through the high-affinity LDL receptor. Clinical and pathologic studies show that elevated plasma levels of total cholesterol (total-C), LDL-cholesterol (LDL-C), and apolipoprotein B (apo B) promote human atherosclerosis and are risk factors for developing cardiovascular disease, while increased levels of HDL-C are associated with a decreased cardiovascular risk.
Statins are largely used in clinics in the treatment of patients with cardiovascular diseases for their effect on lowering circulating cholesterol. Lectin-like oxidized low-density lipoprotein (LOX-1), the primary receptor for ox-LDL, plays a central role in the pathogenesis of atherosclerosis and cardiovascular disorders. We have recently shown that chronic exposure of cells to lovastatin disrupts LOX-1 receptor cluster distribution in plasma membranes, leading to a marked loss of LOX-1 function. Here we investigated the molecular mechanism of statin-mediated LOX-1 inhibition and we demonstrate that all tested statins /including atorvastatin/ are able to displace the binding of fluorescent ox-LDL to LOX-1 by a direct interaction with LOX-1 receptors in a cell-based binding assay. Molecular docking simulations confirm the interaction and indicate that statins completely fill the hydrophobic tunnel that crosses the C-type lectin-like (CTLD) recognition domain of LOX-1. Classical molecular dynamics simulation technique applied to the LOX-1 CTLD, considered in the entire receptor structure with or without a statin ligand inside the tunnel, indicates that the presence of a ligand largely increases the dimer stability. Electrophoretic separation and western blot confirm that different statins binding stabilize the dimer assembly of LOX-1 receptors in vivo. The simulative and experimental results allow us to propose a CTLD clamp motion, which enables the receptor-substrate coupling. ...
3-Hydroxy-3-methylglutaryl coenzyme A reductase inhibitors (statins) exert potent vasculoprotective effects. However, the potential contribution to angiogenesis is controversial. In the present study, we demonstrate that atorvastatin dose-dependently affects endothelial cell migration and angiogenesis. In vivo relevant concentrations of 0.01 to 0.1 umol/L atorvastatin or mevastatin promote the migration of mature endothelial cells and tube formation. Moreover, atorvastatin also increases migration and the potency to form vessel structures of circulating endothelial progenitor cells, which may contribute to vasculogenesis. In contrast, higher concentrations (>0.1 umol/L atorvastatin) block angiogenesis and migration by inducing endothelial cell apoptosis. The dose-dependent promigratory and proangiogenic effects of atorvastatin on mature endothelial cells are correlated with the activation of the phosphatidylinositol 3-kinase-Akt pathway, as determined by the phosphorylation of Akt and endothelial NO synthase (eNOS) at Ser1177. In addition, the stimulation of migration and tube formation was blocked by phosphatidylinositol 3-kinase inhibitors. In contrast, the well-established stabilization of eNOS mRNA was achieved only at higher concentrations, suggesting that posttranscriptional activation rather than an increase in eNOS expression mediates the proangiogenic effect of atorvastatin. Taken together, these data suggest that statins exert a double-edged role in angiogenesis signaling by promoting the migration of mature endothelial cells and endothelial progenitor cells at low concentrations, whereas the antiangiogenic effects were achieved only at high concentrations.
Here, we found that atorvastatin promoted the expansion of myeloid-derived suppressor cells (MDSCs) both in vitro and in vivo. Atorvastatin-derived MDSCs suppressed T-cell responses by nitric oxide production. Addition of mevalonate, a downstream metabolite of 3-hydroxy-3-methylglutaryl coenzyme A reductase, almost completely abrogated the effect of atorvastatin on MDSCs, indicating that the mevalonate pathway was involved. Along with the amelioration of dextran sodium sulfate (DSS) -induced murine acute and chronic colitis, we observed a higher MDSC level both in spleen and intestine tissue compared with that from DSS control mice. More importantly, transfer of atorvastatin-derived MDSCs attenuated DSS acute colitis and T-cell transfer of chronic colitis. Hence, our data suggest that the expansion of MDSCs induced by statins may exert a beneficial effect on autoimmune diseases. In summary, our study provides a novel potential mechanism for statins-based treatment in inflammatory bowel disease and perhaps other autoimmune diseases.
Biological Half-Life
The half-life of atorvastatin is 14 hours while the half-life of its metabolites can reach up to 30 hours.
/MILK/ ...After administration to lactating rats, radioactivity in milk reached the maximum of 17.1 ng eq./mL at 6.0 hr and thereafter declined with a half-life of 7.8 hr.
Mean plasma elimination half-life of Lipitor in humans is approximately 14 hours, but the half-life of inhibitory activity for HMG-CoA reductase is 20 to 30 hours due to the contribution of active metabolites.
Metabolism/Metabolites
Atorvastatin is highly metabolized to ortho- and parahydroxylated derivatives and various beta-oxidation products, primarily by Cytochrome P450 3A4 in the intestine and liver. Atorvastatin's metabolites undergo further lactonization via the formation of acyl glucuronide intermediates by the enzymes UGT1A1 and UGT1A3. These lactones can be hydrolyzed back to their corresponding acid forms and exist in equilibirum. _In vitro_ inhibition of HMG-CoA reductase by ortho- and parahydroxylated metabolites is equivalent to that of atorvastatin. Approximately 70% of circulating inhibitory activity for HMG-CoA reductase is attributed to active metabolites.
Lipitor is extensively metabolized to ortho- and parahydroxylated derivatives and various beta-oxidation products. In vitro inhibition of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase by ortho- and parahydroxylated metabolites is equivalent to that of Lipitor. Approximately 70% of circulating inhibitory activity for HMG-CoA reductase is attributed to active metabolites. In vitro studies suggest the importance of Lipitor metabolism by cytochrome P450 3A4, consistent with increased plasma concentrations of Lipitor in humans following co-administration with erythromycin, a known inhibitor of this isozyme. In animals, the ortho-hydroxy metabolite undergoes further glucuronidation.
The active forms of all marketed hydroxymethylglutaryl (HMG)-CoA reductase inhibitors share a common dihydroxy heptanoic or heptenoic acid side chain. In this study, we present evidence for the formation of acyl glucuronide conjugates of the hydroxy acid forms of simvastatin (SVA), atorvastatin (AVA), and cerivastatin (CVA) in rat, dog, and human liver preparations in vitro and for the excretion of the acyl glucuronide of SVA in dog bile and urine. Upon incubation of each statin (SVA, CVA or AVA) with liver microsomal preparations supplemented with UDP-glucuronic acid, two major products were detected. Based on analysis by high-pressure liquid chromatography, UV spectroscopy, and/or liquid chromatography (LC)-mass spectrometry analysis, these metabolites were identified as a glucuronide conjugate of the hydroxy acid form of the statin and the corresponding delta-lactone. By means of an LC-NMR technique, the glucuronide structure was established to be a 1-O-acyl-beta-D-glucuronide conjugate of the statin acid. The formation of statin glucuronide and statin lactone in human liver microsomes exhibited modest intersubject variability (3- to 6-fold; n = 10). Studies with expressed UDP glucuronosyltransferases (UGTs) revealed that both UGT1A1 and UGT1A3 were capable of forming the glucuronide conjugates and the corresponding lactones for all three statins. Kinetic studies of statin glucuronidation and lactonization in liver microsomes revealed marked species differences in intrinsic clearance (CL(int)) values for SVA (but not for AVA or CVA), with the highest CL(int) observed in dogs, followed by rats and humans. Of the statins studied, SVA underwent glucuronidation and lactonization in human liver microsomes, with the lowest CL(int) (0.4 uL/min/mg of protein for SVA versus approximately 3 uL/min/mg of protein for AVA and CVA). Consistent with the present in vitro findings, substantial levels of the glucuronide conjugate (approximately 20% of dose) and the lactone form of
The genetic variation underlying atorvastatin (ATV) pharmacokinetics was evaluated in a Mexican population. Aims of this study were: 1) to reveal the frequency of 87 polymorphisms in 36 genes related to drug metabolism in healthy Mexican volunteers, 2) to evaluate the impact of these polymorphisms on ATV pharmacokinetics, 3) to classify the ATV metabolic phenotypes of healthy volunteers, and 4) to investigate a possible association between genotypes and metabolizer phenotypes. A pharmacokinetic study of ATV (single 80-mg dose) was conducted in 60 healthy male volunteers. ATV plasma concentrations were measured by high-performance liquid chromatography mass spectrometry. Pharmacokinetic parameters were calculated by the non-compartmental method. The polymorphisms were determined with the PHARMAchip microarray and the TaqMan probes genotyping assay. Three metabolic phenotypes were found in our population: slow, normal, and rapid. Six gene polymorphisms were found to have a significant effect on ATV pharmacokinetics: MTHFR (rs1801133), DRD3 (rs6280), GSTM3 (rs1799735), TNFa (rs1800629), MDR1 (rs1045642), and SLCO1B1 (rs4149056). The combination of MTHFR, DRD3 and MDR1 polymorphisms associated with a slow ATV metabolizer phenotype.
Atorvastatin has known human metabolites that include 7-[2-(4-Fluorophenyl)-4-[(4-hydroxyphenyl)carbamoyl]-3-phenyl-5-propan-2-ylpyrrol-1-yl]-3,5-dihydroxyheptanoic acid and 7-[2-(4-Fluorophenyl)-4-[(2-hydroxyphenyl)carbamoyl]-3-phenyl-5-propan-2-ylpyrrol-1-yl]-3,5-dihydroxyheptanoic acid.
Atorvastatin is extensively metabolized to ortho- and parahydroxylated derivatives and various beta-oxidation products. In vitro inhibition of HMG-CoA reductase by ortho- and parahydroxylated metabolites is equivalent to that of atorvastatin. Approximately 70% of circulating inhibitory activity for HMG-CoA reductase is attributed to active metabolites. CYP3A4 is also involved in the metabolism of atorvastatin.
FDA Pharmacological Classification
A0JWA85V8F
ATORVASTATIN
Established Pharmacologic Class [EPC] - HMG-CoA Reductase Inhibitor
Mechanisms of Action [MoA] - Hydroxymethylglutaryl-CoA Reductase Inhibitors
Atorvastatin is a HMG-CoA Reductase Inhibitor. The mechanism of action of atorvastatin is as a Hydroxymethylglutaryl-CoA Reductase Inhibitor.
MeSH Pharmacological Classification
Substances used to lower plasma CHOLESTEROL levels.
Compounds that inhibit HYDROXYMETHYLGLUTARYL COA REDUCTASES. They have been shown to directly lower CHOLESTEROL synthesis.
Absorption, Distribution and Excretion
Atorvastatin presents a dose-dependent and non-linear pharmacokinetic profile. It is very rapidly absorbed after oral administration. After the administration of a dose of 40 mg, its peak plasma concentration of 28 ng/ml is reached 1-2 hours after initial administration with an AUC of about 200 ng∙h/ml. Atorvastatin undergoes extensive first-pass metabolism in the wall of the gut and the liver, resulting in an absolute oral bioavailability of 14%. Plasma atorvastatin concentrations are lower (approximately 30% for Cmax and AUC) following evening drug administration compared with morning. However, LDL-C reduction is the same regardless of the time of day of drug administration. Administration of atorvastatin with food results in prolonged Tmax and a reduction in Cmax and AUC. Breast Cancer Resistance Protein (BCRP) is a membrane-bound protein that plays an important role in the absorption of atorvastatin. Evidence from pharmacogenetic studies of c.421C>A single nucleotide polymorphisms (SNPs) in the gene for BCRP has demonstrated that individuals with the 421AA genotype have reduced functional activity and 1.72-fold higher AUC for atorvastatin compared to study individuals with the control 421CC genotype. This has important implications for the variation in response to the drug in terms of efficacy and toxicity, particularly as the BCRP c.421C>A polymorphism occurs more frequently in Asian populations than in Caucasians. Other statin drugs impacted by this polymorphism include [fluvastatin], [simvastatin], and [rosuvastatin]. Genetic differences in the OATP1B1 (organic-anion-transporting polypeptide 1B1) hepatic transporter encoded by the SCLCO1B1 gene (Solute Carrier Organic Anion Transporter family member 1B1) have been shown to impact atorvastatin pharmacokinetics. Evidence from pharmacogenetic studies of the c.521T>C single nucleotide polymorphism (SNP) in the gene encoding OATP1B1 (SLCO1B1) demonstrated that atorvastatin AUC was increased 2.45-fold for indivi
Atorvastatin and its metabolites are mainly eliminated in the bile without enterohepatic recirculation. The renal elimination of atorvastatin is very minimal and represents less than 1% of the eliminated dose.
The reported volume of distribution of atorvastatin is of 380 L.
The registered total plasma clearance of atorvastatin is of 625 ml/min.
/MILK/ In a separate experiment, a single dose of 10 mg/kg atorvastatin administered to female Wistar rats on gestation day 19 or lactation day 13 provided evidence of placental transfer and excretion into the milk.
Lipitor and its metabolites are eliminated primarily in bile following hepatic and/or extra-hepatic metabolism; however, the drug does not appear to undergo enterohepatic recirculation. ... Less than 2% of a dose of Lipitor is recovered in urine following oral administration.
Tissue LocationsLiver;Platelet
Cellular LocationsMembrane
Metabolite PathwaysAtorvastatin Action Pathway
용도 및 제조
Uses
MEDICATION
Anticholesteremic Agents; Hydroxymethylglutaryl-CoA Reductase Inhibitors
Use (kg) in Switzerland (2009): >1000;Use (kg; approx.) in Germany (2009): >1000;Use (kg) in USA (2002): 31300;Use (kg) in France (2004): 7924;Consumption (g per capita) in Switzerland (2009): 0.13;Consumption (g per capita; approx.) in Germany (2009): 0.012;Consumption (g per capita) in the USA (2002): 0.11;Consumption (g per capita) in France (2004): 0.13;Excretion rate: 0.46;Calculated removal (%): 97.3
May be used as primary prevention in individuals with multiple risk factors for coronary heart disease (CHD) and as secondary prevention in individuals with CHD to reduce the risk of myocardial infarction (MI), stroke, angina, and revascularization procedures. May be used to reduce the risk of cardiovascular events in patients with acute coronary syndrome (ACS). May be used in the treatment of primary hypercholesterolemia and mixed dyslipidemia, homozygous familial hypercholesterolemia, primary dysbetalipoproteinemia, and/or hypertriglyeridemia as an adjunct to dietary therapy to decrease serum total and low-density lipoprotein cholesterol (LDL-C), apolipoprotein B (apoB), and triglyceride concentrations, while increasing high-density lipoprotein cholesterol (HDL-C) levels.
Methods of ManufacturingPreparation: B.D. Roth, European Patent Office patent 409281; idem, United States of America patent 5273995 (1991, 1993 both to Warner-Lambert).
Formulations/Preparations
Table: Atorvastatin Calcium Preparations [Table#6657]
Table: Atorvastatin Calcium Combinations Preparations [Table#6658]
응용 분야
역사Parke-Davis's Lipitor (Atorvastatin) was discovered in the mid- to late 1980s and brought to market in 1997. Already ahead of it were four statins: Merck's Mevacor and Zocor, Bristol-Myers Squibb's Pravachol, and Sandoz's Lescol. Despite the competition, by 2006 Lipitor had become the best-selling drug in history, with one-year sales totaling $12.9 billion, more than the net worth of the 10th biggest drug company in the world.
용도antihyperlipoproteimic;HMG-CoA reductase inhibition
일반 설명Atorvastatin, [R-(R*,R*)]-2-(4-fluorophenyl)-b,d-dihydroxy-5-(1-methylethyl)-3-phenyl-4-[(phenylamino)carbonyl]-lH-pyrrole-1-heptanoic acid(Lipitor), also possesses the heptanoic acid side chain,which is critical for inhibition of HMG-CoA reductase.Although the side chain is less lipophilic than the lactoneform, the high amount of lipophilic substitution causes this agent to have a slightly higher level of CNS penetration thanpravastatin, resulting in a slight increase in CNS side effects.Even so, its CNS profile is much lower than that of lovastatin.Atorvastatin is marketed as a combination therapywith amlodipine under the trade name Norvasc for managementof high cholesterol and high blood pressure.
상·하류 제품 정보
상류 원료
공급사50 곳
北京华美互利生物化工010-56205725 · [email protected]
湖北永阔科技有限公司027-59223108 15972152991 · [email protected]
湖北万得化工有限公司15377098680 15377098680 · [email protected]
合肥翰刚医药科技有限公司+8618062405514 · [email protected]
河北展药生物科技有限公司15369953316 +8615369953316 · [email protected]
Baoji Guokang Healthchem co.,ltd+8615604608665 15604608665 · [email protected]
Dayang Chem (Hangzhou) Co.,Ltd.+86-0571-88938639 17705817739 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
Syntechem Co.,Ltd[email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
南京圣亿来化工有限公司19951936396 · [email protected]
Advanced chemblocks inc650-6922368 650-6922368;650-6922368 · [email protected]
上海泰坦科技股份有限公司400-6009262 15618770481 · [email protected]
湖北广奥生物科技有限公司027-02702759223056 18162699093 · [email protected]
南京爱珂医药科技有限公司025-58395930 · [email protected]
佛山宝诺生物科技有限公司0757-85921206 18520245316 · [email protected]
HONG KONG IPURE BIOLOGY CO.,LIMITED86 18062405514 18062405514 · [email protected]
Xiamen AmoyChem Co., Ltd+86-86-5926051114 · [email protected]
上海特伯化学科技有限公司+86-21-60341587 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
上海陶素生化科技有限公司021-33632979 · [email protected]
上海喀露蓝科技有限公司18149758185 18149758185 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
湖南华腾制药有限公司400-8592883 · [email protected]
上海创赛科技有限公司400-6087598 15021221957 · [email protected]
天津普西唐生物医药科技有限公司010-60605840 · [email protected]
济南鲁欣化工科技有限公司0531-0531-82929600 18615510361 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
上海寰川实业有限公司021-61478794 · [email protected]
南京百鑫德诺生物科技有限公司025-58849295 · [email protected]
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
TargetMol中国(陶术生物)021-021-33632979 15002134094 · [email protected]
上海陶术生物科技股份有限公司+1-781-999-5354; +1-00000000000 · [email protected]
湖北威德利化学科技有限公司027-83989310 18627915365
西安美川生物科技有限公司029-89275612 +8618991951683 · [email protected]
厦门志信化学有限公司+86-5922680277 +86-13806087780 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
Alfa Chemistry+1-5166625404 · [email protected]
上海德轩医药科技有限公司[email protected] · [email protected]
sgtlifesciences pvt ltd+91-8790379245 · [email protected]
湖北源梦生物科技有限公司027-68897569 18120462897 · [email protected]
武汉多普乐生物医药有限公司+86-02787215551 19945035818 · [email protected]
上海珞珐生化科技有限公司021-51111890 15317326293 · [email protected]
成都润泽本土化工有限公司028-88469284 18000562381 · [email protected]
陕西缔都医药化工有限公司+86-29-81139210 +86-17392587031 · [email protected]
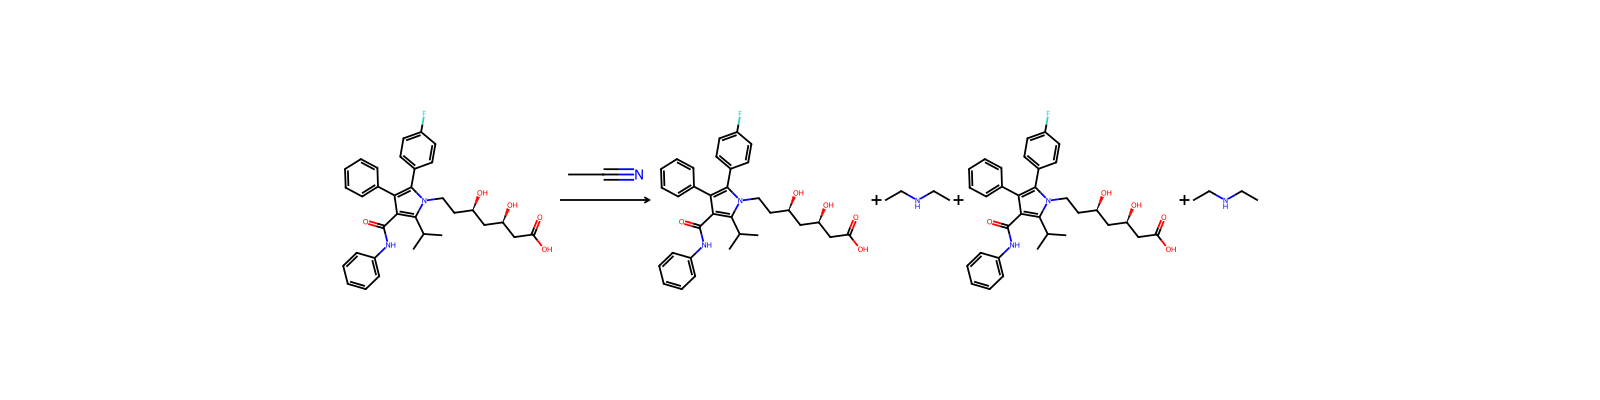
관련 반응
68건
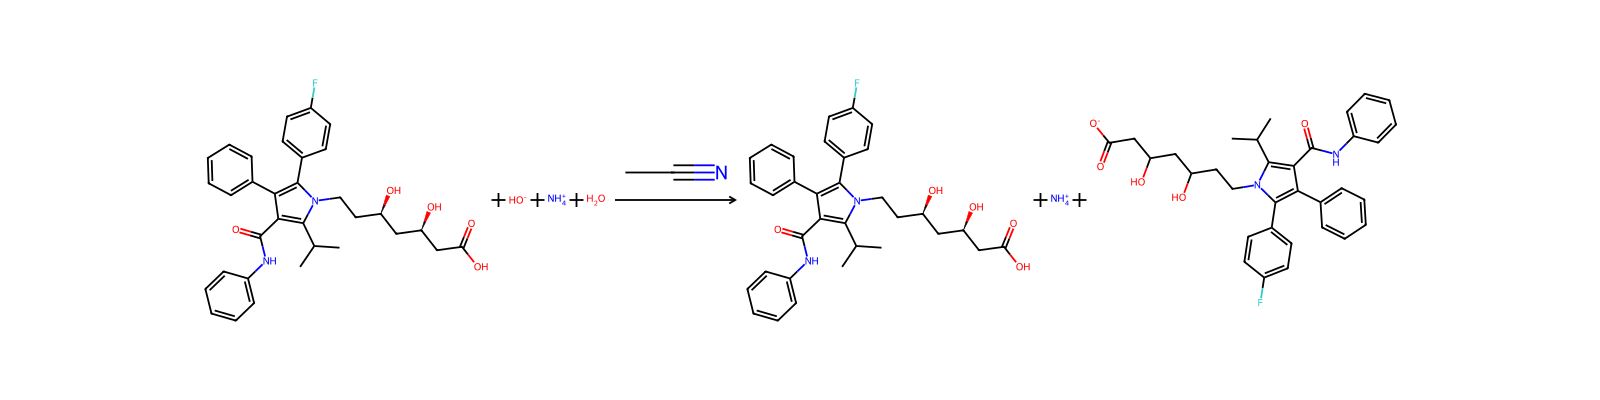
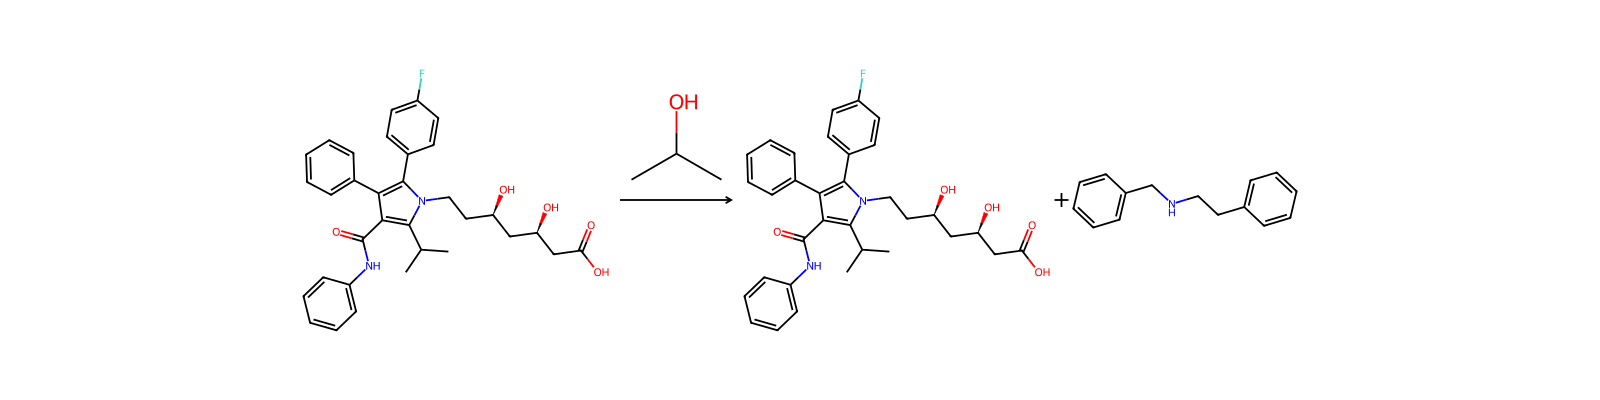
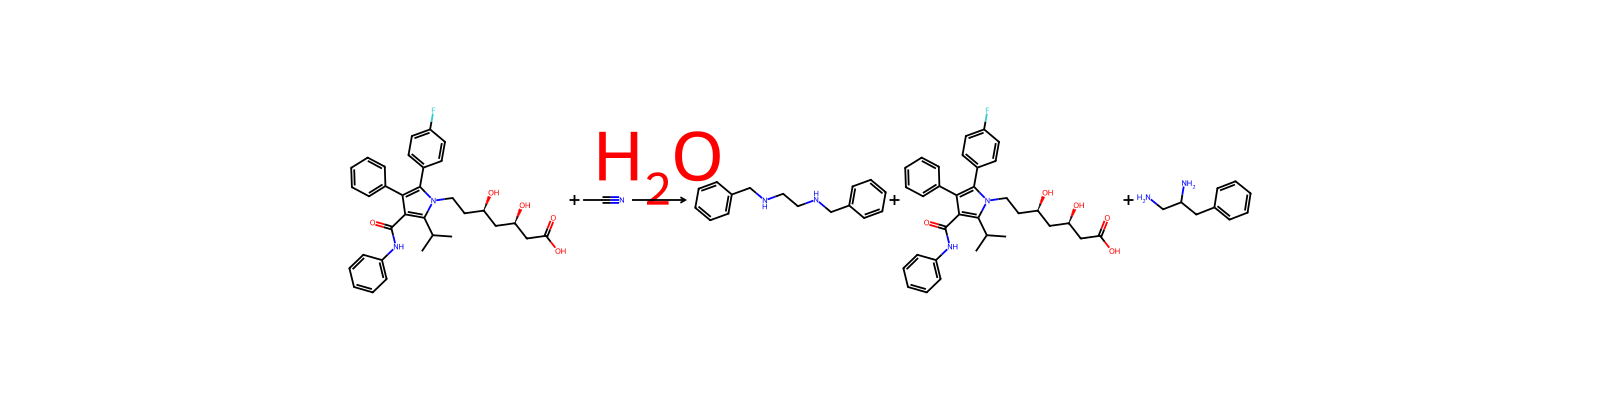
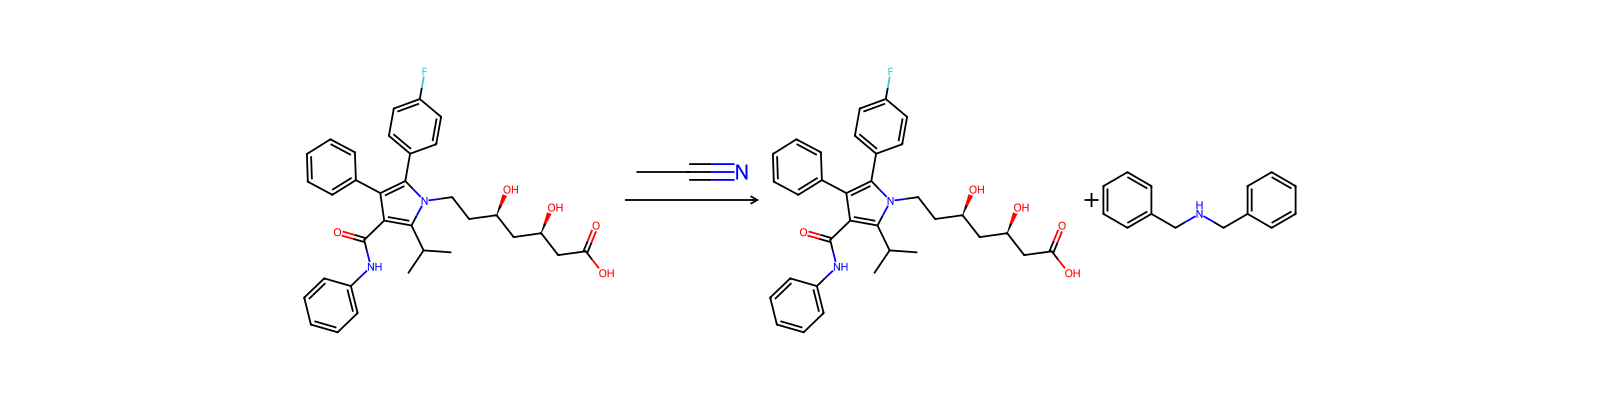
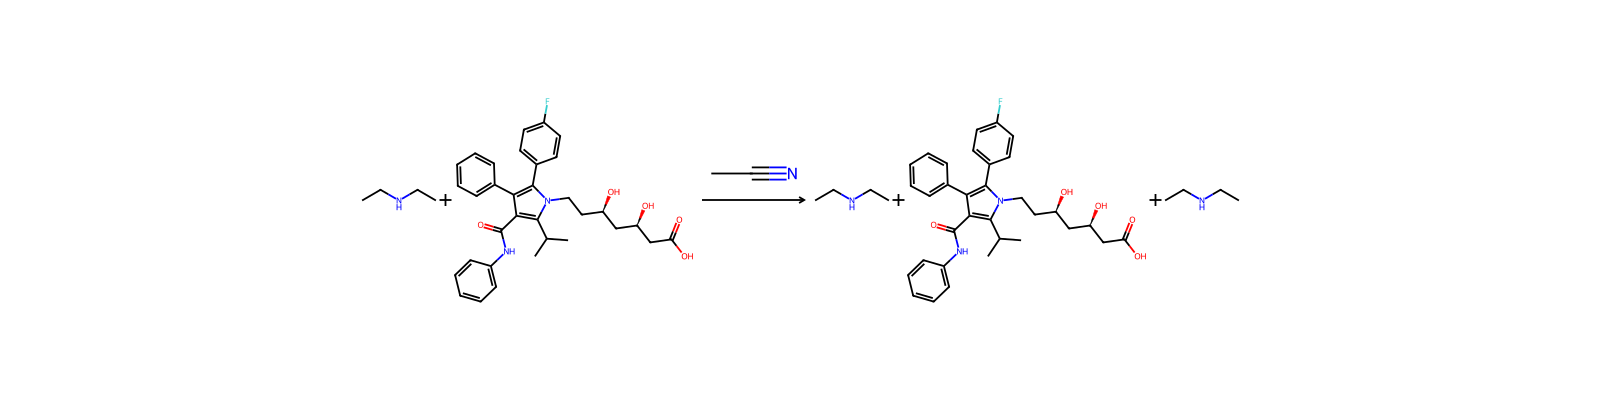
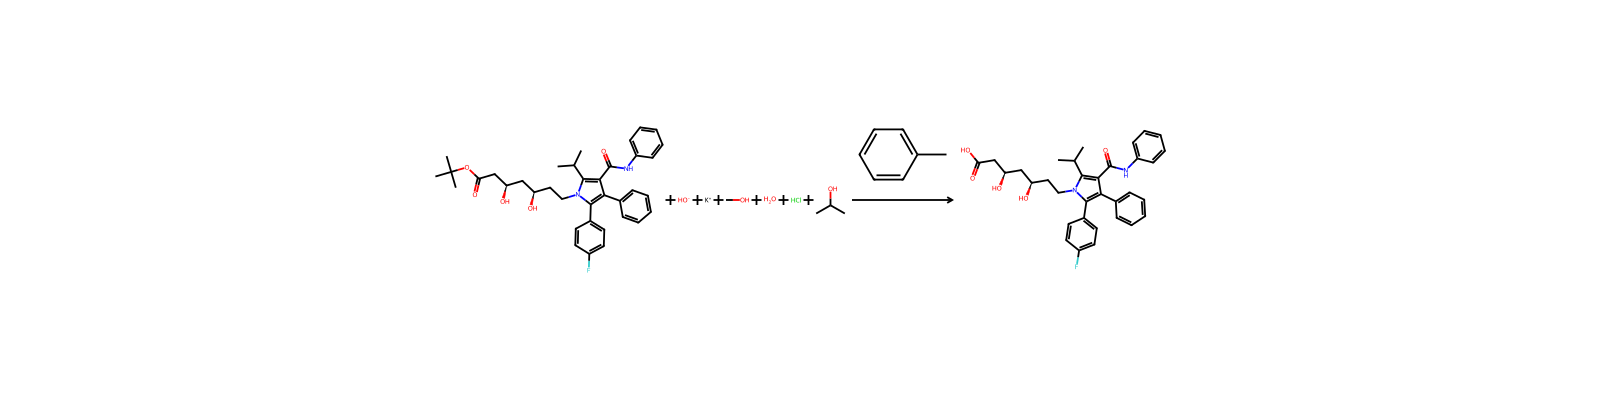
연결된 노트
불러오는 중…