
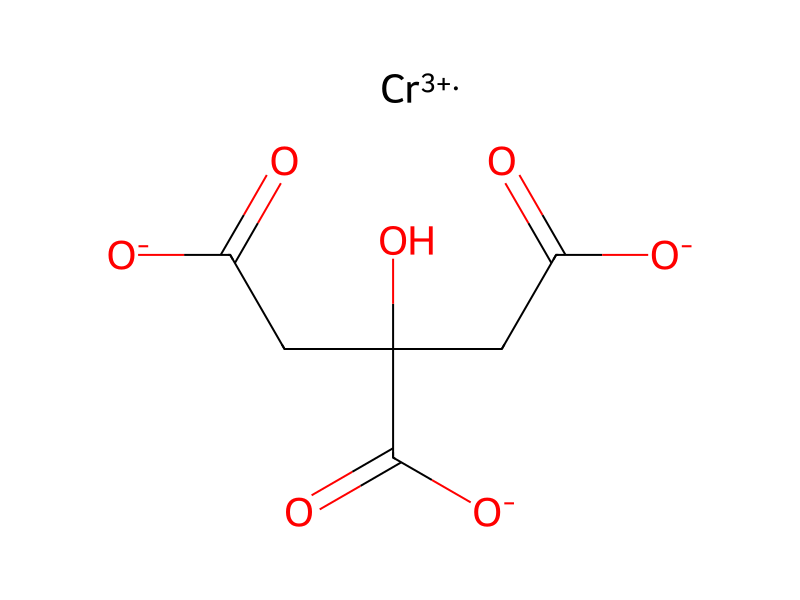
기본 정보
- CAS
57072-40-9- 표준 SMILES
O=C([O-])CC(O)(CC(=O)[O-])C(=O)[O-].[Cr+3]- InChIKey
SWXXYWDHQDTFSU-UHFFFAOYSA-K- 분자식
- C6H5CrO7
- 평균 분자량
- 241.1 g/mol
- 단동위원소 질량
- 240.944035
이름 및 식별자
- 우선 이름
- Chromic citrate
- IUPAC
- chromium(3+);2-hydroxypropane-1,2,3-tricarboxylate
- 영어명
- CHROMIC CITRATE
- 분자식
- C6H8CrO7
- 분자량
- 244.12
이름 및 동의어
CHROMIC CITRATEchromium(III) citrateCitric acid, chromium saltCHROMIUM CITRATE57072-40-9chromium(3+) citrateLQC76G8WUEEINECS 260-543-61,2,3-Propanetricarboxylic acid, 2-hydroxy-, chromium(3+) saltDTXSID401019640CHROMIUM(III) CITRATE [WHO-DD]1,2,3-PROPANETRICARBOXYLIC ACID, 2-HYDROXY-, CHROMIUM(3+) SALT (1:1)
이름 더 보기
2-Hydroxy-1,2,3-propanetricarboxylic acid/chromium(III),(1:x) salt
685853-81-0RefChem:576864DTXCID40128176260-543-6UNII-LQC76G8WUEchromium(3+) 2-hydroxypropane-1,2,3-tricarboxylateSCHEMBL23943DB14526
데이터베이스 식별자
- CAS
57072-40-9、685853-81-0- PubChem CID
- 6453431
- DTXSID
DTXSID401019640- UNII
- LQC76G8WUE
- EC Number
- 260-543-6、614-626-2
물성
구조 계산 물성
- 극성 표면적
- 141 Ų
- 수소 결합 공여자 수
- 1
- 수소 결합 수용자 수
- 7
- 회전 가능 결합 수
- 2
- 무거운 원자 수
- 14
- 형식 전하
- 0
- 복잡도
- 211
안전 및 규제
GHS 분류
GHS Classification
This chemical does not meet GHS hazard criteria for 33.3% (1 of 3) of reports.
Warning
H302 (33.3%): Harmful if swallowed [Warning Acute toxicity, oral]
P261, P264, P264+P265, P270, P271, P280, P301+P317, P302+P352, P304+P340, P305+P351+P338, P317, P319, P321, P330, P332+P317, P337+P317, P362+P364, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 3 reports by companies from 3 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Warning
유해성 정보
Regulatory InformationREACH registered substance: 1,2,3-Propanetricarboxylic acid, 2-hydroxy-, chromium (3+) salt (EC: 614-626-2)
Hazard Classes and Categories
Acute Tox. 4 (33.3%)
Skin Irrit. 2 (100%)
안전 데이터
- 신호 어
- Warning
- 유해·위험 문구
- 암호 유해·위험 문구 위험 등급 범주 신호 어 그림 문자 P- 코드 H302
화학 및 산업
약리 정보
Protein Binding
In the blood, 95% of chromium (III) is bound to large molecular mass proteins, such as transferrin, while a small proportion associates with low molecular mass oligopeptides. Serum chromium is bound to transferrin in the beta globulin fraction.
Pharmacodynamics
Trivalent chromium is part of glucose tolerance factor, an essential activator of insulin-mediated reactions. Chromium helps to maintain normal glucose metabolism and peripheral nerve function. Chromium increases insulin binding to cells, increases insulin receptor density and activates insulin receptor kinase leading to enhanced insulin sensitivity. In chromium deficiency, intravenous administration of chromium resulted in normalization of the glucose tolerance curve from the diabetic-like curve typical of chromium deficiency.
Mechanism of Action
Chromium is an essential nutrient involved in the metabolism of glucose, insulin and blood lipids. Its role in potentiating insulin signalling cascades has been implicated in several studies. Chromium upregulates insulin-stimulated insulin signal transduction via affecting effector molecules downstream of the insulin receptor (IR). IR-mediated signalling pathway involves phoshorylation of multiple intracellular domains and protein kinases, and downstream effector molecules. Upon activation by ligands, intracellular β-subunit of IR autophosphorylates and activates tyrosine kinase domain of the IR, followed by activation and phosphorylation of regulatory proteins and downstream signalling effectors including phosphatidylinositol 2-kinase (PI3K). PI3K activates further downstream reaction cascades to activate protein kinase B (Akt) to ultimately promote translocation of glucose transporter-4 (Glut4)-vesicles from the cytoplasm to the cell surface and regulate glucose uptake. Chromium enhances the kinase activity of insulin receptor β and increases the activity of downstream effectors, pI3-kinase and Akt. Under insulin-resistant conditions, chromium also promotes GLUT-4 transporter translocation that is independent of activity of IR, IRS-1, PI3-kinase, or Akt; chromium mediates cholesterol efflux from the membranes via increasing fluidity of the membrane by decreasing the membrane cholesterol and upregulation of sterol regulatory element-binding protein. As a result, intracellular GLUT-4 transporters are stimulated to translocate from intracellular to the plasma membrane, leading to enhanced glucose uptake in muscle cells. Chromium attenuates the activity of PTP-1B _in vitro,_ which is a negative regulator of insulin signaling. It also alleviates ER stress that is observed to be elevated the suppression of insulin signaling. ER stress is thought to activate c-Jun N-terminal kinase (JNK), which subsequently induces serine phosphorylation of IRS and aberration of insulin signalling. Transient upregulation of AMPK by chromium also leads to increased glucose uptake.
Biological Half-LifeThe elimination half-life of hexavalent chromium is 15 to 41 hours.
Metabolism/Metabolites
The metabolism of Cr (VI) involves reduction by small molecules and enzyme systems to generate Cr (III) and reactive intermediates. During this process, free radicals can be generated, which is thought to induce damage of cellular components and cause toxicity of chromium. The metabolites bind to cellular constituents.
Absorption, Distribution and Excretion
Chromium compounds are both absorbed by the lung and the gastrointestinal tract. Oral absorption of chromium compounds in humans can range between 0.5% and 10%, with the hexavalent (VI) chromium more easily absorbed than the trivalent (III) form. Absorption of chromium from the intestinal tract is low, ranging from less than 0.4% to 2.5% of the amount consumed. Vitamin C and the vitamin B niacin is reported to enhance chromium absorption. Most hexavalent Cr (VI) undergoes partial intragastric reduction to Cr (III) upon absorption, which is an action mainly mediated by sulfhydryl groups of amino acids. Cr (VI) readily penetrates cell membranes and chromium can be found in both erythrocytes and plasma after gastrointestinal absorption of Cr (IV). In comparison, the presence of chromium is limited to the plasma as Cr (III) displays poor cell membrane penetration. Once transported through the cell membrane, Cr (VI) is rapidly reduced to Cr (III), which subsequently binds to macromolecules or conjugate with proteins. Cr (III) may be bound to transferrin or other plasma proteins, or as complexes, such as glucose tolerance factor (GTF).
Absorbed chromium is excreted mainly in the urine, accounting for 80% of total excretion of chromium; small amounts are lost in hair, perspiration and bile. Chromium is excreted primarily in the urine by glomerular filtration or bound to a low molecular-weight organic transporter.
Absorbed chromium is distributed to all tissues of the body and its distribution in the body depends on the species, age, and chemical form. Circulating Cr (III) following oral or parenteral administration of different compounds can be taken up by tissues and accumulates in the liver, kidney, spleen, soft tissue, and bone.
Excretion of chromium is via the kidneys ranges from 3 to 50 μg/day. The 24-hour urinary excretion rates for normal human subjects are reported to be 0.22 μg/day.
공급사5 곳
江阴市贝壳化学有限公司15312220685 · [email protected]
河南天孚化工有限公司+86-0371-55170693 +86-19937530512 · [email protected]
陕西省商南县东正化工有限责任公司400-8031088 17792857068
江阴市贝壳化学有限公司0510-15312220685 15312220685 · [email protected]
DAYANG CHEM (HANGZHOU) CO.,LTD+86-88938639 +86-17705817739 · [email protected]
관련 반응
1건
화합물 노트
불러오는 중…