
Grundinformationen
- Standard-SMILES
CCC(=O)N(c1ccccc1)C1CCN(CCc2ccccc2)CC1- InChIKey
PJMPHNIQZUBGLI-UHFFFAOYSA-N- Summenformel
- C22H28N2O
- Durchschnittliche Molmasse
- 336,5 g/mol
- Monoisotopische Masse
- 336,22016352
Überblick
Fentanyl is a monocarboxylic acid amide resulting from the formal condensation of the aryl amino group of N-phenyl-1-(2-phenylethyl)piperidin-4-amine with propanoic acid. It has a role as an opioid analgesic, an anaesthetic, an intravenous anaesthetic, a mu-opioid receptor agonist, an anaesthesia adjuvant and an adjuvant. It is an anilide, a member of piperidines and a monocarboxylic acid amide.
Namen und Bezeichner
- Bevorzugter Name
- Fentanyl
- IUPAC
- N-phenyl-N-[1-(2-phenylethyl)piperidin-4-yl]propanamide
- Lokaler Name
- Fentanyl
- Englischer Name
- 2-Amino-2-methyl-1-propanol
- Summenformel
- C22H28N2O
- Molmasse
- 336.47
Namen und Synonyme
fentanylPhentanylFentanilFentanest437-38-7DuragesicSublimaseFentanylumDurogesicFentanilaMatrifenDuragesic-100
Weitere Namen anzeigen
AMP-95FENTANYL BASEFTNAbstralFentoraFentanyPentanyl
Duragesic-12Duragesic-25Duragesic-50Duragesic-75Fentanyl-12Fentanyl-25Fentanyl-50Fentanyl-75
Datenbank-Bezeichner
- CAS
437-38-7- PubChem CID
- 3345
- DTXSID
DTXSID9023049- ChEMBL
CHEMBL596- ChEBI
CHEBI:119915- UNII
- UF599785JZ
- EC Number
- 207-113-6
- Nikkaji
- J5.736C
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- 4
- Polarare Oberfläche (TPSA)
- 23,6 Ų
- H-Brücken-Donoren
- 0
- H-Brücken-Akzeptoren
- 2
- Frei drehbare Bindungen
- 6
- Schwere Atome
- 25
- Formalladung
- 0
- Komplexität
- 391
Experimentelle und physikochemische Eigenschaften
Chemical Classes
Other Uses -> Pharmaceuticals
-> NIOSH Emergency Response Categories
Drugs
DEA NFLIS-Drug Category -> Fentanyl and Fentanyl-related
DEA Schedule II Controlled Substance -> Opiates
Pharmaceuticals -> Analgesics (Anesthetics)
Pharmaceuticals
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Synthetic Cannabinoids or Psychoactive Compounds
LogP
log Kow = 4.05
3.9
4.05
Color/FormCrystals
Solubility
0.74mg/mL
In water, 200 mg/L at 25 °C
2.40e-02 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Analgesics, Opioid; Narcotics; Anesthetics, Intravenous; Opiates
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
FDA approved drugs -> Active ingredient
Pharmaceuticals
Animal DrugsActive Ingredients (Fentanyl) -> FDA Greenbook
DecompositionWhen heated to decomposition it emits toxic fumes of /nitrogen oxides/.
Melting Point
83-84
85.2 °C
White crystalline powder; MP: 149-151 °C; bitter taste. Soluble in methanol; slightly soluble in chloroform /Fentanyl citrate/
87.5 °C
Vapor Pressure4.43X10-9 mm Hg at 25 °C (estrapolated)
Physical Description
Solid
Crystals or crystalline powder.
Dissociation Constants
8.43
8.99
pKa = 7.3
Odorless; pKa: 8.3 /Fentanyl citrate/
Physikochemische Eigenschaften
- Schmelzpunkt
- 83 · 83-84°C
- Siedepunkt
- 466 ℃ · 466℃
- Dichte
- 1.087 · 1.087
- Brechungsindex
- 1.65 · 1.6500 (estimate)
- Flammpunkt
- 186 ℃ · 186℃
- storage temp.
- -20 °C · Controlled Substance, -20°C Freezer
- Löslichkeit
- Practically insoluble in water, freely soluble in ethanol (96 per cent) and in methanol
- pka
- 8.4 · 8.4(at 25℃)
- Aggregatzustand
- A crystalline solid
- Farbe
- Crystals
- Wasserlöslichkeit
- 0.2 g/L · 0.2g/L(25 ºC)
- Henry's Law Constant
- 1.1 · 1.1×106 mol/(m3Pa) at 25℃, HSDB (2015)
- Stabilität
- Hygroscopic
- Major Application
- pharmaceutical (small molecule)
- InChI
- 1S/C22H28N2O/c1-2-22(25)24(20-11-7-4-8-12-20)21-14-17-23(18-15-21)16-13-19-9-5-3-6-10-19/h3-12,21H,2,13-18H2,1H3
- InChIKey
- PJMPHNIQZUBGLI-UHFFFAOYSA-N
- SMILES
- N2(CCC(CC2)N(c3ccccc3)C(=O)CC)CCc1ccccc1
- EPA chemische Informationen
- 1 · Propanamide, N-phenyl-N-[1-(2-phenylethyl)-4-piperidinyl]- (437-38-7)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Danger
H300 (98.7%): Fatal if swallowed [Danger Acute toxicity, oral]
P203, P233, P260, P261, P262, P263, P264, P270, P271, P272, P273, P280, P284, P301+P316, P302+P352, P304+P340, P316, P318, P320, P321, P330, P333+P317, P342+P316, P361+P364, P362+P364, P403, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 77 reports by companies from 13 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Gefahrenhinweise
Regulatory Information
DEA schedule II controlled substance
Fentanyl: HSNO Approval: HSR007044 Approved with controls
Other Safety Information- Indoor Air: Fentanyl can be released into indoor air as fine particles or liquid spray (aerosol).
Hazards Summary
Fentanyl is a solid. It is a Schedule II controlled substance. Fentanyl citrate is a strong analgesic used preoperatively, during surgery, and in the immediate postoperative period for its analgesic action. . . . Introduced into clinical practice in the 1960s, the analgesic fentanyl is 100 times more potent than morphine. [HSDB] TLV Basis is CNS impairment and respiratory depression; [ACGIH TLVs and BEIs]
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including fentanyl, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including fentanyl citrate, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Fentanyl citrate/
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Fentanyl is included on this list.
Schedule II shall consist of the drugs and other substances, by whatever official name, common or usual name, chemical name, or brand name designated, listed in this section. Each drug or substance has been assigned the DEA Controlled Substances Code Number set forth opposite it. ... Opiates. Unless specifically excepted or unless in another schedule any of the following opiates, including its isomers, esters, ethers, salts and salts of isomers, esters and ethers whenever the existence of such isomers, esters, ethers, and salts is possible within the specific chemical designation, dextrorphan and levopropoxyphene excepted:. Fentanyl (DEA Code Number: 9801) is included on this list.
Ophthalmic and topical dosage form new animal drugs. Fentanyl. ... Indications for use. For the control of postoperative pain associated with surgical procedures in dogs. ... Limitations. Fentanyl is a Class II controlled substance. Observe all "black-box warnings" on product labeling. Federal law restricts this drug to use by or on the order of a licensed veterinarian.
Explosion Hazards-
Special Reports
DHHS/NIDA; Research Monograph Series 52: Testing Drugs for Physical Dependence Potential and Abuse Liability (1984) DHHS Pub No. (ADM)87-1332
DHHS/NIDA; Research Monograph Series 54: Mechanisms of Tolerance and Dependence (1984) DHHS Pub No. (ADM)88-1330
DHHS/NIDA; Research Monograph Series 56: Etiology of Drug Abuse: Implications for Prevention (1987) DHHS Pub No. (ADM)87-1335
DHHS/NIDA; Research Monograph Series 59: Current Research on the Consequences of Maternal Drug Abuse (1985) DHHS Pub No. (ADM)85-1400
For more Special Reports (Complete) data for Fentanyl (10 total), please visit the HSDB record page.
Chemical Dangers- Hazardous polymerization will not occur.
History and Incidents
On October 23, 2002, in the middle of an evening performance at a Moscow music theater, some 50 Chechen terrorists equipped with firearms as well as large quantities of explosives suddenly seized the venue and the 800 people inside. The terrorists threatened to kill everyone inside unless Russia ended the war in Chechnya. Although the Chechen militants agreed to release some of the hostages during the first couple of days, negotiations with the Russian authorities eventually stalled. Just before dawn on October 26, Russian special police units resorted to using an incapacitating gas based on the drug fentanyl to end the crisis. All of the Chechen militants were killed, and most of the civilian captives survived. But while the operation was largely a success, at least 117 of the hostages died from the effects of the gas. /Incapacitating gas based on the drug fentanyl/
Hazard Classes and CategoriesAcute Tox. 2 (98.7%)
Sicherheit und Schutzausrüstung
Fire Fighting- Burning may produce carbon monoxide, carbon dioxide, and nitrogen oxides.
Disposal Methods
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Threshold Limit Values (TLV)
0.00001 [mg/m3], inhalable particulate matter (Surface Level = 1 ug/100cm2)
0.00002 [mg/m3], inhalable particulate matter
Effects of Short Term ExposureIt is unknown whether chronic or repeated exposure to fentanyl increases the risk of carcinogenicity, reproductive toxicity, or developmental toxicity.
Personal Protective Equipment (PPE)GENERAL INFORMATION
Toxikologische Informationen
Body Burden
The concentration of fentanyl excreted in sweat was 0.17-10.2 ng/uL in persons treated with a total daily dose of 600 ug(1).
... Following an observed spike of heroin-fentanyl related deaths in Melbourne, Australia, a study was undertaken to determine the prevalence of these cases. All reportable deaths occurring in Victoria during 2015 and submitted to the toxicology laboratory were analysed using LC-MS-MS to confirm the combination of the heroin marker 6-acetylmorphine and/or morphine, and fentanyl. Over 4,000 coronial cases in 2015 underwent toxicological analysis for these drugs, there were nine cases identified that involved fentanyl-laced heroin. ... The ages ranged from 25 to 57 years with an average of 40 and median of 37 years, and consisted of eight males and one female. The average and median femoral blood concentration of fentanyl was 18 and 20 ng/mL (range: <1-45 ng/mL), and morphine 140 and 80 ng/mL (range: 20-400 ng/mL), respectively. All nine cases had 6-acetylmorphine detectable in blood. Urine analysis was also performed where available. ...
... Here we report two cases of fatal intravenous injection of the content from fentanyl patches. Both were male drug addicts, found dead within a one week interval in the same apartment. Post-mortem femoral blood was screened for amphetamines, cannabinoids, cocaine, and opioids with immunological methods (EMIT II) and further with headspace gas chromatography for alcohol and with liquid chromatography mass spectrometry (LC-MS) for different drugs, including fentanyl. ... In the first case, the toxicological analysis revealed fentanyl (2.7 ng/mL), morphine (31.4 ng/mL), and ethanol (1.1 g/L) in postmortem blood and amphetamine, cannabinoids, morphine, and ethanol (1.4 g/L) in postmortem urine. In the second case, the analysis revealed fentanyl (13.8 ng/mL), 7-aminoclonazepam (57.1 ng/mL), and sertralin (91.9 ng/mL) in postmortem blood and a small amount of ethanol (0.1 g/L) in postmortem urine. ...
In 2013 and 2014, more than 700 deaths were attributed to fentanyl and fentanyl analogs in the United States. Of recent concern is the cluster of unintentional fentanyl overdoses because of tablets thought to be "Norco" purchased on the street in Northern California. U-47700 (trans-3,4-dichloro-N-[2-(dimethyl-amino)cyclohexyl]-N-methylbenz-amide) is a nonfentanyl-based synthetic opioid with 7.5 times the binding affinity of morphine to mu-opioid. We report a case of fentanyl and U-47700 intoxication from what was thought to be illicitly purchased Norco. A 41-year-old woman presented to the emergency department (ED) for altered mental status shortly after ingesting 3 beige Norco pills bearing a Watson imprint. She had pinpoint pupils and respiratory depression, which reversed after 0.4 mg naloxone administration intravenously. She had complete recovery and was discharged from the ED after a 4-hour observation period. Serum testing with liquid chromatography-quadrupole time-of-flight mass spectrometry (LC 1260 QTOF/MS 6550; Agilent, Santa Clara, CA) confirmed the presence of the medications the patient reported receiving, and additionally fentanyl (15.2 ng/mL) and U-47700 (7.6 ng/mL). In this case report, street Norco purchased in Central California resulted in altered mental status requiring naloxone reversal because of fentanyl and the novel synthetic opioid U-47700. Because these compounds are not detected by routine urine drug testing and physical examination findings are similar to those of a traditional opioid toxidrome, emergency providers should use the patient's history and other circumstantial details to aid in diagnosis. In cases with suspicion of opioid or opioid analogue cause, we recommend that emergency providers contact their local poison control center, medical toxicologist, or public health department to aid in the investigation.
For more Body Burden (Complete) data for Fentanyl (16 total), please visit the HSDB record page.
Treatment
For the management of hypoventilation, immediate countermeasures include removing the Fentanyl and physically or verbally stimulating the patient. These actions can be followed by administration of a specific narcotic antagonist such as naloxone. The duration of hypoventilation following an overdose may be longer than the effects of the narcotic antagonist's action (the half-life of naloxone ranges from 30 to 81 minutes). The interval between IV antagonist doses should be carefully chosen because of the possibility of re-narcotization after system removal; repeated administration of naloxone may be necessary. Reversal of the narcotic effect may result in acute onset of pain and the release of catecholamines. Always ensure a patent airway is established and maintained, administer oxygen and assist or control respiration as indicated and use an oropharyngeal airway or endotracheal tube if necessary. Adequate body temperature and fluid intake should be maintained. (L1712)
Interactions
Serotonin syndrome is a syndrome identified by a triad of altered mental status, neuromuscular overactivity, and autonomic instability caused by the overstimulation of serotonin in the central nervous system and periphery. Serotonin syndrome may be provoked with the addition or increase in serotonergic agents such as selective serotonin reuptake inhibitors, serotonin norepinephrine reuptake inhibitors, tricyclic antidepressants, and monoamine oxidase inhibitors as well as other agents with serotonergic properties. Some narcotics, including fentanyl and methadone, have these properties and may be associated with the development of serotonin syndrome when used in conjunction with other agents. Currently, there are no identified case reports of narcotics as the sole agent causing serotonin syndrome. This report provides a brief overview of serotonin syndrome, particularly with cases involving administration of narcotics such as fentanyl and methadone. The case described is the first report associated with fentanyl and methadone without the coadministration of other serotonergic agents, and a possible drug interaction with voriconazole is discussed. This raises awareness of using multiple serotonergic narcotics and the potential precipitation of serotonin syndrome.
There is an unmet clinical need to develop a pharmacological therapy to counter opioid-induced respiratory depression without interfering with analgesia or behavior. Several studies have demonstrated that 5-HT1A receptor agonists alleviate opioid-induced respiratory depression in rodent models. However, there are conflicting reports regarding their effects on analgesia due in part to varied agonist receptor selectivity and presence of anesthesia. Therefore the authors performed a study in rats with befiradol (F13640 and NLX-112), a highly selective 5-HT1A receptor agonist without anesthesia. Respiratory neural discharge was measured using in vitro preparations. Plethysmographic recording, nociception testing, and righting reflex were used to examine respiratory ventilation, analgesia, and sedation, respectively. Befiradol (0.2 mg/kg, n = 6) reduced fentanyl-induced respiratory depression (53.7 +/- 5.7% of control minute ventilation 4 min after befiradol vs. saline 18.7 +/- 2.2% of control, n = 9; P < 0.001), duration of analgesia (90.4 +/- 11.6 min vs. saline 130.5 +/- 7.8 min; P = 0.011), duration of sedation (39.8 +/- 4 min vs. saline 58 +/- 4.4 min; P = 0.013); and induced baseline hyperventilation, hyperalgesia, and "behavioral syndrome" in nonsedated rats. Further, the befiradol-induced alleviation of opioid-induced respiratory depression involves sites or mechanisms not functioning in vitro brainstem-spinal cord and medullary slice preparations. The reversal of opioid-induced respiratory depression and sedation by befiradol in adult rats was robust, whereas involved mechanisms are unclear. However, there were adverse concomitant decreases in fentanyl-induced analgesia and altered baseline ventilation, nociception, and behavior.
Chlorpromazine is used concurrently with meperidine to enhance its analgesic effect. However, such concurrent use ... may enhance & prolong the respiratory depression produced by meperidine. ... Fentanyl ... /has/ been reported to interact with promethazine /and may produce similar effects/.
Droperidol does not produce analgesia but is a potent neuroleptic agent. It has been suggested that each compound in the droperidol-fentanyl mixture exerts its own pharmacologic action without any well defined antagonistic or potentiating actions. However, there is one exception; droperidol enhances the analgesic potency of fentanyl through a potentiative rather than an additive effect, the mechanism of which is unknown.
For more Interactions (Complete) data for Fentanyl (24 total), please visit the HSDB record page.
Health EffectsMedical problems can include congested lungs, liver disease, tetanus, infection of the heart valves, skin abscesses, anemia and pneumonia. Death can occur from overdose.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 39,600(SRC), determined from a structure estimation method(2), indicates that fentanyl is expected to be immobile in soil. The pKa of fentanyl is 7.3(3), indicating that this compound will exist partially in cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization of the cation from moist soil is not expected because cations do not volatilize(SRC). Volatilization of the neutral form of fentanyl from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 9.8X10⁻¹² atm-cu m/mole(SRC), based upon its vapor pressure, 4.43X10⁻⁹ mm Hg(5), and water solubility, 200 mg/L(6). Fentanyl is not expected to volatilize from dry soil surfaces(SRC) based upon its vapor pressure(5). Biodegradation data in soil were not available(SRC, 2017).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 39,600(SRC), determined from a structure estimation method(2), indicates that fentanyl is expected to adsorb to suspended solids and sediment(SRC). A pKa of 7.3(3) indicates fentanyl will exist partially in the cation form at pH values of 5 to 9 and, therefore, volatilization of the cation from water surfaces is not expected(SRC). Volatilization from water surfaces of neutral fentanyl is not expected(4) based upon an estimated Henry's Law constant of 9.8X10⁻¹² atm-cu m/mole(SRC), from its vapor pressure, 4.43X10⁻⁹ mm Hg(5), and water solubility, 200 mg/L(6). Fentanyl is not expected to undergo hydrolysis in the environment due to the lack of functional groups that hydrolyze under environmental conditions(4). According to a classification scheme(7), an estimated BCF of 220(SRC), from a log Kow of 4.05(8) and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is high. Biodegradation data in water were not available(SRC, 2017).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), fentanyl, which has a vapor pressure of 4.43X10⁻⁹ mm Hg at 25 °C(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase fentanyl may be removed from the air by wet and dry deposition(SRC). Fentanyl contains chromophores that absorb at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
Adverse Effects
ACGIH Carcinogen - Not Classifiable.
Fentanyl's side effects are similar to those of heroin, which produce euphoria, confusion, respiratory depression (which, if extensive and untreated, may lead to arrest), drowsiness, nausea, visual disturbances, dyskinesia, hallucinations, delirium, a subset of the latter known as "narcotic delirium," analgesia, constipation, narcotic ileus, muscle rigidity, constipation, addiction, loss of consciousness, hypotension, coma, and even death. Alcohol and other drugs (ie, cocaine, heroin) can synergistically exacerbate fentanyl's side effects, creating multi-layered clinical scenarios that can be complex to manage. These substances, taken together, generate undesirable conditions that complicate the patient's prognosis.
Exposure Routes
Fentanyl can be absorbed into the body via inhalation, oral exposure or ingestion, or skin contact. It is not known whether fentanyl can be absorbed systemically through the eye. Fentanyl can be administered intravenously (IV), intramuscularly (IM), or as a skin patch (transdermally).
Epidural; parental (transdermal, intramuscular).
Toxicity Summary
IDENTIFICATION AND USE: Fentanyl is a solid. It is a Schedule II controlled substance. Fentanyl citrate is a strong analgesic used preoperatively, during surgery, and in the immediate postoperative period for its analgesic action. In addition, the drug may be used to prevent or relieve tachypnea and postoperative emergence delirium. HUMAN STUDIES: Introduced into clinical practice in the 1960s, the analgesic fentanyl is 100 times more potent than morphine. Various methods of administration exist including the transdermal patch system, widely used in chronic pain and palliative care settings. Numerous, often imaginative methods of abuse of fentanyl patches have been reported, the majority of fatal fentanyl overdose cases resulting from deliberate abuse or suicide. The most serious adverse effect of fentanyl is respiratory depression. Fentanyl should be administered only under the supervision of qualified clinicians. Patients receiving fentanyl should be advised of the importance of taking the drug exactly as prescribed. Skeletal and thoracic muscle rigidity occurs frequently, especially following rapid IV administration of fentanyl. Muscular rigidity may be associated with reduced pulmonary compliance and/or apnea, laryngospasm, and bronchoconstriction and may be managed by use of assisted or controlled respiration or, if necessary, by IV administration of a neuromuscular blocking agent. Bradycardia may occur following administration of fentanyl and may be controlled with atropine. Delayed chest wall muscle rigidity may develop up to 24 hours after administration or 9 hours after after ending an IV infusion and may persist for hours. Masseter muscle spasm and laryngospasm may also occur. Acute overdosage produces signs of opioid toxicity: circulatory and CNS depression, lethargy, coma, respiratory depression, and decreased GI motility with ileus. Miosis is a variable finding, depending on the particular opioid, co-ingestants, and secondary effects, such as hypoxia. Apnea, hypotension, bradycardia, non-cardiogenic pulmonary edema, seizures, dysrhythmias, and death may occur with severe poisoning. With continued use, tolerance to the pharmacologic and adverse effects of the drug develop, but the rate of development of tolerance exhibits considerable interindividual variation. ANIMAL STUDIES: Fentanyl was not teratogenic in rats at dosages of 10-500 ug/kg daily when administered on days 7-21 of gestation. At an IV dosage of 10-30 ug/kg daily on days 6-18 of gestation in rats, fentanyl was embryotoxic or fetotoxic and slightly increased mean delivery time in animals receiving the highest dosage, but the drug was not teratogenic. At IV doses of 30 ug/kg or subcutaneous doses of 160 ug/kg in rats, fentanyl increased embryonic resorptions. Fentanyl citrate was not mutagenic in the in vitro Ames reverse mutation assay in S. typhimurium or E. coli, or the mouse lymphoma mutagenesis assay, and was not clastogenic in the in vivo mouse micronucleus assay. In veterinary use, overdosage may produce profound respiratory and/or CNS depression in most species. Newborns may be more susceptible to these effects than adult animals. Other toxic effects may include cardiovascular collapse, tremors, reck rigidity, and seizures.
Typically, a fentanyl overdose manifests as an extrapolation of its pharmacological side effects. Although the clinical scenarios may vary among patients, one of the main concerns is the level of expression of OIRD. In such cases, oxygen administration and respiratory assistance are a priority. An opioid drug antagonist such as naloxone can help to correct OIRD symptoms. Commonly, repeated doses are necessary since, over time, respiratory depression may overcome the effects of the antagonist drug, particularly with opiates such as fentanyl, in which increased receptor affinity may be present as compared to other opiates. Thus, the therapeutic approach should continue until a normal respiratory rate coincides with appropriate oxygen saturation levels.
Opiate receptors are coupled with G-protein receptors and function as both positive and negative regulators of synaptic transmission via G-proteins that activate effector proteins. Binding of the opiate stimulates the exchange of GTP for GDP on the G-protein complex. As the effector system is adenylate cyclase and cAMP located at the inner surface of the plasma membrane, opioids decrease intracellular cAMP by inhibiting adenylate cyclase. Subsequently, the release of nociceptive neurotransmitters such as substance P, GABA, dopamine, acetylcholine and noradrenaline is inhibited. Opioids also inhibit the release of vasopressin, somatostatin, insulin and glucagon. Fentanyl's analgesic activity is, most likely, due to its conversion to morphine. Opioids close N-type voltage-operated calcium channels (OP2-receptor agonist) and open calcium-dependent inwardly rectifying potassium channels (OP3 and OP1 receptor agonist). This results in hypopolarization and reduced neuronal excitability.
Signs and Symptoms
- Irritation may occur.
- Contracted or pinpoint pupils (miosis) (may later become dilated), reduced level of consciousness (CNS depression), reduced respiratory function (respiratory depression), reduced blood oxygen content (hypoxia), accumulation of acid in the blood (acidosis), low blood pressure (hypotension), slow heart rate (bradycardia), shock, slowing of muscular movement of the stomach (gastric hypomotility) with intestinal obstruction due to lack of normal muscle function (ileus), accumulation of fluid in the lungs (pulmonary edema), lethargy, coma, and death.
- See Ingestion Exposure.
- See Ingestion Exposure.
More common symptoms are dizziness, light-headedness, or feeling faint; drowsiness; nausea or vomiting; unusual tiredness or weakness. Less common or rare ones are blurred or double vision or other vision problems; confusion; constipation; convulsions (seizures); difficult or painful urination; mental depression; shortness of breath, trouble in breathing, tightness in the chest, or wheezing; skin rash, hives, or itching; unusual excitement (L1484)
Ongoing Test Status
EPA has released the Interactive Chemical Safety for Sustainability (iCSS) Dashboard. The iCSS Dashboard provides an interactive tool to explore rapid, automated (or in vitro high-throughput) chemical screening data generated by the Toxicity Forecaster (ToxCast) project and the federal Toxicity Testing in the 21st century (Tox21) collaboration. /The title compound was tested by ToxCast and/or Tox21 assays/[USEPA; ICSS Dashboard Application; Available from, as of May 1, 2017: http://actor.epa.gov/dashboard/]
Effluent Concentrations
Fentanyl was detected in 6% of effluent samples collected from 90 European wastewater treatment plants at <0.5-1.6 ng/L (average 0.1 ng/L, median <0.1 ng/L); samples were collected in 2010(1). Influent and effluent concentrations of fentanyl have been reported as 1.3-1.7 and <0.1-0.5 ng/L, respectively, in wastewater treatment plants(2).
Soil Adsorption/Mobility
Using a structure estimation method based on molecular connectivity indices(1), the Koc of fentanyl can be estimated to be 39,600(SRC). According to a classification scheme(2), this estimated Koc value suggests that fentanyl is expected to be immobile. The pKa of fentanyl is 7.3(3), indicating that this compound will exist partially in the cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4).
Regulatorische Informationen
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including fentanyl, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including fentanyl citrate, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act. /Fentanyl citrate/
The Generic Animal Drug and Patent Restoration act requires that each sponsor of an approved animal drug must submit to the FDA certain information regarding patents held for the animal drug or its method of use. The Act requires that this information, as well as a list of all animal drug products approved for safety and effectiveness, be made available to the public. Fentanyl is included on this list.
Schedule II shall consist of the drugs and other substances, by whatever official name, common or usual name, chemical name, or brand name designated, listed in this section. Each drug or substance has been assigned the DEA Controlled Substances Code Number set forth opposite it. ... Opiates. Unless specifically excepted or unless in another schedule any of the following opiates, including its isomers, esters, ethers, salts and salts of isomers, esters and ethers whenever the existence of such isomers, esters, ethers, and salts is possible within the specific chemical designation, dextrorphan and levopropoxyphene excepted:. Fentanyl (DEA Code Number: 9801) is included on this list.
Ophthalmic and topical dosage form new animal drugs. Fentanyl. ... Indications for use. For the control of postoperative pain associated with surgical procedures in dogs. ... Limitations. Fentanyl is a Class II controlled substance. Observe all "black-box warnings" on product labeling. Federal law restricts this drug to use by or on the order of a licensed veterinarian.
Sicherheitsdaten
- wgk
- 2
- ridadr
- 1544
- hs_code
- 2933330000
- RTECS-Nr.
- UE5550000
- risk_code
- 11-23/25-36/38-39/23/24/25-23/24/25
- Toxizität
- LD50 orl-rat: 18 mg/kg JPPMAB 25,929,73
- hazard_code
- F,T
- safety_code
- 16-24-45-36/37-7
- hazard_class
- 6.1(b)
- packing_group
- III
- Speicherklasse
- 6.1A - Combustible acute toxic Cat. 1 and 2very toxic hazardous materials
- Giftige Stoffe Daten
- 437-38-7(Hazardous Substances Data)
- Hazard Classifications
- Acute Tox. 1 DermalAcute Tox. 1 InhalationAcute Tox. 2 OralSTOT SE 3
Chemie und Industrie
Pharmakologische Informationen
ATC Code
N02AB03
N - Nervous system
N - Nervous system
QN - Nervous system
QN - Nervous system
N01AH01; N02AB03
Protein Binding
Fentanyl is 80-85% bound to plasma proteins. In one study, a 0.1µg/L solution of fentanyl was 77.9±1.1% bound to human serum albumin and 12.0±5.4% bound to α-1 acid glycoprotein. A 0.1µg/L solution of norfentanyl, the primary metabolite of fentanyl, was 7.62±1.2% bound to human serum albumin and 7.24±1.9% bound to α-1 acid glycoprotein.
Pharmacodynamics
Fentanyl produces strong analgesia through its activation of opioid receptors. It has a duration of action of several hours and a wider therapeutic index as patients develop tolerance to opioids. Fentanyl is associated with a risk of addiction and abuse and should not be mixed with alcohol or benzodiazepines.
Mechanism of Action
Fentanyl binds to opioid receptors, especially the mu opioid receptor, which are coupled to G-proteins. Activation of opioid receptors causes GTP to be exchanged for GDP on the G-proteins which in turn down regulates adenylate cyclase, reducing concentrations of cAMP. Reduced cAMP decreases cAMP dependant influx of calcium ions into the cell. The exchange of GTP for GDP results in hyperpolarization of the cell and inhibition of nerve activity.
The aim of the present study was to describe the activity of a set of opioid drugs, including partial agonists, in a cell system expressing only mu opioid receptors. Receptor activation was assessed by measuring the inhibition of forskolin-stimulated cyclic adenosine mono phosphate (cAMP) production. Efficacies and potencies of these ligands were determined relative to the endogenous ligand beta-endorphin and the common mu agonist, morphine. Among the ligands studied naltrexone, WIN 44,441 and SKF 10047, were classified as antagonists, while the remaining ligands were agonists. Agonist efficacy was assessed by determining the extent of inhibition of forskolin-stimulated cAMP production. The rank order of efficacy of the agonists was fentanyl = hydromorphone = beta-endorphin > etorphine = lofentanil = butorphanol = morphine = nalbuphine = nalorphine > cyclazocine = dezocine = metazocine >or= xorphanol. The rank order of potency of these ligands was different from that of their efficacies; etorphine > hydromorphone > dezocine > xorphanol = nalorphine = butorphanol = lofentanil > metazocine > nalbuphine > cyclazocine > fentanyl > morphine >>>> beta-endorphin. These results elucidate the relative activities of a set of opioid ligands at mu opioid receptor and can serve as the initial step in a systematic study leading to understanding of the mode of action of opioid ligands at this receptor. Furthermore, these results can assist in understanding the physiological effect of many opioid ligands acting through mu opioid receptors.
Diabetic neuropathy is one of the most frequent complications of diabetes mellitus. Therefore, the present study was designed to investigate the anti-hyperalgesic mechanism of fentanyl in a mouse model of streptozotocin-induced diabetic neuropathy. The antinociceptive response was assessed by recording the latency in a tail-flick test. The tail-flick latency in diabetic mice was significantly shorter than that in non-diabetic mice. Fentanyl, at doses of 3 and 10 ug/kg, s.c., produced a dose-dependent increase in the tail-flick latencies in diabetic mice. While fentanyl (3 ug/kg, s.c.) did not produce a significant inhibition of the tail-flick response in non-diabetic mice, it significantly prolonged the tail-flick latency in diabetic mice to the same level as the baseline latency in non-diabetic mice. Although pretreatment with naloxone (3 mg/kg, s.c.) completely antagonized fentanyl-induced antinociception in non-diabetic mice, it had no effect on the antinociceptive effect of fentanyl in diabetic mice. Pretreatment with either of the voltage-gated sodium channel openers fenvarelarte and veratridine practically abolished the antinociceptive effects of fentanyl in diabetic mice. However, neither fenvarelate nor veratridine affected the antinociceptive effect of fentanyl in non-diabetic mice. These results suggest that the anti-hyperalgesic effect of fentanyl is mediated through the blockade of sodium channels in diabetic mice, whereas opioid receptors mediate the antinociceptive effect of fentanyl in non-diabetic mice.
Tolerance to opioids frequently follows repeated drug administration and affects the clinical utility of these analgesics. Studies in simple cellular systems have demonstrated that prolonged activation of opioid receptors produces homologous receptor desensitization by G-protein receptor kinase mediated receptor phosphorylation and subsequent beta-arrestin binding. To define the role of this regulatory mechanism in the control of the electrophysiological and behavioral responses to opioids, we used mice having a targeted disruption of the G-protein receptor kinase 3 (GRK3) gene. Mice lacking GRK3 did not differ from wild-type littermates neither in their response latencies to noxious stimuli on the hot-plate test nor in their acute antinociceptive responses to fentanyl or morphine. Tolerance to the electrophysiological response to the opioid fentanyl, measured in vitro in the hippocampus, was blocked by GRK3 deletion. In addition, tolerance to the antinociceptive effects of fentanyl was significantly reduced in GRK3 knockouts compared to wild-type littermate controls. Tolerance to the antinociceptive effects of morphine was not affected by GRK3 deletion although morphine tolerance in hippocampal slices from GRK3 knockout mice was significantly inhibited. Tolerance developed more slowly in vitro to morphine than fentanyl supporting previous work in in vitro systems showing a correlation between agonist efficacy and GRK3-mediated desensitization. The results of these studies suggest that GRK3-mediated mechanisms are important components of both electrophysiologic and behavioral opioid tolerance. Fentanyl, a high efficacy opioid, more effectively produced GRK3-dependent effects than morphine, a low efficacy agonist.
G protein-coupled receptor desensitization is typically mediated by receptor phosphorylation by G protein-coupled receptor kinase (GRK) and subsequent arrestin binding; morphine, however, was previously found to activate a c-Jun N-terminal kinase (JNK)-dependent, GRK/arrestin-independent pathway to produce mu opioid receptor (MOR) inactivation in spinally-mediated, acute anti-nociceptive responses. In the current study, we determined that JNK2 was also required for centrally-mediated analgesic tolerance to morphine using the hotplate assay. We compared JNK activation by morphine and fentanyl in JNK1(-/-), JNK2(-/-), JNK3(-/-), and GRK3(-/-) mice and found that both compounds specifically activate JNK2 in vivo; however, fentanyl activation of JNK2 was GRK3-dependent, whereas morphine activation of JNK2 was GRK3-independent. In MOR-GFP expressing HEK293 cells, treatment with either arrestin siRNA, the Src family kinase inhibitor PP2, or the protein kinase C (PKC) inhibitor Go6976 indicated that morphine activated JNK2 through an arrestin-independent Src- and PKC-dependent mechanism, whereas fentanyl activated JNK2 through a Src-GRK3/arrestin-2-dependent and PKC-independent mechanism. This study resolves distinct ligand-directed mechanisms of JNK activation by mu opioid agonists and understanding ligand-directed signaling at MOR may improve opioid therapeutics.
Opioids are the most effective and widely used drugs in the treatment of severe acute and chronic pain. They act through opioid receptors that belong to the family of G protein-coupled receptors. Three classes of opioid receptors (mu, delta, kappa), expressed in the central and peripheral nervous system, have been identified. The analgesic effect of opioids is mediated through multiple pathways of opioid receptor signaling (e.g., G(i/o) coupling, cAMP inhibition, Ca(++) channel inhibition). The standard exogenous opioid analgesics used in the operating room are fentanyl, sufentanil, morphine, alfentanil, and remifentanil.
Biological Half-Life
The half life of fentanyl is 7 hours. The half life of fentanyl sublingual spray is 5-12 hours.
Fentanyl kinetics were studied in patients with cirrhosis and in patients with normal hepatic and renal function undergoing surgery under general anaesthesia, the latter group served as the controls. Plasma fentanyl concentrations declined bi-exponentially in the controls with an average elimination half-life (T1/2 beta) of 263 min; total plasma clearance (Cl) as 10.8 mL/kg/min, and total apparent volume of distribution (V beta) 3.81 L/kg. No significant change was observed in patients with cirrhosis: T1/2 beta was 304 min, Cl 11.3 mL/kg/min and V beta 4.41 L/kg. These data suggest that the elimination half-life of fentanyl is not primarily influenced by the rate at which it is metabolized in the liver.
Fentanyl was administered intravenously and transdermally to eight surgical patients to determine the systemic bioavailability and rate of absorption of the transdermally administered drug. Serum fentanyl concentrations reached a plateau approximately 14 hr after placement of the transdermal fentanyl delivery system. This plateau was maintained until removal of the system at 24 hr. The decline in serum fentanyl concentrations after removal of the transdermal system had a terminal half-life of 17.0 +/- 2.3 hr (mean +/- SD), considerably longer than the terminal elimination half-life seen after intravenous administration of fentanyl in the same patients (6.1 +/- 2.0 hr). ...
... In order to determine the bioavailability and absorption of fentanyl from OTFC, 12 volunteers were given intravenous fentanyl citrate or OTFC 15 ug/kg on each of two occasions. On a third occasion, the authors assessed oral administration (gastrointestinal absorption) by giving eight of the same volunteers the same dose of a solution of fentanyl citrate to swallow. In each study, arterial blood samples were taken over 24 hr for analysis of plasma fentanyl. After intravenous (iv) administration of fentanyl ... the terminal elimination half-life was 425 +/- 102 min. ...
Following IV administration of fentanyl citrate in healthy individuals, the estimated initial distribution half-life was about 6 minutes, the second distribution half-life was about 1 hour, and the terminal half-life was about 16 hours.
Studies of IV fentanyl suggest that clearance of the drug may be decreased and half-life increased in geriatric patients. Although the pharmacokinetic profile of fentanyl in healthy Caucasian adults 65 years of age or older (mean age: 71 years) generally was similar to that in adults 18-45 years of age following application of a fentanyl transdermal system labeled as delivering 100 ug/hour for 72 hours, the mean half-life of the drug was longer in geriatric individuals compared with younger adults (34.4 versus 23.5 hours).
Metabolism/Metabolites
Fentanyl is metabolized to a number of inactive metabolites. Fentanyl is 99% N-dealkylated to norfentanyl by cytochrome P450. It can also be amide hydrolyzed to despropionylfentanyl, or alkyl hydroxylated to hydroxyfentanyl which is N-dealkylated to hydroxynorfentanyl.
Fentanyl does not appear to be metabolized in skin when administered transdermally. Data from clinical studies and from studies using a human keratinocyte cell assay indicate that about 92% of a dose delivered from the fentanyl transdermal system is accounted for as unchanged drug in systemic circulation. Total plasma clearance of fentanyl is reported to be about 500 mL/hour per kg (range: 300-700 mL/hour per kg) or 42-53 L/hour.
Fentanyl citrate is metabolized extensively in the liver and the intestinal mucosa. Animal studies indicate that the drug undergoes oxidation via the microsomal enzymes in the liver and intestinal mucosa (principally cytochrome P-450 [CYP] isoform 3A4) to form norfentanyl; the drug also undergoes hydrolysis to form 4-N-anilinopiperidine and propionic acid. Norfentanyl has been shown to be pharmacologically inactive in animal studies. Fentanyl is excreted in the urine as inactive metabolites and as unchanged drug. Less than 10% of a dose is excreted in urine unchanged and only about 1% is excreted in the feces as unchanged drug.
This study was undertaken to determine if metabolites of fentanyl might be useful in the detection and monitoring of substance abuse. The presence of fentanyl and two of its metabolites in the urine and saliva of seven female patients receiving small doses (110 +/- 56 micrograms) of fentanyl was studied up to 96 hr from the time of administration. Fentanyl and its two metabolites (norfentanyl and despropionylfentanyl) were extracted from samples and analyzed by gas chromatography/mass spectrometry. Unchanged fentanyl was detectable in urine in all patients immediately postoperatively and in 3 of 7 patients at 24 hr. By 72 hr, fentanyl was undetectable. Norfentanyl was present in larger quantities than fentanyl immediately postoperatively and was detected in all patients at 48 hr and in 4 of 7 patients at 96 hr. Despropionylfentanyl was not detected in any of the urine specimens tested. Neither fentanyl nor its metabolites could be detected consistently at any time in saliva. Saliva testing does not appear to be a viable alternative to urine testing based on this study. Urinary norfentanyl might be considered as the substance of choice when testing for fentanyl abuse.
Fentanyl has known human metabolites that include Norfentanyl and Phenylacetaldehyde.
Fentanyl is metabolized primarily via human cytochrome P450 3A4 isoenzyme system. Route of Elimination: Fentanyl is metabolized primarily via human cytochrome P450 3A4 isoenzyme system and mostly eliminated in urine. Within 72 hours of IV fentanyl administration, approximately 75% of the dose is excreted in urine, mostly as metabolites with less than 10% representing unchanged drug. Half Life: 7 hours (range 3-12)
FDA Pharmacological Classification
UF599785JZ
FENTANYL
Mechanisms of Action [MoA] - Full Opioid Agonists
Established Pharmacologic Class [EPC] - Opioid Agonist
Fentanyl is an Opioid Agonist. The mechanism of action of fentanyl is as a Full Opioid Agonist.
FENTANYL
MeSH Pharmacological Classification
Compounds with activity like OPIATE ALKALOIDS, acting at OPIOID RECEPTORS. Properties include induction of ANALGESIA or NARCOSIS.
Agents that are administered in association with anesthetics to increase effectiveness, improve delivery, or decrease required dosage.
Agents that induce NARCOSIS. Narcotics include agents that cause somnolence or induced sleep (STUPOR); natural or synthetic derivatives of OPIUM or MORPHINE or any substance that has such effects. They are potent inducers of ANALGESIA and OPIOID-RELATED DISORDERS.
Ultrashort-acting anesthetics that are used for induction. Loss of consciousness is rapid and induction is pleasant, but there is no muscle relaxation and reflexes frequently are not reduced adequately. Repeated administration results in accumulation and prolongs the recovery time. Since these agents have little if any analgesic activity, they are seldom used alone except in brief minor procedures. (From AMA Drug Evaluations Annual, 1994, p174)
Absorption, Distribution and Excretion
Fentanyl sublingual tablets are 54% bioavailable, transmucosal lozenges are 50% bioavailable, buccal tablets are 65% bioavailable, sublingual spray is 76% bioavailable, and nasal spray is 20% more bioavailable than transmucosal (or approximately 64% bioavailable). Fentanyl transmucosal lozenges reach a Cmax of 0.4±0.1ng/mL for a 200µg dose and 2.5±0.6ng/mL for a 1600µg dose with a Tmax of 20-40 minutes. The AUC was 172±96ng\*min/mL for a 200µg dose and 1508±1360ng\*min/mL for a 1600µg dose. Fentanyl sublingual spray reached a Cmax of 0.20±0.06ng/mL for a 100µg dose and 1.61±0.60ng/mL for an 800µg dose with a Tmax of 0.69-1.25 hours, decreasing as the dose increased. The AUC was 1.25±0.67ng\*h/mL for a 100µg dose and 10.38±3.70ng\*h/mL for a 800µg dose. Fentanyl transdermal systems reached a Cmax of 0.24±0.20ng/mL with a Tmax of 3.6±1.3h for a 25µg/h dose. The AUC was 0.42±0.35ng/mL\*h. Fentanyl nasal spray reaches a Cmax of 815±301pg/mL with a Tmax of less than 1 hour for a 200µg/100µL dose. The AUC was 3772pg\*h/mL.
Within 72 hours, 75% of a dose of fentanyl is excreted in the urine with <7% unchanged, and 9% is excreted in the feces with <1% unchanged.
The intravenous volume of distribution is 4L/kg (3-8L/kg). The oral volume of distribution is 25.4L/kg. In hepatically impaired patients, the intravenous volume of distribution ranges from 0.8-8L/kg. Fentanyl crosses the blood brain barrier and the placenta.
Total plasma clearance of fentanyl is 0.5L/hr/kg (0.3-0.7L/hr/kg) or 42L/hr. Following an intravenous dose, surgical patients displayed a clearance of 27-75L/h, hepatically impaired patients displayed a clearance of 3-80L/h, and renally impaired patients displayed a clearance of 30-78L/h.
Because release of fentanyl from fentanyl transdermal systems and percutaneous permeability of the drug are temperature dependent, serum fentanyl concentrations could theoretically increase by approximately one-third in patients with a body temperature of 40 °C. Patients who develop a fever while using fentanyl transdermal system should be observed closely for manifestations of opiate toxicity, and dosage of the drug should be adjusted accordingly. Patients should be cautioned to avoid strenuous exertion that leads to increased core body temperature while wearing the transdermal system. Because application of heat over the fentanyl transdermal system increases mean systemic exposure and peak plasma concentrations of the drug by 120 and 61%, respectively, and has resulted in fatal overdosage, patients wearing a fentanyl transdermal system should be advised to avoid exposing the application site or surrounding area to direct external heat sources.
... The aim of this study was to characterize fentanyl pharmacokinetics in pregnant sheep after intravenous and transdermal dosing during surgical procedure performed to ewe and fetus. Pharmacokinetic parameters reported for non-pregnant sheep and nominal transdermal dose rate were utilized for a priori calculation to achieve analgesic fentanyl concentration (0.5-2 ng/mL) in maternal plasma. A total of 20 Aland landrace ewes at 118-127 gestational days were used. In the first protocol, 1 week before surgery, 10 animals received 2 ug/kg fentanyl intravenous bolus, and on the operation day, transdermal fentanyl patches at nominal dose rate of 2 ug/kg/hr were applied to antebrachium, and ewes were then given a 2 ug/kg intravenous bolus followed by an intra-operative 2.5 ug/kg/hr infusion. In the second protocol, 10 animals received fentanyl only as transdermal patches on the operation day and oxycodone for rescue analgesia. The data were analyzsed with population pharmacokinetic modelling. Intra- and post-operative fentanyl concentrations were similar and slightly lower than the a priori predictions, and elimination and distribution clearances appeared slower during than before or after the surgery. Transdermal patches provided sustained fentanyl absorption for up to 5 days, but the absorption rate was slower than the nominal dose rate and showed a high interindividual variability.
Cellular LocationsMembrane
Metabolite PathwaysFentanyl Action Pathway
Verwendung und Herstellung
Uses
Fentanyl (DEA Code Number: 9801) is a Schedule II controlled substance.
Schedule II Controlled Substance: (A) The drug or other substance has a high potential for abuse; (B) The drug or other substance has a currently accepted medical use in treatment in the United States or a currently accepted medical use with severe restrictions; and (C) Abuse of the drug or other substances may lead to severe psychological or physical dependence.
Analgesics, Opioid; Adjuvants, Anesthesia; Narcotics; Anesthetics, Intravenous
MEDICATION (VET)
MEDICATION
Use (kg; approx.) in Germany (2009): >100
Methods of Manufacturing
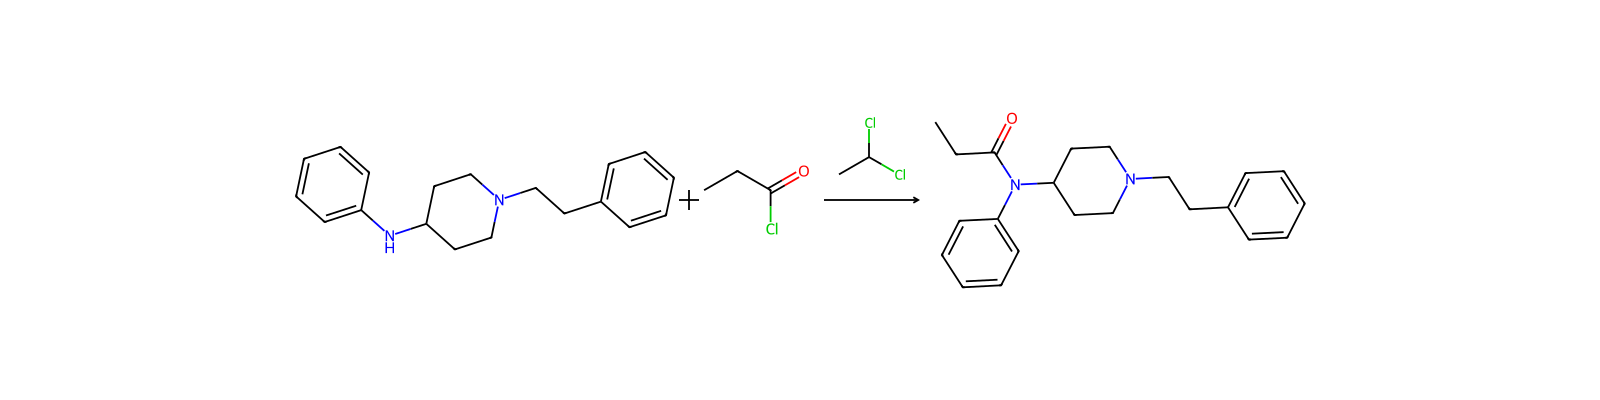
One method consists of condensing propionyl chloride with N-(4-piperidyl)aniline, then treating the resulting N-(4-piperidyl)propionanilide with phenethyl chloride, aiding each condensation by the presence of a suitable dehydrochlorinating agent. Reaction of the base with an equimolar portion of citric acid yields the (1:1) citrate. /Fentanyl citrate/
Preparation: P.A.J. Janssen, France patent 1344366; idem, United States of America patent 3164600 (1963, 1965 both to Janssen)
Formulations/Preparations
Table: Fentanyl Preparations [Table#4533]
Table: Fentanyl Citrate Preparations [Table#4534]
There have been two new alerts issued related to synthetic opioids. The Gulf Coast High Intensity Drug Trafficking Area has issued an alert for a substance with the street name "Grey Death." The substance appears similar to concrete mixing powder and varies in texture, which ranges from a chunky rock-like material to a fine powder. It is not a single drug, but typically contains several potent opioids, including whatever a drug dealer has on hand in varying proportions. It has a potency much higher than heroin and is reportedly administered via injection, ingestion, insufflation, and smoking. The analysis of each grey death sample collected in the gulf coast region so far revealed the presence of three opioids: U-47700, heroin, and fentanyl; though the amount of each drug within grey death varied from sample to sample.
Topical: Transdermal System, iontophoretic: 40 ug (of fentanyl) per activation (9.7 mg/system), Ionsys (C-II; in sealed tray with 1 controller and 1 drug unit) (Medicines Company).
Common street names include: Apache, China Girl, China Town, Dance Fever, Friend, Goodfellas, Great Bear, He-Man, Jackpot, King Ivory, Murder 8, and Tango & Cash.
Use Classification
Animal Drugs -> FDA Approved Animal Drug Products (Green Book) -> Active Ingredients
Pharmaceuticals -> Nervous System -> Anaesthetics -> Opioids
Pharmaceuticals
General Manufacturing Information
Fentanyl is a synthetic opioid related to the phenylpiperidines.
Fentanyl was introduced into the United States in 1968 as an intravenous synthetic anesthetic/analgesic under the trade name Sublimaze or Innovar (fentanyl and droperidol).
Fentanyl has been used illegally as a CNS stimulant in racehorses. The iv admin of fentanyl (total dose of 1, 5, or 10 mg) in thoroughbreds increases spontaneous locomotion 15-fold within a few minutes; this effect can last up to one hour. Limb movements are well controlled & coordinated; the horse rarely stumbles or bumps into objects.
Legal derivatives of fentanyl: 1) Sufentanyl ... 2) Alfentanyl ... 3) Lofentanyl ... 4) Carfentanyl ... .
For more General Manufacturing Information (Complete) data for Fentanyl (7 total), please visit the HSDB record page.
Anwendungen
VerwendenFentanyl is available in a variety of preparations for parenteral, transdermal and transmucosal (including buccal) administration. Because of high firstpass metabolism (~70%) it is not given orally. It is approximately 80–100 times more potent than morphine in the acute seing, although it is approximately 30–40 times as potent when given chronically (e.g. slowrelease transdermal patches). With transdermal administration, the patch and underlying dermis act as a reservoir, and plasma concentration does not reach steady state until approximately 15h after initial application. Plasma concentration also declines slowly after removal (t1/2 ~15–20 h). Fentanyl is very lipophilic, with a relatively short duration of action. There are several new buccal/transmucosal preparations developed for rapid-onset breakthrough pain. These aim to have a very rapid onset in approximately 10min, although this may not be the case in clinical practice. Fentanyl has a large VD with rapid peripheral tissue uptake, limiting initial hepatic metabolism. This may result in significant variability in plasma concentrations and secondary plasma peaks. It binds to αl-acid glycoprotein and albumin; 40% of the protein-bound fraction is taken up by erythrocytes. The lungs may be important in exerting a first-pass effect on fentanyl (up to 75% of the dose), thus buffering the plasma from high peak drug concentrations.
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Ergänzende Hinweise
DefinitionChEBI: The carboxamide resulting from the formal condensation of the aryl amino group of N-phenyl-1-(2-phenylethyl)piperidin-4-amine with propanoic acid.
Zugehörige Reaktionen
9




Verknüpfte Notizen
Wird geladen…