
Grundinformationen
- Standard-SMILES
Cn1nnc2c(C(N)=O)ncn2c1=O- InChIKey
BPEGJWRSRHCHSN-UHFFFAOYSA-N- Summenformel
- C6H6N6O2
- Durchschnittliche Molmasse
- 194,15 g/mol
- Monoisotopische Masse
- 194,05522343
Überblick
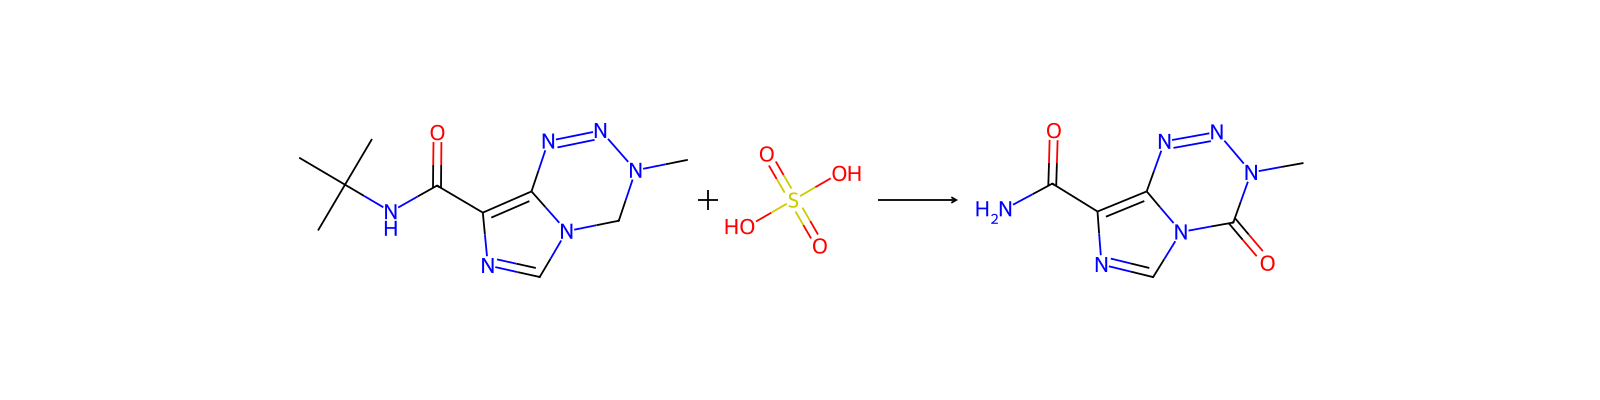
Temozolomide is an imidazotetrazine that is 3,4-dihydroimidazo[5,1-d][1,2,3,5]tetrazine which is substituted at positions 3, 4, and 8 by methyl, oxo, and carboxamide groups, respectively. A prodrug for MTIC (5-(3-methyltriaz-1-en-1-yl)-1H-imidazole-4-carboxamide, formed by spontaneous hydrolysis of temozolomide in the body), it is used as an oral alkylating agent for the treatment of newly diagnosed malignant glioblastoma multiforme (concomitantly with radiotherapy) and malignant melanoma. It has a role as an alkylating agent, an antineoplastic agent and a prodrug. It is a monocarboxylic acid amide, an imidazotetrazine and a triazene derivative.
Namen und Bezeichner
- Bevorzugter Name
- Temozolomide
- IUPAC
- 3-methyl-4-oxoimidazo[5,1-d][1,2,3,5]tetrazine-8-carboxamide
- Englischer Name
- Temozolomide
- Summenformel
- C6H6N6O2
- Molmasse
- 194.15
Namen und Synonyme
temozolomide85622-93-1MethazolastoneTemodarTemodal3-methyl-4-oxo-3,4-dihydroimidazo[5,1-d][1,2,3,5]tetrazine-8-carboxamideTemozolamideCCRG-81045Sch 52365TemozolomidumNSC 362856Sch-52365
Weitere Namen anzeigen
TMZTeMozoloMidTZMTeMozoMide
NSC-362856temozolomidaM&B 39831M&B-39831CCRIS 8996MB 398313,4-dihydro-3-methyl-4-oxoimidazo[5,1-d]-1,2,3,5-tetrazine-8-carboxamideM & B 39831
Datenbank-Bezeichner
- CAS
85622-93-1- PubChem CID
- 5394
- DTXSID
DTXSID5043714- ChEMBL
CHEMBL810- ChEBI
CHEBI:72564- UNII
- YF1K15M17Y
- EC Number
- 630-358-9
- Nikkaji
- J171.234I
Eigenschaften
Berechnete Struktureigenschaften
- XLogP
- -1,1
- Polarare Oberfläche (TPSA)
- 106 Ų
- H-Brücken-Donoren
- 1
- H-Brücken-Akzeptoren
- 5
- Frei drehbare Bindungen
- 1
- Schwere Atome
- 14
- Formalladung
- 0
- Komplexität
- 315
Experimentelle und physikochemische Eigenschaften
Drugs
Pharmaceuticals
Pharmaceuticals -> Listed in ZINC15
SpringerMaterials Properties15N nuclear magnetic resonance spectrum
LogP
-2.8
-1.08
Solubility5.09e+00 g/L
Human Drugs
Breast Feeding; Lactation; Antineoplastic Agents; Antineoplastic Agents, Alkylating
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
Melting Point212 °C
Physical DescriptionSolid
Physikochemische Eigenschaften
- Schmelzpunkt
- 212 °C · 212°C dec.
- Siedepunkt
- 526.6 · 526.6±42.0 °C(Predicted)
- Dichte
- 1.97 · 1.97±0.1 g/cm3(Predicted)
- storage temp.
- 2 · 2-8°C
- Löslichkeit
- 10 mg/mL, · DMSO: soluble10mg/mL, clear
- pka
- 14.77 · 14.77±0.20(Predicted)
- Aggregatzustand
- powder
- Farbe
- white to light brown
- Merck
- 14 · 14,9139
- Stabilität
- 2 years · Stable for 2 years as supplied. Solutions in DMSO may be stored at -20° for up to 3 months.
- Major Application
- forensics and toxicologypharmaceutical (small molecule)veterinary
- InChI
- InChI=1S/C6H6N6O2/c1-11-6(14)12-2-8-3(4(7)13)5(12)9-10-11/h2H,1H3,(H2,7,13)
- InChIKey
- BPEGJWRSRHCHSN-UHFFFAOYSA-N
- SMILES
- N1(C)C(=O)N2C=NC(C(N)=O)=C2N=N1
- CAS Datenbank
- 85622 · 85622-93-1(CAS DataBase Reference)
Sicherheit und Regulatorisches
GHS-Klassifizierung
GHS Classification
Danger
H204 (17.3%): Fire or projection hazard [Warning Explosives]
P203, P210, P230, P234, P236, P240, P250, P260, P261, P264, P264+P265, P270, P271, P280, P301+P316, P301+P317, P302+P352, P304+P340, P305+P351+P338, P318, P319, P321, P330, P332+P317, P337+P317, P362+P364, P370+P380+P375, P401, P403+P233, P405, P501, and P503 (click each P-code to see the statement)
Aggregated GHS information provided per 162 reports by companies from 19 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
Gefahrenhinweise
Hazard Classes and CategoriesExpl. 1.4 (17.3%)
Toxikologische Informationen
Hepatotoxicity
Serum aminotransferase elevations occur during temozolomide therapy in up to 12% of patients, but these elevations are usually mild and self-limited, not requiring dose adjustment or drug discontinuation. An instance of serum aminotransferase elevation with jaundice was reported in the registration trials of temozolomide and subsequent to its approval. More strikingly, multiple single case reports and several case series of temozolomide hepatotoxicity have been reported in the literature. The onset of injury was typically within 2 to 8 weeks of starting temozolomide but several patients had received multiple courses before the onset of liver injury. The pattern of serum enzyme elevations was usually mixed initially, but the disease tended to be cholestatic. In several instances, jaundice was deep and prolonged. Features of hypersensitivity (rash, fever, eosinophilia) and autoantibody formation were not present. Liver histology demonstrated cholestasis and bile duct injury and a striking decrease in bile ducts (bile duct loss or paucity). Jaundice and pruritus tended to be prolonged and some patients developed vanishing bile duct syndrome, while others recovered clinically but had persistent serum alkaline phosphatase elevations during follow up and to the time of death from the brain tumor. Rechallenge was not done, but several patients subsequently received other antineoplastic agents, some of which were alkylating agents without recurrence of liver injury.
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Temozolomide
vLess-DILI-concern
4
Adverse reactions
DOI:10.1016/j.drudis.2016.02.015
Effects During Pregnancy and Lactation◉ Summary of Use during Lactation
Sicherheitsdaten
- wgk
- 3
- hs_code
- 29339900
- RTECS-Nr.
- NJ5927050
- risk_code
- 45-46-60-61-22-36/37/38
- hazard_code
- T,Xi
- safety_code
- 24/25-45-36/37-26-53-36
- Speicherklasse
- 6.1C - Combustible acute toxic Cat.3toxic compounds or compounds which causing chronic effects
- Hazard Classifications
- Acute Tox. 4 OralCarc. 1BEye Irrit. 2Muta. 1BRepr. 1BSkin Irrit. 2STOT SE 3
Chemie und Industrie
Pharmakologische Informationen
ATC Code
L01AX03
L - Antineoplastic and immunomodulating agents
QL - Antineoplastic and immunomodulating agents
Protein Binding
Temozolomide plasma protein binding varies from 8-36%, with an average of around 15%. _In vitro_ binding experiments revealed approximate dissociation constants of 0.2-0.25 and 0.12 mM for temozolomide with human serum albumin (HSA) and alpha-1-acid glycoprotein (AGP), respectively; despite the slightly higher affinity for AGP, it is likely that temozolomide is predominantly bound to HSA due to its higher serum concentration. In addition, temozolomide binding to HSA results in delayed hydrolysis and a longer half-life than in buffer (1 versus 1.8 hours).
Pharmacodynamics
Temozolomide is a prodrug of the imidazotetrazine class that requires nonenzymatic hydrolysis at physiological pH _in vivo_ to perform alkylation of adenine/guanine residues, leading to DNA damage through futile repair cycles and eventual cell death. Temozolomide treatment is associated with myelosuppression, which is likely to be more severe in females and geriatric patients. Patients must have an ANC of ≥1.5 x 10<sup>9</sup>/L and a platelet count of ≥100 x 10<sup>9</sup>/L before starting therapy and must be monitored weekly during the concomitant radiotherapy phase, on days one and 22 of maintenance cycles, and weekly at any point where the ANC/platelet count falls below the specified values until recovery. Cases of myelodysplastic syndrome and secondary malignancies, including myeloid leukemia, have been observed following temozolomide administration. Pneumocystis pneumonia may occur in patients undergoing treatment, and prophylaxis should be provided for patients in the concomitant phase of therapy with monitoring at all stages. Severe hepatotoxicity has also been reported, and liver testing should be performed at baseline, midway through the first cycle, before each subsequent cycle, and approximately two to four weeks after the last dose. Animal studies suggest that temozolomide has significant embryo-fetal toxicity; male and female patients should practice contraception up to three and six months following the last dose of temozolomide, respectively.
Mechanism of Action
Glioblastoma (glioblastoma multiforme) is the most common and aggressive adult primary brain tumour, accounting for 45.6% of all primary malignant brain tumours. Primarily defined histopathologically by necrosis and microvascular proliferation (WHO grade IV classification), glioblastomas are commonly treated through radiotherapy and concomitant alkylation-based chemotherapy with temozolomide. Temozolomide (TMZ) is a small (194 Da) lipophilic alkylating agent of the imidazotetrazine class that is stable at acidic pH, allowing for both oral and intravenous dosing, and can cross the blood-brain barrier to affect CNS tumours. After absorption, TMZ undergoes spontaneous nonenzymatic breakdown at physiological pH to form 5-(3-methyltriazen-1-yl) imidazole-4-carboxamide (MTIC), which then reacts with water to produce 5-aminoimidazole-4-carboxamide (AIC) and a highly reactive methyl diazonium cation. Brain tumours such as glioblastoma typically possess a more alkaline pH than healthy tissue, favouring TMZ activation within tumour tissue. The methyl diazonium cation is highly reactive and methylates DNA at the N7 position of guanine (N7-MeG, 70%), the N3 position of adenine (N3-MeA, 9%), and the O6 position of guanine (O6-MeG, 6%). Although more prevalent, N7-MeG and N3-MeA are rapidly repaired by the base excision repair pathway and are not primary mediators of temozolomide toxicity, although N3-MeA lesions are lethal if not repaired. By comparison, repair of O6-MeG requires action by the suicide enzyme methylguanine-DNA methyltransferase (MGMT), which removes the methyl group to restore guanine. If not repaired by MGMT, O6-MeG mispairs with thymine, activating the DNA mismatch repair (MMR) pathway that removes the thymine (not the O6-MeG), resulting in futile cycles of repair and eventual DNA strand breaks leading to apoptosis. As MMR activity is crucial for temozolomide cytotoxicity, cells that have reduced or absent MGMT function and an intact MMR pathway are the most sensitive to temozolomide treatment. Glioblastomas that upregulate MGMT downregulate MMR or alter both are resistant to TMZ, leading to treatment failure. More recently, increased interest has also been shown in the immunomodulatory effects of TMZ, related to its myelosuppressive effects. Counterintuitively, lymphodepletion may enhance the antitumour effects of cellular immunotherapy and improve the dynamics of memory cells by altering tumour-specific versus tumour-tolerant populations. The depletion of tumour-localized immunosuppressive T<sub>reg</sub> cells may contribute to an improved response to immunotherapy. Hence, TMZ treatment may also form the backbone of immunotherapy strategies against glioblastoma in the future.
Biological Half-LifeTemozolomide has a mean elimination half-life of 1.8 hours.
Metabolism/Metabolites
After absorption, temozolomide undergoes nonenzymatic chemical conversion to the active metabolite 5-(3-methyltriazen-1-yl) imidazole-4-carboxamide (MTIC) plus carbon dioxide and to a temozolomide acid metabolite, which occurs at physiological pH but is enhanced with increasing alkalinity. MTIC subsequently reacts with water to produce 5-aminoimidazole-4-carboxamide (AIC) and a highly reactive methyl diazonium cation, the active alkylating species. The cytochrome P450 system plays only a minor role in temozolomide metabolism. Relative to the AUC of temozolomide, the exposure to MTIC and AIC is 2.4% and 23%, respectively.
FDA Pharmacological Classification
YF1K15M17Y
TEMOZOLOMIDE
Mechanisms of Action [MoA] - Alkylating Activity
Established Pharmacologic Class [EPC] - Alkylating Drug
Temozolomide is an Alkylating Drug. The mechanism of action of temozolomide is as an Alkylating Activity.
TEMOZOLOMIDE
MeSH Pharmacological Classification
A class of drugs that differs from other alkylating agents used clinically in that they are monofunctional and thus unable to cross-link cellular macromolecules. Among their common properties are a requirement for metabolic activation to intermediates with antitumor efficacy and the presence in their chemical structures of N-methyl groups, that after metabolism, can covalently modify cellular DNA. The precise mechanisms by which each of these drugs acts to kill tumor cells are not completely understood. (From AMA, Drug Evaluations Annual, 1994, p2026)
Absorption, Distribution and Excretion
Temozolomide is rapidly and completely absorbed in the gastrointestinal tract and is stable at both acidic and neutral pH. Therefore, temozolomide may be administered both orally and intravenously with a median Tmax of one hour. Following a single oral dose of 150 mg/m2, temozolomide and its active MTIC metabolite had Cmax values of 7.5 μg/mL and 282 ng/mL and AUC values of 23.4 μg\*hr/mL and 864 ng\*hr/mL, respectively. Similarly, following a single 90-minute IV infusion of 150 mg/m2, temozolide and its active MTIC metabolite had Cmax values of 7.3 μg/mL and 276 ng/mL and AUC values of 24.6 μg\*hr/mL and 891 ng\*hr/mL, respectively. Temozolomide kinetics are linear over the range of 75-250 mg/m2/day. The median Tmax is 1 hour Oral temozolomide absorption is affected by food. Administration following a high-fat breakfast of 587 calories caused the mean Cmax and AUC to decrease by 32% and 9%, respectively, and the median Tmax to increase by 2-fold (from 1-2.25 hours).
Roughly 38% of administered temozolomide can be recovered over seven days, with 38% in the urine and only 0.8% in the feces. The recovered material comprises mainly metabolites: unidentified polar metabolites (17%), AIC (12%), and the temozolomide acid metabolite (2.3%). Only 6% of the recovered dose represents unchanged temozolomide.
Temozolomide has a mean apparent volume of distribution (%CV) of 0.4 (13%) L/kg.
Temozolomide has a clearance of approximately 5.5 L/hr/m<sup>2</sup>.
Cellular LocationsCytoplasm
Verwendung und Herstellung
UsesUse (kg; approx.) in Germany (2009): >75
Anwendungen
BeschreibungTemozolomide was launched for the first time in the UK for the treatment of patients with glioblastoma multiforme showing recurrence or progression after standard therapy. It can be considered as a cyclic variant of highly reactive triazenes producing a cascade of ionic or radical antitumoral species. Temozolamide is a 3-methyl analog of mitozolomide and was shown to be converted to cytotoxic triazene MCTIC. It can be prepared in 2 steps from 5- aminoimidazole-4-carboxamide by diazotization then cyclization with methylisocyanate. Mechanistically, the depletion of O6-alkylguanine-DNA alkyltransferase (OGAT) in cells or tumors was shown to be correlated with the cytotoxicity of temozolomide which is a potent inhibitor of this enzyme involved in DNA repair activity. Further approval applications for the treatment of other malignant gliomas such as relapsed anaplastic astrocytoma, advanced metastatic melanoma were submitted.
VerwendenTemozolomide is an antineoplastic drug and an Imidazotetrazine alkylating agent. It induces apoptosis and causes cell cycle arrest at the G2/M checkpoint. It rapidly degrades in the body, producing the active metabolite MTIC, which exerts an anti-tumor effect. Moreover, temozolomide has shown effectiveness against paclitaxel-resistant tumors and has been utilized in the study of drug resistance mechanisms in glioblastoma cell lines.
Darstellung
synthetischeThe synthesis of temozolomide involves several steps. First, 5-Amino-4-imidazolecarboxamide is diazotized using nitrite. Then, the diazotized compound is reacted with methyl isocyanate in dichloromethane. This reaction leads to the cyclization of the compound, ultimately resulting in the formation of temozolomide.
Vor- und nachgelagerte Produkte
Vorgelagerte Rohstoffe
Nachgelagerte Produkte
Anbieter50 Anbieter
国药集团化学试剂有限公司86-21-63210123 · [email protected]
北京华美互利生物化工010-56205725 · [email protected]
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
衢州润东化工有限公司0570-8789886 18892685668 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
山东雨禾医药科技有限公司15263077727
INTATRADE GmbH+49 3493/605464 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
上海迈瑞尔生化科技有限公司4006356688 18621169109 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
广州市亿邦医药科技有限公司+86 (20) 28996708,29078958,28139708,29076128,28133708,28139728,28139738,28133718,021-31663278,021-31663578,021-60538387
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
北京迈索化学技术有限公司010-57862036 18811083386 · [email protected]
上海相辉医药科技有限公司13761987713 · [email protected]
嘉兴市艾森化工有限公司0573-85285100 18627885956 · [email protected]
Pure Chemistry Scientific Inc.001-857-928-2050 or 1-888-588-9418 · [email protected]
上海泰坦科技股份有限公司400-6009262 15618770481 · [email protected]
VDM Biochemicals0330-2528181 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
合肥天健化工有限公司551-65418679 15856988503;15837135945 · [email protected]
武汉丰泰威远科技有限公司027-87465837 19945049750 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
济南精合医药科技有限公司0531-88811783 · [email protected]
云南西力生物技术股份有限公司0871-65217109 · [email protected]
上海汉景化工有限公司021-54285032 13641685631 · [email protected]
天津希恩思生化科技有限公司400 638 7771 · [email protected]
湖南汇百侍生物科技有限公司0731-85526065 13308475853 · [email protected]
上海复和化学科技有限公司0086-21-67651709 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
Wuhan NCE Biomedical Co.,Ltd.4000-027-021 |24 +86-13986109188 | +86-15623472865 | +81-08033611988
上海遐瑞医药科技有限公司+86 21 61551611
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
上海诺宝化工有限公司+86(0)21 60484900
Shanghai Witofly Chemical Co.,Ltd[email protected]
Hubei Datong Bio-Chemical Technology Co.,Ltd027-87666700 · [email protected]
广州爱纯医药科技有限公司020-39119399 18927568969 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
山东博洛达生物科技有限公司0531-68659041 · [email protected]
Cato Research Chemicals Inc.020-81960175 · [email protected]
上海喀露蓝科技有限公司18149758185 18149758185 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
上海将来实业股份有限公司400-0066400 13621662912 · [email protected]
HBCChem, Inc.+1-510-219-6317 · [email protected]
上海笛柏生物科技有限公司400-008-9730,021-54359730 400-008-9730 · [email protected]
雷丁试剂0510-85629785 18013409632 · [email protected]
Ergänzende Hinweise
DefinitionChEBI: An imidazotetrazine that is 3,4-dihydroimidazo[5,1-d][1,2,3,5]tetrazine which is substituted at positions 3, 4, and 8 by methyl, oxo, and carboxamide groups, respectively. A prodrug for MTIC (5-(3-methyltriaz-1-en-1-yl)-1H-i idazole-4-carboxamide, formed by spontaneous hydrolysis of temozolomide in the body), it is used as an oral alkylating agent for the treatment of newly diagnosed malignant glioblastoma multiforme (concomitantly with radiotherapy) and malignant melanoma.
Zugehörige Reaktionen
14


Verknüpfte Notizen
Wird geladen…