
HRID 659751生成物として
Irbesartan
データを補完しています。しばらくしてからページを更新すると最新の内容を表示できます

138402-11-6CCCCC1=NC2(CCCC2)C(=O)N1Cc1ccc(-c2ccccc2-c2nn[nH]n2)cc1YOSHYTLCDANDAN-UHFFFAOYSA-NIrbesartan is a biphenylyltetrazole that is an angiotensin II receptor antagonist used mainly for the treatment of hypertension. It has a role as an antihypertensive agent, a xenobiotic, an angiotensin receptor antagonist and an environmental contaminant. It is an azaspiro compound and a biphenylyltetrazole.
Pharmaceuticals -> Listed in ZINC15
Pharmaceuticals -> Antihypertensives
Pharmaceuticals -> Used in Switzerland
Pharmaceuticals
6
2.71
<1mg/mL
Practically insoluble in water
Slightly soluble in alcohol, methylene chloride
8.84e-03 g/L
Breast Feeding; Lactation; Milk, Human; Antihypertensive Agents; Angiotensin II Type 1 Receptor Blockers; Angiotensin Receptor Blockers
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
180-181 °C
180-181 °C
180 - 181 °C
安全情報は参考情報です。供給元の安全データシート(SDS)、適用法令、専門家による評価に代わるものではありません。
This chemical does not meet GHS hazard criteria for 1% (1 of 104) of reports.
Danger
H315 (57.7%): Causes skin irritation [Warning Skin corrosion/irritation]
P203, P260, P261, P263, P264, P264+P265, P270, P271, P273, P280, P302+P352, P304+P340, P305+P351+P338, P318, P319, P321, P332+P317, P337+P317, P362+P364, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 104 reports by companies from 19 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including irbesartan, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide.
Advice for firefighters: Wear self contained breathing apparatus for fire fighting if necessary.
Store at 25 °C (77 °F); excursions permitted to 15-30 °C (59-86 °F).
Conditions for safe storage, including any incompatibilities: Keep container tightly closed in a dry and well-ventilated place. Recommended storage temperature: 2 - 8 °C.
C09CA04
C - Cardiovascular system
QC - Cardiovascular system
Irbesartan is an angiotensin receptor blocker used to treat hypertension and diabetic nephropathy. It has a long duration of action as it is usually taken once daily and a wide therapeutic index as doses may be as low as 150mg daily but doses of 900mg/day were well tolerated in healthy human subjects.
Irbesartan prevents angiotensin II binding to the AT<sub>1</sub> receptor in tissues like vascular smooth muscle and the adrenal gland. Irbesartan and its active metabolite bind the AT<sub>1</sub> receptor with 8500 times more affinity than they bind to the AT<sub>2</sub> receptor. Irbesartan's prevention of angiotensin II binding causes vascular smooth muscle relaxation and prevents the secretion of aldosterone, lowering blood pressure. Angiotensin II would otherwise bind to the AT<sub>1</sub> receptor, inducing vasoconstriction and aldosterone secretion, raising blood pressure.
Angiotensin II is a potent vasoconstrictor formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II). Angiotensin II is the principal pressor agent of the renin-angiotensin system (RAS) and also stimulates aldosterone synthesis and secretion by adrenal cortex, cardiac contraction, renal resorption of sodium, activity of the sympathetic nervous system, and smooth muscle cell growth. Irbesartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively binding to the AT1 angiotensin II receptor. There is also an AT2 receptor in many tissues, but it is not involved in cardiovascular homeostasis. Irbesartan is a specific competitive antagonist of AT1 receptors with a much greater affinity (more than 8500-fold) for the AT1 receptor than for the AT2 receptor and no agonist activity. Blockade of the AT1 receptor removes the negative feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and circulating angiotensin II do not overcome the effects of irbesartan on blood pressure. Irbesartan does not inhibit ACE or renin or affect other hormone receptors or ion channels known to be involved in the cardiovascular regulation of blood pressure and sodium homeostasis. Because irbesartan does not inhibit ACE, it does not affect the response to bradykinin; whether this has clinical relevance is not known.




138402-11-6DTXSID0023169CHEMBL1513CHEBI:5959186.9 Ų [M+H-H2O]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
200.8 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
201.2 Ų [M+H]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
202.81 Ų [M+H]+
化学的特性Crystalline Solid
Accidental Release Measures. Personal precautions, protective equipment and emergency procedures: Use personal protective equipment. Avoid dust formation. Avoid breathing vapours, mist or gas. Avoid breathing dust. Environmental precautions: Do not let product enter drains. Methods and materials for containment and cleaning up: Pick up and arrange disposal without creating dust. Sweep up and shovel. Keep in suitable, closed containers for disposal.
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
SRP: At the time of review, regulatory criteria for small quantity disposal are subject to significant revision, however, household quantities of waste pharmaceuticals may be managed as follows: Mix with wet cat litter or coffee grounds, double bag in plastic, discard in trash.
Waste treatment methods. Product: Offer surplus and non-recyclable solutions to a licensed disposal company. Contaminated packaging: Dispose of as unused product.
Precautions for safe handling: Avoid formation of dust and aerosols. Provide appropriate exhaust ventilation at places where dust is formed.
Appropriate engineering controls: Handle in accordance with good industrial hygiene and safety practice. Wash hands before breaks and at the end of workday.
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands.
SRP: Local exhaust ventilation should be applied wherever there is an incidence of point source emissions or dispersion of regulated contaminants in the work area. Ventilation control of the contaminant as close to its point of generation is both the most economical and safest method to minimize personnel exposure to airborne contaminants. Ensure that the local ventilation moves the contaminant away from the worker.
Eye/face protection: Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU).
Skin protection: Handle with gloves.
Body Protection: Choose body protection in relation to its type, to the concentration and amount of dangerous substances, and to the specific work-place. The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace.
Respiratory protection: Respiratory protection is not required. Where protection from nuisance levels of dusts are desired, use type N95 (US) or type P1 (EN 143) dust masks. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU).
Do not coadminister aliskiren with Avapro in patients with diabetes. Avoid use of aliskiren with AVAPRO in patients with renal impairment (GFR <60 mL/min).
Dual blockade of the renin-angiotensin system (RAS) with angiotensin-receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Closely monitor blood pressure, renal function, and electrolytes in patients on Avapro and other agents that affect the RAS.
Concomitant use of potassium-sparing diuretics, potassium supplements, or salt substitutes containing potassium may lead to increases in serum potassium.
Possible decreased irbesartan metabolism when irbesartan is used concomitantly with tolbutamide.
For more Interactions (Complete) data for Irbesartan (6 total), please visit the HSDB record page.
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 1.3X10+6(SRC), determined from a structure estimation method(2), indicates that irbesartan is expected to be immobile in soil(SRC). The estimated pKa values of irbesartan are 4.08 and 4.29(3), indicating that this compound will exist partially in the cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Volatilization of ibesartan from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 7.0X10⁻¹⁵ atm-cu m/mole(SRC), using a fragment constant estimation method(5). Irbesartan is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 1.2X10⁻¹⁵ mm Hg at 25 °C(SRC), determined from a fragment constant method(2). Biodegradation data in soil were not available(SRC, 2014).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 1.3X10+6(SRC), determined from a structure estimation method(2), indicates that irbesartan is expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(3) based upon an estimated Henry's Law constant of 5.0X10⁻¹⁵ atm-cu m/mole(SRC), developed using a fragment constant estimation method(4). According to a classification scheme(5), an estimated BCF of 1500(SRC), from its estimated log Kow(2)and a regression-derived equation(2), suggests the potential for bioconcentration in aquatic organisms is very high, provided the compound is not metabolized by the organism(SRC). Biodegradation data in water were not available(SRC, 2014).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), irbesartan, which has an estimated vapor pressure of 1.2X10⁻¹⁵ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist solely in the particulate phase in the ambient atmosphere. Particulate-phase irbesartan may be removed from the air by wet and dry deposition(SRC). Irbesartan contains chromophores that absorb at wavelengths >290 nm(3) and, therefore, may be susceptible to direct photolysis by sunlight(SRC).
IDENTIFICATION AND USE: Irbesartan crystals are formulated into oral tablets. Irbesartan is an angiotensin II type 1 (AT1) receptor antagonist. It is used alone or in combination with other classes of antihypertensive drugs in the management of hypertension. It is also used for the treatment of diabetic nephropathy in patients with type 2 diabetes and hypertension. HUMAN EXPOSURE AND TOXICITY: The most likely manifestations of irbesartan overdose include hypotension and tachycardia; bradycardia might also occur from overdose. The use of irbesartan in pregnancy is contraindicated. While use during the first trimester does not suggest a risk of major anomalies, use during the second and third trimester may cause teratogenicity and severe fetal and neonatal toxicity. Fetal toxic effects may include anuria, oligohydramnios, fetal hypocalvaria, intrauterine growth restriction, premature birth, and patent ductus arteriosus. Anuria-associated oligohydramnios may produce fetal limb contractures, craniofacial deformation, and pulmonary hypoplasia. Severe anuria and hypotension that are resistant to both pressor agents and volume expansion may occur in the newborn following in utero exposure to irbesartan. ANIMAL STUDIES: No evidence of carcinogenicity was observed when irbesartan was administered in rats or mice for up to 2 years. Also, the fertility or mating of male and female rats was unaffected by administration of irbesartan. When pregnant rats were treated with the drug from day 0 to day 20 of gestation, increased incidences of renal pelvic cavitation, hydroureter and/or absence of renal papilla were observed in fetuses at doses as low as 50 mg/kg/day. Subcutaneous edema was observed in fetuses at doses as low as 180 mg/kg/day. As these anomalies were not observed in rats in which drug exposure was limited to gestation days 6 to 15, they appear to reflect late gestational effects of the drug. In pregnant rabbits, oral doses of 30 mg irbesartan/kg/day were associated with maternal mortality and abortion. Surviving females receiving this dose had a slight increase in early resorptions and a corresponding decrease in live fetuses. Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian-cell forward gene-mutation assay). Irbesartan was also negative in several tests for induction of chromosomal aberrations (in vitro-human lymphocyte assay; in vivo-mouse micronucleus study).
Using a structure estimation method based on molecular connectivity indices(1), the Koc of irbesartan can be estimated to be 1.3X10+6(SRC). According to a classification scheme(2), this estimated Koc value suggests that irbesartan is expected to be immobile in soil. The estimated pKa values of 4.08 and 4.29(3) indicate that this compound will exist almost entirely in the cation form in the environment and cations generally adsorb more strongly to soils containing organic carbon and clay than their neutral counterparts(4). Irbesartan adsorption isotherms (Kd) of 7.0X10+2 L/kg and 9.4X10+2 L/kg were measured in primary sludge and long-age secondary sludge, respectively. Sludge was obtained from 2 wastewater treatment plants that were representative of plants utilized in industrialized countries(5).
/SIGNS AND SYMPTOMS/ No data are available in regard to overdosage in humans. However, daily doses of 900 mg for 8 weeks were well-tolerated. The most likely manifestations of overdosage are expected to be hypotension and tachycardia; bradycardia might also occur from overdose.
/GENOTOXICITY/ IIrbesartan was negative in ... /the/ in vitro-human lymphocyte assay ... .
/OTHER TOXICITY INFORMATION/ Drugs that act directly on the renin-angiotensin system (e.g., angiotensin-converting enzyme (ACE) inhibitors, angiotensin II receptor antagonists) can cause fetal and neonatal morbidity and mortality when used in pregnancy during the second and third trimesters. ACE inhibitors also may increase the risk of major congenital malformations when administered during the first trimester of pregnancy. Irbesartan should be discontinued as soon as possible when pregnancy is detected, unless continued use is considered life-saving. Nearly all women can be transferred successfully to alternative therapy for the remainder of their pregnancy.
/OTHER TOXICITY INFORMATION/ The human pregnancy experience with irbesartan is limited. However, the antihypertensive mechanisms of action of irbesartan and angiotensin-converting enzyme (ACE) inhibitors are very close. That is, the former selectively blocks the binding of angiotensin II to AT1 receptors, whereas the latter prevents the formation of angiotensin II itself. Therefore, use of this drug during the 2nd and 3rd trimesters may cause teratogenicity and severe fetal and neonatal toxicity identical to that seen with ACE inhibitors. Fetal toxic effects may include anuria, oligohydramnios, fetal hypocalvaria, intrauterine growth restriction, premature birth, and patent ductus arteriosus. Anuria-associated oligohydramnios may produce fetal limb contractures, craniofacial deformation, and pulmonary hypoplasia. Severe anuria and hypotension that are resistant to both pressor agents and volume expansion, may occur in the newborn following in utero exposure to irbesartan. Newborn function and blood pressure should be closely monitored.
/OTHER TOXICITY INFORMATION/ In July 2010, the US Food and Drug Administration (FDA) initiated a safety review of angiotensin II receptor antagonists after a published meta-analysis suggested a possible association between the use of these agents and an increased risk of cancer. The meta-analysis, which combined cancer-related findings from 5 randomized, controlled trials in over 60,000 patients, found a modest but significant increase in the risk of new cancer occurrence in patients receiving an angiotensin II receptor antagonist (mostly telmisartan) compared with those in control groups (7.2 versus 6%, respectively; risk ratio 1.08). However, because of several limitations of the study (e.g., trials included in the meta-analysis were not specifically designed to evaluate cancer outcomes, lack of individual patient data), the validity of these findings has been questioned. Subsequent studies, including a larger, more comprehensive meta-analysis conducted by FDA, have not shown an increased risk of cancer in patients receiving angiotensin II receptor antagonists. FDA's meta-analysis, which included trial-level data from 31 randomized studies (total of approximately 156,000 patients), found no evidence of an increased risk of cancer in patients who received an angiotensin II receptor antagonist compared with those who received other treatments (placebo or active control). The overall rate of new cancer occurrence was essentially the same in both groups of patients (1.82 and 1.84 cases per 100 patient-years, respectively). In addition, there was no difference in the risk of cancer-related death, breast cancer, lung cancer, or prostate cancer between the groups. Based on these results and a review of all currently available data related to this potential safety concern, FDA has concluded that use of angiotensin II receptor antagonists is not associated with an increased risk of cancer.
Drug Induced Liver Injury Rank (DILIrank 2.0)
Irbesartan
vLess-DILI-concern
5
Adverse reactions
DOI:10.1016/j.drudis.2016.02.015
An estimated BCF of 1500 was calculated in fish for irbesartan(SRC), using an estimated log Kow of 5.31(1) and a regression-derived equation(1). According to a classification scheme(2), this BCF suggests the potential for bioconcentration in aquatic organisms is very high(SRC), provided the compound is not metabolized by the organism(SRC).
The Henry's Law constant for irbesartan is estimated as 7.0X10⁻¹⁵ atm-cu m/mole(SRC) using a fragment constant estimation method(1). This Henry's Law constant indicates that irbesartan is expected to be essentially nonvolatile from water and moist soil surfaces(2). Irbesartan is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 1.2X10⁻¹⁵ mm Hg(SRC), determined from a fragment constant method(3).
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ No evidence of carcinogenicity was observed when irbesartan was administered at doses of up to 500/1000 mg/kg/day (males/females, respectively) in rats and 1000 mg/kg/day in mice for up to 2 years. For male and female rats, 500 mg/kg/day provided an average systemic exposure to irbesartan (AUC0-24 hour, bound plus unbound) about 3 and 11 times, respectively, the average systemic exposure in humans receiving the maximum recommended dose (MRD) of 300 mg irbesartan/day, whereas 1000 mg/kg/day (administered to females only) provided an average systemic exposure about 21 times that reported for humans at the MRD. For male and female mice, 1000 mg/kg/day provided an exposure to irbesartan about 3 and 5 times, respectively, the human exposure at 300 mg/day.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ When pregnant rats were treated with irbesartan from day 0 to day 20 of gestation (oral doses of 50 mg/kg/day, 180 mg/kg/day, and 650 mg/kg/day), increased incidences of renal pelvic cavitation, hydroureter and/or absence of renal papilla were observed in fetuses at doses =50 mg/kg/day (approximately equivalent to the maximum recommended human dose [MRHD], 300 mg/day, on a body surface area basis). Subcutaneous edema was observed in fetuses at doses =180 mg/kg/day (about 4 times the MRHD on a body surface area basis). As these anomalies were not observed in rats in which irbesartan exposure (oral doses of 50, 150, and 450 mg/kg/day) was limited to gestation days 6 to 15, they appear to reflect late gestational effects of the drug. In pregnant rabbits, oral doses of 30 mg irbesartan/kg/day were associated with maternal mortality and abortion. Surviving females receiving this dose (about 1.5 times the MRHD on a body surface area basis) had a slight increase in early resorptions and a corresponding decrease in live fetuses. Irbesartan was found to cross the placental barrier in rats and rabbits.
/LABORATORY ANIMALS: Developmental or Reproductive Toxicity/ Irbesartan had no adverse effects on fertility or mating of male or female rats at oral doses =650 mg/kg/day, the highest dose providing a systemic exposure to irbesartan (AUC0-24 hour, bound plus unbound) about 5 times that found in humans receiving the maximum recommended dose of 300 mg/day.
/GENOTOXICITY/ Irbesartan was not mutagenic in a battery of in vitro tests (Ames microbial test, rat hepatocyte DNA repair test, V79 mammalian-cell forward gene-mutation assay). Irbesartan was negative in ... the in vivo-mouse micronucleus study.
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including irbesartan, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
The terminal elimination half life of irbesartan is 11-15 hours.
The terminal elimination half-life of irbesartan averaged 11 to 15 hours.
Irbesaran is largely metabolized by glucuronidation and oxidation in the liver. The majority of metabolism occurs through the action of CYP2C9 with a negligible contribution from CYP3A4. Some hydroxylation also occurs in irbesartan metabolism. Irbesartan can be glucuronidated by UGT1A3 to the M8 metabolite, oxidized to the M3 metabolite, or hydroxylated by CYP2C9 to one of the M4, M5, or M7 metabolites. The M4, M5, and M7 metabolites are all hydroxylated to become the M1 metabolite, which is then oxidized to the M2 metabolite. The M4 metabolite can also be oxidized to the M6 metabolite before hydroxylation to the M2 metabolite. Finally, the minor metabolite SR 49498 is generated from irbesartan by an unknown mechanism.
Irbesartan is metabolized via glucuronide conjugation and oxidation. Following oral or intravenous administration of (14)C-labeled irbesartan, more than 80% of the circulating plasma radioactivity is attributable to unchanged irbesartan. The primary circulating metabolite is the inactive irbesartan glucuronide conjugate (approximately 6%). The remaining oxidative metabolites do not add appreciably to irbesartan's pharmacologic activity. Irbesartan and its metabolites are excreted by both biliary and renal routes. Following either oral or intravenous administration of (14)C-labeled irbesartan, about 20% of radioactivity is recovered in the urine and the remainder in the feces, as irbesartan or irbesartan glucuronide. In vitro studies of irbesartan oxidation by cytochrome P450 isoenzymes indicated irbesartan was oxidized primarily by 2C9; metabolism by 3A4 was negligible. Irbesartan was neither metabolized by, nor did it substantially induce or inhibit, isoenzymes commonly associated with drug metabolism (1A1, 1A2, 2A6, 2B6, 2D6, 2E1). There was no induction or inhibition of 3A4.
Irbesartan has known human metabolites that include (1S,4S,5S,6R)-3-[5-[2-[4-[(2-butyl-4-oxo-1,3-diazaspiro[4.4]non-1-en-3-yl)methyl]phenyl]phenyl]-5H-tetrazol-2-ium-2-yl]-2,4,5,6-tetrahydroxycyclohexane-1-carboxylic acid, 2-(3-hydroxybutyl)-3-({4-[2-(2H-1,2,3,4-tetrazol-5-yl)phenyl]phenyl}methyl)-1,3-diazaspiro[4.4]non-1-en-4-one, M7, and M3.
J0E2756Z7N
IRBESARTAN
Mechanisms of Action [MoA] - Angiotensin 2 Receptor Antagonists
Established Pharmacologic Class [EPC] - Angiotensin 2 Receptor Blocker
Irbesartan is an Angiotensin 2 Receptor Blocker. The mechanism of action of irbesartan is as an Angiotensin 2 Receptor Antagonist.
IRBESARTAN
Drugs used in the treatment of acute or chronic vascular HYPERTENSION regardless of pharmacological mechanism. Among the antihypertensive agents are DIURETICS; (especially DIURETICS, THIAZIDE); ADRENERGIC BETA-ANTAGONISTS; ADRENERGIC ALPHA-ANTAGONISTS; ANGIOTENSIN-CONVERTING ENZYME INHIBITORS; CALCIUM CHANNEL BLOCKERS; GANGLIONIC BLOCKERS; and VASODILATOR AGENTS.
Agents that antagonize ANGIOTENSIN II TYPE 1 RECEPTOR. Included are ANGIOTENSIN II analogs such as SARALASIN and biphenylimidazoles such as LOSARTAN. Some are used as ANTIHYPERTENSIVE AGENTS.
Irbesartan is 60-80% bioavailable with a Tmax of 1.5-2hours. Taking irbesartan with food does not affect the bioavailability. In one study, healthy subjects were given single or multiple oral doses of 150mg, 300mg, 600mg, and 900mg of irbesartan. A single 150mg dose resulted in an AUC of 9.7±3.0µg\•hr/mL, a Tmax of 1.5 hours, a half life of 16±7 hours, and a Cmax of 1.9±0.4µg/mL. A single 300mg dose resulted in an AUC of 20.0±5.2µg\•hr/mL, a Tmax of 1.5 hours, a half life of 14±7 hours, and a Cmax of 2.9±0.9µg/mL. A single 600mg dose resulted in an AUC of 32.6±11.9µg\•hr/mL, a Tmax of 1.5 hours, a half life of 14±8 hours, and a Cmax of 4.9±1.2µg/mL. A single 900mg dose resulted in an AUC of 44.8±20.0µg\•hr/mL, a Tmax of 1.5 hours, a half life of 17±7 hours, and a Cmax of 5.3±1.9µg/mL. Multiple 150mg doses resulted in an AUC of 9.3±3.0µg\•hr/mL, a Tmax of 1.5 hours, a half life of 11±4 hours, and a Cmax of 2.04±0.4µg/mL. Multiple 300mg doses resulted in an AUC of 19.8±5.8µg\•hr/mL, a Tmax of 2.0 hours, a half life of 11±5 hours, and a Cmax of 3.3±0.8µg/mL. Multiple 600mg doses resulted in an AUC of 31.9±9.7µg\•hr/mL, a Tmax of 1.5 hours, a half life of 15±7 hours, and a Cmax of 4.4±0.7µg/mL. Multiple 900mg doses resulted in an AUC of 34.2±9.3µg\•hr/mL, a Tmax of 1.8 hours, a half life of 14±6 hours, and a Cmax of 5.6±2.1µg/mL.
20% of a radiolabelled oral dose of irbesartan is recovered in urine, and the rest is recovered in the feces. <2% of the dose is recovered in urine as the unchanged drug.
The volume of distribution of irbesartan is 53-93L.
Total plasma clearance of irbesartan is 157-176mL/min while renal clearance is 3.0-3.5mL/min.
Irbesartan is an orally active agent that does not require biotransformation into an active form. The oral absorption of irbesartan is rapid and complete with an average absolute bioavailability of 60% to 80%. Following oral administration of Avapro, peak plasma concentrations of irbesartan are attained at 1.5 to 2 hours after dosing. Food does not affect the bioavailability of Avapro. Irbesartan exhibits linear pharmacokinetics over the therapeutic dose range. The terminal elimination half-life of irbesartan averaged 11 to 15 hours. Steady-state concentrations are achieved within 3 days. Limited accumulation of irbesartan (<20%) is observed in plasma upon repeated once-daily dosing.
Studies in animals indicate that radiolabeled irbesartan weakly crosses the blood-brain barrier and placenta.
MEDICATION
Angiotensin II Type 1 Receptor Blockers; Antihypertensive Agents
Use (kg) in Switzerland (2009): >7500
Table: Irbesartan Preparations [Table#8200]
Table: Irbesartan Combination Preparations [Table#8201]
Pharmaceuticals -> Cardiovascular system -> Antihypertensions
Pharmaceuticals
用途アンジオテンシンⅡ受容体拮 抗剤です。アンジオテンシンⅡ受容体タイプ Ⅰ( AT1)受容体に作用を示します。
用途アンジオテンシンⅡ受容体拮 抗剤です。アンジオテンシンⅡ受容体タイプ Ⅰ(AT1)受容体に作用を示します。
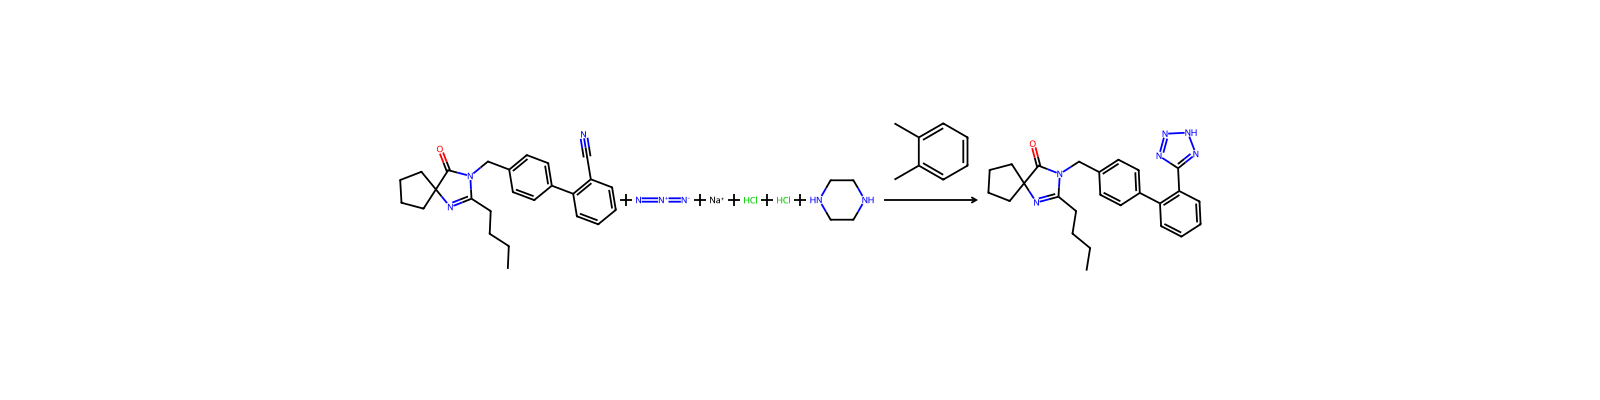
説明Avapro was launched in Germany, the UK and the US for hypertension. It can be prepared in six steps starting with cyclopentanone or in three steps from 1- aminocyclopentanecarboxylic acid ethyl ester and pentanimidic ethyl ester. Avapro is an angiotensin Ⅱ receptor antagonist that is non-competitive and selective for AT, subtypes and has no AT2 activity at postsynaptic receptors compared to presynatpic. It has no affinity for various non angiotensin Ⅱ receptor types in binding, no interaction with calcium channels or antiports, and no affinity for α1- and α2--adrenoreceptors, serotonergic receptors, muscarinic m1 and m2 or other receptors. It is as potent as saralasin but with no agonist activity and is 10 times more potent than DuP753 in rats. It is similar in efficacy to enalapril (in those with severe hypertension) and atenolol, while more effective than losartan for mild to moderate hypertension.
使用For the treatment of hypertension, as well as diabetic nephropathy with an elevated serum creatinine and proteinuria (>300 mg/day) in patients with type 2 diabetes and hypertension. Irbesartan is also used as a second line agent in the treatment of conges
一般的な説明Irbesartan, 2-butyl-3-[[29-(1H-tetrazol-5-yl)[1,19-biphenyl]-4-yl]methyl]1,3-diazaspiro[4,4]non-1en-4-one (Avapro), like losartan, possesses the acidic tetrazolesystem, which most likely plays a role, similar to the acidicgroups of angiotensin II, in binding to the angiotensin II receptor.In addition, the biphenyl system that serves to separatethe tetrazole from the aliphatic nitrogen is still present.A major difference in this agent is that it does not possessthe acidic side chain. Even so, irbesartan has good affinityfor the angiotensin II receptor because of hydrogen bondingwith the carbonyl moiety of the amide system. Also, thisparticular agent does not require metabolic activation ascandesartan does.
定義ChEBI: A biphenylyltetrazole that is an angiotensin II receptor antagonist used mainly for the treatment of hypertension.