

기본 정보
- 표준 SMILES
Nc1cccc2c1C(=O)N(C1CCC(=O)NC1=O)C2=O- InChIKey
UVSMNLNDYGZFPF-UHFFFAOYSA-N- 분자식
- C13H11N3O4
- 평균 분자량
- 273.24 g/mol
- 단동위원소 질량
- 273.07495583
개요
Pomalidomide is an aromatic amine that is thalidomide substituted at position 4 on the isoindole ring system by an amino group. Used for the treatment of multiple myeloma in patients who failed to respond to previous therapies. It has a role as an antineoplastic agent, an angiogenesis inhibitor and an immunomodulator. It is a member of isoindoles, an aromatic amine, a dicarboximide and a member of piperidones. It is functionally related to a thalidomide.
이름 및 식별자
- 우선 이름
- Pomalidomide
- IUPAC
- 4-amino-2-(2,6-dioxopiperidin-3-yl)isoindole-1,3-dione
- 영어명
- Pomalidomide
- 분자식
- C13H11N3O4
- 분자량
- 273.24
이름 및 동의어
Pomalidomide19171-19-8ActimidPomalystCC-4047Imnovid4-Aminothalidomide4-Amino-2-(2,6-dioxo-3-piperidyl)isoindoline-1,3-dione1H-Isoindole-1,3(2H)-dione, 4-amino-2-(2,6-dioxo-3-piperidinyl)-IMID-34-amino-2-(2,6-dioxopiperidin-3-yl)isoindole-1,3-dione3-Amino-N-(2,6-dioxo-3-piperidyl)phthalimide
이름 더 보기
4-AMino-2-(2,6-dioxopiperidin-3-yl)isoindoline-1,3-dionePomadomidePomaLPomalidomide-d4CS-388Pomalomide
IMiD 3CC 4047IMiD3PomalidomidaD2UX06XLB5CC4047DTXSID40893458CHEBI:72690
데이터베이스 식별자
- CAS
19171-19-8- PubChem CID
- 134780
- DTXSID
DTXSID40893458- ChEMBL
CHEMBL43452- ChEBI
CHEBI:72690- UNII
- D2UX06XLB5
- EC Number
- 805-902-5
- Nikkaji
- J1.121.690K
물성
구조 계산 물성
- XLogP
- 0.2
- 극성 표면적
- 110 Ų
- 수소 결합 공여자 수
- 2
- 수소 결합 수용자 수
- 5
- 회전 가능 결합 수
- 1
- 무거운 원자 수
- 20
- 형식 전하
- 0
- 복잡도
- 504
실험 및 물리화학적 성질
Color/FormSolid yellow powder
SolubilityLimited to low solubility into organic solvents ... low solubility in all pH solutions (about 0.01 mg/mL)
Human Drugs
Breast Feeding; Lactation; Milk, Human; Immunosuppressive Agents; Angiogenesis Inhibitors
FDA approved drugs -> Active ingredient
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
EMA approved medicines: Human medicine
Stability/Shelf LifeStable under recommended storage conditions.
물리화학적 성질
- 녹는점
- 318.5 · 318.5 - 320.5°
- 끓는 점
- 582.9 · 582.9±45.0 °C(Predicted)
- 밀도
- 1.57 · 1.570±0.06 g/cm3(Predicted)
- 저장 조건
- 2 · 2-8°C
- 용해도
- 14 mg/mL · DMSO: ≥14mg/mL
- 산도 계수 (pKa)
- 10.75 · 10.75±0.40(Predicted)
- 물리적 상태
- 가루
- 색상
- 노란색
- Merck
- 14 · 14,135
- 안정성
- 1 · 제공된 대로 구매일로부터 1년 동안 안정적입니다. DMSO의 솔루션은 최대 1개월 동안 -20°에서 보관할 수 있습니다.
- InChI
- InChI=1S/C13H11N3O4/c14-7-3-1-2-6-10(7)13(20)16(12(6)19)8-4-5-9(17)15-11(8)18/h1-3,8H,4-5,14H2,(H,15,17,18)
- InChIKey
- UVSMNLNDYGZFPF-UHFFFAOYSA-N
- SMILES
- C1(=O)C2=C(C(N)=CC=C2)C(=O)N1C1CCC(=O)NC1=O
화학적 성질
Yellow Solid
안전 및 규제
GHS 분류
GHS Classification
Danger
H360FD (75.7%): May damage fertility; May damage the unborn child [Danger Reproductive toxicity]
P203, P260, P280, P318, P319, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 37 reports by companies from 8 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
유해성 정보
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including pomalidomide, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
Toxic Combustion ProductsHazardous decomposition products formed under fire conditions. - Carbon oxides, nitrogen oxides (NOx)
Hazard Classes and CategoriesRepr. 1B (75.7%)
Hazardous Reactivities and IncompatibilitiesIncompatible materials: Strong oxidizing agents.
안전 및 보호
Fire Fighting Procedures
Advice for firefighters: Wear self-contained breathing apparatus for firefighting if necessary.
Suitable extinguishing media: Use water spray, alcohol-resistant foam, dry chemical or carbon dioxide.
Storage Conditions
Conditions for safe storage, including any incompatibilities: Keep container tightly closed in a dry and well-ventilated place. Recommended storage temperature: 2 - 8 °C.
Store at 20 °C-25 °C (68 °F-77 °F); excursions permitted to 15 °C-30 °C (59 °F-86 °F).
Cleanup Methods
Accidental Release Measures. Personal precautions, protective equipment and emergency procedures: Avoid dust formation. Avoid breathing vapors, mist or gas. Environmental precautions: Do not let product enter drains. Methods and materials for containment and cleaning up: Sweep up and shovel. Keep in suitable, closed containers for disposal.
Disposal Methods
SRP: At the time of review, regulatory criteria for small quantity disposal are subject to significant revision, however, household quantities of waste pharmaceuticals may be managed as follows: Mix with wet cat litter or coffee grounds, double bag in plastic, discard in trash.
SRP: Expired or waste pharmaceuticals shall carefully take into consideration applicable DEA, EPA, and FDA regulations. It is not appropriate to dispose by flushing the pharmaceutical down the toilet or discarding to trash. If possible return the pharmaceutical to the manufacturer for proper disposal being careful to properly label and securely package the material. Alternatively, the waste pharmaceutical shall be labeled, securely packaged and transported by a state licensed medical waste contractor to dispose by burial in a licensed hazardous or toxic waste landfill or incinerator.
Product: Offer surplus and non-recyclable solutions to a licensed disposal company. Contaminated packaging: Dispose of as unused product.
Preventive Measures
Care should be exercised in handling of Pomalyst. Pomalyst capsules should not be opened or crushed. If powder from Pomalyst contacts the skin, wash the skin immediately and thoroughly with soap and water. If Pomalyst contacts the mucous membranes, flush thoroughly with water.
Appropriate engineering controls: General industrial hygiene practice.
Gloves must be inspected prior to use. Use proper glove removal technique (without touching glove's outer surface) to avoid skin contact with this product. Dispose of contaminated gloves after use in accordance with applicable laws and good laboratory practices. Wash and dry hands.
Personal Protective Equipment (PPE)
Skin protection: Handle with gloves.
Eye/face protection: Use equipment for eye protection tested and approved under appropriate government standards such as NIOSH (US) or EN 166(EU).
Precautions for safe handling: Provide appropriate exhaust ventilation at places where dust is formed.
Respiratory protection: Respiratory protection is not required. Where protection from nuisance levels of dusts are desired, use type N95 (US) or type P1 (EN 143) dust masks. Use respirators and components tested and approved under appropriate government standards such as NIOSH (US) or CEN (EU).
Body Protection: Choose body protection in relation to its type, to the concentration and amount of dangerous substances, and to the specific work-place., The type of protective equipment must be selected according to the concentration and amount of the dangerous substance at the specific workplace.
독성 정보
Interactions
Pomalidomide is a substrate of the efflux transporter P-glycoprotein (P-gp); potent inhibitors or inducers of this transport protein may potentially alter pomalidomide exposure. Concomitant use of pomalidomide with potent inhibitors or inducers of P-gp should be avoided.
Metabolism of pomalidomide is mediated primarily by cytochrome P-450 (CYP) isoenzymes 1A2 and 3A4. Concomitant use of pomalidomide with potent inhibitors of CYP1A2 or CYP3A (e.g., ketoconazole) may increase exposure to pomalidomide and should be avoided. Conversely, concomitant use of pomalidomide with potent inducers of CYP1A2 (e.g., cigarette smoking) or CYP3A (e.g., rifampin) may decrease exposure to pomalidomide and also should be avoided. When the weak CYP3A inducer dexamethasone (20-40 mg once daily) was administered concomitantly with pomalidomide (4 mg once daily) in patients with multiple myeloma, pharmacokinetics of pomalidomide were unchanged. Pomalidomide does not inhibit or induce CYP isoenzymes in vitro.
Thalidomide and the immunomodulatory drug, lenalidomide, are therapeutically active in hematological malignancies. The ubiquitously expressed E3 ligase protein cereblon (CRBN) has been identified as the primary teratogenic target of thalidomide. Our studies demonstrate that thalidomide, lenalidomide and another immunomodulatory drug, pomalidomide, bound endogenous CRBN and recombinant CRBN-DNA damage binding protein-1 (DDB1) complexes. CRBN mediated antiproliferative activities of lenalidomide and pomalidomide in myeloma cells, as well as lenalidomide- and pomalidomide-induced cytokine production in T cells. Lenalidomide and pomalidomide inhibited autoubiquitination of CRBN in HEK293T cells expressing thalidomide-binding competent wild-type CRBN, but not thalidomide-binding defective CRBN(YW/AA). Overexpression of CRBN wild-type protein, but not CRBN(YW/AA) mutant protein, in KMS12 myeloma cells, amplified pomalidomide-mediated reductions in c-myc and IRF4 expression and increases in p21(WAF-1) expression. Long-term selection for lenalidomide resistance in H929 myeloma cell lines was accompanied by a reduction in CRBN, while in DF15R myeloma cells resistant to both pomalidomide and lenalidomide, CRBN protein was undetectable. Our biophysical, biochemical and gene silencing studies show that CRBN is a proximate, therapeutically important molecular target of lenalidomide and pomalidomide.
Pomalidomide offers an alternative for patients with relapsed/refractory multiple myeloma who have exhausted treatment options with lenalidomide and bortezomib. Little is known about pomalidomide's potential for drug-drug interactions (DDIs); as pomalidomide clearance includes hydrolysis and cytochrome P450 (CYP450)-mediated hydroxylation, possible DDIs via CYP450 and drug-transporter proteins were investigated in vitro and in a clinical study. In vitro pomalidomide was neither an inducer nor inhibitor of CYP450, nor an inhibitor of transporter proteins P glycoprotein (P-gp), BCRP, OAT1, OAT3, OCT2, OATP1B1, and OATP1B3. Oxidative metabolism of pomalidomide was predominately mediated by CYP1A2 and CYP3A4, and pomalidomide was shown to be a P-gp substrate. In healthy males, co-administration of oral (4 mg) pomalidomide with ketoconazole (CYP3A/P-gp inhibitor) or carbamazepine (CYP3A/P-gp inducer) did not result in clinically relevant changes in pomalidomide exposure. Co-administration of pomalidomide with fluvoxamine (CYP1A2 inhibitor) in the presence of ketoconazole approximately doubled pomalidomide exposure. Pomalidomide appears to have low potential for clinically relevant DDI and is unlikely to affect the clinical exposure of other drugs. Avoid co-administration of strong CYP1A2 inhibitors unless medically necessary. Pomalidomide dose should be reduced by 50% if co-administered with strong CYP1A2 inhibitors and strong CYP3A/P-gp inhibitors.
Hepatotoxicity
Serum enzyme elevations occur in 1% to 2% of patients taking pomalidomide and are more frequent with higher doses. The enzyme abnormalities are usually mild and self-limited and rarely require drug discontinuation. In addition pomalidomide has been implicated in rare instances of clinically apparent, acute liver injury which can be severe and has been reported to lead to deaths from acute liver failure. However, few of these cases have been published and the clinical features, course and outcome of the typical case of liver injury from pomalidomide have not been defined. Both thalidomide and lenalidomide have been implicated in cases of clinically apparent acute liver injury and the presentation and course of injury is likely to be similar to that caused by pomalidomide. The latency to onset of cases of thalidomide associated liver injury is usually within 1 to 6 weeks of starting the antineoplastic agent. The clinical features vary greatly and can be hepatocellular or cholestatic. Cases of acute liver failure as well as vanishing bile duct syndrome with rapid marked cholestasis and hepatic failure have been described with thalidomide and lenalidomide. Immunoallergic features may be prominent and instances of Stevens Johnson syndrome and toxic epidermal necrolysis with and without liver injury have also been linked to therapy with thalidomide and its derivatives. In most cases, the injury resolves rapidly after therapy is stopped. Monitoring of liver tests at monthly intervals is recommended when using thalidomide and its derivatives, and stopping therapy early may play an important role in preventing severe and fatal outcomes.
Milk Concentrations
EXPERIMENTAL: Following oral administration of pomalidomide to lactating rats, transfer into milk was observed, with milk to plasma ratios of 0.63 to 1.46.
EXPERIMENTAL: It is not known if pomalidomide is excreted in human milk. Pomalidomide was excreted in the milk of lactating rats.
Toxicity Summary
IDENTIFICATION AND USE: Pomalidomide is a solid yellow powder. Pomalidomide, a thalidomide analog, is an immunomodulatory agent with antineoplastic and antiangiogenic activity. It is used in patients with multiple myeloma who have received at least two prior therapies including lenalidomide and bortezomib and have demonstrated disease progression on or within 60 days of completion of the last therapy. HUMAN EXPOSURE AND TOXICITY: Pomalidomide may cause fetal toxicity; it is a structural analog of thalidomide, a known human teratogen. Therefore, pomalidomide is contraindicated during pregnancy. Acute myelogenous leukemia (AML) has been reported in patients receiving pomalidomide as investigational therapy for uses other than multiple myeloma. Serious venous thromboembolic events have also been reported in patients receiving pomalidomide. Pomalidomide did not induce chromosomal aberrations in human peripheral blood lymphocytes. ANIMAL STUDIES: Chronic administration of pomalidomide was well tolerated in rats at doses of 50, 250 and 1000 mg/kg/day for 6 months. However, monkeys exhibited greater sensitivity to pomalidomide in the studies reported. The primary toxicities observed in monkeys were associated with the hematopoietic/lymphoreticular systems. In the 9-month study in monkeys with doses of 0.05, 0.1, and 1 mg/kg/day, morbidity and early euthanasia of 6 animals were observed at the dose of 1 mg/kg/day and were attributed to immunosuppressive effects (staphylococcal infection, decreased peripheral blood lymphocytes, chronic inflammation of the large intestine, lymphoid depletion of lymphoid tissues, and lymphoid hypocellularity of bone marrow) at high exposures of pomalidomide. These immunosuppressive effects resulted in early euthanasia of 4 monkeys due to poor health condition (watery stool, inappetence, reduced food intake, and weight loss); histopathological evaluation of these animals showed chronic inflammation of the large intestine and villous atrophy of the small intestine. Staphylococcal infection was observed in 4 monkeys; 3 of these animals responded to antibiotic treatment and 1 died without treatment. In addition, findings consistent with acute myelogenous leukemia led to euthanasia of 1 monkey; clinical observations and clinical pathology and/or bone marrow alterations observed in this animal were consistent with immunosuppression. Minimal or mild bile duct proliferation with associated increases in ALP and GGT were also observed at 1 mg/kg/day. Evaluation of recovery animals indicated that all treatment-related findings were reversible after 8 weeks of dosing cessation, except for proliferation of intrahepatic bile ducts observed in 1 animal in the 1 mg/kg/day group. Pomalidomide was teratogenic in rabbits when administered during the period of major organogenesis. Doses ranging from 10 to 250 mg/kg produced embryo-fetal developmental malformations and variations. Increased cardiac anomalies and skeletal malformations were seen at all dose levels. At 100 and 250 mg/kg/day, there were slight increases in post-implantation loss and slight decreases in fetal body weights. At 100 and/or 250 mg/kg/day, fetal malformations also included limb anomalies and associated skeletal deformities, moderate dilation of the lateral ventricle in the brain, abnormal placement of the right subclavian artery, absent intermediate lobe in the lungs, low-set kidney, altered liver morphology, incompletely or not ossified pelvis, an increased average for supernumerary thoracic ribs and a reduced average for ossified tarsals. Pomalidomide was also teratogenic in rats. Malformations such as the absence of urinary bladder, absence of thyroid gland, and fusion and misalignment of lumbar and thoracic vertebral elements (central and/or neural arches) sometimes associated with discontinuous and misshapen ribs were observed at all dosage levels (25, 250, and 1000 mg/kg/day). In a fertility and early embryonic development study in rats, pomalidomide was administered to male and female rats at doses of 25, 250, and 1000 mg/kg/day before, during, and after mating with animals at the same dose level. Uterine examination on Gestation Day 13 showed a decrease in mean number of viable embryos and an increase in postimplantation loss at all dose levels. Pomalidomide was not mutagenic in bacterial and mammalian mutation Ames assays, and did not induce micronuclei formation in polychromatic erythrocytes in bone marrow of rats administered doses up to 2000 mg/kg/day.
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ This phase 1, open label, dose-escalation study investigated the tolerated dose (recommended dose), safety, efficacy, and pharmacokinetics of pomalidomide alone or pomalidomide plus low-dose dexamethasone in Japanese patients with refractory or relapsed and refractory multiple myeloma. Twelve patients were enrolled. Patients received pomalidomide 2 mg (Cohort 1) or 4 mg (Cohort 2) orally on day 1 and days 3-21 of a 28-day cycle. The tolerated dose of pomalidomide was determined to be 4 mg administered on days 1-21 of a 28-day cycle. Efficacy outcomes with pomalidomide plus low-dose dexamethasone were consistent with those of previous studies. Responses (partial response or better) were achieved by 3 patients (25%; 1 [17%] in Cohort 1 and 2 [33%] in Cohort 2), and the median time to response was 6.4 months overall (9.0 months for Cohort 1 and 4.2 months for Cohort 2). The median progression-free survival was 5.5 months overall (5.1 months for Cohort 1 and not reached for Cohort 2). The most frequently occurring grade = 3 adverse events were neutropenia (67%), anemia (25%), lymphopenia (25%), and pneumonia (25%), consistent with previous studies of pomalidomide plus low-dose dexamethasone in refractory or relapsed and refractory multiple myeloma. Further investigation of pomalidomide is recommended for Japanese patients with refractory or relapsed and refractory multiple myeloma.
/SIGNS AND SYMPTOMS/ Acute myelogenous leukemia (AML) has been reported in patients receiving pomalidomide as investigational therapy for uses other than multiple myeloma.
/SIGNS AND SYMPTOMS/ Serious venous thromboembolic events have been reported in patients receiving pomalidomide. In the pivotal multiple myeloma trial, deep-vein thrombosis or pulmonary embolism occurred in 3% of patients receiving pomalidomide alone or in combination with low-dose dexamethasone. In this trial, all patients were required to receive an antithrombotic agent for prevention of venous thromboembolism; antithrombotic agents used for prophylaxis or treatment included aspirin (81% of patients), heparin (21%), warfarin (16%), and clopidogrel (3%). The manufacturer and some experts state that decisions regarding use of thromboprophylaxis and selection of an appropriate thromboprophylaxis regimen (e.g., aspirin, anticoagulant) should be based on careful assessment of the patient's risk factors for thromboembolism.
/SIGNS AND SYMPTOMS/ Pomalidomide may cause fetal toxicity; pomalidomide is a structural analog of thalidomide, a known human teratogen, and teratogenic and other fetotoxic effects of pomalidomide (e.g., musculoskeletal anomalies and deformities; absence of internal organs, including bladder and thyroid; defects of internal organ systems, including cardiovascular, respiratory, renal, hepatic, and CNS abnormalities; increased fetal resorptions) have been demonstrated in animals. Therefore, pomalidomide is contraindicated in women who are pregnant.
For more Human Toxicity Excerpts (Complete) data for Pomalidomide (10 total), please visit the HSDB record page.
Drug Induced Liver Injury
Drug Induced Liver Injury Rank (DILIrank 2.0)
Pomalidomide
vMost-DILI-concern
8
Warnings & precautions
DOI:10.1016/j.drudis.2016.02.015
Non-Human Toxicity Excerpts
/LABORATORY ANIMALS: Acute Exposure/ Single-dose oral and intravenous studies in mice and rats indicated that the acute oral minimum lethal dose was >2000 mg/kg, and acute IV minimum lethal dose was >80 mg/kg for mice, and >50 mg/kg for rats.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ One of twelve monkeys dosed with 1 mg/kg of pomalidomide (an exposure approximately 15-fold of the exposure in patients at the recommended dose of 4 mg/per day) developed acute myeloid leukemia in a 9-month repeat-dose toxicology study.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ In monkeys, pomalidomide was evaluated in repeat-dose studies of up to 9 months in duration. In these studies, monkeys exhibited greater sensitivity to pomalidomide effects than rats. The primary toxicities observed in monkeys were associated with the hematopoietic/lymphoreticular systems. In the 9-month study in monkeys with doses of 0.05, 0.1, and 1 mg/kg/day, morbidity and early euthanasia of 6 animals were observed at the dose of 1 mg/kg/day and were attributed to immunosuppressive effects (staphylococcal infection, decreased peripheral blood lymphocytes, chronic inflammation of the large intestine, lymphoid depletion of lymphoid tissues, and lymphoid hypocellularity of bone marrow) at high exposures of pomalidomide (15-fold exposure ratio relative to a 4 mg clinical dose). These immunosuppressive effects resulted in early euthanasia of 4 monkeys due to poor health condition (watery stool, inappetence, reduced food intake, and weight loss); histopathologic evaluation of these animals showed chronic inflammation of the large intestine and villous atrophy of the small intestine. Staphylococcal infection was observed in 4 monkeys; 3 of these animals responded to antibiotic treatment and 1 died without treatment. In addition, findings consistent with acute myelogenous leukemia led to euthanasia of 1 monkey; clinical observations and clinical pathology and/or bone marrow alterations observed in this animal were consistent with immunosuppression. Minimal or mild bile duct proliferation with associated increases in ALP and GGT were also observed at 1 mg/kg/day. Evaluation of recovery animals indicated that all treatment-related findings were reversible after 8 weeks of dosing cessation, except for proliferation of intrahepatic bile ducts observed in 1 animal in the 1 mg/kg/day group. The NOAEL was 0.1 mg/kg/day (0.5-fold exposure ratio relative to a 4 mg clinical dose). Generally, similar findings were seen in shorter duration studies in monkeys that included higher dose level/exposures and also resulted in decreased peripheral blood neutrophil counts and sometimes lower red blood cell parameters.
/LABORATORY ANIMALS: Chronic Exposure or Carcinogenicity/ In rats, chronic administration of pomalidomide at doses of 50, 250, and 1000 mg/kg/day for 6 months was well tolerated. No adverse findings were noted up to 1000 mg/kg/day (175-fold exposure ratio relative to a 4-mg clinical dose).
For more Non-Human Toxicity Excerpts (Complete) data for Pomalidomide (13 total), please visit the HSDB record page.
Populations at Special Risk
Pomalidomide and its metabolites are primarily excreted by the kidneys. The influence of renal impairment on the safety, efficacy, and pharmacokinetics of pomalidomide has not been evaluated. Patients with serum creatinine greater than 3.0 mg/dL were excluded in clinical studies. Avoid Pomalyst in patients with a serum creatinine greater than 3.0 mg/dL.
Use of pomalidomide should be avoided in patients with serum aminotransferase (ALT and AST) concentrations exceeding 3 times the upper limit of normal (ULN) and bilirubin concentrations exceeding 2 mg/dL. Use of pomalidomide also should be avoided in patients with serum creatinine concentrations exceeding 3 mg/dL. Safety and efficacy have not been established in these patients.
Pomalidomide may cause fetal toxicity; pomalidomide is a structural analog of thalidomide, a known human teratogen, and teratogenic and other fetotoxic effects of pomalidomide (e.g., musculoskeletal anomalies and deformities; absence of internal organs, including bladder and thyroid; defects of internal organ systems, including cardiovascular, respiratory, renal, hepatic, and CNS abnormalities; increased fetal resorptions) have been demonstrated in animals. Therefore, pomalidomide is contraindicated in women who are pregnant.
Antidote and Emergency Treatment
/SRP:/ Immediate first aid: Ensure that adequate decontamination has been carried out. If patient is not breathing, start artificial respiration, preferably with a demand valve resuscitator, bag-valve-mask device, or pocket mask, as trained. Perform CPR if necessary. Immediately flush contaminated eyes with gently flowing water. Do not induce vomiting. If vomiting occurs, lean patient forward or place on the left side (head-down position, if possible) to maintain an open airway and prevent aspiration. Keep patient quiet and maintain normal body temperature. Obtain medical attention. /Poisons A and B/
/SRP:/ Basic treatment: Establish a patent airway (oropharyngeal or nasopharyngeal airway, if needed). Suction if necessary. Watch for signs of respiratory insufficiency and assist ventilations if needed. Administer oxygen by nonrebreather mask at 10 to 15 L/min. Monitor for pulmonary edema and treat if necessary ... . Monitor for shock and treat if necessary ... . Anticipate seizures and treat if necessary ... . For eye contamination, flush eyes immediately with water. Irrigate each eye continuously with 0.9% saline (NS) during transport ... . Do not use emetics. For ingestion, rinse mouth and administer 5 mL/kg up to 200 mL of water for dilution if the patient can swallow, has a strong gag reflex, and does not drool ... . Cover skin burns with dry sterile dressings after decontamination ... . /Poisons A and B/
/SRP:/ Advanced treatment: Consider orotracheal or nasotracheal intubation for airway control in the patient who is unconscious, has severe pulmonary edema, or is in severe respiratory distress. Positive-pressure ventilation techniques with a bag valve mask device may be beneficial. Consider drug therapy for pulmonary edema ... . Consider administering a beta agonist such as albuterol for severe bronchospasm ... . Monitor cardiac rhythm and treat arrhythmias as necessary ... . Start IV administration of D5W TKO /SRP: "To keep open", minimal flow rate/. Use 0.9% saline (NS) or lactated Ringer's (LR) if signs of hypovolemia are present. For hypotension with signs of hypovolemia, administer fluid cautiously. Watch for signs of fluid overload ... . Treat seizures with diazepam or lorazepam ... . Use proparacaine hydrochloride to assist eye irrigation ... . /Poisons A and B/
Effects During Pregnancy and Lactation◉ Summary of Use during Lactation
규제 정보
FDA Requirements
The Approved Drug Products with Therapeutic Equivalence Evaluations identifies currently marketed prescription drug products, including pomalidomide, approved on the basis of safety and effectiveness by FDA under sections 505 of the Federal Food, Drug, and Cosmetic Act.
안전 데이터
- wgk
- 3
- rtecs
- NR3397905
- HS 번호
- 29251900
- Hazard Classifications
- Repr. 1B
- 스토리지 클래스
- 6.1C - Combustible acute toxic Cat.3toxic compounds or compounds which causing chronic effects
- 유해 물질 데이터
- 19171-19-8(Hazardous Substances Data)
화학 및 산업
약리 정보
ATC Code
L04AX06
L - Antineoplastic and immunomodulating agents
QL - Antineoplastic and immunomodulating agents
Protein Binding12-44% protein bound. It is not concentration dependent.
PharmacodynamicsPomalidomide is more potent than thalidomide (100-times) and lenalidomide (10-times).
Mechanism of Action
Promalidomide is an immunomodulatory agent with antineoplastic activity. It is shown to inhibit the proliferation and induce apoptosis of various tumour cells. Furthermore, promalidomide enhances T cell and natural killer (NK) cell-mediated immunity and inhibited the production of pro-inflammatory cytokines, like TNF-alpha or IL-6, by monocytes. The primary target of promalidomide is thought to be the protein cereblon. It binds to this target and inhibits ubiquitin ligase activity. It is also a transcriptional inhibitor of COX2.
In vitro studies have identified a molecular mechanism for the pleiotropic effects of pomalidomide in multiple myeloma (MM) and in T cells. Specifically, pomalidomide bound to the protein cereblon (CRBN), part of an E3 ligase complex, and the expression levels of CRBN in myeloma cells was linked to both the efficacy of pomalidomide and to the acquisition of resistance to lenalidomide. Pomalidomide was claimed to have direct antiproliferative activity against B cell lines derived from MM and Burkitt's lymphoma patients. Pomalidomide in combination with dexamethasone increased this effect in a dose dependent manner.
Although several mechanisms have been proposed to explain the activity of thalidomide, lenalidomide and pomalidomide in multiple myeloma (MM), including demonstrable anti-angiogenic, anti-proliferative and immunomodulatory effects, the precise cellular targets and molecular mechanisms have only recently become clear. A landmark study recently identified cereblon (CRBN) as a primary target of thalidomide teratogenicity. Subsequently it was demonstrated that CRBN is also required for the anti-myeloma activity of thalidomide and related drugs, the so-called immune-modulatory drugs (IMiDs). Low CRBN expression was found to correlate with drug resistance in MM cell lines and primary MM cells. One of the downstream targets of CRBN identified is interferon regulatory factor 4 (IRF4), which is critical for myeloma cell survival and is down-regulated by IMiD treatment. CRBN is also implicated in several effects of IMiDs, such as down-regulation of tumor necrosis factor-alpha (TNF-a) and T cell immunomodulatory activity, demonstrating that the pleotropic actions of the IMiDs are initiated by binding to CRBN. Future dissection of CRBN downstream signaling will help to delineate the underlying mechanisms for IMiD action and eventually lead to development of new drugs with more specific anti-myeloma activities. It may also provide a biomarker to predict IMiD response and resistance.
The Cul4-Rbx1-DDB1-Cereblon E3 ubiquitin ligase complex is the target of thalidomide, lenalidomide and pomalidomide, therapeutically important drugs for multiple myeloma and other B-cell malignancies. These drugs directly bind Cereblon (CRBN) and promote the recruitment of substrates Ikaros (IKZF1) and Aiolos (IKZF3) to the E3 complex, thus leading to substrate ubiquitination and degradation. Here we present the crystal structure of human CRBN bound to DDB1 and the drug lenalidomide. A hydrophobic pocket in the thalidomide-binding domain (TBD) of CRBN accommodates the glutarimide moiety of lenalidomide, whereas the isoindolinone ring is exposed to solvent. We also solved the structures of the mouse TBD in the apo state and with thalidomide or pomalidomide. Site-directed mutagenesis in lentiviral-expression myeloma models showed that key drug-binding residues are critical for antiproliferative effects.
In the 1950s, the drug thalidomide, administered as a sedative to pregnant women, led to the birth of thousands of children with multiple defects. Despite the teratogenicity of thalidomide and its derivatives lenalidomide and pomalidomide, these immunomodulatory drugs (IMiDs) recently emerged as effective treatments for multiple myeloma and 5q-deletion-associated dysplasia. IMiDs target the E3 ubiquitin ligase CUL4-RBX1-DDB1-CRBN (known as CRL4(CRBN)) and promote the ubiquitination of the IKAROS family transcription factors IKZF1 and IKZF3 by CRL4(CRBN). Here we present crystal structures of the DDB1-CRBN complex bound to thalidomide, lenalidomide and pomalidomide. The structure establishes that CRBN is a substrate receptor within CRL4(CRBN) and enantioselectively binds IMiDs. Using an unbiased screen, we identified the homeobox transcription factor MEIS2 as an endogenous substrate of CRL4(CRBN). Our studies suggest that IMiDs block endogenous substrates (MEIS2) from binding to CRL4(CRBN) while the ligase complex is recruiting IKZF1 or IKZF3 for degradation. This dual activity implies that small molecules can modulate an E3 ubiquitin ligase and thereby upregulate or downregulate the ubiquitination of proteins.
Biological Half-Life
Healthy subjects = 9.4 hours; Multiple myeloma patients = 7.5 hours.
... the terminal half-lives of pomalidomide in animals ranged from mean values of 4 to 7 hours following an IV dose.
Pomalidomide is eliminated with a median plasma half-life of approximately 9.5 hours in healthy subjects and approximately 7.5 hours in patients with multiple myeloma.
Metabolism/Metabolites
Promalidomide is hepatically metabolized by CYP1A2 and CYP3A4. The metabolites are 26-fold less active than the parent compound. Minor contributions from CYP2C19 and CYP2D6 have been observed in vitro.
In hepatocytes from rabbit and human, and in vivo in rat, monkey and human, pomalidomide was metabolized primarily via hydroxylation of the phthalimide ring (M14, M16 and M17) followed by glucuronidation (M12 and M13), hydrolysis of the glutarimide ring (M10 and M11), and hydrolysis of the phthalimide ring (M2). There were no unique or disproportionate metabolites observed in humans, compared to rats and monkeys.
Pomalidomide is primarily metabolized in the liver by CYP1A2 and CYP3A4. In vitro, CYP1A2 and CYP3A4 were identified as the primary enzymes involved in the CYP-mediated hydroxylation of pomalidomide, with additional minor contributions from CYP2C19 and CYP2D6.
FDA Pharmacological Classification
D2UX06XLB5
POMALIDOMIDE
Established Pharmacologic Class [EPC] - Thalidomide Analog
Pomalidomide is a Thalidomide Analog.
POMALIDOMIDE
Thalidomide Analog [EPC]
MeSH Pharmacological Classification
Biologically active substances whose activities affect or play a role in the functioning of the immune system.
Agents and endogenous substances that antagonize or inhibit the development of new blood vessels.
Absorption, Distribution and Excretion
Pomalidomide is generally well absorbed. The major circulating component is the parent compound. Tmax, single oral dose = 2 -3 hours. When 4 mg of promalidomide is given to patients with multiple myeloma, the steady-state pharmacokinetic parameters are as follows: AUC(T) = 400 ng.hr/mL; Cmax = 75 ng/mL. Promalidomide accumulates following multiple doses.
When a single oral dose (2mg) is given to healthy subjects, 73% of the dose was eliminated in urine. 15% of the dose was eliminated in feces. 2% and 8% of the dose eliminated unchanged as pomalidomide in urine and feces, respectively.
Mean apparent volume of distribution (Vd/F), steady-state = 62 - 138 L
Total body clearance = 7-10 L/hour
Pomalidomide has a mean apparent volume of distribution (Vd/F) between 62 and 138 L at steady state. Pomalidomide is distributed in semen of healthy subjects at a concentration of approximately 67% of plasma level at 4 hours post-dose (approximate Tmax) after 4 days of once-daily dosing at 2 mg. Human plasma protein binding ranges from 12% to 44% and is not concentration dependent. Pomalidomide is a substrate for P-glycoprotein (P-gp).
In patients with multiple myeloma who received Pomalyst 4 mg daily alone or in combination with dexamethasone, pomalidomide steady-state drug exposure was characterized by AUC(T) of 400 ng*h/mL and Cmax of 75 ng/mL. Following multiple doses, pomalidomide has an accumulation ratio of 27% to 31%.
용도 및 제조
Uses
MEDICATION
Angiogenesis Inhibitors; Immunologic Factors
Methods of Manufacturing
Pomalidomide is synthesized in two main steps using commercially available well defined starting materials with acceptable specifications. The first step consists of a coupling reaction in which the starting materials react to form crude pomalidomide. The second step is a purification process consisting on filtration, crystallization and drying to obtain the final drug substance.
Preparation: G. W. Muller et al., World Intellectual Property Organization patent 9803502; eidem, United States of America patent 6335349 (1998, 2002 both to Celgene).
Formulations/PreparationsTable: Pomalidomide Preparations [Table#8206]
응용 분야
개요In February 2013, the US FDA approved pomalidomide (also known as CC4047) for the treatment of multiple myeloma (MM) in patients with disease progression after receiving other cancer therapeutics. Pomalidomide is a 4-amino analog of thalidomide with enhanced potency and an improved toxicity profile. Pomalidomide and thalidomide exert their effects by modulation of immunity, inhibition of angiogenesis, interference with the bone/tumor microenvironment, and inhibition of the cereblon protein. Pomalidomide potently inhibited in vitro proliferation in a variety of human MM cell lines, IC50~10 nM, while thalidomide showed almost no inhibition up to 100 μM. In mouse MM tumor models, 50 mg/kg daily doses of pomalidomide resulted in marked inhibition of tumor growth after 15 days of treatment and complete regression in 3–6 weeks versus thalidomide-treated controls at the same dose. Pomalidomide is prepared by condensation of 4-nitrophthalic anhydride with 3-aminopiperidine-2,6-dione followed by catalytic hydrogenation of the nitro group.
역사Pomalidomide, a third-generation immunomodulatory agent (IMiD) following thalidomide and lenalidomide, was developed by Celgene in the United States. It represents a structural optimization and enhanced potency of thalidomide-like drugs. Its development stems from precise modifications to the thalidomide structure, particularly the addition of an amino group at the fourth carbon atom of the phthalimide ring. This improvement enhances its antitumor activity and immunomodulatory effects, aiming to overcome patient resistance to the first two generations of IMiD drugs. Pomalidomide exerts its potent anti-myeloma effect by binding to the intracellular Cerebrolysin (CRBN) protein and targeting the degradation of various tumor proteins. Its key clinical approval was based on the results of the MM-003 Phase III clinical trial, which showed that pomalidomide in combination with low-dose dexamethasone (Pom+LoDEX) significantly prolonged progression-free survival (PFS) in patients with relapsed and refractory multiple myeloma (RRMM). Based on this groundbreaking data, the U.S. FDA granted accelerated approval to pomalidomide on February 8, 2013, for the treatment of patients with RRMM who have received at least two prior lines of therapy, making it an important third- or fourth-line treatment option for refractory myeloma. Subsequently, its indication was expanded to include Kaposi's sarcoma in 2020. However, due to its structural similarity to thalidomide, pomalidomide remains subject to strict risk assessment and remission strategy (REMS) procedures worldwide to ensure its safety.
용도Pomalidomide inhibits LPS-induced TNF-α release with IC50 of 13 nM
상·하류 제품 정보
상류 원료
공급사50 곳
梯希爱(上海)化成工业发展有限公司021-67121386 · [email protected]
衢州润东化工有限公司0570-8789886 18892685668 · [email protected]
上海阿拉丁生化科技股份有限公司400-6206333 13167063860 · [email protected]
爱斯特(成都)生物制药股份有限公司+86-28-85122536 85324413 · [email protected]
韶远科技(上海)有限公司021-50795510 4000665055 · [email protected]
江西泰欣诺实业有限公司13576915071 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
Syntechem Co.,Ltd[email protected]
大连美仑生物技术有限公司0411-62910999 13889544652 · [email protected]
南京药石科技股份有限公司025-86918202 4000255188 · [email protected]
安耐吉化学&3A(安徽泽升科技股份有限公司)400-0056266 · [email protected]
上海瀚鸿科技股份有限公司021-54306202 13764082696 · [email protected]
China Kouting Group Limited+86 (21) 5811-6473 5811-6475 · [email protected]
嘉兴市艾森化工有限公司0573-85285100 18627885956 · [email protected]
上海泰坦科技股份有限公司400-6009262 15618770481 · [email protected]
上海瀚香生物科技有限公司177-54423994 17754423994 · [email protected]
安徽海康药业有限责任公司86-0556-5800026 17709662922 · [email protected]
大赛璐药物手性技术(上海)有限公司021-50460086-9 15921403865 · [email protected]
上海复和化学科技有限公司0086-21-67651709 · [email protected]
成都海品信医药科技有限公司85114309 18982182443 · [email protected]
天津永生生物技术有限公司022-60987737 13512258274;13820956092
上海思域化工科技有限公司86-21-34053660 · [email protected]
AdooQ BioScience, LLC+1 (866) 930-6790 · [email protected]
Wuhan NCE Biomedical Co.,Ltd.4000-027-021 |24 +86-13986109188 | +86-15623472865 | +81-08033611988
江苏艾康生物医药研发有限公司025-66113011 13913916777 · [email protected]
上海健超生物科技有限公司150-2103-5486 18017383231 · [email protected]
TOKYO CHEMICAL INDUSTRY CO., LTD.03-36680489 · [email protected]
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
随州市红旗化工有限公司0722-3257376 13026100080;13235518175 · [email protected]
深圳康特腾科技有限公司86-0755-86635001 · [email protected]
Shanghai Witofly Chemical Co.,Ltd[email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
ApexBio Technology LLC+1-832-696-8203 · [email protected]
上海陶素生化科技有限公司021-33632979 · [email protected]
济南铭雅医药科技有限公司0531-85828981 · [email protected]
山东友帮生化科技有限公司15098208899 · [email protected]
上海笛柏生物科技有限公司400-008-9730,021-54359730 400-008-9730 · [email protected]
北京汤普森生物科技有限公司+86-13439059536 +86-15201677815 · [email protected]
四川省维克奇生物科技有限公司028-81700200 18116577057 · [email protected]
上海御略医药科技有限公司021-60345187 13671753212 · [email protected]
上海麦克林生化科技股份有限公司15221275939 15221275939 · [email protected]
上海寰川实业有限公司021-61478794 · [email protected]
南京百鑫德诺生物科技有限公司025-58849295 · [email protected]
广州市慈铭生物科技有限公司020-38082199,29065168,38082986,29878298,29866629,4000192398
上海孚一生物科技有限公司+86 (21) 61124340
凯试(上海)科技有限公司021-50135380 · [email protected]
湖北巨胜科技有限公司027-59599241 18871490274 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
济南凯化化工有限公司0531-86986780 13153183025 · [email protected]
Sigma-Aldrich西格玛奥德里奇(上海)贸易有限公司021-61415566 800-8193336 · [email protected]
추가 설명
정의ChEBI: Pomalidomide is an aromatic amine that is thalidomide substituted at position 4 on the isoindole ring system by an amino group. Used for the treatment of multiple myeloma in patients who failed to respond to previous therapies. It has a role as an antineoplastic agent, an immunomodulator and an angiogenesis inhibitor. It is a dicarboximide, a member of isoindoles, a member of piperidones and an aromatic amine. It is functionally related to a thalidomide.
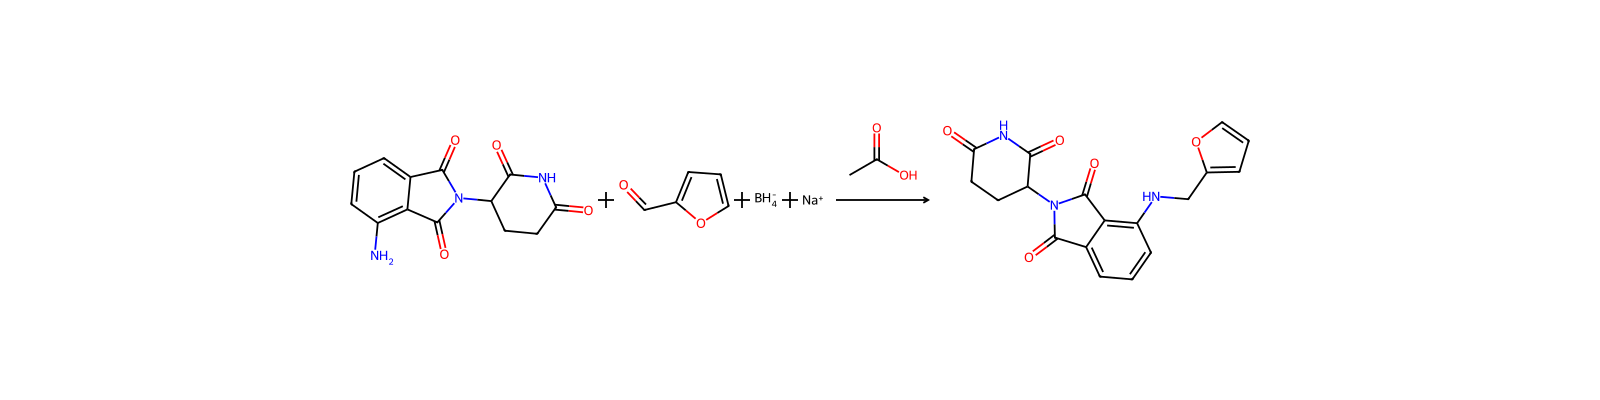
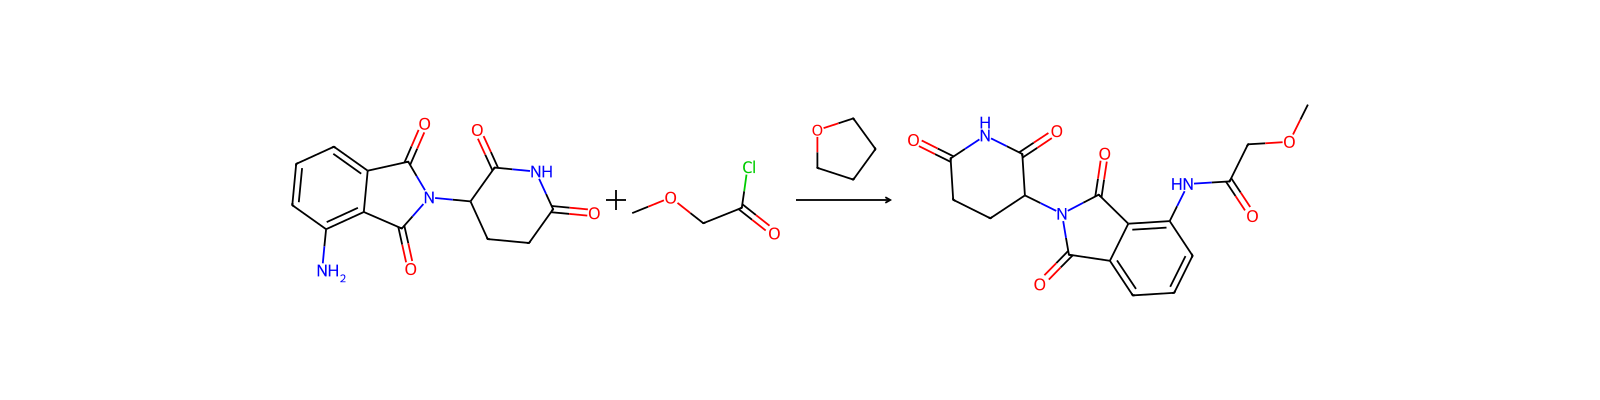
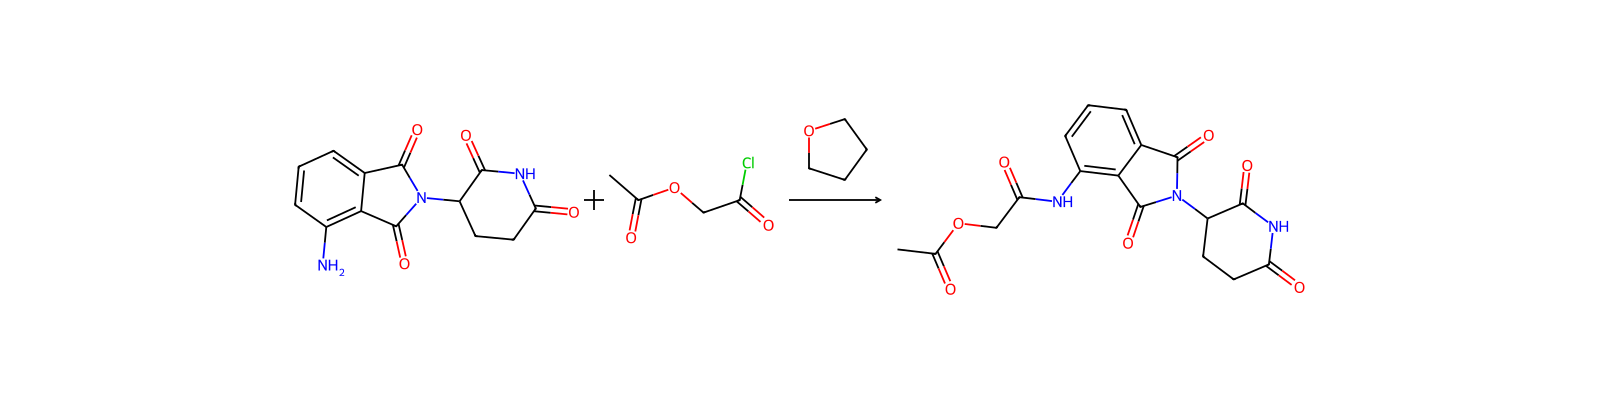
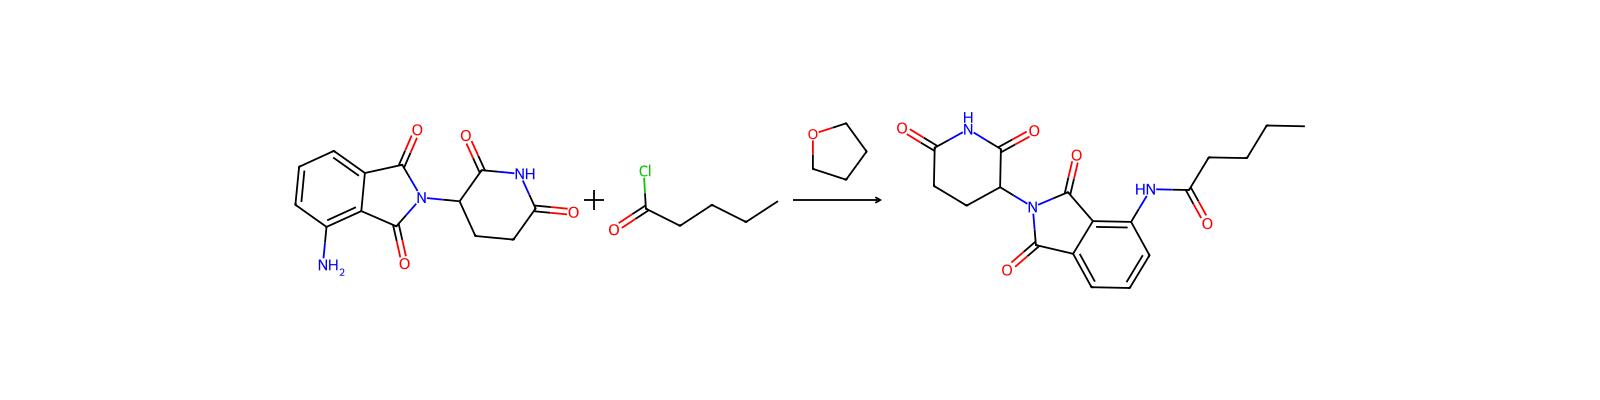
관련 반응
115건



연결된 노트
불러오는 중…