
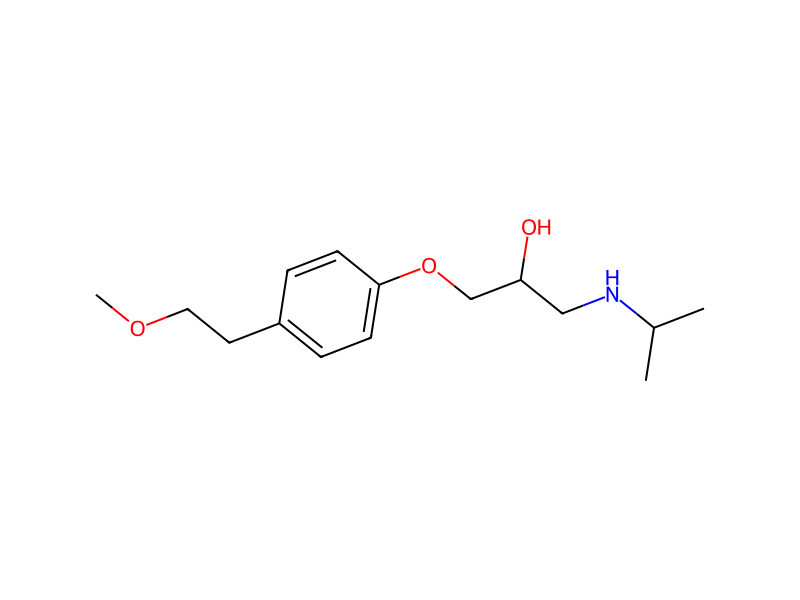
기본 정보
- 표준 SMILES
COCCc1ccc(OCC(O)CNC(C)C)cc1- InChIKey
IUBSYMUCCVWXPE-UHFFFAOYSA-N- 분자식
- C15H25NO3
- 평균 분자량
- 267.36 g/mol
- 단동위원소 질량
- 267.18344366
개요
Metoprolol is a propanolamine that is 1-(propan-2-ylamino)propan-2-ol substituted by a 4-(2-methoxyethyl)phenoxy group at position 1. It has a role as a geroprotector, a beta-adrenergic antagonist, an antihypertensive agent, a xenobiotic and an environmental contaminant. It is a propanolamine, an aromatic ether, a secondary alcohol and a secondary amino compound.
이름 및 식별자
- 우선 이름
- Metoprolol
- IUPAC
- 1-[4-(2-methoxyethyl)phenoxy]-3-(propan-2-ylamino)propan-2-ol
- 현지명
- 메토프로롤
- 영어명
- Metoprolol
- 분자식
- C15H25NO3
- 분자량
- 267.36
이름 및 동의어
metoprolol51384-51-1(RS)-MetoprololBeatrololdl-MetoprololSeroken37350-58-6MetoprololumSpesikor1-(Isopropylamino)-3-(4-(2-methoxyethyl)phenoxy)propan-2-olCGP 2175CGP-2175
이름 더 보기
메토프로롤d-Metoprololl-Metoprololrac MetoprololC07202LoresorPreblokSpesicorMetohexal
Metoprolol slow releaseDTXSID2023309GEB06NHM231-(isopropylamino)-3-[4-(2-methoxyethyl)phenoxy]propan-2-ol1-[4-(2-methoxyethyl)phenoxy]-3-(propan-2-ylamino)propan-2-olH-93/262-Propanol, 1-(4-(2-methoxyethyl)phenoxy)-3-((1-methylethyl)amino)-2-Propanol, 1-[4-(2-methoxyethyl)phenoxy]-3-[(1-methylethyl)amino]-
데이터베이스 식별자
- CAS
37350-58-6、51384-51-1- PubChem CID
- 4171
- DTXSID
DTXSID2023309- ChEMBL
CHEMBL13- ChEBI
CHEBI:6904- UNII
- GEB06NHM23
- EC Number
- 253-483-7、257-166-4
- Nikkaji
- J31.137E
물성
구조 계산 물성
- XLogP
- 1.9
- 극성 표면적
- 50.7 Ų
- 수소 결합 공여자 수
- 2
- 수소 결합 수용자 수
- 4
- 회전 가능 결합 수
- 9
- 무거운 원자 수
- 19
- 형식 전하
- 0
- 복잡도
- 215
실험 및 물리화학적 성질
Chemical ClassesPharmaceutical
Drugs
Drug
Pharmaceuticals
Pharmaceuticals -> Used in Switzerland
Pharmaceuticals -> Antihypertensive drugs
LogP
log Kow = 1.88
1.88
1.65
Solubility
Soluble (tartrate form)
Solubility (mg/ml) @ 25 °C: water >1000; methanol >500; chloroform 496; acetone 1.1; acetonitrile 0.89; hexane 0.001; UV max (water): 223 nm (E 23400) /Tartrate/
Human Drugs
Breast Feeding; Lactation; Milk, Human; Antihypertensive Agents; Adrenergic Beta-Antagonists; Antiarrhythmics
Pharmaceuticals
Antianginal medicines
Boiling Point398ºC (estimate)
Physical DescriptionSolid
Dissociation Constants
9.56
9.7
9.7
Collision Cross Section
172.1 Ų [M+H]+ [CCS Type: DT; Buffer gas: N2; Ionization: ESI+; Dataset: TOXCAST; Source Identifier: DTXSID2023309]
170.7 Ų [M+H]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
171.4 Ų [M+H]+ [CCS Type: DT; Method: single field calibrated]
172.7 Ų [M+H]+ [CCS Type: TW; Method: Major Mix IMS/Tof Calibration Kit (Waters)]
163.49 Ų [M+H-H2O]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
172.54 Ų [M+H]+
Other Experimental Properties
White crystalline powder; freely soluble in water; soluble in methanol; sparingly soluble in ethanol; slightly soluble in dichloromethane and 2-propanol; practically insoluble in ethyl acetate, acetone, diethylether and heptane /Metoprolol succinate/
White crystalline powder /Metoprolol tartrate/
Bitter taste; pKa = 9.68; very sol in water and freely sol in alc. /Metoprolol tartrate/
물리화학적 성질
- 녹는점
- 35 °C · 35 °C
- 끓는 점
- 398.6 · 398.6±37.0 °C(Predicted)
- 밀도
- 1.033 · 1.033±0.06 g/cm3(Predicted)
- 저장 조건
- -20 °C · -20°C Freezer
- 용해도
- 클로로포름(약간 용해됨), DMSO(약간 용해됨), 메탄올(약간 용해됨)
- 산도 계수 (pKa)
- 9.56 · pKa 9.56± 0.01(H2O,t =25,I=0.15(KCl))(Approximate)
- 물리적 상태
- 고체
- 색상
- 흰색에서 황백색까지
- EPA
- 2 · 2-Propanol, 1-[4-(2-methoxyethyl)phenoxy]-3-[(1-methylethyl)amino]- (51384-51-1)
안전 및 규제
GHS 분류
GHS Classification
Warning
H315 (66.7%): Causes skin irritation [Warning Skin corrosion/irritation]
P203, P261, P264, P264+P265, P271, P273, P280, P302+P352, P304+P340, P305+P351+P338, P318, P319, P321, P332+P317, P337+P317, P362+P364, P391, P403+P233, P405, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 3 reports by companies from 3 notifications to the ECHA C&L Inventory. Each notification may be associated with multiple companies.
This chemical does not meet GHS hazard criteria for 33.3% (1 of 3) of reports.
Danger
유해성 정보
Other Safety InformationIMAP assessments - 2-Propanol, 1-[4-(2-methoxyethyl)phenoxy]-3-[(1-methylethyl)amino]-: Environment tier I assessment
FDA Requirements
Metoprolol tartrate, used as a beta adrenergic blocking agent, was approved by FDA for marketing in the United States 12/84.
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed drug products, incl metaprolol, metoprolol tartrate, and metoprolol succinate approved on the basis of safety and effectiveness by FDA under sections 505 and 507 of the Federal Food, Drug, and Cosmetic Act. /Metaprolol, metoprolol tartrate, and metoprolol succinate/
Manufacturers, packers, and distributors of drug and drug products for human use are responsible for complying with the labeling, certification, and usage requirements as prescribed by the Federal Food, Drug, and Cosmetic Act, as amended (secs 201-902, 52 Stat. 1040 et seq., as amended; 21 U.S.C. 321-392).
Special ReportsBenfield P et al; Metoprolol. An Updated Review of its Pharmacodynamic and Pharmacokinetic Properties, and Therapeutic Efficacy, in Hypertension, Ischaemic Heart Disease and Related Cardiovascular Disorders; Drugs 31 (5): 376-429 (1986).
Hazard Classes and Categories
Skin Irrit. 2 (66.7%)
Flam. Sol. 1 (33.3%)
안전 및 보호
Storage Conditions
Commercially available preparations of metoprolol tartrate should be protected from light. Metoprolol tartrate tablets should be stored in tight, light-resistant containers at 15-30 °C and metoprolol tartrate injection should be stored at a temperature of 30 °C or less, preferably at 15-30 °C, freezing of the injection should be avoided.
Disposal Methods
SRP: The most favorable course of action is to use an alternative chemical product with less inherent propensity for occupational exposure or environmental contamination. Recycle any unused portion of the material for its approved use or return it to the manufacturer or supplier. Ultimate disposal of the chemical must consider: the material's impact on air quality; potential migration in soil or water; effects on animal, aquatic, and plant life; and conformance with environmental and public health regulations.
독성 정보
Body BurdenMetoprolol is distributed into milk in a concentration about 3-4 times that of maternal plasma concentrations, but the actual amount distributed into milk appears to be very small.
Interactions
The effect of verapamil coadministration on the hepatic first pass clearance of metoprolol was investigated in dogs. Plasma concentration-time course of metoprolol enantiomers and urinary recovery of oxidative metabolites were determined after a single iv (0.51 mg/kg) and an oral (1.37 mg/kg) dose of deuterium labeled pseudoracemic metoprolol, with or without concomitant administration of racemic verapamil (3 mg/kg). Verapamil inhibited both the systemic and oral clearance of metoprolol by about 50-70%. The first pass effect of metoprolol was completely abolished after coadministration of verapamil, reflecting a marked alteration in the degree of hepatic extraction of metoprolol from intermediate to low. The hepatic clearance of metoprolol was slightly (S)-enantioselective (R/S ratio = 0.89 + or - 0.04) in control dogs. Inhibition of hepatic clearance of metoprolol by verapamil was selective towards (S)-metoprolol, such that the enantioselectivity in hepatic clearance toward (S)-metoprolol disappeared following verapamil coadministration (R/S ratio = 1.01 + or - 0.05). Urinary metabolite profiles indicated that O-demethylation and N-dealkylation were the major pathways of oxidative metabolism in the dog. alpha-Hydroxymetoprolol was a minor metabolite in urine. N-Dealkylation showed a strong preference for (S)-metoprolol, whereas O-demethylation and alpha-hydroxylation exhibited a modest selectivity toward (R)-metoprolol; hence, the slight (S)-enantioselectivity in the overall hepatic clearance. Comparison of metoprolol metabolite formation clearances in the absence or presence of verapamil coadministration showed that all three oxidative pathways were inhibited by 60-80%. The greater inhibition of hepatic clearance observed with (S)-metoprolol as compared to (R)-metoprolol was attributed to a significant (S)-enantioselective inhibition in the O-demethylation of metoprolol by verapamil.
The interaction between metoprolol and bromazepam and lorazepam was studied in 12 healthy male volunteers aged 21-37 years. Metoprolol had no significant effect on the pharmacokinetics of bromazepam or lorazepam. However, bromazepam area under the curve was 35% higher in the presence of metoprolol. Bromazepam enhanced the effect of metoprolol on systolic blood pressure but not on diastolic blood pressure or pulse rate. Lorazepam had no effect on either blood pressure or pulse. Metoprolol did not enhance the effect of bromazepam on the psychomotor tests used in this study. Metoprolol caused a small increase in critical flicker fusion threshold with lorazepam but had no effect on the other tests. Lorazepam (2 mg) was more potent than bromazepam (6 mg) in the doses used in this study. The interaction of metoprolol with bromazepam and lorazepam is unlikely to be of clinical significance. No change in dose is necessary when using these drugs together.
In contrast to early work showing inhibition of the absorption of beta adrenergic blocking drugs by antacids, subsequent studies did not confirm a reduction in the bioavailability of either atenolol or propranolol during antacid treatment; indeed, they showed an increase in the plasma concentrations of metoprolol when the drug was coadministered with an antacid.
Caffeine and metoprolol have been reported to increase peak salicylic acid concentration following aspirin administration.
For more Interactions (Complete) data for METOPROLOL (12 total), please visit the HSDB record page.
Hepatotoxicity
Metoprolol therapy has been associated with a low rate of mild-to-moderate elevations of serum aminotransferase levels which are usually asymptomatic and transient and resolve even with continuation of therapy. A few instances of clinically apparent, acute liver injury attributable to metoprolol have been reported. In view of its wide scale use, metoprolol induced liver injury is exceedingly rare. The typical liver injury associated with beta-blockers has a latency to onset of 2 to 12 weeks and a hepatocellular pattern of liver enzyme. Symptoms of hypersensitivity (rash, fever, eosinophilia) and autoantibody formation have not been reported. Reported cases due to metoprolol have included cases of acute liver failure, but ultimately all were self-limiting and resolved fairly rapidly once once drug was stopped.
Environmental Fate
TERRESTRIAL FATE: Based on a classification scheme(1), an estimated Koc value of 62(SRC), determined from a structure estimation method(2), indicates that metoprolol is expected to have high mobility in soil(SRC). Volatilization of metoprolol from moist soil surfaces is not expected to be an important fate process(SRC) given an estimated Henry's Law constant of 2.1X10⁻¹¹ atm-cu m/mole(SRC), using a fragment constant estimation method(3). Metoprolol is not expected to volatilize from dry soil surfaces(SRC) based upon an estimated vapor pressure of 2.9X10⁻⁷ mm Hg(SRC), determined from a fragment constant method(4).
AQUATIC FATE: Based on a classification scheme(1), an estimated Koc value of 62.24(SRC), determined from a structure estimation method(2), indicates that metoprolol is not expected to adsorb to suspended solids and sediment(SRC). Volatilization from water surfaces is not expected(3) based upon an estimated Henry's Law constant of 2.1X10⁻¹¹ atm-cu m/mole(SRC), developed using a fragment constant estimation method(4). An estimated pKa of metoprolol is 9.6(9), indicating that this compound will primarily exist in cation form in the environment and cations generally adsorb to organic carbon and clay more strongly than their neutral counterparts(5). According to a classification scheme(6), an estimated BCF of 1.252(SRC), from its log Kow of 1.88(7) and a regression-derived equation(8), suggests the potential for bioconcentration in aquatic organisms is low(SRC).
ATMOSPHERIC FATE: According to a model of gas/particle partitioning of semivolatile organic compounds in the atmosphere(1), metoprolol, which has an estimated vapor pressure of 2.9X10⁻⁷ mm Hg at 25 °C(SRC), determined from a fragment constant method(2), is expected to exist in both the vapor and particulate phases in the ambient atmosphere. Vapor-phase metoprolol is degraded in the atmosphere by reaction with photochemically-produced hydroxyl radicals(SRC); the half-life for this reaction in air is estimated to be 0.22 days(SRC), calculated from its rate constant of 1.58X10⁻¹⁰ cu cm/molecule-sec at 25 °C(SRC) that was derived using a structure estimation method(3).
Adverse EffectsCommon Adverse Events
Milk ConcentrationsMetoprolol is distributed into milk in a concentration about 3-4 times that of maternal plasma concentrations, but the actual amount distributed into milk appears to be very small.
Toxicity SummarySigns and Symptoms of Metoprolol Overdose
Effluent Concentrations
Effluent from sewage treatment plants (n=29) in Germany 1996-1998 contained metoprolol concentrations of 0.73 ug/l (median), 1.3 ug/l (90th percentile) and 2.2 ug/l (maximum)(1). Removal efficiency for metoprolol from sewage treatment plants was 83%(1). Metoprolol concentrations in sewage effluent in Germany were reported ranging from <0.025 to 2.20 ug/l (2). Mean concentration and loads of metoprolol in the effluent of a municipal sewage treatment plant close to Frankfurt/Main, June 24-30, 1996 were 7.2 ug/l (mean concn influent), 2.08 ug/l (mean concn effluent), 374 g/day (load influent), 108 g/day (load effluent)(3). The percent removal for metoprolol was 67% and the mean flow rate for the plant was 63,190 cu m/day(3).
Soil Adsorption/Mobility
Using a structure estimation method based on molecular connectivity indices(1), the Koc for metoprolol can be estimated to be 62(SRC). According to a classification scheme(2), this estimated Koc value suggests that metoprolol is expected to have high mobility in soil. An estimated pKa of metoprolol is 9.6(3), indicating that this compound will primarily exist in the protonated form in the environment and cations generally adsorb to organic carbon and clay more strongly than their neutral counterparts(4).
Human Toxicity Excerpts
/HUMAN EXPOSURE STUDIES/ A fatality involving a 26-year-old male who intentionally ingested approximately 10 g of metoprolol is presented. Autopsy findings revealed foreign material in the gastric content with an acute thrombosis of the left anterior descending coronary artery. Microscopic studies showed evidence of an extremely early infarct. Metoprolol concentrations in the blood, liver, gastric content, and urine are reported by both capillary gas chromatography and ultraviolet spectrophotometric analysis.
/SIGNS AND SYMPTOMS/ Acute beta blocker poisoning is characterized by depression of cardiac conduction and contractility, respiratory depression, coma, seizures, and in some patients, hypoglycemia. Symptoms occur within 1-2 hr of ingestion. /Class II Drugs: Beta-Blockers/
Artificial Pollution SourcesMetoprolol's production and use as an antihypertensive, antianginal, and antiarrhythmic drug(1) may result in its release to the environment through various waste streams(SRC).
Drug Induced Liver Injury
Benchmark Dataset for the Liver Toxicity Knowledge Base (LTKB)
metoprolol
Lopressor®
Beta blockers
5
less-DILI-concern drugs
규제 정보
FDA Requirements
Metoprolol tartrate, used as a beta adrenergic blocking agent, was approved by FDA for marketing in the United States 12/84.
The Approved Drug Products with Therapeutic Equivalence Evaluations List identifies currently marketed drug products, incl metaprolol, metoprolol tartrate, and metoprolol succinate approved on the basis of safety and effectiveness by FDA under sections 505 and 507 of the Federal Food, Drug, and Cosmetic Act. /Metaprolol, metoprolol tartrate, and metoprolol succinate/
Manufacturers, packers, and distributors of drug and drug products for human use are responsible for complying with the labeling, certification, and usage requirements as prescribed by the Federal Food, Drug, and Cosmetic Act, as amended (secs 201-902, 52 Stat. 1040 et seq., as amended; 21 U.S.C. 321-392).
안전 데이터
- 신호 어
- Warning
- 유해·위험 문구
- 암호 유해·위험 문구 위험 등급 범주 신호 어 그림 문자 P- 코드 H315
화학 및 산업
약리 정보
ATC Code
C07AB02
C07AB02
C - Cardiovascular system
QC - Cardiovascular system
Protein BindingMetoprolol is not highly bound to plasma proteins and only about 11% of the administered dose is found bound. It is mainly bound to serum albumin.
Pharmacodynamics
Administration of metoprolol in normal subjects is widely reported to produce a dose-dependent reduction on heart rate and cardiac output. This effect is generated due to a decreased cardiac excitability, cardiac output, and myocardial oxygen demand. In the case of arrhythmias, metoprolol produces its effect by reducing the slope of the pacemaker potential as well as suppressing the rate of atrioventricular conduction. The Metoprolol Atherosclerosis Prevention in Hypertensives (MAPHY) trial showed a significant improvement in sudden cardiac death and myocardial infarction when patients were given with metoprolol as compared with diuretics. As well, in clinical trials performed in 1990, metoprolol reduces mortality and re-infarction in 17% of the individuals when administered chronically after an episode of myocardial infarction.
Mechanism of Action
Metoprolol is a beta-1-adrenergic receptor inhibitor specific to cardiac cells with negligible effect on beta-2 receptors. This inhibition decreases cardiac output by producing negative chronotropic and inotropic effects without presenting activity towards membrane stabilization nor intrinsic sympathomimetics.
Beta-adenoreceptor blocking property the amount of beta1 and beta2 effect depends on the cardioselectivity of the drug. Decreased automaticity. Reduced conduction velocity and increased refractoriness in accessory bundles (Wolff- Parkinson-White syndrome). /Class II- beta-Blocking Agents/
At low doses, metoprolol is a selective inhibitor of beta 1-adrenergic receptors. Like propranolol, metoprolol inhibits response to adrenergic stimuli by competitively blocking b1-adrenergic receptors within the myocardium. Unlike propranolol, however, metoprolol blocks b2-adrenergic receptors within bronchial and vascular smooth muscle only in high doses.
The precise mechanism of metoprolol's hypotensive action has not been determined. It has been postulated that beta-adrenergic blocking agents reduce blood pressure by blocking peripheral (especially cardiac) adrenergic receptors (decreasing cardiac output), by decreasing sympathetic outflow from the CNS, and/or by suppressing renin release.
In the management of angina pectoris, the mechanism of action of metoprolol is thought to be blockage of catecholamine-induced increases in heart rate, velocity and extent of myocardial contraction, and blood pressure, which results in a net decrease in myocardial oxygen consumption.
For more Mechanism of Action (Complete) data for METOPROLOL (7 total), please visit the HSDB record page.
Biological Half-Life
The immediate release formulations of metoprolol present a half-life of about 3-7 hours.
The plasma half-life ranges from approximately 3 to 7 hours.
Metabolism/Metabolites
Metoprolol goes through significant first-pass hepatic metabolism which covers around 50% of the administered dose. The metabolism of metoprolol is mainly driven by the activity of CYP2D6 and to a lesser extent due to the activity of CYP3A4. The metabolism of metoprolol is mainly represented by reactions of hydroxylation and O-demethylation.
Metoprolol does not inhibit or enhance its own metabolism. Three main metabolites of the drug are formed by oxidative deamination, O-dealkylation with subsequent oxidation, and aliphatic hydroxylation; these metabolites account for 85% of the total urinary excretion of metabolites. The metabolites apparently do not have appreciable pharmacologic activity. The rate of hydroxylation, resulting in alpha-hydroxymetoprolol, is genetically determined and is subject to considerable interindividual variation. Poor hydroxylators of metoprolol have increased areas under the plasma concentration-time curves, prolonged elimination half-lives (about 7.6 hours), higher urinary concentrations of unchanged drug, and negligible urinary concentrations of alpha-hydroxymetoprolol compared with extensive hydroxylators. Beta-adrenergic blockade of exercise-induced tachycardia persists for at least 24 hours after administration of a single 200-mg oral dose of metoprolol tartrate in poor hydroxylators.
Controlled studies have shown that debrisoquine oxidation phenotype is a major determinant of the metabolism, pharmacokinetics and some of the pharmacological actions of metoprolol. The poor metabolizer phenotype is associated with increased plasma drug concentrations, a prolongation of elimination half-life and more intense and sustained beta blockade. Phenotypic differences have also been observed in the pharmacokinetics of the enantiomers of metoprolol. In vivo and in vitro studies have identified some of the metabolic pathways which are subject to the defect, that is alpha-hydroxylation and O-demethylation.
Metropolol is a racemic mixture of R-and S-enantiomers, and is primarily metabolized by CYP2D6.
FDA Pharmacological Classification
GEB06NHM23
METOPROLOL
Mechanisms of Action [MoA] - Adrenergic beta-Antagonists
Established Pharmacologic Class [EPC] - beta-Adrenergic Blocker
Metoprolol is a beta-Adrenergic Blocker. The mechanism of action of metoprolol is as an Adrenergic beta-Antagonist.
METOPROLOL
MeSH Pharmacological Classification
Agents used for the treatment or prevention of cardiac arrhythmias. They may affect the polarization-repolarization phase of the action potential, its excitability or refractoriness, or impulse conduction or membrane responsiveness within cardiac fibers. Anti-arrhythmia agents are often classed into four main groups according to their mechanism of action: sodium channel blockade, beta-adrenergic blockade, repolarization prolongation, or calcium channel blockade.
Drugs used in the treatment of acute or chronic vascular HYPERTENSION regardless of pharmacological mechanism. Among the antihypertensive agents are DIURETICS; (especially DIURETICS, THIAZIDE); ADRENERGIC BETA-ANTAGONISTS; ADRENERGIC ALPHA-ANTAGONISTS; ANGIOTENSIN-CONVERTING ENZYME INHIBITORS; CALCIUM CHANNEL BLOCKERS; GANGLIONIC BLOCKERS; and VASODILATOR AGENTS.
Drugs that inhibit the actions of the sympathetic nervous system by any mechanism. The most common of these are the ADRENERGIC ANTAGONISTS and drugs that deplete norepinephrine or reduce the release of transmitters from adrenergic postganglionic terminals (see ADRENERGIC AGENTS). Drugs that act in the central nervous system to reduce sympathetic activity (e.g., centrally acting alpha-2 adrenergic agonists, see ADRENERGIC ALPHA-AGONISTS) are included here.
Drugs that bind to and block the activation of ADRENERGIC BETA-1 RECEPTORS.
Absorption, Distribution and Excretion
When metoprolol is administered orally, it is almost completely absorbed in the gastrointestinal tract. The maximum serum concentration is achieved 20 min after intravenous administration and 1-2 hours after oral administration. The bioavailability of metoprolol is of 100% when administered intravenously and when administered orally it presents about 50% for the tartrate derivative and 40% for the succinate derivative. The absorption of metoprolol in the form of the tartrate derivative is increased by the concomitant administration of food.
Metoprolol is mainly excreted via the kidneys. From the eliminated dose, less than 5% is recovered unchanged.
The reported volume of distribution of metoprolol is 4.2 L/kg. Due to the characteristics of metoprolol, this molecule is able to cross the blood-brain barrier and even 78% of the administered drug can be found in cerebrospinal fluid.
The reported clearance rate on patients with normal kidney function is 0.8 L/min. In cirrhotic patients, the clearance rate changes to 0.61 L/min.
Plasma levels following oral administration of conventional metoprolol tablets, however, approximate 50% of levels following intravenous adminsitration, indicating about 50% first-pass metabolism... Elimination is mainly by biotransformation in the liver.
Metoprolol tartrate is rapidly and almost completely absorbed from the GI tract; absorption of a single oral dose of 20-100 mg is complete in 2.5-3 hours. After an oral dose, about 50% of the drug administered as conventional tablets appears to undergo first-pass metabolism in the liver. Bioavailability of orally administered metoprolol tartrate increases with increased doses, indicating a possible saturable disposition process of low capacity such as tissue binding in the liver. Steady-state oral bioavailability of extended-release tablets of metoprolol succinate given once daily at dosages equivalent to 50-400 mg of metoprolol tartrate is about 77% of that of conventional tablets at corresponding dosages given once daily or in divided doses. Food does not appear to affect bioavailability of metoprolol succinate extended-release tablets. Following a single oral dose as conventional tablets, metoprolol appears in the plasma within 10 minutes and peak plasma concentrations are reached in about 90 minutes. When metoprolol tartrate conventional tablets are administered with food rather than on an empty stomach, peak plasma concentrations are higher and the extent of absorption of the drug is increased. Following oral administration of metoprolol succinate as extended-release tablets, peak plasma metoprolol concentrations are aobut 25-50% of those attained after administration of metoprolol tartrate conventional tablets given once daily or in divided doses. Time to peak concentration is longer with extended-release tablets, with peak plasma coentrations being reached in about 7 hours following administration of such tablets. Plasma concentrations attained 1 hour after an oral dose are linearly related to metoprolol tartrate doses ranging from 50-400 mg as conventional tablets.
Tissue LocationsLiver
Cellular LocationsMembrane
Metabolite PathwaysMetoprolol Action Pathway
용도 및 제조
Uses
MEDICATION
Use (kg) in Switzerland (2009): >2500
Formulations/Preparations
Metoprolol tartrate: Beloc; Betaloc; Lopressor; Lopresor; Prelis; Seloken; Selopral; Selo-Zok.
Metoprolol succinate: Toprol-XL.
Use Classification
Pharmaceuticals
Pharmaceuticals -> Cardiovascular system -> Beta blockers -> Beta blocking agents, selective
응용 분야
역사Metoprolol was first made in 1969, patented in 1970, and approved for medical use in 1978. Metoprolol was discovered by Astra Pharmaceuticals. It is a cardioselective beta-adrenoceptor antagonist. It has a higher affinity for beta-1 receptors than for the beta-2 receptor subtype. Receptor-subtype selectivity is diminished at higher doses. Treatment of hypertension is the only indication for metoprolol presently sanctioned by the Food and Drug Administration.
용도rac Metoprolol is a β1 selective aryloxypropanolamine andrenergic antagonist. Used in the treatment of a variety of cardiovascular disorder.
상·하류 제품 정보
상류 원료
공급사50 곳
北京华美互利生物化工010-56205725 · [email protected]
江苏永健医药科技有限公司17701422015
广州隽沐生物科技股份有限公司020-36607679; 13502246435 · [email protected]
Shenzhen Monkono Technology Co.,Ltd+86-17063441314 · [email protected]
南京林叶化学试剂有限公司13376084917 13376082704 · [email protected]
江苏艾康生物医药研发有限公司025-025-66113011 15955137747 · [email protected]
Sinoway Industrial co., ltd.+86-0592-5800732 +86-13806035118 · [email protected]
河北枫嘉新材料科技有限公司+86-0311-87836622 +86-18712993135 · [email protected]
淮安嘉目生物科技有限公司0517-83187139 18205232085 · [email protected]
Syntechem Co.,Ltd[email protected]
湖北丹鼎医药科技有限公司17701422019 17701422019 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
广东元丰化学试剂有限公司0751-2829979 13318593351 · [email protected]
北京亿思研科技开发中心010-56645598 13366904824 · [email protected]
梯希爱(上海)化工贸易有限公司021-61109150 · [email protected]
希瓦生物科技(广州)有限公司13268215580 · [email protected]
淄博容纳生物科技有限公司+86-86-13583358881 +8618560316533 · [email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
上海艾梯西生物科技有限公司18721763493
上海景颜化工科技有限公司13817811078 · [email protected]
上海常丰生物医药科技有限公司+86-021-61727342 13611721451 · [email protected]
上海昊锐医药生物科技有限公司021-58388037;21-58388037 13472507714 · [email protected]
金克隆(北京)生物技术有限公司400-910-1997 15330005590 · [email protected]
南京生利德生物科技有限公司025-57798810 18652991625 · [email protected]
湖北鑫源顺医药化工有限公司13971561712, 13995564702, 027-50664929 · [email protected]
陕西缔都医药化工有限公司029-81024372 17792795018 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
普善实业(陕西)有限公司029-81310890 18165209495 · [email protected]
上海昕凯医药科技有限公司21-619849051-1 18521059765 · [email protected]
河南誉康卓宁进出口有限公司13393721940 · [email protected]
sgtlifesciences pvt ltd+91-8790379245 · [email protected]
上海德欣致远生物技术有限公司58088081 18317173152 · [email protected]
南京艾比克斯生化科技有限公司025-87193546 18652950785 · [email protected]
南京熙朗化工产品有限公司18936048580 · [email protected]
凯立德生物医药技术(上海)有限公司021-58180488 · [email protected]
山东小野化学股份有限公司0539-6362799 20)
Shanghai Acmec Biochemical Technology Co., Ltd.+86-18621343501 · [email protected]
Shaanxi Didu New Materials Co. Ltd+86-86-17392712779 +86-13289823923 · [email protected]
杭州洁汉化工有限公司+86-571-86217390; +8618058761490 · [email protected]
上海易恩化学技术有限公司400-400-1332688 18019345275 · [email protected]
厦门盈融达化工有限公司+86-0592-6210733 · [email protected]
career henan chemical co+86-0371-86658258 · [email protected]
上海吉至生化科技有限公司021-4009004166/18616739031 18616739031 · [email protected]
海蔚化学86-21-51086038 · [email protected]
Huadong Medicine (Xi'an)Bodyguard Pharmaceutical Co.,Ltd.+86-029-86185165 +86-18629664246 · [email protected]
武汉福鑫化工有限公司027-59207852 13308628970 · [email protected]
常州翔龙医药科技有限公司18661161657 · [email protected]
默科催化材料科技(南京)有限公司13851755987 · [email protected]
Nanjing Doge Biomedical Technology Co., Ltd+86-25-58227606 +86-15305155328 · [email protected]
山西诺诚生物科技有限公司17835231871 · [email protected]
관련 반응
3건


연결된 노트
불러오는 중…