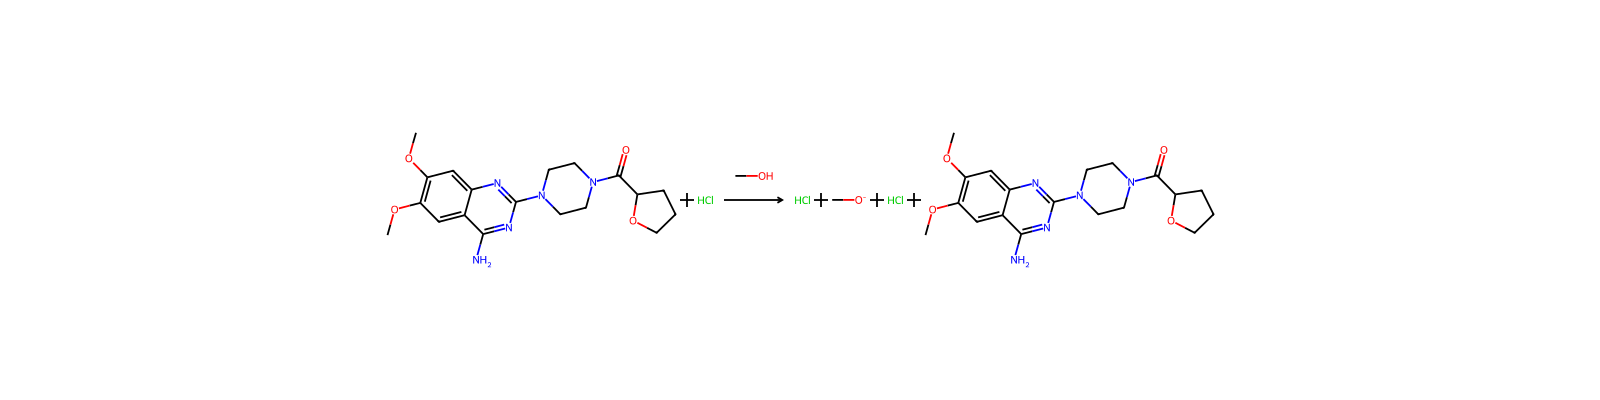
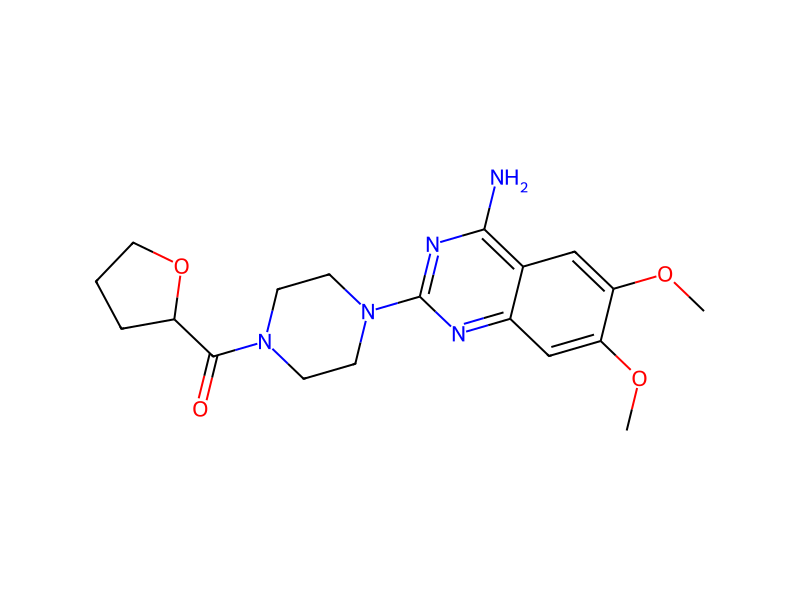
기본 정보
- 표준 SMILES
COc1cc2nc(N3CCN(C(=O)C4CCCO4)CC3)nc(N)c2cc1OC- InChIKey
VCKUSRYTPJJLNI-UHFFFAOYSA-N- 분자식
- C19H25N5O4
- 평균 분자량
- 387.4 g/mol
- 단동위원소 질량
- 387.19065428
개요
Terazosin is a member of furans, a member of piperazines, a member of quinazolines and a primary amino compound. It has a role as an antineoplastic agent, an antihypertensive agent and an alpha-adrenergic antagonist.
이름 및 식별자
- 우선 이름
- Terazosin
- IUPAC
- [4-(4-amino-6,7-dimethoxyquinazolin-2-yl)piperazin-1-yl]-(oxolan-2-yl)methanone
- 영어명
- Terazosin
- 분자식
- C19H25N5O4
- 분자량
- 387.43
이름 및 동의어
terazosin63590-64-7TerazosineFosfomicTerazosinaBlavinFlumarcTerazosinumTerazosabb1-(4-Amino-6,7-dimethoxy-2-quinazolinyl)-4-((tetrahydro-2-furanyl)carbonyl)piperazineHytrinexVicard
이름 더 보기
TERAZOSIN HCLUrodieHYTRINerazosinarbonyl)-CID 663211Vasomet:VicardHytrin:Hytrinex
8L5014XET7CHEBI:9445DTXSID3023639Piperazine, 1-(4-amino-6,7-dimethoxy-2-quinazolinyl)-4-((tetrahydro-2-furanyl)carbonyl)-6,7-dimethoxy-2-(4-((oxolan-2-yl)carbonyl)piperazin-1-yl)quinazolin-4-amine6,7-dimethoxy-2-(4-(oxolane-2-carbonyl)piperazin-1-yl)-3,4-dihydroquinazolin-4-imine6,7-dimethoxy-2-[4-(oxolane-2-carbonyl)piperazin-1-yl]-3,4-dihydroquinazolin-4-imine6,7-dimethoxy-2-{4-[(oxolan-2-yl)carbonyl]piperazin-1-yl}quinazolin-4-amine
데이터베이스 식별자
- CAS
63590-64-7- PubChem CID
- 5401
- DTXSID
DTXSID3023639- ChEMBL
CHEMBL611- ChEBI
CHEBI:9445- UNII
- 8L5014XET7
- EC Number
- 613-265-8
- Nikkaji
- J19.669J
물성
구조 계산 물성
- XLogP
- 1.4
- 극성 표면적
- 103 Ų
- 수소 결합 공여자 수
- 1
- 수소 결합 수용자 수
- 8
- 회전 가능 결합 수
- 4
- 무거운 원자 수
- 28
- 형식 전하
- 0
- 복잡도
- 544
실험 및 물리화학적 성질
Drugs
Pharmaceuticals -> Antihypertensives
Pharmaceuticals
LogP
1
1.14
Solubility1.50e+00 g/L
Human Drugs
Breast Feeding; Lactation; Milk, Human; Adrenergic alpha-Antagonists; Antihypertensive Agents
Pharmaceuticals
Melting Point
271-274
273 °C
Physical DescriptionSolid
Collision Cross Section189.79 Ų [M+Na]+ [CCS Type: TW; Method: calibrated with polyalanine and drug standards]
물리화학적 성질
- 녹는점
- 281 · 281-283°C
- 끓는 점
- 664.5 · 664.5±65.0 °C(Predicted)
- 밀도
- 1.332 · 1.332±0.06 g/cm3(Predicted)
- 저장 조건
- -20 °C · -20°C Freezer
- 용해도
- 2 O: · H2O: 25 mg/mL
- 물리적 상태
- 가루
- 산도 계수 (pKa)
- pKa (0.1N NaOH): 7.1(at 25℃)
- 색상
- 흰색에서 황백색까지
- 수용성
- 30.6 mg/L · 30.6mg/L(22.5℃)
- BCS Class
- 1 · 1/3
- InChIKey
- VCKUSRYTPJJLNI-UHFFFAOYSA-N
화학적 성질
White to Off-White Crystalline Powder
안전 및 규제
GHS 분류
GHS Classification
This chemical does not meet GHS hazard criteria for 2.3% (1 of 44) of reports.
Warning
H302 (97.7%): Harmful if swallowed [Warning Acute toxicity, oral]
P264, P270, P301+P317, P330, and P501 (click each P-code to see the statement)
Aggregated GHS information provided per 44 reports by companies from 3 notifications to the ECHA C&L Inventory.
유해성 정보
Regulatory InformationStatus: Active Update: 25-07-2018 https://echa.europa.eu/registration-dossier/-/registered-dossier/25502
Hazard Classes and CategoriesAcute Tox. 4 (97.7%)
독성 정보
Treatment
Should overdosage of Terazosin lead to hypotension, support of the cardiovascular system is of first importance. Restoration of blood pressure and normalization of heart rate may be accomplished by keeping the patient in the supine position. If this measure is inadequate, shock should first be treated with volume expanders. If necessary, vasopressors should then be used and renal function should be monitored and supported as needed. Laboratory data indicate that Terazosin is highly protein bound; therefore, dialysis may not be of benefit. (L1712)
Health EffectsHypotension, palpitations, postural hypotension, syncope, peripheral edema, weight gain, dyspnea, nasal congestion/rhinitis, impotence.
Hepatotoxicity
Terazosin has been associated with a low rate of serum aminotransferase elevations that in controlled trials was no higher than with placebo therapy. These elevations were transient and did not require dose modification. Instances of serum enzyme elevations, but no instances of clinically apparent acute liver injury with jaundice due to terazosin, have been published. Furthermore, product labels do not include discussion of hepatic toxicity. Cholestatic hepatitis and jaundice have been reported with other alpha-adrenergic blockers. Thus, acute symptomatic liver injury due to terazosin must be exceedingly rare if it occurs at all.
Adverse EffectsTerazosin is generally well-tolerated. Many adverse effects of terazosin are explainable due to its blockade of alpha-1 adrenergic receptors.
Exposure RoutesOral. Essentially completely absorbed in man (90% bioavailability).
Toxicity Summary
Overdose of terazosin may lead to hypotension, and standard life-support protocols should be in place for instances of hemodynamic instability. There are no specific antidotes for terazosin toxicity. Vasopressors may be used to support physiologic blood pressure parameters in the event of terazosin overdose. Terazosin is long-acting, with an elimination half-life of approximately 12 hours, and is highly protein-bound. Elimination is via renal excretion (40%) and excretion of feces (60%).
Terazosin selectively and competitively inhibits vascular postsynaptic alpha(1)-adrenergic receptors, resulting in peripheral vasodilation and a reduction of vascular resistance and blood pressure. Unlike the nonselective alph-adrenergic blockers phenoxybenzamine and phentolamine, terazosin does not block presynaptic alpha(2)-receptors and, hence, does not cause reflex activation of norepinephrine release to produce reflex tachycardia.
Signs and SymptomsAsthenia, postural hypotension, dizziness, somnolence, nasal congestion/rhinitis.
Carcinogen ClassificationNo indication of carcinogenicity to humans (not listed by IARC).
Drug Induced Liver Injury
Drug-Induced Liver Injury Severity and Toxicity (DILIst)
terazosin
DILI Negative
Oral
DOI:10.1016/j.drudis.2019.09.022
Effects During Pregnancy and Lactation◉ Summary of Use during Lactation
Toxicity DataLD50: 259.3mg/kg (parental-intravenous, Mouse) (A308)
안전 데이터
- wgk
- 3
- rtecs
- TK8044925
- risk_code
- 22-36/37/38
- hazard_code
- Xn,Xi
- safety_code
- 26-36
화학 및 산업
약리 정보
ATC Code
G04CA03
G - Genito urinary system and sex hormones
Protein Binding90-94%.
PharmacodynamicsTerazosin is a quinazoline derivative alpha-1-selective adrenergic blocker.
Mechanism of Action
Terazosin is selective for alpha-1-adrenoceptors but not their individual subtypes. Inhibition of these alpha-1-adrenoceptors results in relaxation of smooth muscle in blood vessels and the prostate, lowering blood pressure and improving urinary flow. Smooth muscle cells accounts for roughly 40% of the volume of the prostate and so their relaxation reduces pressure on the urethra. It has also been shown that catecholamines induce factors responsible for mitogenesis and alpha-1-adrenergic receptor blockers inhibit this effect. A final long term mechanism of terazosin and other alpha-1-adrenergic receptor blockers is the induction of apoptosis of prostate cells. Treatment with terazosin enhances the expression of transforming growth factor beta-1 (TGF-beta1), which upregulates p27kip1, and the caspase cascade.
Biological Half-LifeTerazosin has a mean half life 12 hours though this can be as high as 14 hours in patients over 70 years and as low as 11.4 hours in patients 20 to 39 years old.
Metabolism/Metabolites
The majority of terazosin is hepatically metabolized. The metabolites recovered include 6-O-demethyl terazosin, 7-O-methyl terazosin, a piperozine derivative, and a diamine derivative.
Hepatic. One of the four metabolites identified (piperazine derivative of terazosin) has antihypertensive activity. Route of Elimination: Approximately 10% of an orally administered dose is excreted as parent drug in the urine and approximately 20% is excreted in the feces. Half Life: 12 hours
FDA Pharmacological Classification
8L5014XET7
TERAZOSIN
Mechanisms of Action [MoA] - Adrenergic alpha-Antagonists
Established Pharmacologic Class [EPC] - alpha-Adrenergic Blocker
Terazosin is an alpha-Adrenergic Blocker. The mechanism of action of terazosin is as an Adrenergic alpha-Antagonist.
TERAZOSIN
MeSH Pharmacological Classification
Drugs that bind to and block the activation of ADRENERGIC ALPHA-1 RECEPTORS.
Drugs used in the treatment of urological conditions and diseases such as URINARY INCONTINENCE and URINARY TRACT INFECTIONS.
Absorption, Distribution and Excretion
Approximately 90%.
Approximately 10% of the oral dose is excreted unchanged in the urine and approximately 20% is excreted in the feces. 40% of the total dose is eliminated in urine and 60% of the total dose is eliminated in the feces.
25L to 30L.
Plasma clearance is 80mL/min and renal clearance is 10mL/min.
Cellular LocationsMembrane
용도 및 제조
Uses
Use (kg; approx.) in Germany (2009): >75
Terazosin is indicated for the treatment of symptomatic benign prostatic hyperplasia (BPH). There is a rapid response, with approximately 70% of patients experiencing an increase in urinary flow and improvement in symptoms of BPH when treated with terazosin. The long-term effects of terazosin on the incidence of surgery, acute urinary obstruction or other complications of BPH are yet to be determined. Terazosin tablets are also indicated for the treatment of hypertension. Terazosin tablets can be used alone or in combination with other antihypertensive agents such as diuretics or beta-adrenergic blocking agents.
Use ClassificationPharmaceuticals
응용 분야
용도Terazosin is used for the same indications as is prazosin; however, it has the advantage of being able to be used once a day.
상·하류 제품 정보
상류 원료
공급사50 곳
北京华美互利生物化工010-56205725 · [email protected]
陕西缔都新材料有限公司81124267 17392282731 · [email protected]
湖北威德利化学试剂有限公司181-6332-1995 18062128043 · [email protected]
Shaanxi LonierHerb Bio Technology Co Ltd+86-86-+86-86-029-87551862 15002946897 · [email protected]
山东海舟生物工程有限公司130-0567-0367 13006570367 · [email protected]
广州佳途科技股份有限公司81960175 18933936954 · [email protected]
Hong Kong Tiansheng New Material Trading Co., Ltd+8617320695765 · [email protected]
杭州品高化工有限公司0571-87658025 · [email protected]
上海毕得医药科技股份有限公司400-1647117 13681763483 · [email protected]
杭州摩库生物医药科技有限公司+86-057181025280; +8617767106207 · [email protected]
Hebei shuoxi biotechnology co. LTD+8613081092107
湖北研科时代科技有限公司15780669880 · [email protected]
LGM Pharma1-(800)-881-8210 · [email protected]
武汉易泰科技有限公司上海分公司18930552037 · [email protected]
安耐吉化学&3A(安徽泽升科技有限公司)021-58432009 400-005-6266 · [email protected]
广东元丰化学试剂有限公司0751-2829979 13318593351 · [email protected]
广州市亿邦医药科技有限公司+86 (20) 28996708,29078958,28139708,29076128,28133708,28139728,28139738,28133718,021-31663278,021-31663578,021-60538387
江苏艾康生物医药研发有限公司025-5885952 15955137747 · [email protected]
United Life Science020-82099279 18988941402 · [email protected]
西安泽邦生物科技有限公司[email protected]
MedBio脉铂医药021-69568360 18916172912 · [email protected]
上海沛灵生物科技有限公司13127581762 13127581762 · [email protected]
上海隆盛化工有限公司58099637 13585536065 · [email protected]
MedChemexpress LLC021-58955995 · [email protected]
湖北魏氏化学试剂股份有限公司17771898297 13125137661 · [email protected]
NANJING YINGWEN BIOTECHNOLOGY CO LTD+86-13382787392 · [email protected]
孝感深远化工有限公司15527621225; 15527621225 · [email protected]
玺标(上海)科技有限公司18512111473 18512111473 · [email protected]
上海遐瑞医药科技有限公司+86 21 61551611
深圳振强药物研发有限公司0755-66853366 13670046396 · [email protected]
武汉鹏胤药业有限公司13163333255 · [email protected]
湖北威德利化学试剂有限公司186-02735115 18602735115 · [email protected]
北京奥秘佳得医药科技有限公司+86-13522808617 · [email protected]
杭州杰恒化工有限公司0571-87396432 · [email protected]
常州翔龙医药科技有限公司18915873328 18915873328 · [email protected]
广州市慈铭生物科技有限公司020-38082199,29065168,38082986,29878298,29866629,4000192398
上海孚一生物科技有限公司+86 (21) 61124340
凯试(上海)科技有限公司021-50135380 · [email protected]
池州凯隆进出口贸易有限公司[email protected]
Sigma-Aldrich西格玛奥德里奇(上海)贸易有限公司021-61415566 800-8193336 · [email protected]
湖北威德利化学科技有限公司027-83989310 18627915365
厦门志信化学有限公司+86-5922680277 +86-13806087780 · [email protected]
上海阿拉丁生化科技股份有限公司6206333 13167063860 · [email protected]
风咏生物(AbMole)021-10000000 13000000000 · [email protected]
陕西缔都医药化工有限公司+86-29-81139210 +86-17392587031 · [email protected]
上海源叶生物科技有限公司13636370518 · [email protected]
上海陶术生物科技股份有限公司13564774135 · [email protected]
上海麦克林生化科技股份有限公司50706066 15221275939 · [email protected]
成都标样生物科技有限公司028-81700200 13308200041 · [email protected]
常州合晶化工有限公司85528066 13775048983 · [email protected]
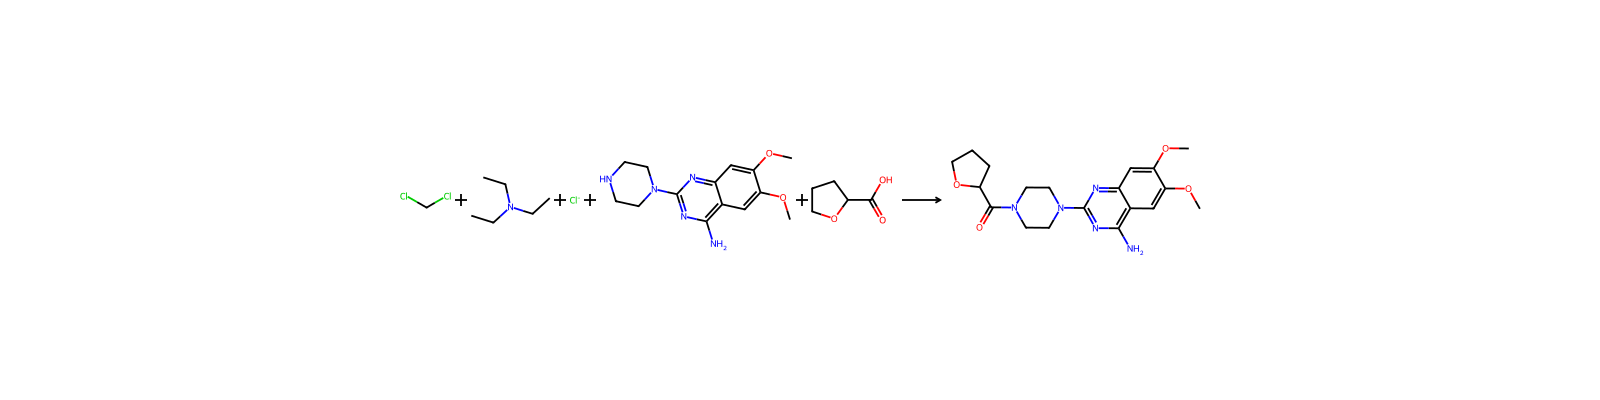
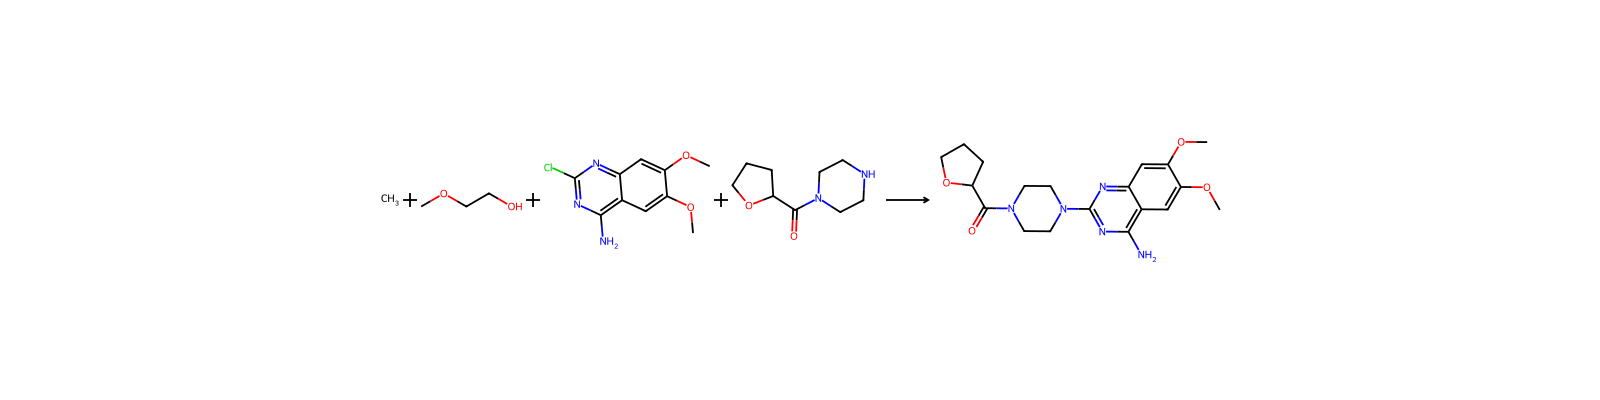
관련 반응
24건


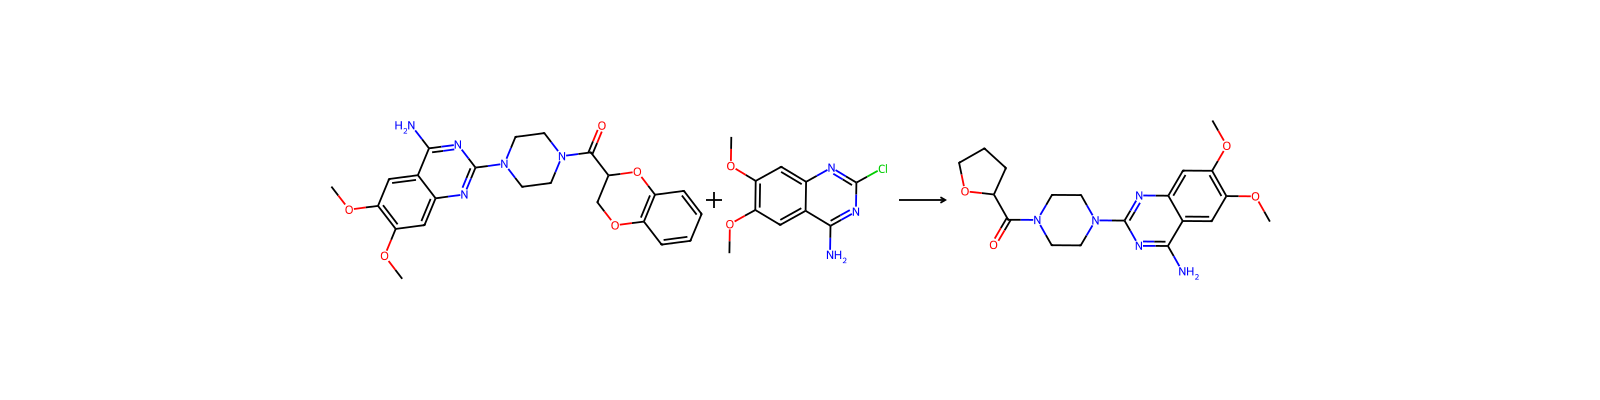

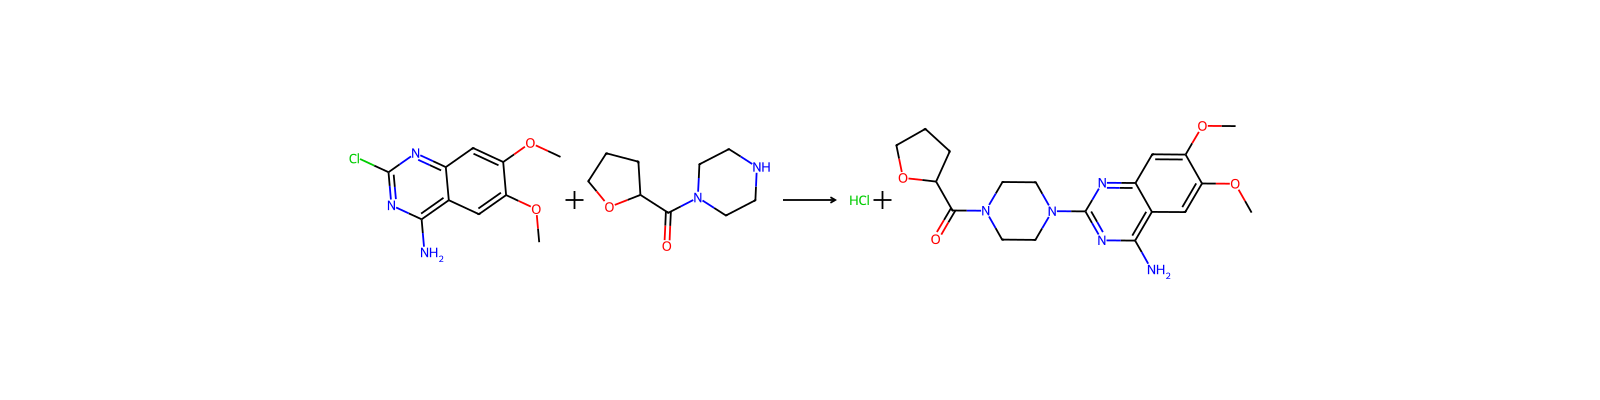
연결된 노트
불러오는 중…